



 Chat with AI
Exam 3: Office/Health Center

Exam 1: Emergency Department218 Questions
Exam 2: In-patient Facilities128 Questions
Exam 3: Office/Health Center900 Questions
Select questions type


A 55-year-old man comes to the physician due to myalgias, arthralgias, and weight loss. He has not felt well for 2 years. Over that time, he has experienced 4 episodes of sinusitis that responded poorly to treatment and required prolonged courses of antibiotics for symptom resolution. During the last 6 months, the patient has experienced diffuse aches. He has pain that migrates from his knees to his shoulders and wrists and has also lost 4.5 kg (10 lb). He has no history of hypertension, diabetes mellitus, or chronic kidney disease.
His blood pressure is 138/90 mm Hg. A small amount of crusted blood is present in one nostril. There are no other significant physical findings.
Laboratory results are as follows:
 Chest CT reveals two 2-3 cm nodules in the left upper lobe. Serum anti-neutrophil cytoplasmic antibodies are negative.
Which of the following would be the best method to establish the diagnosis?
Chest CT reveals two 2-3 cm nodules in the left upper lobe. Serum anti-neutrophil cytoplasmic antibodies are negative.
Which of the following would be the best method to establish the diagnosis? (Multiple Choice)
4.9/5  (76)
(76) A 44-year-old woman with celiac disease comes to the physician with complaints of bone pain in her lower back and extremities. She followed a gluten-free diet for the first 5 years after diagnosis but has not done so for the last 2 years. The patient has 2 or 3 loose bowel movements a day. She also complains of weakness and low energy.
Physical examination shows no bony deformities. Her conjunctivae are pale. There is no organomegaly, and the remainder of the examination is unremarkable.
Which of the following is the most likely finding in this patient's initial laboratory workup?

(Multiple Choice)
4.9/5 (88)
(88) A 32-year-old primigravida at 24 weeks gestation is evaluated for excessive tiredness. The patient feels sleepy throughout the day and keeps dozing off at work. Her overnight sleep is poor and she does not feel refreshed on awakening in the morning. She also reports occasional morning headaches. The patient had mild nausea during the first trimester but her pregnancy has otherwise been uneventful. She has no known medical issues and her only medication is prenatal vitamins. The patient drinks alcohol occasionally but stopped after conception and does not use tobacco or illicit drugs.
Blood pressure is 142/90 mm Hg, pulse is 98/min, respirations are 18/min, and SaO2 is 96% on room air. The patient's pre-pregnancy weight was 76 kg (167.6 lb) with BMI of 28 kg/m2; she has gained 7 kg (15.4 lb) during the pregnancy. Examination shows normal thyroid gland, prominent jugular venous pulse estimated at 2 cm above the sternal angle, clear lungs, grade 2/6 systolic ejection murmur, and gravid uterus appropriate for gestation. There is mild ankle edema. Fetal heart rate is within normal limits.
Laboratory studies are significant for hemoglobin of 11.4 g/dL and trace protein in urine.
Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.8/5 (88)
(88) A 30-year-old woman comes to the physician with knee swelling and pain after twisting her knee while playing soccer 2 days ago. She is an avid soccer player and has increased her game time over the last couple of weeks. The patient was initially unable to bear weight on the knee but was able to walk later that day. She has iced the knee and taken ibuprofen, with some relief.
Physical examination shows a small effusion with medial joint line tenderness to palpation. Passive flexion and extension of the knee result in a painful click in mid-extension. The patient is unable to squat due to significant pain as she attempts the maneuver. Valgus and varus stress tests are normal. Anterior drawer test shows no signs of knee instability.
Plain radiographs of the knee are normal.
Which of the following is the most likely diagnosis?
(Multiple Choice)
5.0/5 (84)
(84) A 47-year-old previously healthy man comes to the office due to 3 days of abdominal discomfort, nausea, and diarrhea. He has had 10-12 small-volume stools per day with no visible blood or mucus. He has had no fever or vomiting but did have generalized aches and a sense of being unwell prior to the onset of diarrhea. The patient has not taken any antibiotics or traveled recently. He ate at an outdoor cookout 2 days before he developed symptoms.
Vital signs are within normal limits with no orthostatic changes. Examination shows moist mucous membranes. Mild periumbilical tenderness is present with no guarding or rebound tenderness. Bowel sounds are increased. Rectal examination reveals no blood.
Which of the following is the most likely cause of this patient's symptoms?
(Multiple Choice)
5.0/5 (84)
(84) A 19-year-old woman comes to the physician with a 1-week history of malaise and joint pains. She also has mild shortness of breath. The patient initially developed left elbow pain and swelling but now has pain in the right knee and ankle. She emigrated from Thailand 6 months ago and has resided with family members in New York City, none of whom have been ill.
Her temperature is 38 C (100.4 F), blood pressure is 104/64 mm Hg, pulse is 92/min, and respirations are 20/min. Lungs are clear bilaterally. Cardiac examination reveals a blowing 3/6 holosystolic murmur at the apex. The right knee and left elbow are mildly swollen and tender. There are palpable subcutaneous nodules on the extensor surface of both arms.
Erythrocyte sedimentation rate is 100 mm/hr and blood cultures are negative.
Which of the following is most useful in confirming the diagnosis?
(Multiple Choice)
4.9/5 (70)
(70) A 43-year-old executive comes to the office for a follow-up appointment. He has been traveling between the United States and Switzerland for business every 2 months. Each time he flies to Switzerland, he has difficulty adjusting to the time difference for 4-5 days afterward and is unable to sleep well at night. The patient gets irritable during work hours due to lack of sleep at night and inability to control his sleepiness during the day. He is worried that his colleagues in Switzerland have noticed his fatigue and that his work performance has suffered. He has no other medical conditions and takes no daily medications.
Vitals signs are normal. Examination shows no abnormalities.
Apart from advising exercise and exposure to bright light during the day, which of the following is the best recommendation for improving this patient's jet lag?
(Multiple Choice)
4.8/5 (90)
(90) A 65-year-old woman recently diagnosed with mild cognitive impairment seeks advice about prevention of dementia. The patient has glaucoma, osteoarthritis, type 2 diabetes mellitus, and osteoporosis. She lives alone and performs all activities of daily living independently. The patient is troubled by her memory impairment but compensates by writing things down and making lists. She has no depression and scores 25/30 on the Mini-Mental Status Examination. The patient's sister developed dementia at age 69 and was recently admitted to a long-term care facility. Her aunt suffered from dementia and died of pneumonia at age 78.
Blood pressure is 122/70 mm Hg and pulse is 77/min. BMI is 26 kg/m2. General physical examination, including neurologic examination, shows no abnormalities.
Complete blood count, comprehensive metabolic panel, serum thyroid-stimulating hormone, and vitamin B12 level are all within normal limits.
Which of the following is the most appropriate recommendation for this patient?
(Multiple Choice)
4.7/5 (82)
(82) A 78-year-old woman is brought to the office for evaluation of a right heel wound. She had an ischemic stroke a year ago with residual right hemiplegia and has lived in a nursing home facility since. The patient also has oropharyngeal dysphagia and is fed through a gastrostomy tube. For the past several weeks, she has had a gradually enlarging right heel ulcer She has no pain sensation in the right leg and has had no fever or foul-smelling drainage. Her other medical problems include hypertension, type 2 diabetes mellitus, and coronary artery disease.
Right heel examination shows a 2-cm ulcer with thick, firm eschar. There is no crepitus or surrounding redness. The lower-extremity pulses are weak.
Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.7/5 (72)
(72) A 22-year-old woman comes to the urgent care clinic with a painful, gritty sensation in her right eye, eyelid swelling, and photophobia for the past 2 days. She has been studying for college exams and initially attributed her symptoms to fatigue. The patient wears contact lenses for myopia but has been using glasses since this morning.
Physical examination shows conjunctival injection and upper eyelid swelling. Fluorescein staining shows a 6-mm corneal defect. Visual acuity is normal bilaterally.
Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (88)
(88) A 52-year-old woman comes to the office to discuss an elevated calcium level. Mild hypercalcemia was recently noted on a serum chemistry panel performed to manage her chronic antihypertensive therapy. The patient has no musculoskeletal symptoms other than occasional low back pain, and she walks 2-3 miles every day. She experienced menopause 2 years ago but has minimal vaginal dryness and no hot flashes. Current medications include lisinopril and a daily over-the-counter calcium and vitamin D supplement. Her mother suffered a hip fracture at age 60, and her father died of prostate cancer. The patient does not use tobacco, alcohol, or illicit drugs.
Blood pressure is 144/91 mm Hg and pulse is 68/min. BMI is 25 kg/m2. Physical examination is unremarkable.
Laboratory results are as follows:
 Repeat serum calcium is 10.9 mg/dL and parathyroid hormone level is 89 pg/mL (normal: 10-65). X-rays of the thoracic and lumbar spine reveal no fractures. DXA reveals T-scores as follows:
 Which of the following is the most appropriate next step in management of this patient?
Repeat serum calcium is 10.9 mg/dL and parathyroid hormone level is 89 pg/mL (normal: 10-65). X-rays of the thoracic and lumbar spine reveal no fractures. DXA reveals T-scores as follows:
Which of the following is the most appropriate next step in management of this patient? (Multiple Choice)
4.8/5 (79)
(79) A 36-year-old man comes to the physician with daily epigastric pain for past 3 months. He has no vomiting, diarrhea, or weight loss. He has suffered from painful ulcers in his mouth once a year since he was a teenager. His only medications are a daily multivitamin and occasional ibuprofen for headaches. He does not use tobacco, alcohol, or illicit drugs. The patient emigrated from Taiwan 3 years ago. There is no family history of gastrointestinal malignancy or inflammatory bowel disease.
Examination is remarkable for mild epigastric tenderness. Stool is positive for occult blood.
His hemoglobin is 12.9 g/dL. Stool Helicobacter pylori antigen testing is positive. An upper endoscopy reveals no esophageal lesions and a solitary 1.4-cm ulcer with well demarcated edges in the antrum of the stomach.
Which of the following is the best next step in managing this patient?
(Multiple Choice)
4.9/5 (80)
(80) A 67-year-old man comes to the office for routine follow-up. He has a history of hypertension, osteoarthritis, and chronic aortic regurgitation. He reports that he is doing well overall and plays doubles tennis three times a week for exercise, which he does without any chest pain or pressure. He denies shortness of breath, orthopnea, paroxysmal nocturnal dyspnea, or edema. His medications include aspirin, nebivolol, simvastatin, chlorthalidone, and acetaminophen.
His blood pressure is 128/60 mm Hg and pulse is 67 /min. His BMI is 27 kg/m2. Cardiovascular examination reveals a normal S1 and S2. There is 2/6 mid-systolic murmur at the right upper sternal border followed by a high-pitched diastolic decrescendo murmur best heard at the left upper sternal border. The intensity of the diastolic murmur is increased with handgrip. His peripheral pulses are 3+ bilaterally.
A transthoracic echocardiogram demonstrates normal left ventricular size and function. The aortic valve is calcified and demonstrates mild stenosis (mean gradient = 13 mm Hg) with moderate aortic regurgitation. When compared to the echocardiogram from two years ago, both the aortic stenosis and regurgitation are worse.
Which of the following would be the most appropriate next step?
(Multiple Choice)
4.8/5 (85)
(85) A 68-year-old man comes to the physician because of lower extremity edema. His edema has been present for the last six months, but it has worsened lately. He denies chest pain or pressure, although he reports some exertional shortness of breath and a dry cough that occurs mostly at night. He denies any recent change in diet or medications. His other medical problems include chronic obstructive pulmonary disease and hyperlipidemia. His current medications include albuterol/ipratropium inhaler, simvastatin, and aspirin. He has smoked 1 pack of cigarettes per day for the last 48 years, but he denies alcohol or illicit drug use.
His blood pressure is 140/75 mm Hg in both arms, pulse is 60/min, and respirations are 14/min. He is in no acute distress. His jugular veins are distended with the peak of the 'a' wave poorly visualized at 90 degrees. There is a sustained parasternal lift best felt at the left lower parasternal border. There is a normal S1 with a loud S2. There is a holosystolic murmur best heard at the left sternal border that increases with inspiration. The lungs are clear bilaterally. The liver is slightly enlarged. There is 2+ pitting edema to the thighs bilaterally.
A 12 lead ECG is shown in this exhibit. 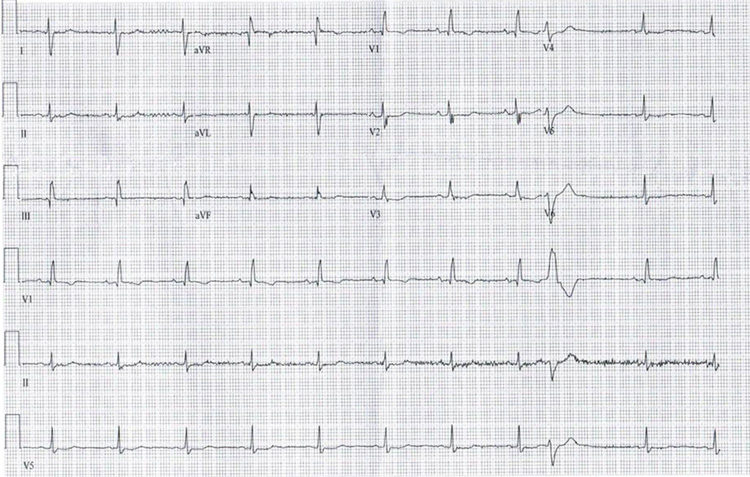 Which of the following will most likely be seen on echocardiography?
 (Multiple Choice)
4.8/5 (83)
(83) A 20-year-old man with a history of asthma comes to the office due to a marked increase in cough, wheezing, and sputum production. The asthma is usually very well controlled on mometasone-formoterol 1 puff twice daily, but over the past week, the patient has used his inhaler several times daily for chest tightness, cough, and wheezing. These symptoms started 5 days ago, when he "felt lousy" and had muscle aches; cough; nasal congestion; thick, yellowish nasal discharge; sore throat; and fever. The fever and sore throat improved, but the cough and nasal congestion have persisted. The patient has no headache. He can barely sleep due to frequent coughing.
The patient is afebrile. Pulse is 82/min and respirations are 14/min. Pulse oximetry shows 97% on room air. Physical examination shows a healthy-appearing man who is not in acute respiratory distress. There is no sinus tenderness, but some postnasal drip is seen in the oropharynx. Lung examination shows good air entry and diffuse wheezing. The remainder of the physical examination is normal.
Which of the following is the most appropriate treatment for this patient?
(Multiple Choice)
4.9/5 (83)
(83) A 72-year-old man is evaluated for progressive exertional dyspnea over the last 2-3 years. His current exercise tolerance is walking one block on flat ground, and he gets very short of breath when climbing stairs. He takes amlodipine for hypertension.
Blood pressure is 154/90 mm Hg, pulse is 88/min, and oxygen saturation at rest is 96%. BMI is 32 kg/m2. Breath sounds are decreased at the lung bases with scattered crackles. The remainder of the examination is within normal limits.
Transthoracic echocardiogram shows moderate left atrial enlargement, mild left ventricular hypertrophy, normal valves, and left ventricular ejection fraction of 60%. Coronary angiography shows no obstructive coronary disease. Right heart catheterization shows pulmonary capillary wedge pressure of 28 mm Hg and pulmonary artery pressure of 70/30 mm Hg (mean pressure 42 mm Hg).
Which of the following is the best initial management for this patient?
(Multiple Choice)
4.9/5 (80)
(80) A 38-year-old man comes to the office due to progressive shortness of breath for the past several months. The patient gets winded when carrying groceries up a flight of stairs and when walking 2-3 city blocks. He also has a frequent cough productive of thick yellow sputum, especially in the morning. The patient has no other medical conditions. He says he smoked cigarettes occasionally during college, but recently he has been smoking 3 or 4 cigarettes daily after he began work at a new company 2 years ago. The patient does not use alcohol or illicit drugs.
Blood pressure is 124/72 mm Hg and pulse is 84/min. Oxygen saturation is 96% on room air. Lung auscultation reveals occasional expiratory wheezes and rhonchi. There are no heart murmurs. Chest x-ray reveals hyperinflated lungs. Spirometry shows the following:
 Which of the following additional testing is most appropriate for this patient?
 (Multiple Choice)
4.8/5 (71)
(71) A 68-year-old woman comes to the office due to worsening pain and stiffness in her hands for the past several months. The patient initially had pain in the fingers and at the base of the thumb only after prolonged gardening or sewing, but she is now having difficulty with daily activities such as buttoning her blouse or holding her dog's leash. Her fingers are stiff in the morning, with gradual improvement after 15-20 minutes of use. The patient has experienced no fever or swelling in the hands. She has attempted treatment of her pain with stretching exercises and over-the-counter acetaminophen without relief. Medical history is notable for hypertension, for which she takes amlodipine and lisinopril. The patient occasionally drinks alcohol but does not use tobacco or illicit drugs.
Vital signs are within normal limits. Hand examination shows no redness, swelling, or joint deformities, but passive and active range of motion elicits pain at the proximal and distal interphalangeal joints. The remainder of the examination is normal.
X-ray of the patient's hand is shown in the exhibit.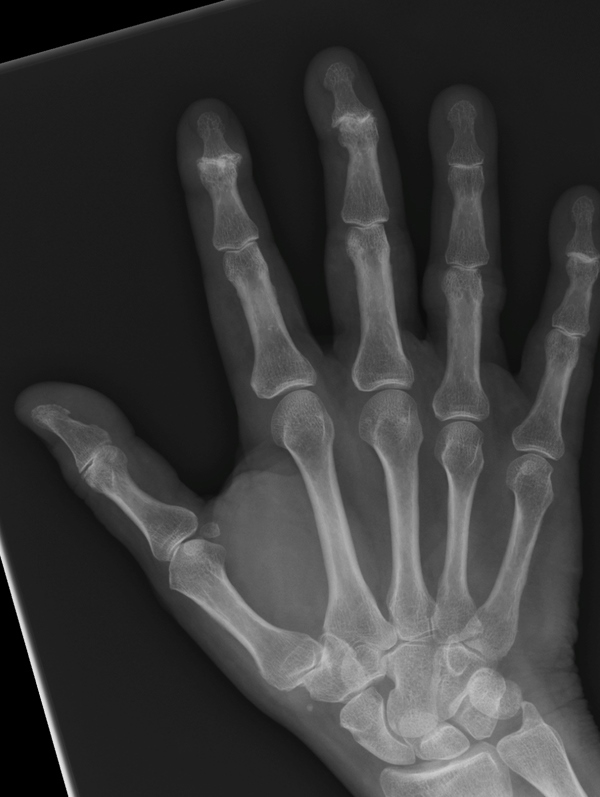 Which of the following is the most appropriate next step in management of this patient's symptoms?
 (Multiple Choice)
4.7/5 (83)
(83) A 54-year-old man with no significant past medical history comes to the physician with complaints of fatigue over the last 2 months. He tried to exercise a few times but tired easily. The patient is so exhausted by the end of the day that he starts "to see double." An upper respiratory illness 2 weeks ago left him extremely fatigued. He has also noticed occasional trouble swallowing and frequent coughing while drinking. The patient has no fever, cough, chills, weight loss, or night sweats. He does not use tobacco, alcohol, or illicit drugs. He has been married for 26 years and has no HIV risk factors.
His blood pressure is 122/68 mm Hg, and pulse is 82/min. His BMI is 25 kg/m2. There is no scleral icterus or conjunctival pallor on inspection. Visual field examination is within normal limits. No enlarged lymph nodes are palpated. Lungs are clear to auscultation. There is no palpable spleen tip.
After initial evaluation, CT scan of the chest is performed (see below).
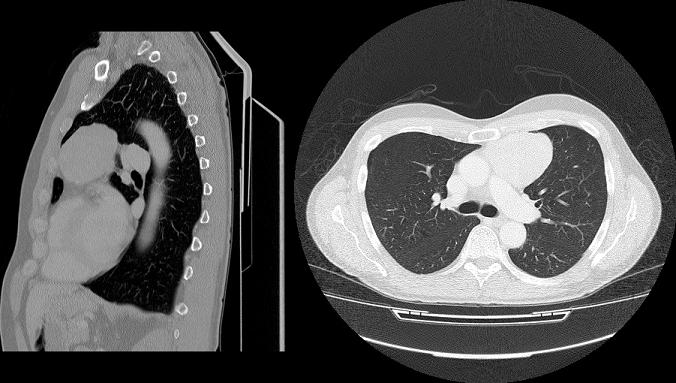 Which of the following is the most likely diagnosis?
 (Multiple Choice)
4.9/5 (83)
(83) A 22-year-old man comes to the office for evaluation of an abnormal ECG. The patient was seen recently at an urgent care clinic for chest pain and was diagnosed with costochondritis. The chest pain subsequently resolved with ibuprofen. He has no prior history of chest pain, palpitations, or lightheadedness. However, he had an abnormal ECG finding on that visit and was advised to follow-up with a primary care physician. The patient does not use tobacco, alcohol, or illicit drugs. He has no family history of heart disease or arrhythmia.
His blood pressure is 118/78 mm Hg and pulse is 88/min. Cardiopulmonary, abdominal, and neurological examination findings are unremarkable.
Resting ECG performed in the primary care office is shown here. The ECG from the urgent care clinic also has similar findings.
Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (84)
(84) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)