



 Chat with AI
Exam 3: Office/Health Center

Exam 1: Emergency Department218 Questions
Exam 2: In-patient Facilities128 Questions
Exam 3: Office/Health Center900 Questions
Select questions type


A 34-year-old woman comes to the physician with lateral right lower-extremity pain for a week. The pain is located just above the knee and radiates to the thigh. It is described as burning and occasionally sharp with moderate severity and an intermittent, unpredictable course. A trial of over-the-counter ibuprofen gave inconsistent improvement.
The patient was recently diagnosed with type 2 diabetes mellitus and is attempting to avoid medication with an aggressive weight loss program that includes intense exercise.
Her vital signs are normal. Body mass index is 37.8 kg/m2. The knee appears grossly normal with no effusion and normal, pain-free range of motion. There is mild, poorly localized tenderness over the lateral knee especially with flexion and extension. Knee ligaments appear stable. Pedal pulses are full and there is trace edema at both ankles.
Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.9/5  (82)
(82) A 56-year-old man comes to the office due to 2 months of upper abdominal discomfort, bloating, and anorexia. Over this period, the patient has had no nausea, vomiting, or black/tarry stools but has lost 8 kg (17.6 lb). He has a history of hypertension and gout. The patient is an active smoker with a 45 pack-year history and drinks alcohol occasionally. He traveled to Mexico 3 months ago for vacation.
Temperature is 37.2 C (99 F), blood pressure is 120/70 mm Hg, pulse is 86/min, and respirations are 12/min. BMI is 29 kg/m2. Scleral icterus is present. The abdomen is soft and nondistended. There is mild right upper quadrant discomfort on deep palpation. The liver edge is palpable 3 cm below the right costal margin. Stool testing for occult blood is negative. The remainder of the physical examination shows no abnormalities.
Laboratory results are as follows:
 Abdominal ultrasound shows dilated intrahepatic and extrahepatic bile ducts. The gallbladder is enlarged but no gallstones are visualized.
Which of the following is the best next step in management of this patient?
Abdominal ultrasound shows dilated intrahepatic and extrahepatic bile ducts. The gallbladder is enlarged but no gallstones are visualized.
Which of the following is the best next step in management of this patient? (Multiple Choice)
4.8/5 (59)
(59) A 35-year-old woman comes to the office due to postprandial fullness, early satiety, and epigastric pain for the past 6 months. She has had no blood in the stool or melena. The patient has not lost weight. Two months ago, she started treatment with over-the-counter omeprazole for 2 weeks but discontinued after noticing only minimal improvement. Medical history includes generalized anxiety disorder. The patient takes no regular medications. Her mother was diagnosed with colon cancer at age 62.
Temperature is 36.7 C (98.1 F), blood pressure is 110/60 mm Hg, and pulse is 76/min. Physical examination is within normal limits except for mild epigastric tenderness.
Initial laboratory results are as follows:
 Which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.9/5 (96)
(96) A 75-year-old woman comes to the office for follow-up of osteoporosis. She has been on weekly oral risedronate for the last 2 years and has an adequate daily intake of calcium and vitamin D via diet and oral supplements. However, in the past year the patient has experienced 2 vertebral compression fractures and lost 5.1 cm (2 in) in height. She was evaluated in a fall reduction program, and home safety improvements were implemented. A home health aide assists the patient with her medications and notes that adherence has been excellent. Medical history is notable for a mild stroke 2 years ago with minimal residual deficits.
Vital signs are normal. BMI is 20 kg/m2. On examination, the patient appears frail and has a modest thoracic kyphosis. Physical examination is otherwise normal.
Laboratory results show normal blood counts, liver function tests, serum creatinine, alkaline phosphatase, TSH, serum parathyroid hormone, anti-tissue transglutaminase antibody assay, 25-hydroxyvitamin D, and serum protein electrophoresis. 24-hour urine calcium excretion is 290 mg. DXA reveals a T-score of −2.8 in the hip and −3.6 in the spine, which represents a significant (>5%) decrease compared with her last test 2 years ago.
Which of the following is the most appropriate next step in management of this patient's osteoporosis?
(Multiple Choice)
4.9/5 (77)
(77) A 46-year-old man comes to the physician because of recurrent abdominal discomfort. He describes episodes of moderate, dull, epigastric pain lasting 2-3 days that have occurred 1-2 times/month over the last 2 years. He also describes occasional nausea but denies any vomiting, diarrhea, black stools, blood in the stool, abdominal distention, or weight loss. He takes ibuprofen for chronic low back pain. He drinks 8-10 beers over the weekends and frequently throughout the week.
His vital signs are within normal limits and his BMI is 28 kg/m2. Physical examination is unremarkable.
Fasting blood glucose is 127 mg/dL. Abdominal x-ray shows focal calcifications anterior to the spine over the epigastric area.
Upper GI endoscopy reveals a normal esophagus, gastric varices in the fundus of the stomach, and a normal duodenum.
Which of the following is the most likely diagnosis?
(Multiple Choice)
4.8/5 (78)
(78) A 64-year-old man comes to the physician because of a tremor. He first began experiencing a tremor in his right hand two years ago that gradually has involved his left hand. The tremor worsens when he drinks from a glass of water or tries to tie his shoes. His other medical problems include hypertension treated with lisinopril. He does not smoke cigarettes, but drinks occasionally and mentions that his tremor improves with a glass of wine. His father died of old age and had a "movement problem" in his later years. His mother died of breast cancer. He currently lives alone.
His blood pressure is 120/70 mm Hg, pulse is 84/min, and respirations are 12/min. At rest, he appears comfortable sitting on the examination table. His heart and lung examinations are within normal limits. He is alert and oriented to person, place, and time. He has 5/5 muscle strength in all extremities and has no obvious resting tremor. When asked to touch his finger to his nose, a tremor is present that increases when his finger touches his nose. His head also appears to have a mild tremor as he stands up that decreases once he sits down. His gait appears to be normal.
Which of the following is the most likely diagnosis?
(Multiple Choice)
4.8/5 (84)
(84) A 70-year-old woman comes to the office after several months of severe pain in her upper back and anterior chest. She used over-the-counter analgesics and a lotion to cope with the pain. The patient stopped using the lotion when it caused a skin rash with blisters. The blisters eventually healed, but she continues to have a severe burning sensation that can be triggered with even a slight touch. The pain interferes with the patient's sleep and daily activities. She has degenerative joint disease and lives independently.
The patient's vital signs are normal. Skin examination is unremarkable except for an area of hyperesthesia along the fourth intercostal space. The remainder of the examination is within normal limits.
Which of the following medications is the most appropriate therapy for this patient?
(Multiple Choice)
4.8/5 (83)
(83) A 78-year-old woman is brought to the office from a nursing home for evaluation of urinary and fecal incontinence. She has longstanding, episodic urinary incontinence but started to also have fecal incontinence over the last week. The stool is described as loose and moderate in volume. The patient has chronic constipation treated with a stable dose of laxatives, but these were discontinued at the onset of fecal incontinence. Her other medical problems include moderate dementia, hypertension, type 2 diabetes mellitus, osteoporosis, and well-controlled congestive heart failure. The patient is in a wheelchair for about 4 hours daily, but otherwise remains in bed. No new medications have been added recently.
Vital signs are stable and unchanged from baseline. The abdomen is soft and nontender with distant but normoactive bowel sounds.
Which of the following is the most likely mechanism of fecal incontinence in this patient?
(Multiple Choice)
4.9/5 (74)
(74) A 66-year-old woman comes to the office to review the results of her recent DXA scan of the hips and spine. She has a history of essential hypertension, osteoarthritis, and acid reflux disease. Current medications include lisinopril, omeprazole, and acetaminophen as needed. She has never smoked and has no history of fractures or falls.
Height is 165 cm (5 ft 5 in) and weight is 70 kg (154.3 lb).
Laboratory testing, including renal function, electrolytes, TSH, and parathyroid hormone level, is normal.
Results of the DXA scan are as follows:
 Which of the following is the most appropriate next step in management of this patient?
 (Multiple Choice)
4.9/5 (73)
(73) A 65-year-old man comes to the physician due to attacks of joint pain and swelling that affect primarily his hands but sometimes his knees or elbows. He currently has no pain, but the episodes occur once or twice a month.
The patient's other medical problems include type 2 diabetes mellitus and hypertension. He has not seen a physician for 2 years, and he has managed his diabetes with diet. He was diagnosed with arthritis 2 years ago at a different clinic and was prescribed ibuprofen. The patient smokes 1-2 packs of cigarettes a day and drinks 2-3 cans of beer each night.
Temperature is 36.7 C (98 F), blood pressure is 155/96 mm Hg, pulse is 84/min, and respirations are 16/min. The patient's BMI is 35 kg/m2. He has clear lungs and normal first and second heart sounds. His abdomen is obese, nontender, and without hepatosplenomegaly. His fingers are shown in the images below. There is no joint tenderness and no joint effusions are present elsewhere.
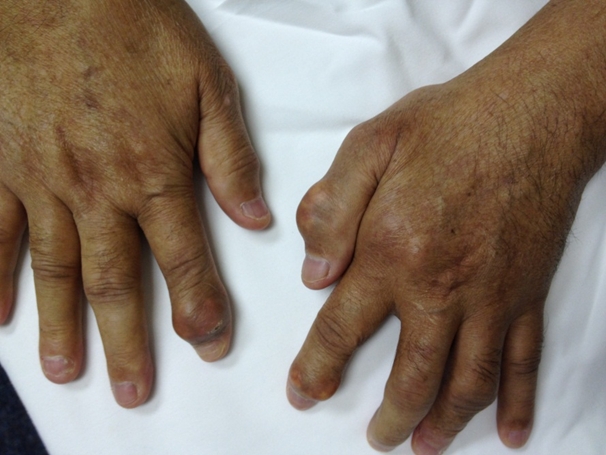
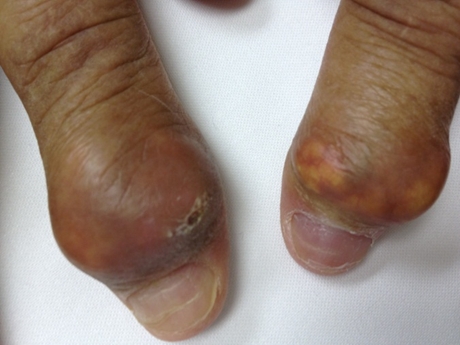 Serum creatinine level is normal and fasting blood glucose level is 133 mg/dL.
Which of the following agents is most likely to provide long-term relief for this patient's symptoms?
Serum creatinine level is normal and fasting blood glucose level is 133 mg/dL.
Which of the following agents is most likely to provide long-term relief for this patient's symptoms? (Multiple Choice)
4.9/5 (67)
(67) A 56-year-old man comes to the office due to a 3-week history of hoarseness. The patient is a school teacher and has never had similar symptoms during his 20-year career. He has had no recent upper respiratory illness, cough, shortness of breath, or difficulty swallowing but has been having vague right ear discomfort. The patient takes lisinopril for hypertension and over-the-counter antacids for occasional heartburn. He has smoked a pack of cigarettes daily for 30 years but does not use alcohol or illicit drugs.
Blood pressure is 122/72 mm Hg, pulse is 78/min, and BMI is 28 kg/m2. His voice sounds hoarse. On examination, there is no nasal discharge, the tympanic membranes appear normal, and the oropharyngeal mucous membranes are pink with no abnormal lesions. The remainder of the physical examination is normal.
Which of the following is the most appropriate next step in management of this patient's symptoms?
(Multiple Choice)
4.9/5 (80)
(80) A 20-year-old college student comes to the office for evaluation of a recent head injury. Two weeks ago, he sustained a blow to the head with loss of consciousness while playing football. He had headache, mild confusion, and dizziness for several days after the injury, but these symptoms have since resolved. The patient has resumed his schoolwork in the past week and is performing at his prior academic level. Comprehensive neurological examination and computerized cognitive testing are unremarkable.
Which of the following is the most appropriate recommendation regarding this patient's return to play?
(Multiple Choice)
4.8/5 (70)
(70) A 45-year-old woman comes to the physician because of chronic nasal congestion. Her symptoms began years ago, but they have worsened lately. She often has paroxysms of 10-12 sneezes, especially when waking up in the morning. She also complains of chronic rhinorrhea and post-nasal drip, and she occasionally has itchy eyes. She is unsure if there is a seasonal component to her symptoms, but they may be worse in the Spring. She does not use aspirin and has not had any episodes of sinusitis. She has tried chlorpheniramine in the past, but it made her drowsy. She does not smoke tobacco or drink alcohol and she denies cocaine or other illicit drug use. She has mild hypertension but is in good health otherwise.
Her blood pressure is 134/84 mm Hg and pulse is 67/min. Her nares are patent with a clear discharge. There are no nasal polyps or septal deviation. The turbinates are pale and her conjunctivae appear normal. Neck, pulmonary, and cardiovascular examinations are within normal limits.
Which of the following is the best next step in this patient's management?
(Multiple Choice)
4.9/5 (75)
(75) A 32-year-old woman comes to the office for preconceptual counseling due to a history of insulin-controlled gestational diabetes mellitus during her previous pregnancy 2 years ago. The pregnancy ended with a cesarean delivery for arrest of descent. There were no postpartum complications and the insulin was discontinued after delivery. A glucose tolerance test at the postpartum visit was normal. The patient has no chronic medical conditions. Medications include a prenatal vitamin and oral contraceptives.
Blood pressure is 130/80 mm Hg and pulse is 82/min. BMI is 29 kg/m2. The remainder of the physical examination is normal.
The patient asks about her risk of diabetes mellitus (DM) in her next pregnancy. Which of the following is the most appropriate statement about this patient's risk of recurrence?
(Multiple Choice)
4.9/5 (82)
(82) A 60-year-old man comes to the physician due to nighttime chest pain. The patient was diagnosed with extensive coronary artery disease a year ago and was offered coronary artery bypass grafting surgery. He refused surgery and instead opted for medical management. Since the medical therapy was started, the patient's symptoms have improved. He has angina during the daytime only after moderate to severe exertion. However, the patient still has been waking up 3-4 times per week in the middle of the night with substernal chest pain, which usually resolves spontaneously in 7-8 minutes but sometimes requires nitroglycerin. His other medical problems include difficult-to-control hypertension, hyperlipidemia, and peripheral vascular disease. The patient has smoked cigarettes for 35 years and quit 5 years ago. His medications include aspirin, metoprolol, isosorbide mononitrate, amlodipine, lisinopril, rosuvastatin, and nitroglycerin as needed. He takes all his medications during the morning hours.
His blood pressure is 150/82 mm Hg, pulse is 62/min and regular, and respirations are 14/min. The patient is obese with large neck circumference and a BMI of 34 kg/m2. Chest is clear to auscultation. There is no peripheral edema. The remainder of the examination is normal.
An electrocardiogram (ECG) performed in the office shows normal sinus rhythm with nonspecific T wave changes. His most recent echocardiogram showed a left ventricular ejection fraction of 60%. During exercise single photon emission computed tomography (SPECT) performed a month ago, the patient exercised for 8 minutes and reached 85% of age-predicted maximal predicted heart rate. He stopped due to fatigue and mild chest discomfort. Stress SPECT images showed a moderately extensive inferior wall reversible defect.
Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.8/5 (79)
(79) A 54-year-old man comes to the physician because of headaches, fatigue, and joint pains involving both his wrists and knees. His wife has noticed that he has been snoring excessively at night. He has been healthy all his life and takes no medications. He has not seen a physician for more than 5 years. He denies tobacco or alcohol use. Family history is not significant.
His blood pressure is 146/70 mm Hg and pulse is 70/min. Body mass index (BMI) is 28 kg/m2. Physical examination shows numerous skin tags, widened interdental spaces, and large hands. Visual fields are normal on confrontation.
Laboratory results are as follows:
 The patient is at the highest risk of developing which of the following conditions if left untreated?
 (Multiple Choice)
4.8/5 (86)
(86) A 55-year-old woman comes to the physician with a rash on her face for the past 4 weeks. The rash seems to get worse when she spends time outdoors, but it does not flare with food intake. She has no flushing or itching. The patient denies fever, weight loss, or muscle weakness. She was recently diagnosed with hypertension and type 2 diabetes mellitus and started on lisinopril, metformin, and sitagliptin.
Physical examination reveals a 1-cm ulcer in the roof of the hard palate. A photograph of the rash is shown below.
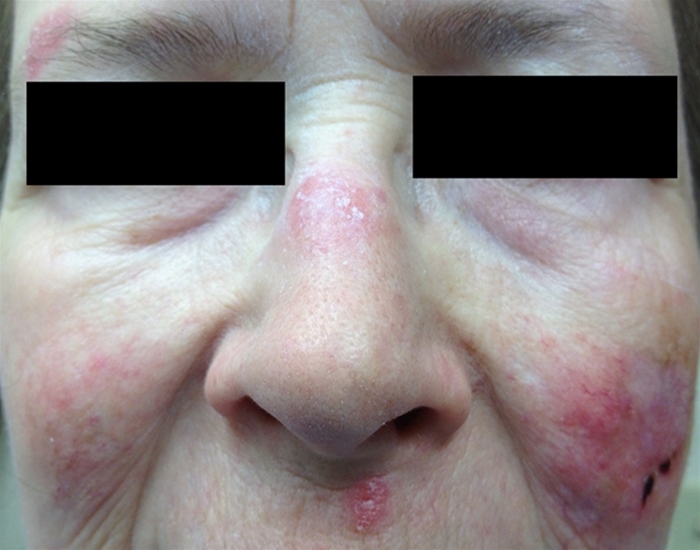 Which of the following conditions is the most likely diagnosis?
 (Multiple Choice)
4.9/5 (81)
(81) A 42-year-old man comes to the physician because of a dull headache, worsening malaise, neck pain, and sore throat for the last two weeks. He has no other medical problems and is compliant with his annual physical examinations. On further questioning, he recalls recovering from a transient, non-pruritic rash a few months ago that he attributed to his vitamin E supplement. He works as a corporate attorney serving a large number of customers overseas, and returned from a business trip to Thailand two months ago.
His medications include calcium, vitamin D, and occasional green tea tablets. He stopped taking vitamin E shortly after the appearance of the rash. He denies smoking and drinks socially. He experienced an anaphylactic reaction to penicillin as a child.
His vital signs are within normal limits. Examination shows no abnormalities.
Laboratory studies showed a normal complete blood count and metabolic panel. His serum RPR titer is reactive at 1:50 and he has a reactive FTA-ABS. HIV ELISA testing was negative. Head CT is normal.
Cerebral spinal fluid (CSF) analysis is as follows:
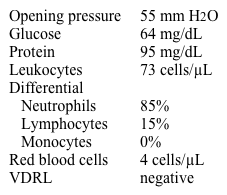 Which of the following is the next best step in management?
 (Multiple Choice)
4.8/5 (76)
(76) A 51-year-old man comes to the physician with a rash on his hands and feet for the past 2 weeks. The rash is associated with a tingling and burning sensation but no pruritus. He has no fevers or chills. He has a history of advanced renal cell carcinoma that is treated with sunitinib. His other medical problems include acid reflux disease and hypertension, and his medications include over-the-counter antacids and amlodipine. An HIV test performed 2 months ago was negative.
The patient's vital signs are normal. Skin examination shows tender, erythematous lesions on his palms and soles with areas that look like blisters.
Laboratory results are as follows:
 Which of the following conditions is the most likely diagnosis?
 (Multiple Choice)
4.7/5 (77)
(77) A 37-year-old man comes to the clinic complaining of rectal problems. He has had a constant urge to defecate for the past 2-3 days. When he does have a bowel movement, it is a small volume that contains purulent material sometimes streaked with blood. He has no fever but feels tired with generalized malaise. He recently had unprotected anal-receptive sex with a new male partner. He is in otherwise general good health and takes no medications. He has no history of similar illness.
His vital signs are within normal limits. Cardiopulmonary and abdominal examinations are also within normal limits. There are no lesions visible in the perianal area. There is no inguinal lymphadenopathy.
Which of the following is the most likely cause of his symptoms?
(Multiple Choice)
4.8/5 (81)
(81) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)