



 Chat with AI
Exam 3: Office/Health Center

Exam 1: Emergency Department218 Questions
Exam 2: In-patient Facilities128 Questions
Exam 3: Office/Health Center900 Questions
Select questions type


A 65-year-old man comes to the clinic with 1 week of pruritic facial rash. He was recently diagnosed with community-acquired pneumonia and is on day 8 of his 10-day antibiotic course. He otherwise feels healthy and has no other complaints.
His past medical history includes Parkinson disease, mild dementia, and hypertension. His medications include carbidopa-levodopa, donepezil, amlodipine, and levofloxacin.
The rash is shown in the image below.
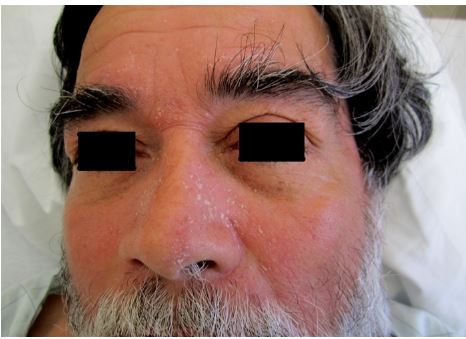 Which of the following is the best next step in management of this patient's facial rash?
 (Multiple Choice)
4.7/5  (82)
(82) A 54-year-old woman comes to the office for her annual health maintenance visit. The patient's medical problems include hypercholesterolemia, gastroesophageal reflux disease, and alcohol use disorder. She was hospitalized for treatment of alcohol withdrawal last year and attended an outpatient substance abuse program after discharge. The patient maintained abstinence for 3 months following completion of the program. Since then, she has attempted to limit her consumption to 1 drink a day; however, since being let go from her job last month, she has started drinking heavily again and currently consumes 8-10 vodka drinks daily. She says, "I thought I could control it on my own, but the cravings are so intense." The patient lives alone and is currently looking for work. She has smoked a pack of cigarettes daily for 30 years but does not use illicit drugs.
Temperature is 36.7 C (98 F), blood pressure is 130/80 mm Hg, pulse is 78/min, and respirations are 12/min. BMI is 27 kg/m2. Examination shows no abnormalities.
In addition to psychosocial interventions, which of the following is the most appropriate pharmacotherapy?
(Multiple Choice)
4.8/5 (81)
(81) A 53-year-old woman, gravida 1 para 1, comes to the office for a routine gynecologic examination. The patient says that she feels well. Menopause was at age 50. Medical problems include obesity and type 2 diabetes mellitus managed with a single oral medication. The patient is sexually active with a new partner of 6 months; her husband of 18 years died several years ago. She has a 30-pack-year smoking history but does not use alcohol or illicit drugs.
Vital signs are within normal limits. Pelvic examination reveals no abnormalities.
A Pap test is performed and the cervical cytology report specifies that there are "atypical squamous cells of undetermined significance."
Which of the following is the best next step in management of this patient?
(Multiple Choice)
5.0/5 (79)
(79) A 36-year-old man comes to the office due to a leg injury. He suffered an abrasion to his right leg after falling from his motorcycle 5 days earlier. The patient washed the wound with tap water and covered it with an occlusive dressing but is now having increasing pain. He has not removed the dressing for the last 3 days due to pain. Past medical history is unremarkable. On examination, he is afebrile but has a 10-cm abrasion on the lateral right leg involving the epidermis and superficial dermis. There is a surrounding area of erythema and warmth extending 3-5 cm from the margin of the wound.
Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.9/5 (66)
(66) A 72-year-old obese woman is scheduled for right knee replacement due to osteoarthritis. She can barely walk due to severe knee pain. She has no chest pain, dyspnea, palpitations, or syncope. The patient has a history of hypertension and diet-controlled diabetes mellitus. She had an uncomplicated cholecystectomy for symptomatic gallstones 10 years ago.
Blood pressure is 152/75 mm Hg and pulse is 75/min and regular. BMI is 32 kg/m2. A 3/6 late-peaking systolic murmur is heard at the right upper sternal border. S2 is soft with paradoxical splitting. The lungs are clear on auscultation. The abdomen is nontender. The right knee is deformed and tender with mild effusion. There is no peripheral edema.
ECG shows normal sinus rhythm, voltage criteria for left ventricular hypertrophy, and T-wave inversion in leads I, aVL, and V6. Serum creatinine is 1.1 mg/dL.
Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (79)
(79) A 56-year-old woman comes to the emergency department due to acute dyspnea and cough. She has a history of chronic obstructive pulmonary disease (COPD) treated with inhaled albuterol, tiotropium, and fluticasone. The patient's other medical problems include hypertension and hypothyroidism, for which she takes lisinopril, hydrochlorothiazide, and levothyroxine. She also takes a daily over-the-counter supplement containing vitamin D and calcium carbonate. The patient has a 25-pack-year smoking history but quit after the diagnosis of COPD was made 4 years ago. She experienced menopause at age 49 and has no history of low trauma fracture or loss of height.
Blood pressure is 140/80 mm Hg, pulse is 108/min, and respirations are 24/min. Oxygen saturation is 94% on 2 L of oxygen via nasal cannula. BMI is 29 kg/m2. Chest examination reveals coarse rhonchi bilaterally, and the remainder of the physical examination is unremarkable.
Laboratory results are as follows:
 The patient is admitted to the hospital and treated with systemic glucocorticoids, antibiotics, and inhaled bronchodilators. On the third day of hospitalization, repeat serum calcium is 11.2 mg/dL and parathyroid hormone is 60 pg/mL (normal: 10-65).
Which of the following is the most likely cause of this patient's hypercalcemia?
The patient is admitted to the hospital and treated with systemic glucocorticoids, antibiotics, and inhaled bronchodilators. On the third day of hospitalization, repeat serum calcium is 11.2 mg/dL and parathyroid hormone is 60 pg/mL (normal: 10-65).
Which of the following is the most likely cause of this patient's hypercalcemia? (Multiple Choice)
4.8/5 (90)
(90) A 54-year-old woman comes to the office for evaluation of a rash on her face. She initially developed facial flushing and redness 8 months ago and has had intermittent, progressive symptoms since then. She has also had a burning sensation in the cheeks. The rash worsens with sun exposure and spicy foods. The patient has traveled extensively the past few months and has been outdoors more than usual. She has no history of tobacco or alcohol use.
Vital signs are within normal limits. Skin examination is shown in the exhibit.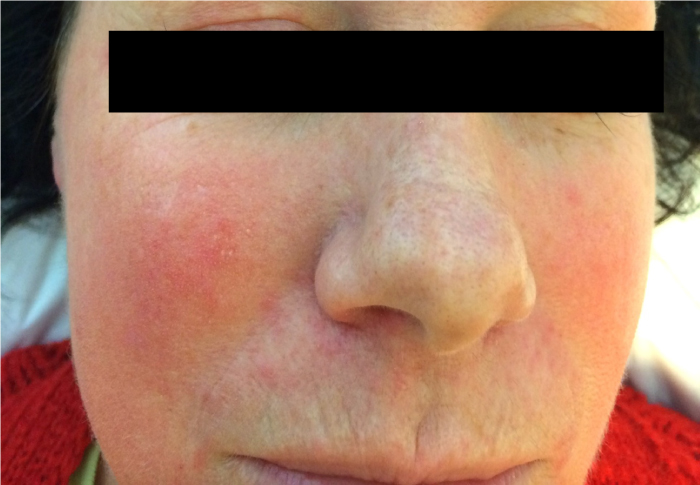 The remainder of the physical examination is normal.
Which of the following is the best next step in management of this patient's rash?
The remainder of the physical examination is normal.
Which of the following is the best next step in management of this patient's rash? (Multiple Choice)
4.9/5 (74)
(74) A 26-year-old woman with new-onset vaginal discharge is diagnosed with Trichomonas infection. She has had several sexual partners over the last year. The patient has no genital ulcers, skin rash, back pain, headaches, vision problems, or fever. She has no other known medical problems or drug allergies. She does not recall having previous testing for sexually transmitted infections.
Physical examination is unremarkable.
Laboratory results are as follows:
 In addition to treating the Trichomonas infection, which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.7/5 (79)
(79) A 52-year-old woman is evaluated for a 1-year history of diarrhea. The patient describes "runs" of watery diarrhea that last several weeks before subsiding but then reappear. She has been taking over-the-counter loperamide and bismuth subsalicylate, which provide only transient symptom relief. The patient has also experienced a 5-kg (11-lb) weight loss over the past year but has had no fever, abdominal pain, or rectal bleeding. Medical history is notable for hypertension and depression treated with ramipril and fluoxetine, respectively. She is an ex-smoker with a 12-pack-year history and does not drink alcohol.
Vital signs are normal. Examination reveals mild, generalized abdominal tenderness with no guarding or rebound tenderness. Bowel sounds are normal. Test for stool occult blood is negative.
Blood cell counts, serum chemistry studies, and TSH levels are within normal limits. HIV and stool tests for infection are negative. IgA anti-tissue transglutaminase antibodies are negative with normal IgA levels. Colonoscopy reveals grossly normal terminal ileal and colonic mucosa. Random biopsies show a lymphocyte-predominant mononuclear infiltrate with few neutrophils and eosinophils in the lamina propria. Crypt architecture is preserved, but focal cryptitis is present.
Which of the following is most appropriate next step in management of this patient's illness?
(Multiple Choice)
4.8/5 (78)
(78) A 75-year-old woman comes to the office for evaluation of a rash on her chest. She is nonambulatory and lives in a nursing home. One week ago, the patient had a fever with a productive cough of yellow sputum. She was started on azithromycin for presumed pneumonia with slight improvement in her symptoms. However, her caregivers have noted significant sweating over the past 5 days and a diffuse rash on her chest, abdomen, and back. She has a history of hypertension, stroke, and dementia.
Her vital signs are within normal limits. Skin examination is shown in the image below. There is no warmth or tenderness around the skin lesions.
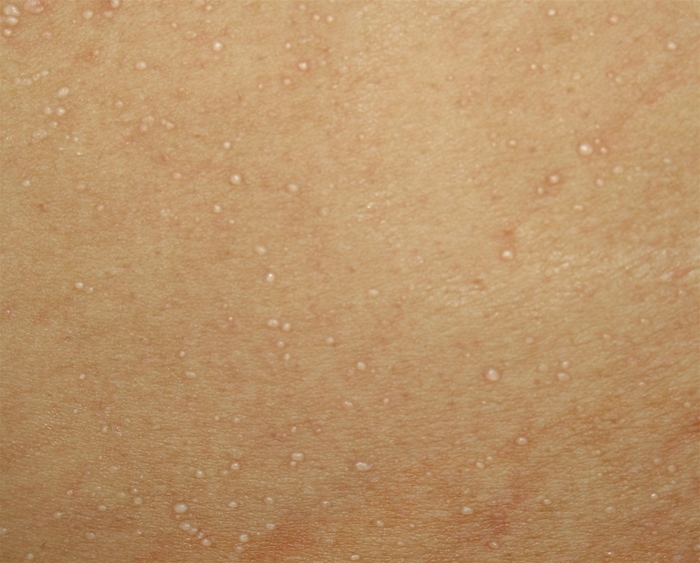 Which of the following is the most likely diagnosis?
 (Multiple Choice)
4.8/5 (76)
(76) A 35-year-old HIV-positive man comes to the physician because of acute-onset severe perianal pain for the last 24 hours. His pain is 9/10 and burning in quality. He denies fever, chills, dysuria, or pain when moving his bowels. His other medical problems include anxiety disorder and hypertension. His last CD4 count was 340 cells/µL. His medications include antiretroviral therapy, losartan, and amlodipine. He ended his 8-year relationship with his male partner one week ago, and he denies any other recent sexual encounters. He does not use tobacco, alcohol, or recreational drugs.
His temperature is 37.2 C (99 F), blood pressure is 144/89 mm Hg, and pulse is 104/min. Physical examination reveals 3 superficial, highly tender, ulcerated lesions located in the perianal skin area. There is mild, non-tender, generalized lymphadenopathy. The remainder of his physical examination is unremarkable.
Which of the following is the most likely cause of this patient's current condition?
(Multiple Choice)
4.9/5 (75)
(75) A 43-year-old woman is being evaluated for a heart murmur. She is physically active and takes a yoga class three times a week without difficulty. She exercises on a treadmill twice per week. She denies any chest pain or pressure, palpitations, and shortness of breath.
She had arthroscopic knee surgery two years ago after sustaining a knee injury while running. Otherwise, her past medical history is unremarkable.
Her blood pressure is 122/78 mm Hg and pulse is 67 /min. Her BMI is 25 kg/m2. There is a blowing 3/6 holosystolic murmur heard best at the apex. Lungs are clear on auscultation. Her physical examination is otherwise unremarkable.
EKG shows normal sinus rhythm with non-specific ST segment and T wave changes. Echocardiogram shows normal left ventricular size and function, an ejection fraction of 65%, and posterior mitral leaflet prolapse with severe eccentric mitral regurgitation. Left atrial size is moderately increased. Pulmonary artery systolic pressure is estimated at 25 mm Hg.
Which of the following is the best recommendation for this patient?
(Multiple Choice)
4.8/5 (63)
(63) A 35-year-old man comes to the office due to bloating, excessive flatus, and loose stools since an episode of food poisoning several months ago. The patient had been on a cruise ship when he developed nausea, vomiting, and diarrhea. Several other patrons developed similar symptoms that resolved with supportive care only. The patient's current symptoms began 1-2 weeks after returning home and usually occur in the morning shortly after breakfast. His usual breakfast consists of coffee with whole milk and cereal or oatmeal. Soon after eating, he develops bloating followed by crampy abdominal pain and loose stools. The symptoms occasionally recur after dinner. Medical history is insignificant. The patient drinks 1 or 2 beers on weekends and does not use tobacco or illicit drugs. He reports no other recent travel outside the country or unusual food exposures.
Vital signs are normal. The abdomen is soft and nontender. Bowel sounds are present with loud borborygmi. There is no hepatomegaly or splenomegaly. Stool occult blood testing is negative.
Complete blood count, serum chemistries, TSH, erythrocyte sedimentation rate, and HIV serology are within normal limits.
Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (83)
(83) A 56-year-old woman with colon cancer diagnosed on screening colonoscopy is scheduled for hemicolectomy in 2 weeks. She has a history of systemic lupus erythematosus, lupus nephritis, and pericarditis. The patient was treated with cyclophosphamide and high-dose corticosteroids for her lupus nephritis 6 years ago. The nephritis went into remission after 2 years of treatment and has not reoccurred. Six months ago, she had an episode of pericarditis with effusion that was treated with high-dose prednisone. The prednisone was slowly tapered and discontinued a week ago. She is currently on a maintenance regimen of hydroxychloroquine.
Blood pressure is 135/80 mm Hg and pulse is 82/min. Her body mass index is 29 kg/m2. Lungs are clear to auscultation. There are no skin rashes or striae. She has a Cushingoid appearance. There is no peripheral edema.
Laboratory results are as follows:
 Which of the following is the best next step in managing this patient's preoperative steroid requirement?
 (Multiple Choice)
4.8/5 (83)
(83) A 74-year-old man is brought to the physician by his son for forgetfulness. Over the last 2 years, the patient has missed several important appointments, often forgets to take his medication, and has limited his social interaction. Two months ago, he got lost in the neighborhood he has lived in for the last 20 years. The patient says he is "fine and in good spirits." He is a retired mathematics professor.
Neurologic examination, including gait assessment, is unremarkable. His mini-mental state examination score is 26/30.
Which of the following is the most likely diagnosis?
(Multiple Choice)
4.8/5 (85)
(85) A 38-year-old woman is evaluated for joint pain and fatigue, which has been slowly progressive over the last year. Her other past medical problems include migraine headaches, lower back pain, and non-ulcer dyspepsia. She has had no miscarriages or thrombotic events.
Vital signs are within normal limits. Her body mass index is 30 kg/m2. Examination shows symmetric tenderness of multiple small joints in the hands and a small effusion at the left knee.
X-ray image of the left hand is shown below.
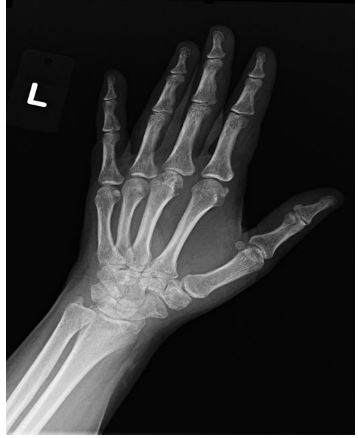 Which of the following would have the most prognostic value for this patient?
 (Multiple Choice)
4.8/5 (83)
(83) A 42-year-old man comes to the office for further evaluation after a high blood pressure reading on an automated machine at a supermarket. He has no chronic medical problems and takes no medications. The patient has felt fatigued lately, which he attributes to stress at work. He also reports constipation and a 4.5-kg (10-lb) weight gain since he stopped exercising 9 months ago. The patient smoked cigarettes for a few years in college but has not smoked for the last 20 years. He does not use alcohol or illicit drugs. The patient lives with his girlfriend and has no children.
Blood pressure is 145/95 mm Hg and pulse is 66/min. Repeat blood pressure after 10 minutes is 135/85 mm Hg. BMI is 31 kg/m2. The patient appears mildly obese, but the remainder of the examination is normal.
Fasting laboratory results are as follows:
 Which of the following is the most appropriate next step in management of this patient's metabolic abnormalities?
 (Multiple Choice)
4.9/5 (74)
(74) A 75-year-old man comes to the office for hypertension follow-up. The patient has been taking chlorthalidone since being diagnosed with hypertension 15 years ago, and he was started on metoprolol 4 years ago after he had a non-ST elevation myocardial infarction. Over the last 2 years, his blood pressure measurements have ranged from 160/80 mm Hg to 180/100 mm Hg, and amlodipine was added to his medical regimen 6 months ago. The patient has had no chest pain, dyspnea, palpitation, headache, or subjective neurological deficits. His medical history includes hyperlipidemia and peripheral vascular disease, and other medications are aspirin and atorvastatin. The patient is a former smoker with a 30-pack-year history and does not use alcohol or illicit drugs.
Today, blood pressure is 165/86 mm Hg and pulse is 68/min. Physical examination is notable for an abdominal bruit.
Serum creatinine is 1.2 mg/dL, and duplex Doppler ultrasonography reveals >60% stenosis of bilateral renal arteries.
Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.8/5 (86)
(86) A 16-year-old girl comes to the office due to a 3-week history of constipation and stomachaches, which are getting worse despite over-the-counter laxatives. The patient has no significant medical history and takes no medication. She consumes a vegan diet and exercises 2 hours a day, which she says "is necessary so I don't become any fatter than I am already." Family history is significant for Hashimoto thyroiditis in her mother, as well as scleroderma and obsessive-compulsive disorder in her sister.
Physical examination is significant for a thin, young female with fine hair on her face and body and with dry skin. Temperature is 37.2 C (99 F), blood pressure is 80/55 mm Hg, pulse is 39/min, and respirations are 14/min. BMI is 16.5 kg/m2. Laboratory results are as follows:
 Which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.7/5 (79)
(79) A 45-year-old woman comes to the office for routine follow-up. Six weeks ago, the patient was admitted to the hospital for treatment of left lower lobe pneumonia. After receiving intravenous antibiotic therapy for 3 days, she was sent home to finish a 7-day course of oral moxifloxacin. Since discharge, the patient has felt well. She reports getting her energy back and being able to perform daily activities without difficulty. The patient has a 15-pack-year history but stopped smoking after the pneumonia. She does not drink alcohol. Vital signs are normal. Physical examination shows no abnormalities. Which of the following is the most appropriate next step in management?
(Multiple Choice)
4.9/5 (84)
(84) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)