



 Chat with AI
Exam 3: Office/Health Center

Exam 1: Emergency Department218 Questions
Exam 2: In-patient Facilities128 Questions
Exam 3: Office/Health Center900 Questions
Select questions type


A 70-year-old man seeks advice for continuing bladder problems. Over the last several years, the patient has had a slow decrease in the volume and force of his urinary stream associated with nocturia and urinary frequency. When seen in the office 12 months ago, his American Urological Association symptom score was 18 (indicating significant symptoms). Digital rectal examination showed a slightly enlarged, smooth, nontender prostate. Urinalysis and prostate-specific antigen were normal. The patient was prescribed a long-acting alpha adrenergic blocker and his symptoms improved. However, he now has intermittent urinary incontinence associated with a strong urge to void. This usually occurs when he senses a full bladder, but it is also triggered by the sound of running water or with exposure to cold. Limiting his fluid intake and scheduling himself to void frequently have not helped. The patient has had no associated dysuria and has not added any new medications in the past year.
Genitourinary examination including prostate examination is unchanged from a year ago. Urinalysis is normal. Ultrasound bladder scan estimates a residual urine volume of 60 mL.
Which of the following is the best next step in management of this patient's urinary symptoms?
(Multiple Choice)
5.0/5  (88)
(88) A 35-year-old woman who was recently diagnosed with HIV comes to the office for evaluation after moving to New York City from Tucson, Arizona. She began taking highly active antiretroviral therapy 9 months ago and has been compliant with the regimen. She also takes trimethoprim/sulfamethoxazole for Pneumocystis pneumonia prophylaxis. The patient reports no symptoms except for occasional nausea. Her CD4 count 3 months ago was 210/mm3. She also has a history of asthma, which is stable with inhaled beclomethasone therapy.
Vital signs are within normal limits. Examination shows no abnormalities.
Laboratory results are as follows:
 The patient's viral load is undetectable.
Chest x-ray shows no acute disease.
Which of the following is the best next step in management of this patient?
The patient's viral load is undetectable.
Chest x-ray shows no acute disease.
Which of the following is the best next step in management of this patient? (Multiple Choice)
4.9/5 (76)
(76) A 75-year-old man recently diagnosed with advanced colon cancer comes to the physician with increasing abdominal pain. He has known metastatic disease to the liver, lungs, brain, and peritoneum. In addition to his pain, he complains of increasing fatigue and generalized weakness. He now requires assistance from his family to perform activities of daily living and becomes dyspneic after walking from his bed to the bathroom.
His other medical problems include chronic obstructive pulmonary disease, hypertension, osteoarthritis, and coronary artery disease. His medications include tiotropium, albuterol, lisinopril, aspirin, long-acting morphine, and oxycodone as needed for pain.
Which of the following risk factors is the most important predictor of this patient's prognosis?
(Multiple Choice)
4.9/5 (77)
(77) A 45-year-old man comes to the office for evaluation of a rash on his abdomen. The rash started 3 weeks ago and has slowly worsened since. There is no pruritus. The patient has a history of diabetes treated with metformin. He has no history of tobacco or alcohol use.
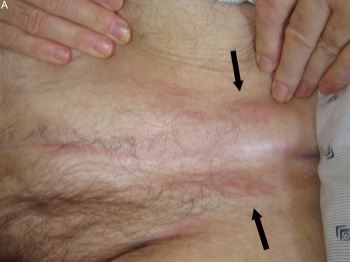
Vital signs are within normal limits. BMI is 32 kg/m2. Skin examination findings are shown in the image below. There is no warmth or tenderness around the skin lesions. The remainder of his physical examination is normal.
 Which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.8/5 (83)
(83) A 62-year-old man comes to the office after a week of persistent back pain. The patient has had back pain before, but this episode is more disturbing. The pain is limited to his lower back, becomes worse with movement, and persists at night. He has no leg pain or abdominal symptoms. Three weeks ago, the patient was evaluated for fever, urinary frequency, and dysuria. He was found to have an enlarged, nontender prostate with a prostate-specific antigen level of 2.2 ng/mL (normal <4 ng/mL), and was prescribed a 7-day course of ciprofloxacin. Except for mild malaise, the symptoms have subsided. The patient's medications include vitamin D and daily fiber supplements.
Temperature is 36.7 C (98.1 F), blood pressure is 120/70 mm Hg, and pulse is 88/min. The patient has limited mobility of his back in all directions due to pain. There is no tenderness on palpation of any of the spinal processes. There is no costovertebral angle tenderness. Gait, perineal sensation, and deep tendon and plantar reflexes are normal. The remainder of the examination is normal.
Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (88)
(88) A 63-year-old man comes to the physician because of back and neck pain for the last 2 months. He takes over-the-counter acetaminophen and ibuprofen with adequate pain relief; however, the pain has recently begun to disturb his sleep. He denies weight loss, night sweats, and joint swelling. He has no other medical problems. His father was diagnosed with prostate cancer at the age of 65 and died from metastatic disease.
His blood pressure is 112/72 mm Hg and pulse is 89/min. There is no peripheral lymphadenopathy. The liver span is 11 cm and the spleen is not palpable. There is no spinal deformity or percussion tenderness. There are no skin rashes. The prostate is mildly enlarged and rubbery.
Laboratory results are as follows:
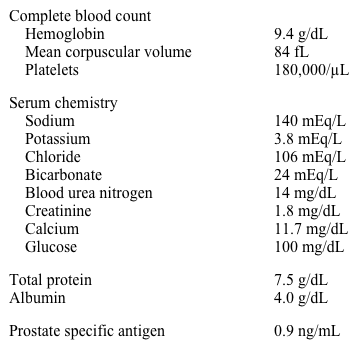 Radiographs of the lumbar spine show multiple lytic lesions and a compression fracture of the L3 vertebra. Serum protein agar gel electrophoresis and immunofixation do not reveal an M-spike.
Which of the following is the most appropriate next step in managing this patient?
Radiographs of the lumbar spine show multiple lytic lesions and a compression fracture of the L3 vertebra. Serum protein agar gel electrophoresis and immunofixation do not reveal an M-spike.
Which of the following is the most appropriate next step in managing this patient? (Multiple Choice)
5.0/5 (81)
(81) A 43-year-old woman comes to the office due to nausea, vomiting, and intermittent epigastric pain for the last 6 months. Her symptoms have gradually worsened and now she cannot finish a regular meal without feeling full quickly. Although the patient has a decent appetite, she is afraid to eat due to postprandial bloating and heartburn. Fatty foods and salads are particularly bothersome. Consequently, the patient has lost 6.8 kg (15 lb).
Other medical problems include hypertension, type 1 diabetes mellitus complicated by diabetic nephropathy and neuropathy, hypercholesterolemia, and nonalcoholic fatty liver disease. Medications include insulin glargine, insulin lispro, lisinopril, gabapentin, simvastatin, low-dose aspirin, and ranitidine. The patient has no known drug allergies.
Examination reveals a distended and nontender abdomen with an obvious succussion splash. Rectal examination shows brown stool negative for occult blood.
Laboratory results are as follows:
 Which of the following is the most appropriate next step in management of this patient?
 (Multiple Choice)
4.8/5 (79)
(79) A 27-year-old man is referred for preoperative evaluation prior to elective craniotomy to remove a benign brain tumor. He was diagnosed with type 1 von Willebrand disease at age 17 and has intermittent epistaxis and easy bruising. Last year he had a prolonged and severe episode of epistaxis that required cautery and nasal packing. He has no other medical problems or surgeries. The patient has no known drug allergies.
Vital signs are within normal limits. Skin examination shows an area of ecchymosis on the left thigh. Neurologic examination is normal.
Laboratory results are as follows:
 The patient has blood type A, and von Willebrand factor (VWF) antigen and activity level are pending.
Which of the following is the most effective strategy for decreasing this patient's risk of perioperative bleeding?
The patient has blood type A, and von Willebrand factor (VWF) antigen and activity level are pending.
Which of the following is the most effective strategy for decreasing this patient's risk of perioperative bleeding? (Multiple Choice)
4.9/5 (91)
(91) A 42-year-old man comes to the physician with complaints of daytime sleepiness, dyspnea on exertion, and impaired concentration. His other medical problems include hypertension and type 2 diabetes mellitus.
His temperature is 36.1° C (97° F), blood pressure is 162/85 mm Hg, pulse is 92/min, and respirations are 14/min. His BMI is 40 kg/m2. The patient's pulse oximetry is 94% on room air. Examination shows jugular venous distention, clear lung fields, loud second heart sound, and 2+ pretibial edema bilaterally.
Laboratory results are as follows:
 Chest x-ray shows low lung volumes but is otherwise unremarkable. Spirometry shows a FEV1 of 70% of predicted and a FEV1/FVC ratio of 90%. Transthoracic echocardiography is limited by body habitus but shows mild right ventricular enlargement.
Which of the following is the best initial therapy for this patient?
Chest x-ray shows low lung volumes but is otherwise unremarkable. Spirometry shows a FEV1 of 70% of predicted and a FEV1/FVC ratio of 90%. Transthoracic echocardiography is limited by body habitus but shows mild right ventricular enlargement.
Which of the following is the best initial therapy for this patient? (Multiple Choice)
4.8/5 (84)
(84) A 34-year-old woman comes to the physician's office due to worsening shortness of breath over the last 6 months. She can no longer walk a block or climb a flight of stairs without stopping to catch her breath. The patient is occasionally lightheaded when trying to exert herself. An albuterol inhaler prescribed 3 months ago has provided little relief. She does not use tobacco.
Pulse oximetry on room air is 97% at rest and drops to 92% on walking in the office hallway. The patient's BMI is 26 kg/m2. Lung examination is normal.
Chest x-ray is unremarkable. Echocardiogram shows moderate right ventricular dilation and hypokinesis with increased flow velocities through the tricuspid valve.
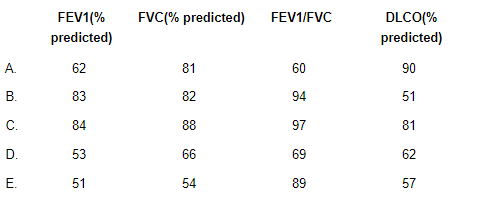
Which of the following is most likely to be seen on pulmonary function testing?
DLCO = diffusing capacity for carbon monoxide; FEV1 = forced expiratory volume in 1 second; FVC = forced vital capacity.
(Multiple Choice)
4.8/5 (77)
(77) A 32-year-old white man is referred for evaluation of a murmur noted on a pre-employment physical. He has no specific complaints. He is physically active and runs 4-5 miles almost every day. His older brother died of presumed sudden cardiac arrest at age 37 years. On physical examination, there is a wide, fixed splitting of the second heart sound. A faint mid-systolic ejection murmur is heard best over the left second intercostal space. Otherwise, his physical examination is unremarkable. An echocardiogram confirms the presence of a large secundum atrial septal defect.
Which of the following is the most likely explanation for the murmur?
(Multiple Choice)
4.7/5 (80)
(80) A patient consults the physician regarding her daughter's plans to get a tattoo. She wishes to be informed about the possible complications so that she can discuss the issue with her daughter. The mother asks for advice on how best to ensure that the procedure is done properly to minimize complications.
Which of the following infections is most commonly associated with the tattooing process?
(Multiple Choice)
4.9/5 (67)
(67) A 63-year-old man comes to the physician for his yearly follow up. He has no known medical problems and takes no medication. He has gained 10 lbs (4.6 kg) over the last year. Both of his parents had type 2 diabetes mellitus. He is divorced and has no children. Since his divorce, he mainly eats frozen foods and has a very sedentary lifestyle. He drinks 2 glasses of wine on the weekends.
His blood pressure is 144/96 mm Hg and BMI is 29 kg/m2. He has acanthosis on his neck. The remainder of the physical examination is within normal limits.
His laboratory investigations reveal a fasting blood glucose of 112 mg/dL, serum creatinine of 1.1 mg/dL, and hemoglobin A1c of 6.2% (normal 4.0-5.6%).
Which of the following is the best option to prevent this patient from developing overt type 2 diabetes mellitus?
(Multiple Choice)
4.9/5 (65)
(65) A 72-year-old man is scheduled for right knee replacement surgery due to severe osteoarthritis. He has no other medical problems. He takes ibuprofen and occasionally oxycodone for knee pain. He also takes herbal supplements that he purchases from a health food store.
Which of the following herbal supplements increases the risk of bleeding in this patient?
(Multiple Choice)
4.9/5 (91)
(91) A 79-year-old woman is brought to the emergency department by her son due to worsening lethargy, confusion, and irritability over the past 2 weeks. The patient has lived by herself since the death of her husband a year ago, but her son frequently visits and helps her with grocery shopping and laundry. Her son says that the patient has had frequent falls at home and that he has asked her to come live with him but she has refused. He also states that she has not been as socially active as she was before her husband's death and that she has been drinking alcohol more frequently. Medical history includes hypertension and hyperlipidemia, but the patient is not adherent with medications or follow-up visits. She is a lifetime nonsmoker.
Blood pressure is 155/80 mm Hg and pulse is 78/min. The patient is somnolent but wakes easily to voice. She is oriented to place and person but not to time. Cardiopulmonary examination reveals no abnormalities. The abdomen is soft and nontender with normal bowel sounds. Cranial nerve examination is normal. She has mild weakness of the left leg with exaggerated knee reflex, but all other deep tendon reflexes are normal. Vibration sensation is decreased in both feet. Romberg test with eyes closed reveals mild unsteadiness.
Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.7/5 (79)
(79) A 50-year-old man comes to the physician for follow-up of epigastric pain. He was evaluated in the emergency department 3 days ago. Abdominal CT scan with and without contrast showed a 2-cm left adrenal mass. The lesion was homogenous with well-defined margins and low x-ray attenuation (2 Hounsfield units measured on noncontrast images). The abdominal pain resolved with antacids. The patient has no other medical problems and takes no medications. He denies weight gain, headache, flushing, sweating, muscle weakness, myalgias, or polyuria. He smokes 5 cigarettes a day but does not drink alcohol or use illicit drugs. Family history is unremarkable.
His blood pressure is 112/76 mm Hg and pulse is 67/min. His BMI is 25 kg/m2. The physical examination is unremarkable.
Laboratory results are as follows:
 What is the most appropriate next step in managing this patient?
 (Multiple Choice)
4.9/5 (71)
(71) A 52-year-old man comes to the physician for intermittent sore throat, nocturnal high fevers, cold sweats, fatigue, anorexia, and weight loss over the last 4 weeks. He also complains of pain and swelling of his hands and wrists and brief episodes of a rash. He does not recall any tick bites and has no travel history or ill contacts. His temperature is 39 C (102.2 F), blood pressure is 100/70 mm Hg, and pulse is 92/min. Oropharyngeal mucosa is dry without exudates. There are several enlarged cervical lymph nodes. A scarce macular, nontender, purple rash is noted on both arms. There are no heart murmurs. Splenomegaly is noted. Synovitis is present in several joints including both hands, wrists, and elbows. A moderate effusion is present in the left knee joint. Laboratory results are as follows:
 Which of the following is the most likely diagnosis?
 (Multiple Choice)
4.9/5 (79)
(79) A 67-year-old man comes to an urgent care clinic with skin rash and malaise over the last several days. He has a history of hypertension and suffered an ischemic stroke 2 years earlier. One month ago, he had an episode of new-onset tonic-clonic seizures and was hospitalized for 2 days. MR imaging of the brain during that admission showed no intracranial mass lesion. Electroencephalogram done at that time was normal. His current medications include aspirin, rosuvastatin, valsartan, amlodipine, and phenytoin. He does not use tobacco, alcohol, or illicit drugs.
The patient's temperature is 38.2 C (100.8 F), blood pressure is 120/80 mm Hg, and pulse is 85/min. Oral examination shows mild pharyngeal erythema but no mucosal ulcerations. There are numerous and diffuse erythematous macules and papules present on the trunk and proximal extremities. Enlarged lymph nodes are palpated in the cervical, axillary, and inguinal areas. The remainder of the examination is within normal limits.
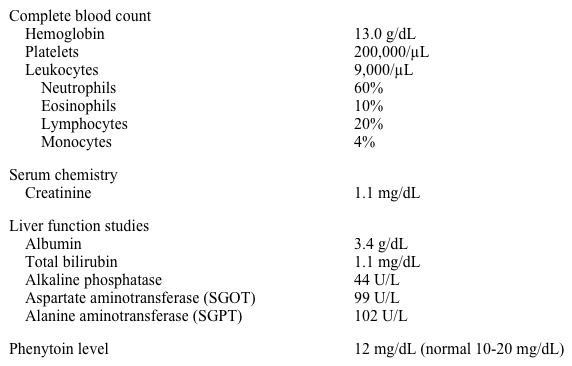
Laboratory results are as follows:
 What is the best next step in management of this patient?
 (Multiple Choice)
4.9/5 (85)
(85) A 25-year-old woman comes to the office due to poor sleep quality and daytime sleepiness. She has a 10-year history of intermittent asthma symptoms, which had been well-controlled with a combination inhaled corticosteroid and long-acting beta agonist (ICS-formoterol) as needed once every few days. The patient relocated to the Southeast for work 3 months ago and now has frequent awakenings throughout the night due to cough and wheezing. Lately, she has been using her rescue inhaler at night 2 or 3 times a week. The patient does not get enough rest at night and feels sleepy during the day. She has no other medical concerns but reports occasional indigestion. She does not report heartburn or regurgitation during the episodes of nocturnal coughing. The patient has gained 3.7 kg (8.2 lb) since moving, which she attributes to interruption of her usual exercise routine and a difficult work schedule. Her roommate has told her that she snores.
Vital signs are within normal limits and BMI is 26 kg/m2. Neck circumference is 35.5 cm (14 in). On examination, the nares are clear, the pharyngeal mucosa appears normal, the tonsils are not enlarged, and the uvula is fully visible. Retrognathia is not present. Heart sounds are regular and jugular venous pressure is normal. The lungs are clear to auscultation. The abdomen is soft and nontender. There is no lower extremity edema.
Pulmonary function testing shows FEV1 of 2.76 L (72% of predicted value) and FEV1/FVC ratio of 0.65. Bronchodilator responsiveness is present. Complete blood count and metabolic panels are within normal limits.
Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (82)
(82) A physician practices oncology in a suburb 15 miles outside of a large city. She presently refers patients in need of special imaging studies to one of two centers in the city depending on the patient's home location and medical history. Recently, a respected radiologist informs the physician that he has joined a for-profit imaging center with the latest equipment and technology. The company is considering opening a new location in the physician's area. The radiologist states that this center would provide the highest quality of care and that an opportunity now exists to invest in this new center. He adds that more local investors will increase the likelihood that the company will locate their new center in the physician's suburb. The physician is interested in investing in the new center.
Which of the following most accurately describes the conflict of interest regarding the physician's referral practices and potential investment in this center?
(Multiple Choice)
4.8/5 (69)
(69) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)