



 Chat with AI
Exam 3: Office/Health Center

Exam 1: Emergency Department218 Questions
Exam 2: In-patient Facilities128 Questions
Exam 3: Office/Health Center900 Questions
Select questions type


A 36-year-old woman comes to the physician with knee pain that started 2 weeks earlier. The pain is localized anteriorly in both knees and is greater in the left. She moved to a new 2-story house 3 weeks ago and has used the stairs many times. Lately she has experienced severe pain when ascending or descending the stairs. The pain also increases after prolonged rest. The patient has no obvious knee trauma or swelling. When she tried to run every day 3 months ago, she developed similar symptoms and had to stop. Her only other medical problem is psoriasis on her elbows, for which she uses corticosteroid and vitamin D combination ointment.
Vital signs are normal. BMI is 34 kg/m2. There is no joint line tenderness, redness, warmth, or effusion noted in either knee. Range of motion is normal with mild crepitus. Directly compressing the patella while the leg is extended elicits pain. Valgus and varus stress testing are normal. Lachman, McMurray, and anterior and posterior drawer tests are normal.
Which of the following is the best next step in management?
(Multiple Choice)
4.9/5  (64)
(64) A 72-year-old man comes to the office accompanied by his daughter. She relates that he is not doing well and frequently does not answer his phone until noon. There was little food in the refrigerator when she visited recently. The patient appears to care less about his grooming and appearance lately and does not seem to be eating well. His wife died 2 years ago. After a period of mild depression immediately following her death, he felt better and has continued to live independently.
The patient says that he is doing fine. He admits to insomnia (frequent awakenings in the middle of the night) and not eating well. He spends his days playing cards with friends and watching televised sports and news programs. He has been to the emergency department twice in the last 8 months, once to be checked after a minor motor vehicle accident and once after suffering a shoulder injury in a fall. The patient appears to be his stated age on general examination. Blood pressure is 148/90 mm Hg and pulse is 84/min. BMI is 18 kg/m2. His general examination is unremarkable. The patient scores 27/30 on the Mini-Mental State Examination. He has no suicidal ideation. There are no focal neurologic findings.
Laboratory results are as follows:
 Which of the following is the most likely primary cause of the patient's decline?
 (Multiple Choice)
4.9/5 (87)
(87) A 67-year-old woman comes to the physician because of edema and shortness of breath. She reports that the edema has been present for approximately 3-4 months and involves her lower extremities. The shortness of breath occurs with minimal exertion and occasionally at rest. She denies chest pain or pressure, cough, and fever.
She has history of breast cancer diagnosed 12 years ago that was treated with mastectomy, chemotherapy, and chest wall radiation therapy. Her medications include aspirin, fish oil, and simvastatin.
Her blood pressure is 115/70 mm Hg, pulse is 62/min, and BMI is 27 kg/m2. The patient is in no acute distress. Her lungs are clear bilaterally. There is a normal S1 and S2 with a 2/6 apical murmur that radiates to the axilla. She has 3+ pitting edema below the knees bilaterally.
Her electrocardiogram is shown below.
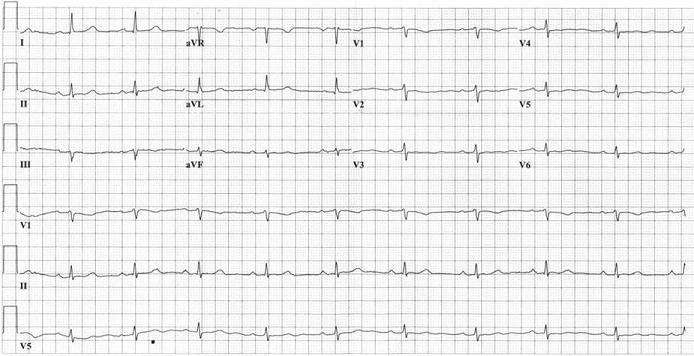 A transthoracic echocardiogram shows a normal left ventricular cavity size, a left ventricular ejection fraction of 70%, biatrial dilatation, severe left ventricular hypertrophy, and moderate mitral regurgitation.
Which of the following is the most likely additional finding in this patient?
A transthoracic echocardiogram shows a normal left ventricular cavity size, a left ventricular ejection fraction of 70%, biatrial dilatation, severe left ventricular hypertrophy, and moderate mitral regurgitation.
Which of the following is the most likely additional finding in this patient? (Multiple Choice)
4.8/5 (83)
(83) A 48-year-old woman comes to the clinic for follow-up. Three months ago, the patient experienced sudden-onset chest pain and dyspnea after undergoing an elective cholecystectomy. Examination revealed a left lower lobe segmental pulmonary embolism with co-existing right femoral deep venous thrombosis. Treatment with an oral factor Xa inhibitor was started and her symptoms have since resolved. The patient has had no bleeding or other adverse drug effects. She has no other medical problems and takes no other medications. She does not use tobacco, alcohol, or injection drugs. Family history is unremarkable.
Vital signs are within normal limits. BMI is 31 kg/m2. Physical examination reveals normal heart sounds with no murmur. Lungs are clear to auscultation bilaterally. The bilateral lower extremities are normal. The remainder of the physical examination shows no abnormalities.
Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.8/5 (78)
(78) A 52-year-old man comes to the office due to difficulty falling asleep, frequent nighttime awakenings, and daytime fatigue for the past several months. It takes him over an hour to fall asleep, and he often awakens at 2 AM and again at 4 AM. During the day, the patient struggles to stay awake during long staff meetings. He experiences no snoring, shortness of breath, or chest pain. The patient recently went through a divorce and is under financial pressure to make childcare payments. He has a history of hypertension and hypercholesterolemia. Family history is significant for coronary artery disease and emphysema. The patient smokes a pack of cigarettes a day. He drinks 2 or 3 cups of coffee every morning, an energy drink in the afternoon 1 or 2 days a week, and a beer with dinner.
On physical examination, blood pressure is 125/78 mm Hg and pulse is 74/min. BMI is 30 kg/m2. The remainder of the examination is normal.
Laboratory studies include a hematocrit of 43%, a leukocyte count of 5,300/mm³, a fasting plasma glucose of 100 mg/dL, and a serum TSH level of 2.3 µU/mL. Results of a chest radiograph and ECG are normal.
Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.8/5 (77)
(77) A 41-year-old woman comes to the office for a routine follow-up visit. The patient has had malaise and mild abdominal discomfort over the last 3-4 months. Her other medical problems include hypertension, type 2 diabetes mellitus, hyperlipidemia, asthma, and osteoarthritis. The patient also has a history of breast cancer treated with lumpectomy 5 years ago. She smokes a pack of cigarettes daily and drinks 1 or 2 glasses of wine on the weekends. Medications include glyburide, metformin, lisinopril, amlodipine, albuterol, and acetaminophen. The patient stopped taking a statin 2 months ago due to muscle aches.
Blood pressure is 141/78 mm Hg and pulse is 78/min. BMI is 32 kg/m2. There is no jugular venous distension. Bilateral scattered wheezes are heard on expiration. The liver edge is palpated 3 cm below the costal margin. No splenomegaly is present. There is 1+ pitting edema of both ankles.
Laboratory results are as follows:
 Which of the following is the most likely mechanism of hepatomegaly in this patient?
 (Multiple Choice)
4.9/5 (80)
(80) A 65-year-old woman with a history of rheumatoid arthritis comes to the physician with persistent hand pain aggravated by use. She was prescribed tramadol and occupational therapy 1 year ago and has had no relief. Rheumatoid arthritis was diagnosed 20 years ago, and she was started on methotrexate, prednisone, and hydroxychloroquine at that time. She was prescribed etanercept 10 years ago and switched to adalimumab 5 years later due to persistent disease activity. The patient's other medical problems include hypertension and acid reflux disease. Her current medications include methotrexate, hydroxychloroquine, adalimumab, tramadol, prednisone, and ibuprofen. She does not use tobacco, alcohol, or illicit drugs.
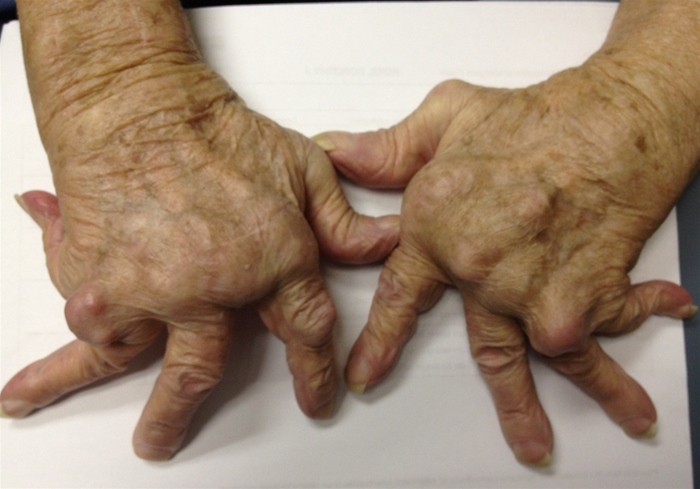
Her vital signs are normal. Musculoskeletal examination is notable for the presence of rheumatoid deformities in the hands (shown below) and feet. There is no joint tenderness or effusion. Neurological examination is within normal limits.
 Laboratory results are as follows:
 Which of the following is the most appropriate next step in management?
Laboratory results are as follows:
Which of the following is the most appropriate next step in management? (Multiple Choice)
4.9/5 (94)
(94) A 30-year-old man comes to the physician for a pre-employment physical examination. He has no past medical history. He exercises regularly and tries to eat a healthy diet.
The patient's blood pressure is 122/70 mm Hg and pulse is 78/min and regular. The jugular venous pressure is estimated at 5 mm H2O. There are no carotid bruits. A 3/6 short systolic murmur is heard at the left lower sternal border and the apex in the supine position, and the murmur gets longer with standing. There is a normal splitting of the second heart sound. The apical impulse is not displaced. Femoral pulses are full and symmetric.
Which of the following is the most likely diagnosis?
(Multiple Choice)
4.9/5 (98)
(98) A 50-year-old woman comes to the office to follow up type 2 diabetes mellitus. She was diagnosed 5 years ago and is treated with metformin at the maximal tolerated dose. She has been unable to lose weight despite following a healthy diet and exercising at least 5 times a week. The patient has no chronic complications of diabetes but has had recurrent episodes of vaginal candidiasis in the last 2 years. She works as a commercial bus driver for a tourist company and does not use tobacco, alcohol, or illicit drugs.
Vital signs are normal. BMI is 27 kg/m2. Physical examination is otherwise unremarkable. Serum creatinine is 1 mg/dL, fasting glucose is 156 mg/dL, and hemoglobin A1c is 7.9%. Six months ago her A1c was 7.2%.
When added to metformin, which of the following medications is most appropriate for this patient?
(Multiple Choice)
4.8/5 (75)
(75) An 82-year-old man is evaluated for dizziness. He has felt dizzy for the past year, and the sensation is worsening. The dizziness occurs primarily when he ambulates; however, it does not bother him while seated or recumbent, and is not accentuated by head turning. He denies a sensation of spinning or movement, headache, focal weakness, palpitations, or muscle pain. He fell twice over the last year, but he did not sustain any significant injuries. His hearing has been poor for several years. He has visual difficulties which makes reading difficult.
He has a history of diet-controlled diabetes mellitus, degenerative joint disease of his knees and hips, hypertension, chronic obstructive pulmonary disease, mild cognitive impairment, hyperlipidemia, and post-herpetic neuralgia. His medications include chlorthalidone, ibuprofen, acetaminophen, lovastatin, and a tiotropium inhaler.
His blood pressure is 136/70 mm Hg supine and 130/72 mm Hg standing, and pulse is 84 /min. There is a 2/6 holosystolic murmur at the apex. Breath sounds are generally decreased. Hearing is grossly decreased in both ears. Vision corrects to 20/70 in both eyes. His cranial nerves are intact. There is no nystagmus. Deep tendon reflexes are symmetric. There is decreased vibration, position, and light touch sensation below the knees bilaterally. He cannot walk heel-to-toe, and the Romberg test is positive. He has a slightly broad-based gait with decreased accessory movement. Rapid alternating movements are decreased symmetrically. His score on a Mini-Mental State Examination is 25/30, decreased from 26/30 one year ago. He answers two depression screening tests normally.
Lab tests, including a complete blood count, comprehensive metabolic panel, B12 level, serum RPR, and thyroid function tests are normal. A hemoglobin A1C is 7.5%. An electrocardiogram reveals normal sinus rhythm and left ventricular hypertrophy.
The patient would most likely benefit from which of the following?
(Multiple Choice)
4.9/5 (87)
(87) A 54-year-old man comes to the physician with chest discomfort. During the last 6 months, the patient has had left-sided chest pain radiating to the left shoulder, which is commonly provoked by exertion but also occurs at rest. The chest pain lasts a few seconds to several minutes, and he can usually "walk it off." Past medical history includes hypertension, hyperlipidemia, and peptic ulcer disease. The patient received a permanent pacemaker 6 years ago after an episode of syncope. His father also had a pacemaker. Current medications include lisinopril, amlodipine, famotidine, and rosuvastatin.
His blood pressure is 111/70 mm Hg and pulse is 67/min. Chest is clear to auscultation. No cardiac murmurs or carotid bruits are appreciated. The abdomen is nontender. Pulses are full and symmetric bilaterally.
Electrocardiogram shows normal sinus rhythm with paced ventricular complexes (atrial sensed, ventricular paced rhythm).
Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (88)
(88) A 41-year-old woman comes to the office due to irregular menstrual periods and intermittent milky discharge from both breasts for the past 6 months. During this time, she has also had vaginal dryness and dyspareunia. The patient has had no headaches, visual loss, weight changes, or hirsutism. She has had no prior medical problems and takes no medications except for over-the-counter vitamin supplements.
Blood pressure is 112/70 mm Hg and pulse is 66/min. BMI is 21 kg/m2. Physical examination shows no abnormalities except mild expressive galactorrhea from both breasts.
Laboratory results are as follows:
 Serum chemistry is within normal limits. MRI of the brain shows a 7-mm pituitary mass. The patient is very reluctant to start any treatment.
Which of the following is the patient at an increased risk of developing if her current condition is left untreated?
Serum chemistry is within normal limits. MRI of the brain shows a 7-mm pituitary mass. The patient is very reluctant to start any treatment.
Which of the following is the patient at an increased risk of developing if her current condition is left untreated? (Multiple Choice)
4.9/5 (88)
(88) A 30-year-old woman comes to the office due to concerns about her weight despite losing 10.9 kg (24 lb) in the past 6 months. She says, "I still feel very unattractive and I am afraid that my weight problems are destroying my marriage." During the past 5 years, the patient has had wide fluctuations in her weight, and at one point weighed 104.3 kg (230 lb). Much of this weight gain occurred surrounding her 2 pregnancies, the last being over 2 years ago. She is typically home all day caring for the children. At times the patient will consume large quantities of food, only to vomit intentionally before her husband returns from work. On weekends when her husband is home, she avoids this behavior and instead reduces her food consumption dramatically. She becomes anxious if her husband returns home early for fear that he will witness her overeating or vomiting. The patient is angry at her husband and also at herself for not having better control of her life. She denies feelings of depression or hopelessness but does feel overwhelmed.
On examination, the patient's vital signs are within normal limits. BMI is 25.3 kg/m2.
In addition to psychotherapy, which of the following is the most appropriate management for this patient?
(Multiple Choice)
4.8/5 (72)
(72) A 45-year-old woman comes to the physician because of exertional dyspnea and fatigue. She has been gaining weight lately due to her sedentary lifestyle and started exercising with the help of a professional trainer. She becomes short of breath easily and attributes this to deconditioning. However, she had a near syncopal episode during her last exercise session. She denies dyspnea, fatigue at rest, cough, chest pain, morning headaches, nocturnal awakenings, snoring, or mood changes.
Her other medical problems include a history of pulmonary embolism (PE) 3 years ago after an abdominal hysterectomy for complex atypical endometrial hyperplasia. She received anticoagulation for six months and has been doing well since then. She quit smoking after the pulmonary embolism and denies using alcohol or illicit drugs. Her mother has a history of rheumatoid arthritis and her father died from an acute myocardial infarction.
Vitals signs and complete physical examination are within normal limits. Her BMI is 26 kg/m2.
Complete blood count, liver function tests, and serum chemistries are within normal limits. Chest x-ray and high resolution CT scan of the chest without contrast showed no abnormalities. Echocardiogram shows normal left ventricular size and function, moderate right ventricular enlargement, and an estimated pulmonary artery systolic pressure of 60 mm Hg. Pulmonary function tests are within normal limits.
Which of the following is the most appropriate next step in management?
(Multiple Choice)
4.9/5 (70)
(70) A 38-year-old woman with type 2 diabetes mellitus comes to the office for follow-up. Although her laboratory results indicate good glycemic control, she describes low energy, fatigue, and difficulty concentrating at work. Further evaluation reveals that the patient has become increasingly depressed over the past month. She says, "All I do is work and then go home so I can get in bed and sleep. I feel bad that I stopped exercising. It takes too much effort see my friends or date and I have no interest in sex." The patient has no psychiatric history. Her sister takes paroxetine for depression and anxiety with good results.
Physical examination is unremarkable apart from a BMI of 27.9 kg/m2 and a 2.26-kg (5-lb) weight gain since her last visit. Mental status examination shows depressed mood and affect and no suicidal ideation. The patient is diagnosed with major depressive disorder and treatment options are discussed.
Which of the following is the most appropriate pharmacotherapy for this patient?
(Multiple Choice)
4.9/5 (80)
(80) A 19-year-old woman comes to the office due to increasing vaginal discharge. The discharge began 6 months ago when she started taking a combined estrogen/progestin contraceptive pill. Since then, she has had multiple episodes of thin discharge accompanied occasionally by mild vulvar irritation. The discharge improves with probiotics and douches but then recurs after a week. She recently became sexually active and has had 2 lifetime partners.
Vital signs are normal. BMI is 22 kg/m2. Pelvic examination reveals a thin, slightly malodorous, clear, yellow discharge throughout the vaginal vault. There is no discharge from the cervical os and no cervical friability. Bimanual examination demonstrates no cervical motion tenderness.
Wet mount microscopy shows numerous epithelial cells and occasional polymorphonuclear leukocytes, and the pH of the discharge is 4.2. Urine pregnancy test is negative.
Which of the following is the most likely diagnosis in this patient?
(Multiple Choice)
4.8/5 (85)
(85) A 30-year-old primigravida at 18 weeks gestation comes to the office due to left calf pain and swelling that developed after a 4-hour car trip. The pain is worse with ambulation. The pregnancy was complicated by first-trimester bleeding. A recent ultrasound showed an 18-week-sized fetus with normal anatomy and no placenta previa.
Examination shows 1+ pretibial edema with pain elicited on plantar flexion of the left lower extremity. The remainder of the examination is unremarkable.
A lower extremity compression ultrasound with Doppler shows a thrombosis in the left popliteal vein.
Which of the following is the best treatment strategy for this patient?
(Multiple Choice)
4.9/5 (74)
(74) A 25-year-old primigravida at the 32nd week of pregnancy comes to the physician with increasing headaches. She describes the headaches as severe in intensity, unilateral, throbbing, and associated with light sensitivity and nausea. They currently occur once or twice a week. She has had similar headaches for the last several years that usually improve with ibuprofen and bed rest. However, she does not want to take any unsafe drugs. The patient has tried massage, relaxation, and techniques to improve her sleep without significant improvement. She has no other medical problems. Her current medications include an oral multivitamin.
Vital signs and examination are within normal limits.
Which of the following is the most appropriate course of action?
(Multiple Choice)
4.9/5 (76)
(76) A 35-year-old woman comes to the office with a tongue lesion that she noticed recently. She has no pain or difficulty swallowing. A few months earlier, she had a sexual encounter that included oral sex with a new male partner.
On examination, there is a 2-cm ulcer with induration on the dorsal aspect of the tongue. Multiple, nontender, cervical lymph nodes are present. The rest of her skin and genital examination is unremarkable.
Which of the following is the most appropriate next step in management of this patient's tongue lesion?
(Multiple Choice)
4.9/5 (89)
(89) A 59-year-old man comes to the physician with painful enlargement of both breasts for the last 2-3 weeks. He also complains of significant fatigue, loss of libido, and erectile dysfunction. His past medical history is significant for type 2 diabetes mellitus, hypertension, hyperlipidemia, and ischemic cardiomyopathy. Echocardiogram 6 months ago showed global left ventricular hypokinesis (ejection fraction 25%) and moderate mitral regurgitation. The patient's current medications include sitagliptin, candesartan, amlodipine, spironolactone, furosemide, atorvastatin, and aspirin. Spironolactone was added 8 weeks ago after he complained of dyspnea on moderate physical activity. He has also started taking over-the-counter omeprazole to "protect my stomach from my medications."
On examination, bilateral tender gynecomastia is noted. There is no jugular venous distension or pedal edema. Examination of the heart shows a 3/6 pansystolic murmur at the apex radiating to the axilla. Lungs are clear to auscultation. Testicular examination is unremarkable.
Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.8/5 (98)
(98) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)