



 Chat with AI
Exam 3: Office/Health Center

Exam 1: Emergency Department218 Questions
Exam 2: In-patient Facilities128 Questions
Exam 3: Office/Health Center900 Questions
Select questions type


A 29-year-old Middle Eastern man is evaluated for difficulty breathing and nonproductive cough for the past month. He reports difficulty walking and frequent falls over the last year but has not seen a physician. The patient has no other medical problems. He is married and has a 3-year-old son.
His blood pressure is 96/60 mm Hg and pulse is 100/min. Jugular venous pressure is estimated at 12 mm H2O. Lung examination shows bibasilar crackles. The point of maximal impulse is displaced to the left and a third heart sound is present. The proximal extremity muscles are atrophied, but both calves are prominently enlarged.
Chest x-ray shows cardiomegaly.
The son's risk of developing his father's condition is closest to which of the following?
(Multiple Choice)
4.9/5  (79)
(79) A 78-year-old woman is brought to the physician by her daughter for evaluation of pain and swelling of the left shoulder for the past 6 weeks. The swelling has progressively worsened in the past 2 weeks, with severe pain and impairment of her activities of daily living. She has a remote history of falls onto the shoulder but no recent trauma. The patient has no fever or pains in her other joints.
Her past medical history is significant for pacemaker implantation for complete heart block.
Vital signs are stable and the patient is afebrile. The left shoulder is tender with anterior swelling and a palpable fluid collection. Attempted movement at the shoulder is limited and elicits severe pain. An x-ray of the left shoulder is ordered. Laboratory results are as follows:
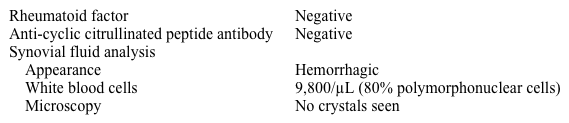 Which of the following is the most likely diagnosis in this patient?
 (Multiple Choice)
4.7/5 (82)
(82) An 82-year-old woman is brought to the clinic by her caregiver for a new leg wound. The patient has had chronic lower-extremity swelling for many years. Over the past 2 weeks, she developed a small, shallow opening on her right anterior lower leg that has slowly expanded. She has no fever, chills, warmth, or purulent drainage. The patient says that her legs often feel tired and heavy, especially when sitting for extended periods, but they improve with walking.
Her past medical history includes hypertension, degenerative joint disease, and obesity.
Vital sign signs normal. Cardiovascular examination shows normal rate and rhythm and no murmurs. Estimated jugular venous pressure is normal. The patient's lungs are clear. Lower extremities have symmetric edema bilaterally; the wound is shown in the image below. The feet are warm with palpable dorsalis pedis pulses bilaterally.
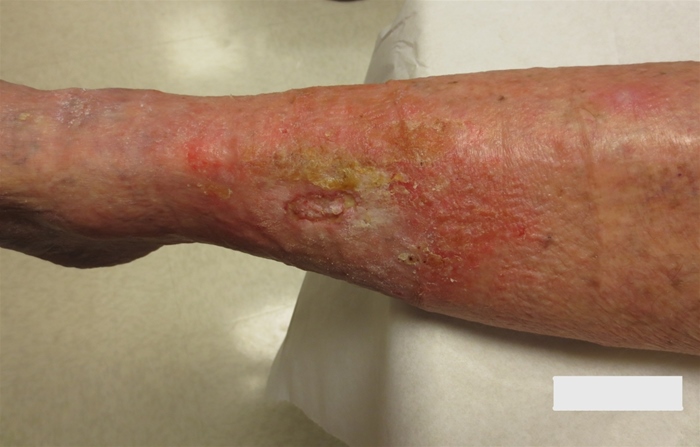 In addition to wound dressing recommendations, what is the best next step in management of this patient?
 (Multiple Choice)
4.8/5 (87)
(87) A 66-year-old woman is seen in the outpatient clinic for follow-up. The patient has no current symptoms. She has a history of hypothyroidism and takes levothyroxine replacement therapy. The patient's other medical problems include hypertension and acid reflux disease. She underwent dual-energy x-ray absorptiometry 2 months ago, which was normal. Her TSH level is <0.01 mU/L. Despite a long discussion, the patient refuses to decrease the dose of levothyroxine as lower doses make her feel "exhausted and sleepy all the time."
Which of the following is a possible complication of levothyroxine overreplacement in this patient?
(Multiple Choice)
4.8/5 (74)
(74) An 81-year-old woman is brought to the clinic with complaints of constant ringing in her ears over the last several months. She also is having difficulty hearing, especially at social gatherings and while watching television. She has had 2 episodes of near falls during the past year. The patient's other medical problems include hypertension, recurrent urinary tract infections, and osteoarthritis. Her medications include hydrochlorothiazide and acetaminophen. She takes trimethoprim-sulfamethoxazole for urinary tract infections several times a year.
Physical examination shows a normal external ear, no signs of cerumen impaction, and pearly gray tympanic membranes bilaterally with a normal light reflex. She is mildly unsteady in Romberg's position with her eyes closed. There are no carotid bruits. She has an abnormal whisper test in both ears.
Which of the following is the most likely diagnosis?
(Multiple Choice)
4.9/5 (76)
(76) A 46-year-old woman comes to the office due to frequent episodes of "choking" at night for the past 3 months. She wakes up in the middle of the night and is unable to "catch her breath." The symptoms subside slowly after she gets up and walks around. She has also experienced occasional palpitations. The patient is otherwise physically active and walks on a treadmill 5 times a week for 30-45 minutes. Other medical problems include rheumatic fever at age 12, hypertension, depression, fibromyalgia, and non-Hodgkin lymphoma treated with combination chemotherapy 10 years ago. She is a lifelong nonsmoker.
Temperature is 37.2 C (99 F), blood pressure is 122/80 mm Hg, pulse is 92/min, and respirations are 14/min. The lungs are clear to auscultation. Cardiac examination reveals a loud S1 and a "snapping" sound shortly after S2. There is a 2/6 ejection-type systolic murmur best heard over the second right intercostal space. There is also a faint mid-diastolic murmur heard over the cardiac apex. The remainder of the physical examination is unremarkable.
A transthoracic echocardiogram shows normal left ventricular size and function with an ejection fraction of 60%. The left atrium is moderately dilated. The mitral valve leaflets appear thickened with restricted opening. The estimated mitral valve area is 1.8 cm2 (normal: 4-6 cm2), consistent with moderate mitral stenosis. The aortic valve is sclerotic with mild restriction of leaflet motion and there is evidence of mild aortic stenosis. The pulmonary artery systolic pressure appears to be normal. ECG is shown in the exhibit.
Which of the following is the best next step in evaluating this patient's current symptoms?
(Multiple Choice)
4.8/5 (73)
(73) A 24-year-old man comes to the office due to a nonpruritic, painless rash over his upper and lower extremities. Vital signs are within normal limits. Skin examination shows scattered lesions, shown in the image below. He has no oral or ocular mucosal erosions.
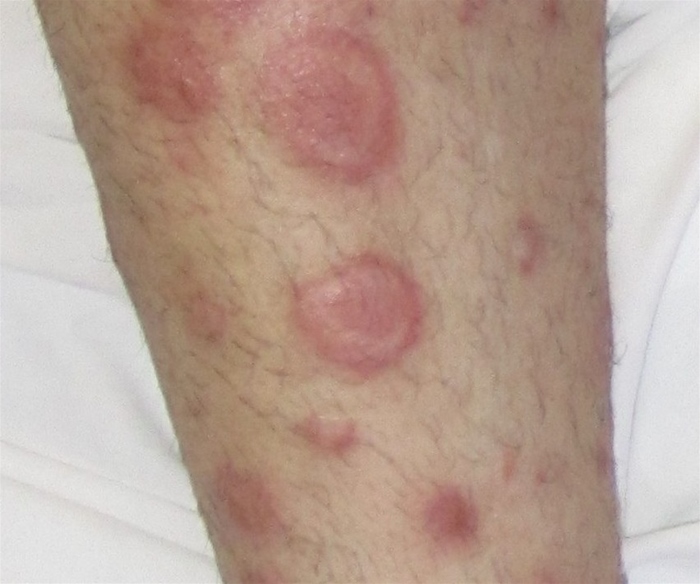 Further elaboration of medical history in this patient is most likely to reveal which of the following?
 (Multiple Choice)
4.9/5 (74)
(74) A 31-year-old woman comes to the office due to fatigue and cold intolerance. She has also experienced abdominal bloating, and states, "I can't think clearly and I feel like I am always in a fog." The patient has a history of hypothyroidism treated with levothyroxine and has required escalating doses (currently 200 mcg/day) over the last several months as her serum TSH has remained elevated. She has been compliant in taking her levothyroxine every day 1 hour before breakfast and takes no other medications or supplements. The patient had a miscarriage at age 25, and her menstrual periods have been irregular since then. She quit smoking cigarettes 10 years ago, drinks a few beers on most weekends, and does not use recreational drugs.
Blood pressure is 136/92 mm Hg and pulse is 66/min. BMI is 30 kg/m2. Examination shows diffuse firm enlargement of the thyroid gland. Cardiopulmonary and abdominal examinations are unremarkable.
Laboratory results are as follows:
 Which of the following is the most appropriate diagnostic study for this patient?
 (Multiple Choice)
4.7/5 (71)
(71) An 18-year-old woman comes to the office due to 3 days of right foot pain. She is a ballet dancer and has been practicing intensely over the last few weeks for an upcoming show. The patient is under a lot of stress and is worried that the pain may limit her practice sessions. She has no medical history other than a left tibia stress fracture a year ago. The patient has irregular menses, and her last menstrual period was 12 weeks ago. She does not use tobacco, alcohol, or illicit drugs.
BMI is 17 kg/m2. There is focal tenderness over the right fourth metatarsal shaft. Urine pregnancy test is negative.
Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.9/5 (54)
(54) A 52-year-old woman with recently diagnosed rheumatoid arthritis comes to the physician complaining of decreased appetite, sore throat, and mild nausea for the past 2 weeks. She has no fevers, vomiting, or dark or bloody stools. She has been treated with oral naproxen daily and methotrexate weekly for the last 6 weeks with improvement of joint symptoms. She also takes ranitidine for occasional heartburn and senna for chronic constipation.
Her temperature is 36.7° C (98° F), blood pressure is 120/70 mm Hg, and pulse is 78/min. Oral examination shows several shallow ulcers on the buccal mucosa and hard palate as well as mild pharyngeal erythema. No enlarged lymph nodes are palpated. There are no skin rashes. The abdomen is soft and nontender. The small hand joints are mildly swollen and tender to palpation bilaterally. A small effusion is present in the right knee.
Laboratory results are as follows:
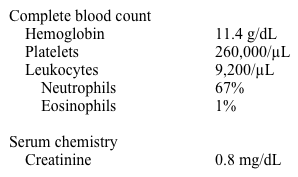 Liver function tests are normal.
Which of the following is the best next step in management of this patient?
Liver function tests are normal.
Which of the following is the best next step in management of this patient? (Multiple Choice)
4.9/5 (85)
(85) A 32-year-old man comes for evaluation of a bump on the right side of his chest. He initially noticed it 4 months ago, and it has grown slightly larger in the past month. The patient has not experienced any trauma to the area or recent surgeries. He does not use tobacco or alcohol.
Skin examination is shown below. There is no drainage from the lesion or tenderness to palpation. The lesion does not change in shape when pinched at the edges. The remainder of his physical examination is within normal limits.
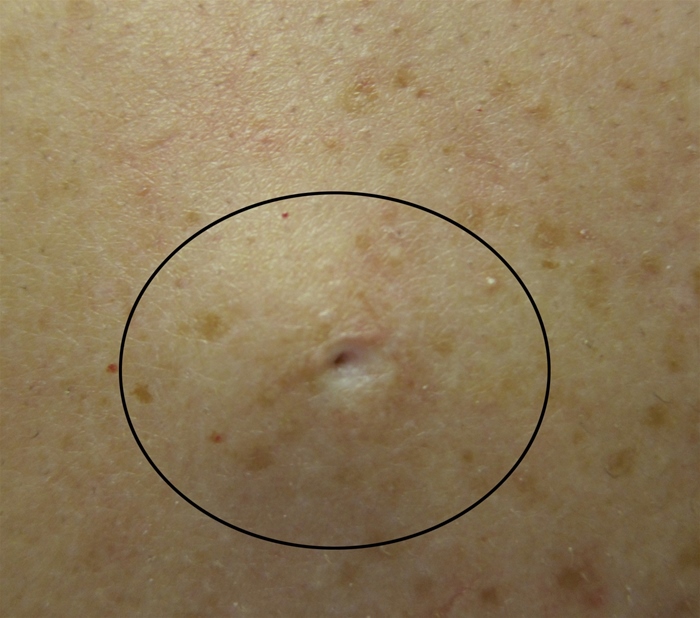 Which of the following is the most likely diagnosis?
 (Multiple Choice)
4.8/5 (66)
(66) A 73-year-old woman comes to the clinic complaining of acute onset of urinary incontinence after recent hospitalization for total knee replacement. Over the last 3 days, she has had 5-10 episodes of spontaneous urinary leakage daily. She also has had small, loose bowel movements. The patient has no urgency, increased frequency, dysuria, hematuria, or involuntary leakage associated with coughing, sneezing, or laughing. There is no recent history of fever or chills.
Her other medical problems include hypertension, well-controlled type 2 diabetes mellitus with HbA1c of 6.9%, and chronic constipation. Her medications include metformin, glipizide, lisinopril, amlodipine, docusate, and oxycodone. She has not changed her diet or increased her caffeine intake. Her stable routine includes 1or 2 alcoholic beverages each night. She has 4 children, all of whom were delivered vaginally.
Her vital signs are within normal limits. The abdomen is distended and mildly tender to palpation in the lower quadrants. Rectal examination shows hard stool in the rectal vault. Pelvic examination shows no thinning or pallor of the vaginal mucosa and no evidence of vaginal wall prolapse.
Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.9/5 (84)
(84) A 25-year-old obese woman comes to the office due to sudden onset of blurry vision and pain in her left eye with a headache that began 2 days ago. She was watching television when she noticed a throbbing headache behind her left eye and eye pain that is exacerbated with movement. She has also noticed that colors in her visual field, especially red, have become less bright. She has had no diplopia, vertigo, dysphasia, pulsatile tinnitus, dysarthria, or weakness.
Medical history is unremarkable. Family history is significant for stroke and diabetes mellitus. The patient takes no medications except for birth control pills. She is a stay-at-home mom and does not use tobacco, alcohol, or illicit drugs.
Blood pressure is 130/80 mm Hg and pulse is 88/min and regular. The patient is awake, alert, and oriented. Cranial nerve testing reveals a visual acuity of 20/30 in the right eye and 20/200 in the left eye. Funduscopic examination of both eyes is unremarkable. The pupils are round and symmetrical; however, there is a relative afferent pupillary defect on the left with the swinging flashlight test. Muscle power is 5/5 and deep tendon reflexes are 2+ in all 4 extremities. The remainder of the neurological examination is unremarkable.
Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (82)
(82) A 35-year-old woman comes to the physician for evaluation of a rash on her hands. She noted the onset of periungual swelling around all her fingers 2 weeks ago. She subsequently developed a rash with stinging pain and burning on some of her fingertips. The patient has worked as a manicurist for the past 10 years and has worn artificial nails intermittently for the past 2 years. She has a history of hypothyroidism and gastroesophageal reflux disease. Her medications include omeprazole and levothyroxine. She has no history of tobacco or alcohol use.
Vital signs are within normal limits. Skin examination of the fingers reveals mild warmth, edema, and tenderness to palpation. There are also fissures at the distal fingers. Neurological examination shows decreased sensation at the patient's fingertips. The remainder of her physical examination is normal.
Which of the following is the most likely diagnosis?
(Multiple Choice)
4.7/5 (77)
(77) A 57-year-old man with prostate cancer comes to the office due to progressive lower back pain. He rates the pain as 7 on a scale of 0-10. The patient has been taking nonsteroidal anti-inflammatory drugs and acetaminophen, which are no longer providing pain relief. He has had no lower extremity weakness or numbness, falls, or urinary or fecal incontinence. The patient was diagnosed with prostate cancer 3 years ago and was recently found to have multifocal bone metastases. He takes leuprolide and zoledronic acid.
Temperature is 37.2 C (99 F), blood pressure is 150/90 mm Hg, and pulse is 98/min. Examination shows tenderness to percussion along his lower spine. The abdomen is soft and nontender. Rectal examination reveals an enlarged and firm prostate and normal rectal tone. Lower extremity motor power, deep tendon reflexes, and sensation are normal.
Laboratory results are as follows:
 Imaging studies show multiple osteoblastic lesions in the thoracic and lumbar spine without evidence of compression fractures.
Which of the following is the best next step in management of this patient's pain?
Imaging studies show multiple osteoblastic lesions in the thoracic and lumbar spine without evidence of compression fractures.
Which of the following is the best next step in management of this patient's pain? (Multiple Choice)
4.8/5 (80)
(80) An 85-year-old woman is brought to the emergency department with headache and right-sided weakness. Family members report that she was in her usual state of health until 2 hours ago. Six months ago, the patient had an intracerebral hemorrhage into the right occipital lobe. Past medical history includes hypertension and type 2 diabetes mellitus. She was treated for locally invasive breast cancer 7 years ago with surgery and chemotherapy.
Her blood pressure is 150/90 mm Hg and pulse is 90/min. Neurologic examination shows right hemiparesis with right facial droop, dysarthria, and right hemisensory loss.
Noncontrast CT of the head reveals a moderate-sized, left frontoparietal lobar hemorrhage with mass effect. MRI of the brain with and without gadolinium shows no enhancement or acute infarction.
Which of the following is the most likely cause of this patient's current condition?
(Multiple Choice)
4.9/5 (68)
(68) A 61-year-old woman comes to the office due to insomnia. She describes difficulty both falling and staying asleep over the past 6 months. Her insomnia varies and is much worse some days than others. In the mornings, she wakes up half an hour earlier than she would like and rarely feels well rested. The patient has tried several over-the-counter sleep medications, but they make her feel too tired the next day. She is not aware if she snores. The patient drinks a glass of wine several times a week and does not use illicit drugs. She has a history of osteoarthritis and major depression for which she takes ibuprofen and venlafaxine. She has lived alone since her divorce 2 years ago and maintains close relationships with her adult children and grandchildren. The patient is worried about one son who recently lost his job, but she has had no change in mood or appetite. Physical examination is noncontributory.
Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.8/5 (80)
(80) A 51-year-old man comes to the physician after recently returning from a trip to Bangladesh. He reports 1 week of fever and left lower-quadrant abdominal pain. His medical problems include type 2 diabetes mellitus and hypertension. The patient does not use tobacco, alcohol, or illicit drugs. His current medications include metformin and lisinopril.
His temperature is 103° F (39.4 C), blood pressure is 120/70 mm Hg, pulse is 72/min, and respirations are 14/min. Examination shows an uncomfortable-appearing man in no acute distress. There is an erythematous, macular, patchy rash across his lower abdomen. The abdomen is soft with left lower-quadrant tenderness. There is no rebound tenderness or involuntary guarding. The remainder of the examination is unremarkable.
Laboratory results are as follows:
 Which of the following is the most likely diagnosis?
 (Multiple Choice)
4.8/5 (80)
(80) An 84-year-old woman comes to the office due to a fall. She was walking through a hallway in the evening when she tripped and fell on her left hip. She had no symptoms preceding the fall and no loss of consciousness. The patient, who lives alone, lay on the floor for about an hour before her daughter found her. She sustained only minor bruising on her left side. The patient experienced a similar fall 8 months ago. Medical history is notable for osteoarthritis in the hands and knees, chronic low back pain, chronic constipation, and osteoporosis. Current medications include acetaminophen, docusate, calcium, vitamin D, and alendronate.
Blood pressure is 155/70 mm Hg supine and 150/73 mm Hg standing, and pulse is 78/min and regular. Crepitus is noted on flexion of the knees bilaterally. The hips have full range of motion bilaterally and normal log rolls. Muscle strength is normal in all extremities. Pinprick and light touch sensations are intact.
X-rays of the left hip and pelvis reveal no fractures.
Which of the following is the best next step to reduce this patient's risk for further falls?
(Multiple Choice)
4.9/5 (72)
(72) A 27-year-old man comes to the office to discuss HIV prevention. One of his sexual partners is an HIV-positive man who intermittently adheres to antiretroviral therapy, and the patient also has sexual encounters with men of unknown HIV status. The patient does not reliably use condoms due to loss of sensation during intercourse. He is concerned about his risk of HIV infection and is interested in the use of antiretroviral therapy or pre-exposure prophylaxis (PrEP) to prevent contracting the disease. The patient has had no recent fever, weight loss, rash, or malaise. He was diagnosed with gonococcal urethritis 3 months ago and was treated with antibiotics; he has no other medical history. The patient occasionally uses intranasal cocaine prior to intercourse and drinks a few beers on weekends. He does not use tobacco or injection drugs.
The patient's vital signs are within normal parameters, and physical examination is significant only for diffuse tattoos over the upper extremities. Serum chemistry is normal, and viral hepatitis screening is positive for hepatitis C IgG antibody alone. HIV testing is negative. After careful discussion about safe sex practices, which of the following is the most appropriate next step regarding PrEP use in this patient?
(Multiple Choice)
4.8/5 (73)
(73) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)