



 Chat with AI
Exam 3: Office/Health Center

Exam 1: Emergency Department218 Questions
Exam 2: In-patient Facilities128 Questions
Exam 3: Office/Health Center900 Questions
Select questions type


A 40-year-old man comes to the physician for an insurance physical. He has no current complaints. His medical problems include borderline hypertension and seasonal allergies. He takes fexofenadine. He does not smoke and drinks 1-2 alcoholic beverages per weekend. His family history is remarkable for an uncle who died suddenly in his 30s while playing basketball. His older brother had two unexplained syncopes.
His blood pressure is 120/70 mm Hg, pulse is 88 /min, and respirations are 12 /min. The patient's pulse oximetry showed 98% on room air. His BMI is 23 kg/m2. There is a 3/6 systolic murmur heard at the mid and upper sternum bilaterally. Carotid upstrokes are delayed. The intensity of the murmur decreases when the patient assumes a standing position from a sitting position.
Which of the following is the most likely diagnosis?
(Multiple Choice)
4.9/5  (81)
(81) A 43-year-old man seeks care for a painful testicle. The discomfort started 2-3 days ago and has progressed to sharp left testicular pain every time he steps down with his left foot. He has no fever, chills, or dysuria. He has been in a stable monogamous relationship for 20 years and denies anal sexual intercourse. He has not had this problem previously. There is no history of trauma to the area. He considers himself in good health and takes no medications.
His temperature is 37.4 C (99.4 F), blood pressure is 130/80 mm Hg, and pulse is 84/min. Cremasteric reflexes are normal bilaterally. He has no skin lesions involving the genitalia and no palpable inguinal lymph nodes. The scrotum is warm, and the left testicle feels slightly swollen with severe tenderness to palpation, especially over its posterior aspect. There are no inguinal hernias. There is no urethral discharge.
A urinalysis is normal.
Which of the following is the most likely diagnosis?
(Multiple Choice)
4.8/5 (83)
(83) A large multicenter double-blinded randomized placebo-controlled study is being planned to evaluate a new medication. Primary endpoints addressing mortality benefits are chosen, and a comprehensive analysis strategy is specified, including for predefined subgroups.
In discussing the advantages of this study design, which of the following represents a benefit of randomization?
(Multiple Choice)
4.9/5 (85)
(85) A 24-year-old man comes to the physician due to right eye pain for the last 12 hours. When he opens his right eyelid, he feels a foreign body sensation in the eye. Prior to onset of the pain, he was hiking off-trail with a friend and was hit in the face with 2 tree branches. The patient has rubbed his eyelid several times and washed the eye with ocular solution without any relief. He does not wear contact lenses.
Examination of the right eye shows a small, round, and reactive pupil. The conjunctiva is red with no purulent discharge. There is no evidence of penetrating injury or visible foreign body. The anterior chamber is clear. There is a red reflex. Fluorescein staining under cobalt blue filter of an ophthalmoscope shows a small linear stain across the central cornea. Visual acuity screening shows 20/40 in the affected eye.
In addition to measures that reduce pain, which of the following is the best management for this patient?
(Multiple Choice)
4.8/5 (78)
(78) A 28-year-old man comes to the office for follow-up of hypertension. The patient has a 6-month history of fatigue and occasional headaches. When he came for evaluation 3 weeks ago, his blood pressure was 160/100 mm Hg. Medical history is unremarkable and he takes no medications. He has no family history of stroke or early heart disease. The patient smokes a pack of cigarettes daily but does not use alcohol or illicit drugs.
Blood pressure is 164/102 mm Hg and pulse is 82/min. BMI is 28 kg/m2. Physical examination is unremarkable.
Laboratory results are as follows:
 ECG shows normal sinus rhythm without ischemic changes. Urinalysis shows 1+ proteinuria. CT scan of the abdomen reveals normal adrenal glands.
Which of the following is the best next step in management of this patient's disorder?
ECG shows normal sinus rhythm without ischemic changes. Urinalysis shows 1+ proteinuria. CT scan of the abdomen reveals normal adrenal glands.
Which of the following is the best next step in management of this patient's disorder? (Multiple Choice)
4.9/5 (82)
(82) An 80-year-old woman comes to the office accompanied by her nephew, who helps take care of her. The patient lives alone and rarely leaves the house. She has a history of hypertension, osteoporosis, type 2 diabetes mellitus, and cognitive impairment (Mini-Mental Status Exam score of 23 out of 30). She received treatment for a spiral fracture of the humerus a year ago. The patient performs most of her activities of daily living unassisted but needs help with cooking, cleaning, and shopping. She reports no new problems today. Medications include metoprolol, hydrochlorothiazide, glipizide, calcium, and vitamin D.
On examination, she is quiet and appears frail. Blood pressure is 170/94 mm Hg and pulse is 90/min. BMI is 18 kg/m2. There is a 2×4 cm, Stage 2 pressure ulcer in her presacral area. Fingerstick blood glucose level is 250 mg/dL.
On further questioning, the patient states that she is now unable to pay for her prescription refills.
Which of the following is the most appropriate course of action?
(Multiple Choice)
4.9/5 (83)
(83) A 67-year-old male seeks follow-up after a screening ultrasound at a health fair showed an abdominal aortic aneurysm. He has no symptoms and specifically denies claudication. He smoked 1-2 packs of cigarettes per day for 35 years and stopped 10 years ago. He has been told that his cholesterol was high in the past.
His temperature is 37.1 C (98.7 F), blood pressure is 142/92 mm Hg, pulse is 72/min and respirations are 14/min. His Body Mass Index is 29 kg/m2. Examination of the heart, chest, and abdomen are unremarkable. His lower extremity pulses are 2+ with good upstroke.
The patient's laboratory data obtained at the health fair showed a normal complete blood count. His total cholesterol was 240 mg/dL, low density lipoprotein 140 mg/dL, and high density lipoprotein 40 mg/dL. His serum creatinine was 1.3 mg/dL, and the remainder of his laboratory tests were normal. The abdominal ultrasound report revealed an infrarenal abdominal aortic aneurysm with a diameter of 4.2 centimeters.
In addition to addressing the patient's abnormal lipids and blood pressure, which of the following represents the best option at present?
(Multiple Choice)
4.8/5 (81)
(81) A 36-year-old man with known ankylosing spondylitis for the last 7 years comes to the physician complaining of persistent back pain. He describes aching pain at night and in the morning that slowly goes away during the day. In the evening, he feels fine and prefers to do most of his activities then. He takes high-dose naproxen, which previously relieved his pain but recently has had only moderate effect. He was evaluated for right hip pain 6 months ago, but no joint involvement was diagnosed.
His vital signs are within normal limits. Examination shows limited spinal mobility and sacroiliac joint tenderness.
Laboratory results are as follows:
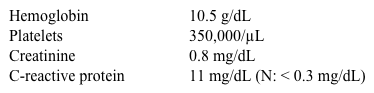 Which of the following is the best next step in managing this patient?
 (Multiple Choice)
4.9/5 (77)
(77) A 76-year-old woman who has resided in a nursing home for two years is seen, along with her family, to discuss her medical plans. She has chronic kidney disease with an estimated glomerular filtration rate (eGFR) of 7 ml/min/1.73 m2. Her other medical problems include type 2 diabetes mellitus, chronic congestive heart failure, moderate cognitive impairment, recurrent falls, a previous hip fracture, and impaired vision. She gets up in a chair for approximately 1 hour per day. She needs help with all activities of daily living except for feeding herself. She relates that she is comfortable and voices no complaints.
On examination, her BMI is 19 kg/m2 and she appears frail. There is 2+ pitting pedal edema bilaterally, bibasilar fine inspiratory crackles, and a stage 2 sacral pressure ulcer.
An ultrasound of her kidneys at the time of admission to the nursing home revealed no obstruction.
Which of the following is the best management plan?
(Multiple Choice)
4.8/5 (82)
(82) A 77-year-old man is brought to the office by his daughter because of weight loss and poor appetite. The patient denies having any problems and states that his daughter worries unnecessarily. The daughter agrees that she has become overly concerned about her father's health since his stroke three months ago. According to her, he has lost 10-15 pounds since then and sometimes takes a long time to finish his meals. He also suffers from coughing spells during his meals which usually lasts a couple of minutes. She has not noticed any other symptoms except for some slurred speech.
His medical history is significant for an ischemic stroke, hypertension, diabetes mellitus, arthritis, and depression. He had a recent hospitalization for pneumonia 1 month ago. He is currently taking atenolol, baby aspirin, insulin, and trazodone. He intermittently takes over-the-counter naproxen. His dentist started him on an unknown antibiotic 5 days ago. He has a 20-pack-year smoking history, but quit smoking 30 years ago. He stopped drinking alcohol after the stroke, but otherwise says he has enjoyed a glass of wine everyday of his life.
Physical examination shows a thin-built elderly man. His blood pressure is 152/72mmHg, pulse is 55/min, and BMI is 19 kg/m2. He has some halitosis, decaying molars bilaterally, and dry oral mucosa. Minimal crackles are heard at the right lung base. There is trace peripheral edema on both lower extremities.
Which of the following is the best next step in evaluating this patient?
(Multiple Choice)
5.0/5 (84)
(84) A 25-year-old woman at 10 weeks gestation comes to the office for a consultation regarding a positive HIV-1 enzyme-linked immunosorbent assay and a confirmatory Western blot that were ordered as part of routine prenatal care. She has never been tested before and does not know when she was exposed to HIV. She has no other chronic medical conditions and has had no prior surgeries. The patient takes a daily prenatal vitamin but no other medication. She does not use tobacco or illicit drugs. The patient is a college student and lives with her boyfriend.
Physical examination is within normal limits. A complete blood count, basic metabolic panel, lipid panel, and hepatic function panel are all normal. HIV viral load is 3,240 copies/mL and CD4 count is 473 cells/mm3.
Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (80)
(80) A 43-year-old African-American man with known HIV is evaluated for edema. A diagnosis of HIV was established five years ago and HAART therapy initiated, but he has been non-compliant due to side effects. He began experiencing leg edema 3 months ago that has progressively increased in severity.
His temperature is 36.6 C (97.9 F), blood pressure is 130/82 mm Hg, and pulse is 84/min. Cardiac, pulmonary, and abdominal examinations are unremarkable. He has 3+ ankle edema that extends to the knees and 1+ presacral edema.
His laboratory studies are shown below.
 Which of the following would you expect to see on kidney biopsy?
 (Multiple Choice)
4.8/5 (83)
(83) A 35-year old man comes to the physician because of dyspnea on exertion over the last 3-4 months. The dyspnea is more prominent when he plays tennis. He has no symptoms at rest. He denies chest pain, palpitations, or leg swelling. His other medical problems include chronic low back pain and gastroesophageal reflux disease. He has had local corticosteroid injections due to frequent left heel pain. His current medications include ranitidine and ibuprofen daily, and occasional acetaminophen/codeine for back pain.
His blood pressure is 120/55 mm Hg, pulse is 56/min, and respirations are 12/min. He is in no acute distress. The lungs are clear to auscultation bilaterally. His apical impulse is slightly displaced both inferiorly and laterally. There is a normal S1 and S2. An early decrescendo diastolic murmur is heard best at the left upper sternal border. A third heart sound is present. His pulses are 3+ and symmetric. There is no peripheral joint inflammation or tenderness; range of motion is normal. There are no skin rashes.
Chest x-ray shows normal lung fields, a moderately enlarged cardiac silhouette, and widening of the mediastinum. The chest CT shows a dilated aortic root (4.4 cm) without evidence of dissection.
Which of the following is the most likely diagnosis?
(Multiple Choice)
4.9/5 (72)
(72) A 75-year-old man comes to the physician for a sore on his ear that he says "won't heal." He is a retired lineman for an electrical company in a rural area. He first noticed a small lump on the top of his ear 1 year ago. It has grown and opened up into a painful sore that has not responded to a topical antibiotic cream.
He has a history of hypertension, chronic gouty arthritis, hyperlipidemia, and chronic kidney disease with a stable serum creatinine of 2.0 mg/dL. His current medications include atenolol, fosinopril, allopurinol, and simvastatin.
His vital signs are stable. The lesion on his right pinna is shown in the photograph below.
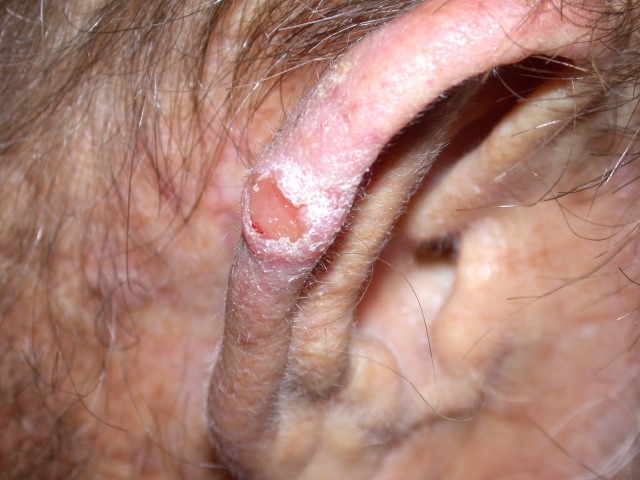 What is the most likely diagnosis for this patient's nonhealing ulcer?
 (Multiple Choice)
4.8/5 (79)
(79) A 24-year-old man comes to the office due to hematuria. For the past 2 days, he has been passing bright red blood at the end of micturition. He has mild dysuria, but no fever or abdominal pain. He travels throughout Africa frequently and returned from a rafting trip in central Africa 3 months ago. The patient followed medical advice regarding vaccinations and medication prophylaxis. His past medical history is otherwise insignificant. He drinks 2-3 cans of beer on the weekend and does not use tobacco or illicit drugs. The patient has one sexual partner, with whom he uses condoms consistently. He works as a sales representative.
His temperature is 36.1 C (97 F), blood pressure is 120/70 mm Hg, and pulse is 68/min. Cardiopulmonary examination is normal. The abdomen is soft and nontender without organomegaly. The external genitalia are unremarkable. On rectal examination, the prostate is normal in size and nontender.
Laboratory results are as follows:
 Which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.8/5 (76)
(76) A 26-year-old woman comes to the physician because of increasing fatigue. She was diagnosed with Graves' disease 3 months ago and did not have any extrathyroidal manifestations at that time. Radioactive iodine was administered to treat her thyrotoxicosis approximately 8 weeks ago. Her palpitations and tremors have improved. She has gained 4 lbs (1.8 kg) in the last 4 weeks and she is now experiencing cold intolerance.
Her blood pressure is 130/80 mm Hg and pulse is 80/min. Examination reveals mild diffuse thyromegaly without nodules or bruits. There is no tremor, proptosis, or pretibial myxedema. Deep tendon reflexes do not show delayed relaxation time.
Her serum thyroid stimulating hormone (TSH) level is 0.05 µU/mL.
Which of the following is the most appropriate next step in management?
(Multiple Choice)
4.9/5 (78)
(78) A 48-year-old man comes to the office due to insomnia. The patient was attacked and robbed at gunpoint 3 weeks ago, during which he was kicked in the abdomen and chest and sustained a fractured rib that is healing without complication. He is no longer in pain but describes difficulty falling asleep, frequent nightmares, and multiple nighttime awakenings since the incident. The patient says, "I just need to get some rest so I can function the next day at work." He describes irritability and difficulty concentrating. He is unable to remember details of the attack and has avoided walking alone at night. Although his friends have offered support, the patient has no interest in seeing them and feels emotionally distant from his family. He is seen yearly for hypertension and familial hypercholesterolemia. He has no psychiatric history.
On mental status examination, the patient is anxious and tense and startles easily. Physical examination is unremarkable.
Which of the following is the most appropriate management for this patient?
(Multiple Choice)
4.8/5 (70)
(70) A 50-year-old woman comes to the physician for follow-up of type 2 diabetes mellitus. She was diagnosed with diabetes 2 years ago and tried lifestyle modifications. She currently takes metformin 1000 mg twice daily. The patient has a family history of diabetes, chronic kidney disease, and stroke. She does not use tobacco, alcohol, or illicit drugs.
Her blood pressure is 152/92 mm Hg and pulse is 88/min. Her BMI is 39 kg/m2. Acanthosis nigricans is present on the neck and axilla. The liver span is 10 cm. Peripheral pulses are 2+ bilaterally. There is no sensory loss over the lower extremities as assessed by microfilament test.
Laboratory results are as follows:
 Urine is positive for microalbumin.
Which of the following measures is most likely to achieve a hemoglobin A1c <6.0% in one year in this patient?
Urine is positive for microalbumin.
Which of the following measures is most likely to achieve a hemoglobin A1c <6.0% in one year in this patient? (Multiple Choice)
4.9/5 (83)
(83) A 77-year-old man with a long-standing history of hypertension comes to the office due to exertional shortness of breath and fatigue. He went to the emergency department 4 weeks ago for shortness of breath and was treated with intravenous diuretics. Echocardiogram at that time showed left atrial enlargement, left ventricular hypertrophy, and a left ventricular ejection fraction of 65%. Medications include daily furosemide 40 mg, amlodipine 10 mg, spironolactone 12.5 mg, and low-dose aspirin.
Blood pressure is 128/76 mm Hg and pulse is 74/min. Jugular venous pressure is estimated at 9 cm H2O. Cardiac examination is notable for an S4 gallop and nondisplaced apical impulse. Lung auscultation reveals bibasilar crackles. The abdomen is nondistended and nontender to palpation. There is bilateral pitting ankle edema.
ECG shows normal sinus rhythm and voltage criteria for left ventricular hypertrophy. Serum potassium is 4.1 mEq/L and serum creatinine is 0.9 mg/dL.
Which of the following is the best treatment option for this patient?
(Multiple Choice)
4.9/5 (78)
(78) A 37-year-old woman with known systemic lupus erythematosus is evaluated for generalized weakness and dyspnea on exertion. She has no weight loss, night sweats, hemoptysis, or cough. Her current medications include hydroxychloroquine, naproxen, and low-dose prednisone. She stopped taking azathioprine 4 weeks ago due to side effects.
Her blood pressure is 142/90 mm Hg and pulse is 82/min. The oropharynx is moist with no visible lesions. Small, mobile lymph nodes are palpable in the submandibular area. Skin examination shows a scaly erythematous rash over the face, scalp, and upper trunk. Cardiopulmonary examination is within normal limits. There is no splenomegaly.
Laboratory results are as follows:
 Peripheral blood smear shows polychromatic red blood cells, spherocytes, and normal platelets. No schistocytes are seen.
Which of the following is most likely responsible for this patient's symptoms?
Peripheral blood smear shows polychromatic red blood cells, spherocytes, and normal platelets. No schistocytes are seen.
Which of the following is most likely responsible for this patient's symptoms? (Multiple Choice)
5.0/5 (83)
(83) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)