



 Chat with AI
Exam 3: Office/Health Center

Exam 1: Emergency Department218 Questions
Exam 2: In-patient Facilities128 Questions
Exam 3: Office/Health Center900 Questions
Select questions type


A 65-year-old man is evaluated for progressively worsening dyspnea for the past year. His past medical history is significant for hypertension and acid reflux disease. Six months ago, he complained of a dry cough. At that visit, his omeprazole dose was increased from 20 mg daily to 20 mg twice daily, and his blood pressure medication was switched from lisinopril to amlodipine. These interventions did not help, however, and his symptoms continued to worsen. He is a lifelong nonsmoker and retired after working as a chemical engineer at an oil refinery for 35 years.
His temperature is 37.2 C (99 F), blood pressure is 120/80 mm Hg, pulse is 78/min, and respirations are 16/min. His pulse oximetry at rest is 94% on room air and decreases to 82% after walking for 3 minutes. He has finger clubbing. There is no jugular venous distension. Heart sounds are normal without murmurs. Lung auscultation shows diffuse, dry, mid-inspiratory crackles bilaterally. There is no swelling or tenderness of any joints, including the proximal interphalangeal and metacarpophalangeal joints of the hands.
Laboratory results are as follows:
 High-resolution chest CT scan is performed; a representative image is shown below.
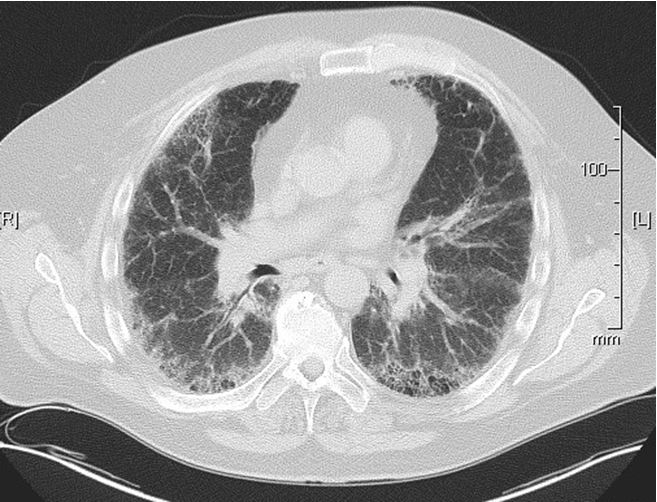 Which of the following is the most likely diagnosis in this patient?
High-resolution chest CT scan is performed; a representative image is shown below.
Which of the following is the most likely diagnosis in this patient?
Free
(Multiple Choice)
4.9/5  (85)
(85) Correct Answer: Verified
C
A 64-year-old man comes to the office with pain and swelling over the left upper chest for 7 days. He also had an episode of fever, but no cough, sore throat, abdominal pain, diarrhea, or urinary symptoms. Five months ago, the patient had a single-lead implantable cardioverter-defibrillator placed due to a sudden cardiac arrest. His other medical problems include nonischemic cardiomyopathy (ejection fraction, 20%) and chronic kidney disease.
Temperature is 36.7 (98 F), blood pressure is 109/70 mm Hg, pulse is 70/min, and respirations are 16/min. Pulse oximetry is 95% on room air. Examination shows clear lungs and normal S1 and S2. Swelling, erythema, and tenderness are present over the defibrillator generator. A small amount of discharge is seen through an erosion of the healed suture line.
Leukocytes are 11,200/mm3. Two sets of blood cultures are negative after 2 days.
Which of the following is the best next step in management of this patient?
Free
(Multiple Choice)
4.8/5 (82)
(82) Correct Answer:Verified
VerifiedB
A 22-year-old-woman comes to the office with a rash that started 2 days earlier with the sudden appearance of multiple red spots on the trunk and arms. The rash is mildly pruritic but not painful. She has used no new medications or over-the-counter hygiene products. The patient had a sore throat that started 2 weeks ago and is slowly getting better. She has no other medical problems and takes no prescription medications. She drinks 2 or 3 beers on the weekend but does not use tobacco or illicit drugs.
On physical examination, the patient appears well. Vital signs are normal. The throat has erythema but no exudate. No cervical lymphadenopathy is noted. Cardiopulmonary examination is normal. The rash is shown in the photograph below. The palms and soles are spared.
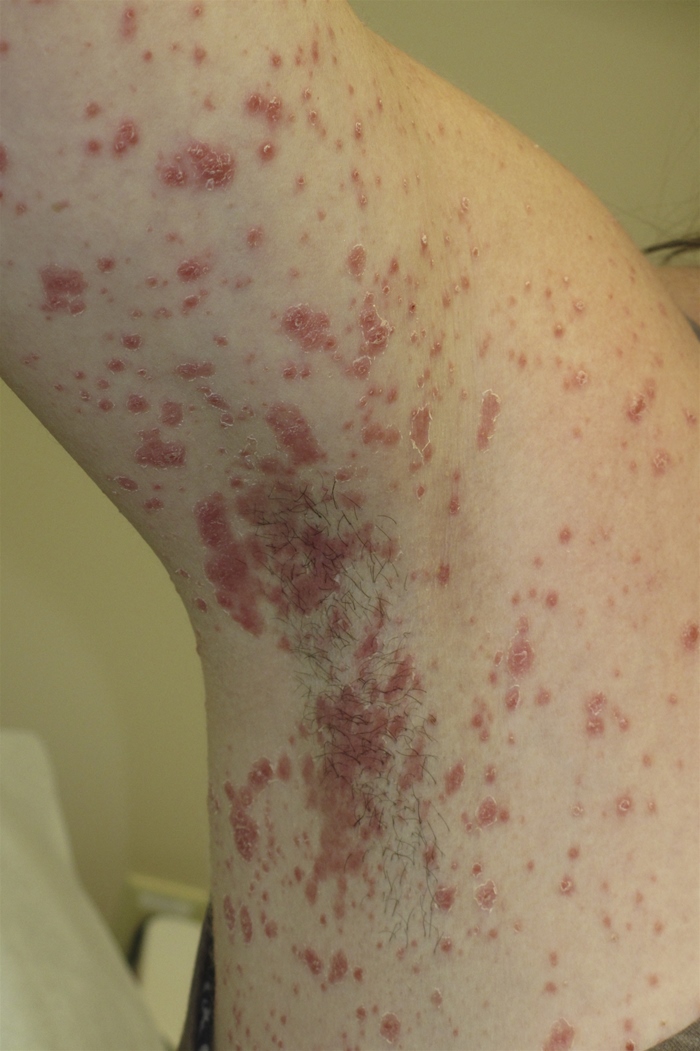 Which of the following is the most likely diagnosis?
Free
(Multiple Choice)
4.9/5 (77)
(77) Correct Answer:Verified
VerifiedC
A 74-year-old woman comes to the office for a routine checkup. She has had difficulty with her memory that has worsened over the past year. She sometimes forgets important appointments, including doctors' appointments. The patient often forgets to take her daily pills. It has also become difficult for her to remember the names of new people she meets, and she often has to write them down. The patient drives, shops, and pays her bills independently. She admits that she has had bouts of loneliness since her husband died 2 years ago; however, she still enjoys socializing with friends when she has the energy. The patient has hypertension, hyperlipidemia, gastroesophageal reflux disease, and left knee osteoarthritis. Her mother died of a stroke, and her father died of Alzheimer disease.
The patient's blood pressure is 132/78 mm Hg and pulse is 76/min. BMI is 29 kg/m2. Neurological examination shows no focal deficits. She scores a 25/30 on the Montreal Cognitive Assessment.
Which of the following is the most likely diagnosis for this patient?
(Multiple Choice)
4.8/5 (77)
(77) A 75-year-old man comes for follow-up 6 months after radical prostatectomy for prostate cancer. He continues to have occasional episodes of involuntary loss of urine with activities such as straining or lifting heavy objects. The patient was an avid golfer but stopped after the surgery due to urinary leakage. He has no dysuria, nocturia, or hematuria. The patient did not undergo radiation therapy. He has a history of hypertension and type 2 diabetes mellitus.
The blood pressure is 130/80 mm Hg and pulse is 68/min. The abdomen is soft and nontender without palpable masses. There is decreased sensation to light touch and pinprick on bilateral feet. Ankle reflexes are absent and muscle strength is normal. Post-void residual volume is low.
Prostate-specific antigen level is undetectable and urinalysis findings are within reference range.
Which of the following is the best next step in managing this patient?
(Multiple Choice)
4.8/5 (68)
(68) A 68-year-old man is seen for follow-up of non-small cell lung cancer with bone metastases. He is accompanied by his wife, who is worried about his condition. The patient has undergone surgical resection and several courses of combination chemotherapy. His prognosis is 3-6 months. At today's visit, the patient reports that his cancer pain is generally controlled, but he feels extremely weak and fatigued. He has difficulty falling asleep and also awakens at 2:00 and 4:00 AM. His wife says, "I make his favorite foods but he barely takes a bite. When the children visited last weekend, he seemed uninterested in spending time with his son and grandson and retired to his room while they were still there." The patient says, "I am just so exhausted all the time. I know I'm not getting better and feel guilty about being a burden to my family."
The patient has lost 8.2 kg (18 lb) since his last visit. Physical examination is otherwise unchanged. His mood is sad but he is able to smile when appropriate. He thinks about death and dying but has no suicidal ideation, intent, or plan.
Which of the following symptoms is most suggestive of major depression in this patient?
(Multiple Choice)
4.8/5 (90)
(90) A 64-year-old man with a history of type 2 diabetes mellitus comes to the physician with 3 weeks of left foot pain. He reports recent difficulty with ambulation that requires a cane. He has no fevers, chills, nausea, vomiting, malaise, or fatigue. The patient has a history of hypertension and poorly controlled diabetes mellitus complicated by mild renal disease and neuropathy. His current medications include insulin, lisinopril, metoprolol, and gabapentin.
His temperature is 37.1 C (98.8 F), blood pressure is 124/84 mm Hg, pulse is 90/min, and respirations are 18/min. Examination of the lower extremities shows decreased sensation to fine touch bilaterally extending to the knees. There is a 2x2 cm ulcerated lesion at the base of the left first metatarsal. The borders are clean without erythema. There is scant and foul-smelling purulent drainage at the base with poor granulation tissue and visualized bone.
An x-ray of the foot reveals cortical erosion with elevated periosteum.
Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (85)
(85) A 35-year-old woman comes to the physician because of right arm weakness. She began noticing some clumsiness several months ago that she attributed to excess yard work. However, it worsened recently, causing her to drop things while working in the kitchen. She also reports stumbling and almost falling several times over the last month. She denies headaches, vision problems, or vertigo. She suffered from acute lymphoblastic leukemia at age 7 and received combination chemotherapy, cranial irradiation, and intrathecal chemotherapy. She has no other medical problems. She does not smoke or use alcohol.
Her blood pressure is 111/68 mm Hg and pulse is 68/min. Her BMI is 23 kg/m2. Physical examination does not reveal any lymph node enlargement, carotid bruits, or heart murmurs. The spleen is not palpable. There is pronator drift on the right side. Her deep tendon reflexes are symmetric. She is stable in the Romberg position with her eyes closed but has mild instability on tandem walking.
Brain imaging in this patient would most likely reveal which of the following?
(Multiple Choice)
4.7/5 (69)
(69) A 65-year-old woman comes to the office due to involuntary facial and mouth movements. The patient first noticed the condition 6 months ago with protruding and twisting movements of the tongue and puckering movements of the lips; the movements have worsened since then. She has also experienced foot-tapping movements and an uncontrollable twisting of her neck to the right side. The patient has type 2 diabetes mellitus and chronic gastroparesis. She also has a long history of bipolar disorder that has been stable over the past year on a combination of lithium and quetiapine. Other medications include metformin and metoclopramide. She has no family history of a movement disorder or any neurologic disease.
Temperature is 37.5 C (99.5 F), blood pressure is 138/76 mm Hg, and pulse rate is 84/min. Occasional tongue protrusion, facial grimacing, cervical torticollis, slow gait, and reduced arm swing are noted.
Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.9/5 (82)
(82) A 32-year-old woman comes to the physician because of palpitations and mild anxiety over the last two months. She feels fatigued and has difficulty falling asleep at night. She delivered a healthy child 9 months ago, and her pregnancy was complicated by hypertension that resolved after delivery. She also gained excessive weight during pregnancy and has been trying to lose weight. Three months ago, she had an episode of acute sinusitis requiring antibiotic therapy. She has no other medical issues and does not take any prescription medications. She does not smoke cigarettes but drinks a few glasses of wine on the weekends.
Her blood pressure is 140/80 mm Hg and pulse is 100/min. Her BMI is 32 kg/m2. The thyroid gland is non-tender and is not enlarged. The remainder of the physical examination is unremarkable.
Laboratory results are as follows:
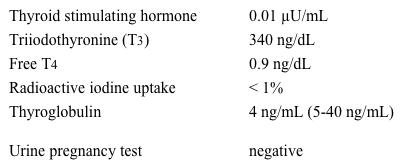 Which of the following is the most likely diagnosis?
 (Multiple Choice)
4.9/5 (95)
(95) A 67-year-old man comes to the physician because of bloody urine. This morning, he noticed gross hematuria with passage of a few small blood clots in his urine. He also reports mild dysuria. He has since continued to have grossly bloody urine with occasional small blood clots. He denies fever, chills, back/flank pain, and bruising or bleeding at other sites. He denies any history of urolithiasis or trauma.
His other medical problems include a history of granulomatosis with polyangiitis (Wegener's) diagnosed 3 years ago. At that time, he was treated with 6 months of oral cyclophosphamide and tapering doses of prednisone. He has subsequently been maintained on oral methotrexate. He denies recent weight loss, arthralgias, or respiratory symptoms.
His blood pressure is 130/86 mm Hg, pulse is 84/min, and respirations are 16/min. He is afebrile. There are no bruises or petechiae. He does not have any flank pain. Cardiopulmonary examination is normal.
After sending a urine sample to the laboratory for culture, the following laboratory results are obtained:
 Which of the following would have the highest diagnostic yield?
 (Multiple Choice)
4.8/5 (93)
(93) A 58-year-old woman comes to the office due to diarrhea over the past 6 months. Every day, the patient has 3 or 4 watery bowel movements that sometimes awaken her at night. She has had no nausea, vomiting, fever, or recent travel. She also has associated fecal urgency and mild abdominal discomfort that is partially relieved after bowel movements. Other medical problems include seasonal allergies and tension headaches. She smokes a pack of cigarettes a day but does not use alcohol. Medications include regular use of naproxen and loratadine.
Vital signs are normal. Examination shows no abnormalities. There are no skin rashes.
Laboratory results show normal complete blood count and comprehensive metabolic panel. Serum TSH is normal. Stool studies for occult blood, leukocytes, ova and parasites, and Clostridium difficile toxin are negative. Colonoscopy is grossly normal, but random mucosal biopsies reveal an abnormally thickened subepithelial collagen band.
Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.8/5 (82)
(82) A 30-year-old man comes to the physician because of decreased sexual desire over the last 3 months. He says that he is otherwise healthy and has no other complaints. His other medical problems include hypercholesterolemia and migraine headaches. He was prescribed topiramate 4 months ago by his previous primary care physician for frequent headaches, but it did not seem to help much. He does not use tobacco or drink alcohol. He has a sedentary lifestyle and has gained 24 lbs (10.9 kg) in the past 3 years. His sister suffers from migraine headaches and his father had a myocardial infarction at the age of 45.
His blood pressure is 132/80 mm Hg and pulse is 72/min. The patient's body mass index (BMI) is 32 kg/m2. Examination shows no gynecomastia or hepatomegaly. He has normal secondary sexual characteristics. His testes are normal in size and consistency. The remainder of the examination is within normal limits.
Laboratory results are as follows:
 Which of the following is the most appropriate next step in management?
 (Multiple Choice)
4.7/5 (79)
(79) An 80-year-old man comes to the physician because of a skin rash on his legs. He also complains of mild fatigue and a poor energy level. He denies chest pain/pressure, orthopnea, or dyspnea with exertion. Two weeks ago, he underwent coronary arteriography for unstable angina and had a stent placed in his right coronary artery. His subsequent hospital course was uncomplicated. His other medical problems include hyperlipidemia, type 2 diabetes mellitus, hypertension, and mild cognitive impairment. His current medications include low-dose aspirin, benazepril, atenolol, clopidogrel, hydrochlorothiazide, rosuvastatin, and glipizide. Clopidogrel was added after the stent placement.
His blood pressure is 144/82 mm Hg and pulse is 72/min. His lungs are clear on auscultation. There is a mottled, lace-like, purplish discoloration of both lower extremities from the mid-thigh downward. His pulses are 1+ bilaterally over the distal lower extremities.
Laboratory results are as follows:
 Which of the following is the most likely diagnosis?
 (Multiple Choice)
5.0/5 (79)
(79) A 27-year-old woman with multiple sclerosis comes to the physician because of right arm numbness and mild balance problems for the past one month. She was diagnosed with multiple sclerosis one year ago after presenting with partial right-sided vision loss and finger tingling. She was treated with corticosteroids for two weeks and had improvement of her symptoms. She has been treated with glatiramer acetate since then. She developed a recurrence of right-sided hand numbness 1 month ago that progressed to right arm numbness and left leg weakness. Her past medical history is otherwise unremarkable.
Routine laboratory tests, including complete blood count and comprehensive metabolic panel, are unremarkable. Repeat MRI of the brain shows white matter changes that appear to be worse compared to the study one year ago. She is being considered for a switch to natalizumab therapy due to progressive disease.
Which of the following antibody titers would be most helpful in managing this patient?
(Multiple Choice)
4.9/5 (85)
(85) A 32-year-old woman comes to the physician complaining of severe left flank pain and gross hematuria. The pain started about 6 hours earlier and has steadily increased. It is not colicky in nature. There is no history of trauma, bleeding, or bruising. The patient has no weight loss, fever, chills, or dysuria. She considers herself in good health and works full-time as an editorial assistant. There is no family history of hematuria, kidney stones, or kidney disease. Her past medical history is unremarkable and she takes no medications.
On examination, the patient appears uncomfortable. Her vital signs are within normal limits. Some scattered small pits are noted in her teeth. Cardiac and pulmonary examinations are unremarkable. An ill-defined mass is felt in the left flank area on abdominal examination.
Laboratory results show a urinalysis with red bloods cells too numerous to count, normal complete blood count, and normal comprehensive metabolic panel.
An urgent ultrasound reveals a 10-cm echogenic mass in the left kidney. Smaller echogenic masses and 3 renal cysts are seen in the right kidney. Abdominal CT scan reveals a 10x13-cm mass in the left kidney with attenuation similar to perirenal fat.
Which of the following is the most likely diagnosis?
(Multiple Choice)
4.9/5 (87)
(87) A 31-year-old woman comes to the office due to headaches, intermittent diarrhea, dizziness, poor sleep, and fatigue. She describes muscle tension in her shoulders and neck, frequent tension headaches, and nonspecific gastrointestinal distress. Her symptoms have been ongoing for the past year but are worse since she separated from her husband 3 months ago. The patient has difficulty falling asleep, frequently lying awake in bed for several hours worrying about her health, finances, work deadlines, and lack of social life. During the day she is anxious and irritable and has low energy and difficulty concentrating at work. She rarely goes out with her friends as she is too tired at the end of the day. The patient was evaluated 6 months ago for similar symptoms. She says, "I was reassured that everything was normal, but I am still worried something was missed." The patient does not use alcohol or illicit drugs. She has a history of asthma treated with albuterol as needed.
The patient is afebrile; blood pressure is 130/72 mm Hg, pulse is 88/min, and respirations are 14/min. BMI is 22 kg/m2. Physical examination is unremarkable.
Serum TSH level, complete blood count, and urinalysis are normal.
Which of the following is the most likely diagnosis?
(Multiple Choice)
4.9/5 (68)
(68) A 53-year-old man comes to the office due to exertional dyspnea. He can walk only 2 blocks before becoming short of breath. The patient has no chest pain, palpitations, or syncope. He was hospitalized 8 months ago with heart failure with reduced ejection fraction and treated with diuretics. Cardiac catheterization showed nonobstructive coronary artery disease. Echocardiogram revealed left ventricle enlargement with an ejection fraction of 25%. Current medications include carvedilol, sacubitril-valsartan, furosemide, and spironolactone.
Blood pressure is 112/68 mm Hg, pulse is 62/min, and oxygen saturation is 99% on room air. Jugular venous pressure is estimated at 7 cm H2O. Breath sounds are decreased at the right lung base. The point of maximal impulse is displaced laterally. A regular heart rhythm and an S3 are heard. The liver span is 8 cm. The tip of the spleen is not palpated. There is mild edema of both ankles.
Laboratory results are as follows:
 Repeat transthoracic echocardiogram is unchanged from the previous study.
Which of the following ECG findings will change this patient's heart failure management?
Repeat transthoracic echocardiogram is unchanged from the previous study.
Which of the following ECG findings will change this patient's heart failure management? (Multiple Choice)
4.8/5 (101)
(101) A 46-year-old man comes to the physician with anterior neck pain, night sweats, and palpitations for the past 3 weeks after an upper respiratory infection. The pain is severe and continues to bother him at night. He has tried over-the-counter acetaminophen and ibuprofen without significant relief. He has no other medical problems.
His temperature is 37.8 C (100 F), blood pressure is 144/72 mm Hg, and pulse is 121/min. He appears restless. Eye examination shows mild lid lag. The thyroid gland is markedly tender bilaterally. He has fine hand tremors. There is no proptosis or pretibial myxedema.
Laboratory testing shows normal complete blood count and basic chemistry profile. Other laboratory results are as follows:
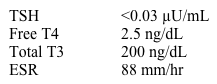 A 24-hour radioactive iodine uptake is 1%.
In addition to a beta blocker, what is the most appropriate next step in management of this patient?
A 24-hour radioactive iodine uptake is 1%.
In addition to a beta blocker, what is the most appropriate next step in management of this patient? (Multiple Choice)
4.8/5 (86)
(86) A 48-year-old woman comes to the office for the first time due to a 3-year history of diffuse abdominal pain, headaches, muscle pain and weakness, constipation, and an intermittent tingling sensation in the right arm. The symptoms are debilitating and frequently interfere with the patient's ability to work. She saw 2 other physicians this past year for similar symptoms but received no definitive diagnosis or treatment. The patient has no depressed mood or anhedonia. Medications include ibuprofen and polyethylene glycol as needed as well as daily multivitamins. She does not use tobacco, alcohol, or illicit drugs.
Vital signs are within normal limits. The patient grimaces on gentle abdominal palpation but not when she is actively engaged in conversation. There is no demonstrable extremity weakness or sensory loss. The remainder of the examination shows no abnormalities.
Complete blood counts, serum metabolic profile, erythrocyte sedimentation rate, TSH, vitamin B12 levels, antinuclear antibody titer, and urinalysis performed 3 months ago by another physician were within reference range. Previous abdominal CT scans and MRI of the brain were also normal.
Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.9/5 (69)
(69) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)