



 Chat with AI
Exam 3: Office/Health Center

Exam 1: Emergency Department218 Questions
Exam 2: In-patient Facilities128 Questions
Exam 3: Office/Health Center900 Questions
Select questions type


A 32-year-old man comes to the office due to severely depressed mood. He says, "For the past month I have had no energy. I could sleep all day and have missed several days at work because I can't motivate myself to get out of bed." The patient is sleeping 12 hours a day and his appetite is poor. He has suicidal ideation but no intent or plan. He has no delusions or hallucinations. The patient has a history of depression in his 20s that responded poorly to fluoxetine. He was hospitalized briefly 2 years ago after being arrested for aggressive behavior when police attempted to restrain him as he entered a government building without authorization. At the time, the patient wanted to explain his "strategy for world peace at the United Nations." Following discharge, he did not follow up with treatment and currently takes no medication. The patient has a history of childhood asthma and knee pain from a motorcycle accident. He drinks beer on weekends and does not use illicit drugs. Family history is significant for depression in his maternal grandfather, who was treated with nortriptyline.
Blood pressure is 122/78 mm Hg, pulse is 72/min, and respirations are 16/min. Physical examination is unremarkable.
Which of the following is the most appropriate pharmacotherapy?
(Multiple Choice)
4.7/5  (78)
(78) A 46-year-old woman comes to the physician with complaints of exertional dyspnea over the last 6 months. She can barely walk a block without having to stop and catch her breath. She has minimal dry cough and denies chest pain, orthopnea, and hemoptysis. She reports intermittent lower-extremity swelling. The patient has lost 3 kg (7 lb) over the last 3 months due to poor appetite. She was diagnosed with Hodgkin's lymphoma 2 years ago and was treated with doxorubicin, bleomycin, vinblastine, and dacarbazine. She does not use tobacco, alcohol, or illicit drugs.
Her vital signs and physical examination are unremarkable. Laboratory studies, including complete blood count and lactate dehydrogenase, are normal. EKG shows normal sinus rhythm and no ST-segment or T-wave abnormalities.
Posteroanterior chest x-ray of the patient is shown below.
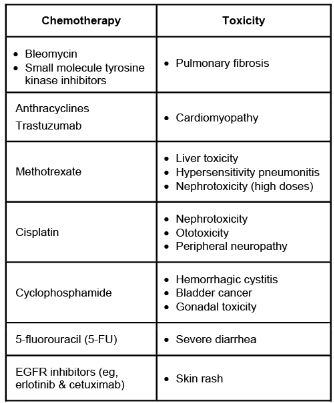 Which of the following conditions is the most likely cause of this patient's presentation?
 (Multiple Choice)
4.8/5 (81)
(81) A 46-year-old woman comes to the office with a 3-week history of back pain. She has experienced no trauma, focal leg weakness, or incontinence. A compression fracture of the T11 vertebra was found a year ago when she had similar symptoms. At that time, a dual-energy x-ray absorptiometry scan showed a T score of -3.1 at the lumbar spine and -2.0 at the femoral neck. She was prescribed alendronate. The patient has gained about 6.8 kg (15 lb) over the last year and attributes this to a decrease in physical activity following the first compression fracture. She now has difficulty climbing up stairs and standing up from a sitting position. Her last menstrual period was a year ago.
Her medical history is significant for diet-controlled diabetes and hypothyroidism. Her other medications include levothyroxine and calcium with vitamin D. The patient has no family history of diabetes or osteoporosis. She does not use tobacco, alcohol, or illicit drugs.
Blood pressure is 154/88 mm Hg and pulse is 78/min. BMI is 35 kg/m2. Tinea versicolor is noted on skin examination. She has local tenderness at the level of the T8 vertebra. The remainder of the physical examination is normal.
Laboratory results are as follows:
 Thoracic spine radiograph shows a new T8 vertebral compression fracture.
Which of the following is the best next step in management of this patient?
Thoracic spine radiograph shows a new T8 vertebral compression fracture.
Which of the following is the best next step in management of this patient? (Multiple Choice)
4.9/5 (97)
(97) A 25-year-old woman comes to the physician with complaints of fatigue and worsening shortness of breath. She first noticed her symptoms 8 months ago. She awoke 2 days ago with palpitations and severe coughing and noticed some bright-colored blood in her sputum. She emigrated from the Philippines 2 years ago and works as a nurse at a local hospital. She has no history of smoking, illicit drug use, or unprotected sexual intercourse. She has no past medical history of childhood illnesses.
Her blood pressure is 106/62 mm Hg, and pulse is 82/min and regular. Neck veins are pulsatile with a prominent c-v wave. Lungs fields are clear with minimal rales heard at both lung bases. Heart sounds are regular with a loud first heart sound. A low-pitched mid-diastolic rumble and a snapping sound after the second heart sound are present at the cardiac apex. There is also a loud holosystolic murmur heard over the precordium that increases with inspiration.
Which of the following is the most likely diagnosis?
(Multiple Choice)
4.9/5 (79)
(79) A 32-year-old woman comes to the physician because of hand pain and swelling that lasts several hours every morning. She has not felt well since "getting the flu" two weeks ago from her two children (ages 4 and 6). She initially had a sore throat and fever without rash, cough, dysuria, or diarrhea. She works as a flight attendant and travels extensively, but has been on medical leave for the past two weeks due to her illness. She is in a monogamous relationship and uses a barrier method for contraception. She does not smoke, but she drinks alcohol occasionally.
Her vital signs are within normal limits. There are no skin rashes. Oropharyngeal examination shows mild tonsillar swelling and normal appearing pharyngeal mucosa. Several 0.5 cm non-tender lymph nodes are palpable in the anterior cervical region. Auscultation of the heart and lungs is normal. There is no hepatosplenomegaly. The small joints of her hands and wrists are swollen and tender. She is unable to flex or extend her wrists or make a fist due to the pain and swelling. She has normal range of motion without swelling in both knees, ankles, shoulders, and feet.
Laboratory results are as follows:
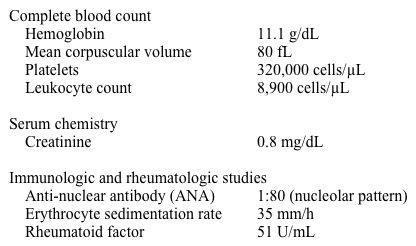 Which of the following is the most likely diagnosis?
 (Multiple Choice)
4.9/5 (95)
(95) A 27-year-old man comes to the physician with fatigue, erectile dysfunction, and muscle weakness. He says, "I am losing my muscles despite working out every day in the gym." He has no past medical history. He had taken over-the-counter supplements to improve his endurance but now cannot afford them as he was recently laid off from his job. He requests a prescription to improve his fatigue and sex drive. He has no headaches, peripheral vision loss, weight gain, decrease in facial hair growth, or joint pain.
His vital signs are normal, and BMI is 26 kg/m2. He is a well-built, muscular man with minimal gynecomastia. The testes are small and soft. The remainder of the physical examination is normal.
Initial laboratory results show normal chemistry profile and hematocrit of 52%.
Which of the following laboratory abnormalities would most likely be present on further evaluation?
(Multiple Choice)
4.8/5 (93)
(93) A 73-year-old woman comes to the physician for routine follow-up and medication refill. She has experienced an acute onset of hand shaking over the last couple of weeks. It has significantly affected her daily activities, especially pouring tea and knitting. She has no chest pain, anxiety, shortness of breath, lower-extremity edema, or weight loss. She has had no recent falls. The patient has taken atenolol and hydrochlorothiazide for hypertension for many years but ran out of medications about a month ago and has not renewed them until today.
Her blood pressure is 152/76 mm Hg and pulse is 85/min. Her thyroid gland is not enlarged. There is a 2/6 ejection type systolic murmur at the right upper sternal border. A mild tremor of outstretched hands is seen bilaterally. Romberg maneuver is negative for any signs. Gait is normal.
Which of the following is the most likely diagnosis?
(Multiple Choice)
4.9/5 (74)
(74) A 35-year-old woman comes to the physician with 2 months of arm and leg weakness accompanied by puffy swelling of her hands. She also complains of dry eyes and mouth. She reports that her fingers turn blue or white when exposed to cold temperatures. The patient was evaluated for fatigue 6 months ago and was found to have normal complete blood count, serum chemistry, thyroid-stimulating hormone, vitamin D level, erythrocyte sedimentation rate, and C-reactive protein. Her antinuclear antibody test was positive at a low titer 1:80.
She was advised to increase her aerobic activity level and was prescribed myofascial stretching exercises. She has no other significant past medical history. Her medications include acetaminophen and oral contraceptive pills. The patient drinks alcohol occasionally but does not use tobacco or illicit drugs. She works on a factory assembly line and has 3 children.
Vital signs are within normal limits. On examination, she has several telangiectasias in the face. Both hands appear edematous and there is synovitis in several metacarpophalangeal and proximal interphalangeal joints. There is no leg edema. Muscle strength is decreased symmetrically and is 4/5 in both upper and lower extremities.
Laboratory results are as follows:
 Which of the following antibodies is most likely to be positive in this patient?
 (Multiple Choice)
4.8/5 (78)
(78) A 66-year-old man with a known history of Parkinson disease complains of very painful involuntary contractions affecting the toes of both feet. The contractions occur in the morning, soon after he wakes up, and occasionally wake him from sleep. The episodes last about 15-20 minutes. His other medical problems include acid reflux disease and hypertension. He has been taking immediate-release carbidopa/levodopa twice daily for the last 5 years. He has no history of falls.
Vital signs are within normal limits. Examination shows a 3-4 Hz resting tremor in both hands that is exacerbated by distraction and decreased with action. There is mild rigidity of the upper and lower extremities bilaterally. His gait is stable.
Which of the following is most likely to improve this patient's current symptoms?
(Multiple Choice)
4.8/5 (84)
(84) A 75-year-old woman comes to the office due to difficulty with memory and thinking. The patient has stopped going for walks and has not attended bingo in months; she explains that these activities are no longer enjoyable. She has low energy and difficulty falling asleep. Her appetite has decreased, and she has lost >6.8 kg (>15 lb) in the past 3 months.
Medical history is significant for hypertension, well-controlled epilepsy, and type 2 diabetes mellitus. The patient lives alone and drove herself to today's appointment. She has not gotten lost while driving and has had no difficulty caring for herself.
Blood pressure is 138/84 mm Hg, pulse is 76/min, and respirations are 14/min. Neurologic examination is nonfocal, and she scores a 26/30 on the Montreal Cognitive Assessment. Laboratory results, including thyroid function studies, are normal.
Which of the following is the most appropriate pharmacotherapy?
(Multiple Choice)
4.9/5 (85)
(85) A 72-year-old woman with type 2 diabetes mellitus is brought to the emergency department with dyspnea and chest pressure that started about 6 hours earlier.
Her blood pressure is 82/62 mm Hg and pulse is 104/min. Pulse oximetry shows 92% on 15 L oxygen by face mask. She is mildly confused. Examination shows moist oral mucosa and distended neck veins in a sitting position. The apical impulse is displaced to the left with a third heart sound. Lung examination shows fine crackles one third of the way up in bilateral lung fields. Lower extremities are cold to the touch with weak peripheral pulses.
Her initial ECG shows sinus tachycardia and a new left bundle branch block.
Which of the following measures instituted immediately is most likely to improve survival in this patient?
(Multiple Choice)
5.0/5 (76)
(76) A 43-year-old woman comes to the physician because of weakness and pain in her left hand for the past 3 weeks. She has no other complaints. Her other medical problems include left-sided breast cancer for which she underwent lumpectomy and radiation therapy 1 year ago.
Examination shows no edema of the left arm, but pain to palpation of the medial forearm and hand. She also has weakness throughout the muscles of her left hand (4/5) compared to the muscles of her right hand. Both pupils are reactive (left eye: 3 mm, right eye: 4 mm), but there is mild ptosis on the left.
Which of the following is the most likely diagnosis?
(Multiple Choice)
4.7/5 (76)
(76) A 62-year-old man comes to the physician for evaluation of chest and upper abdominal discomfort for the past 6 months. He has noted the discomfort during his daily walks and sometimes at rest, especially after heavy meals. His other medical problems include hypertension, type 2 diabetes mellitus, and gastroesophageal reflux disease. His medications include metformin, aspirin, hydrochlorothiazide, and lisinopril.
The patient's blood pressure is 142/82 mm Hg and pulse is 74/min. BMI is 33 kg/m2. His physical examination is remarkable for chronic venous stasis and 1+ swelling of both lower extremities.
The patient is referred for an exercise radionuclide stress test. After 5 minutes on the Bruce protocol, he is able to reach 85% of maximum age-predicted heart rate. His blood pressure at baseline is 148/88 mm Hg and is 142/86 mm Hg at peak exercise. He complains of discomfort in both arms and his chest during the end of exercise, which resolves 5 minutes later during the recovery period. ECG monitoring shows 2-mm horizontal ST-segment depression in leads II, aVF, and V4-V6 at peak stress with normalization at recovery. However, myocardial perfusion images show no evidence of ischemia, and ejection fraction is calculated at 65%.
Which of the following is the most appropriate next step in management?
(Multiple Choice)
4.9/5 (73)
(73) A 52-year-old man comes to the office for follow-up after recent emergency department evaluation for knee pain. The patient had sudden-onset, severe pain in the right knee associated with swelling and difficulty walking. Arthrocentesis was performed; microscopic findings from the synovial fluid are shown in the exhibit.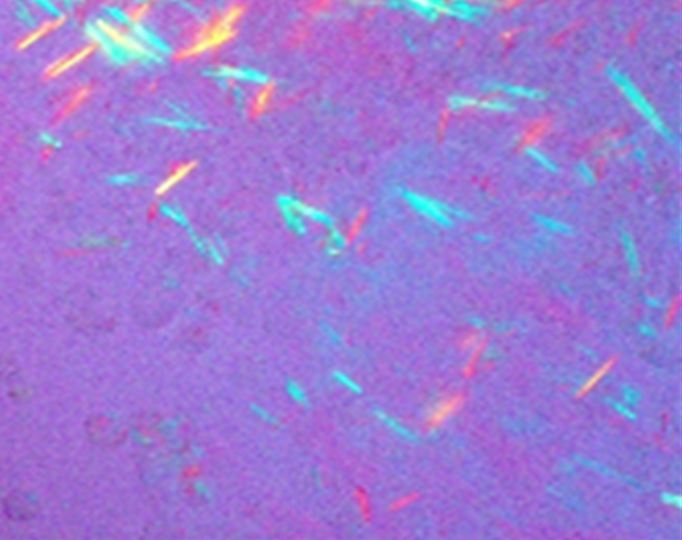 The patient's symptoms have improved with medical treatment. Medical history is notable for hypertension treated with amlodipine. The patient drinks 2 or 3 beers daily but does not use tobacco or illicit drugs. He works in a warehouse and his job involves lifting heavy boxes. He is divorced, has had 2 sexual partners in the past 6 months, and rarely uses condoms.
Blood pressure is 130/82 mm Hg and pulse is 80/min. BMI is 32 kg/m2. Physical examination is normal.
Which of the following is the most appropriate intervention for this patient to decrease the future risk of similar episodes?
The patient's symptoms have improved with medical treatment. Medical history is notable for hypertension treated with amlodipine. The patient drinks 2 or 3 beers daily but does not use tobacco or illicit drugs. He works in a warehouse and his job involves lifting heavy boxes. He is divorced, has had 2 sexual partners in the past 6 months, and rarely uses condoms.
Blood pressure is 130/82 mm Hg and pulse is 80/min. BMI is 32 kg/m2. Physical examination is normal.
Which of the following is the most appropriate intervention for this patient to decrease the future risk of similar episodes? (Multiple Choice)
4.8/5 (72)
(72) A 76-year-old man comes to the office for a preoperative evaluation. The patient is scheduled for an elective prostatectomy in 2 weeks. He initially had difficulty urinating and was found to have an enlarged, irregular prostate; subsequent evaluation revealed adenocarcinoma of the prostate. Medical history is notable for hypertension and diet-controlled diabetes mellitus. The patient also had a stroke 6 years ago and has residual right upper extremity weakness. Medications include daily low-dose aspirin, atorvastatin, valsartan, tamsulosin, and finasteride. He walks 2 miles most days and smokes half a pack of cigarettes daily.
Physical examination is normal except for mild weakness in the right upper extremity.
ECG shows normal sinus rhythm at 74/min with occasional premature atrial beats. Hemoglobin is 14.1 g/dL, platelet count is 340,000/mm3, and creatinine is 0.8 mg/dL.
Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.9/5 (81)
(81) A 56-year-old man complains of pain in his right groin 3 days after cardiac catheterization. He underwent the procedure after 2 months of intermittent chest pain. The coronary angiogram showed mild nonobstructive coronary disease. He has no fever, chest pain, leg numbness, or cold feet.
Vital signs are normal. The puncture site at the right femoral artery shows no erythema or ecchymosis. A tender mass is palpated below the right inguinal ligament near the puncture site. Bilateral popliteal and posterior tibial pulses are full.
Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (85)
(85) A 25-year-old man comes to the office due to problems with concentration and restlessness. His younger brother takes stimulants for attention-deficit hyperactivity disorder, and the patient wonders if medication will help him to focus. He is accompanied by his girlfriend, who says, "Over the past month, he has been uncharacteristically hyperactive and irritable, jumping from one activity to another but getting little accomplished." The patient is frustrated with his current job as a computer data entry clerk, which he feels is beneath him, and he was upset when his boss recently criticized him for making several mistakes. His girlfriend says that he is on the verge of losing his job. The patient stays up late developing plans for a new business that he believes will make him a millionaire. He is sleeping 2-3 hours a night. He drinks 3-4 alcoholic drinks a week and uses marijuana twice a month.
Physical examination is unremarkable. Urine toxicology is positive for tetrahydrocannabinol. On mental status examination, the patient appears restless and easily distracted. He is very talkative and leaves his chair to pace during the interview. His mood is irritable. He has no suicidal ideation or psychotic features.
Which of the following is the most likely diagnosis?
(Multiple Choice)
4.8/5 (78)
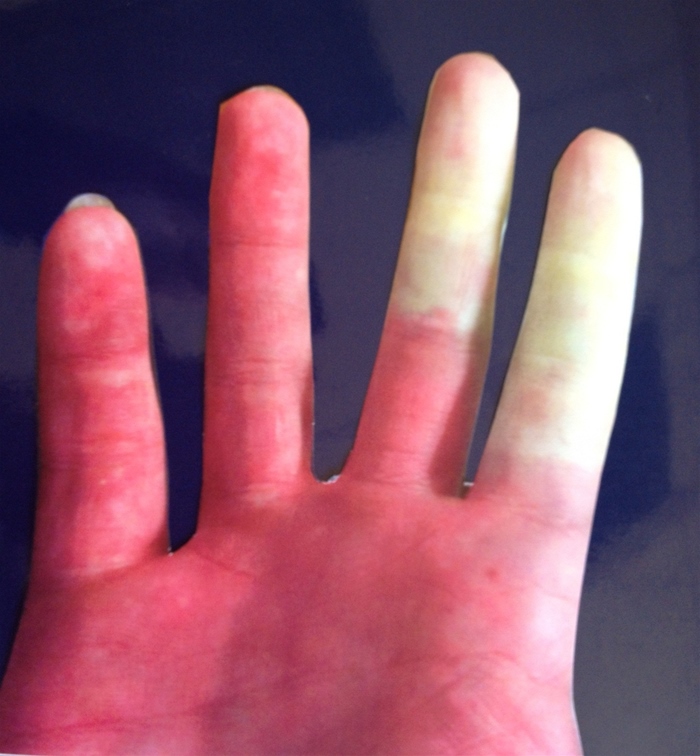
(78) A 20-year-old woman comes to the physician because her fingers turn white episodically. The symptoms started 6 months ago during the summer when she noticed that opening the freezer or holding cold beverages precipitated these episodes. She was advised to avoid cold stimuli and wear protective gloves. However, the symptoms worsened during the winter and the episodes occurred more frequently. She feels numbness and pain with each episode and seeks relief.
The patient has no skin thickening, chest pain, acid reflux symptoms, or shortness of breath. She has no other past medical history. She does not smoke but drinks alcohol occasionally.
Her vital signs are within normal limits. The remainder of the physical examination is within normal limits. The hand is shown in the picture.
 Laboratory results are as follows:
 Which of the following is the most appropriate pharmacotherapy?
Laboratory results are as follows:
Which of the following is the most appropriate pharmacotherapy? (Multiple Choice)
4.8/5 (73)
(73) A 52-year-old woman comes to the office due to fatigue and mild weight loss. For the last several weeks, she has also experienced hot flashes, heat intolerance, and trouble sleeping. The patient has had no tremors, palpitations, neck pain, proximal weakness, eye discomfort, diplopia, or swelling. Her medical history is notable for hypertension treated with metoprolol and hydrochlorothiazide. Family history is positive for hypertension and osteoporosis in her mother. The patient does not use tobacco or alcohol. She experienced natural menopause at age 50.
Vital signs are normal. Ocular examination shows mild lid lag without proptosis. Neck examination reveals a 2.5-cm nodule in the right lobe of the thyroid gland without surrounding lymphadenopathy. There are no tremors or pretibial myxedema. The remainder of the examination is normal.
Laboratory results are as follows:
 Thyroid ultrasound shows a 2.5-cm solitary thyroid nodule in the right lobe. Radioactive iodine uptake scan (shown in the image) at 24 hours is 30% (normal: 10%-30%), predominantly in the nodule with minimal surrounding uptake.
 Beta blocker therapy is initiated to reduce the patient's symptoms. Which of the following additional interventions is the most appropriate management for this patient's condition?
Thyroid ultrasound shows a 2.5-cm solitary thyroid nodule in the right lobe. Radioactive iodine uptake scan (shown in the image) at 24 hours is 30% (normal: 10%-30%), predominantly in the nodule with minimal surrounding uptake.
Beta blocker therapy is initiated to reduce the patient's symptoms. Which of the following additional interventions is the most appropriate management for this patient's condition? (Multiple Choice)
4.9/5 (77)
(77) A 49-year-old man comes to the physician because of a two-month history of right-sided neck, shoulder, and arm pain. The onset of the pain occurred a few days after he spent an afternoon chopping firewood. He describes the pain as constant and occasionally pulsating, especially at night. He also notes that his right arm alternates between warm and cold to the touch. He gets partial pain relief when he applies ice to the affected areas. He tried over-the-counter acetaminophen and ibuprofen without relief.
His other medical problems include hypertension, hypercholesterolemia, and gastroesophageal reflux disease. His medications include losartan, amlodipine, omeprazole, and simvastatin.
Physical examination is remarkable for tenderness over the right occipital area. There is mild edema of the fingers on the right hand. Neck motion is complete but slow in all directions. Neurological examination, including pinprick, motor strength, and deep tendon reflexes of the upper extremities, is unremarkable.
Laboratory results are as follows:
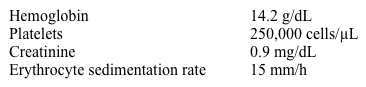 Radiographs of the cervical spine show some mild disk space narrowing at C5-C6 and C6-C7. A right shoulder x-ray demonstrates normal alignment, no fractures, and no calcifications. There is some patchy bone demineralization involving the acromion.
Which of the following is the most likely diagnosis?
Radiographs of the cervical spine show some mild disk space narrowing at C5-C6 and C6-C7. A right shoulder x-ray demonstrates normal alignment, no fractures, and no calcifications. There is some patchy bone demineralization involving the acromion.
Which of the following is the most likely diagnosis? (Multiple Choice)
4.8/5 (69)
(69) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)