



 Chat with AI
Exam 1: Emergency Department

Exam 1: Emergency Department218 Questions
Exam 2: In-patient Facilities128 Questions
Exam 3: Office/Health Center900 Questions
Select questions type


A 28-year-old man is brought to the emergency department by his parents due to agitation, paranoid delusions, and hearing voices. The patient has no medical issues. He drinks a beer each day but does not use illicit drugs. Family history is significant for Graves disease and depression in his mother and hypertension and coronary heart disease in his father. Medical and substance-induced causes of psychosis are ruled out; further history indicates that the patient has become increasingly paranoid and withdrawn over the past year. He is diagnosed with schizophrenia and hospitalized, then started on olanzapine and as-needed lorazepam. After a week the patient is significantly calmer and less paranoid and reports that the voices have decreased in frequency and intensity. He is discharged on olanzapine 20 mg.
The patient is seen for a routine medical checkup 3 months later. Apart from an upper respiratory infection a month ago, he has been well. Vital signs and physical examination are unremarkable. He no longer hears voices and has no suicidal ideation.
Which of the following tests is the most appropriate at this visit?

Free
(Multiple Choice)
5.0/5  (81)
(81) Correct Answer: Verified
C
A 78-year-old man is brought to the emergency department with abdominal pain. According to his wife, he has had epigastric discomfort for the past 2 days; this morning he refused to get out of bed and appeared confused. Past medical history is significant for diet-controlled diabetes mellitus, coronary artery disease with stable angina, hypertension, and gastroesophageal reflux disease.
On examination, the patient is lethargic. His temperature is 38 C (100.4 F), blood pressure is 144/90 mm Hg, pulse is 112/min and irregular, and respirations are 20/min. Chest is clear on auscultation. There are no heart murmurs. The abdomen is tender to palpation in the epigastric and right upper quadrant areas. His skin is warm and there are no rashes.
Laboratory results are as follows:
 ECG reveals atrial fibrillation with no significant ST segment or T wave changes. Abdominal ultrasound shows several small gallstones without wall thickening or edema around the gallbladder. Common bile duct size is normal.
Which of the following is the best next step in managing this patient?
ECG reveals atrial fibrillation with no significant ST segment or T wave changes. Abdominal ultrasound shows several small gallstones without wall thickening or edema around the gallbladder. Common bile duct size is normal.
Which of the following is the best next step in managing this patient?Free
(Multiple Choice)
4.8/5 (85)
(85) Correct Answer:Verified
VerifiedC
A 76-year-old man is seen in the emergency department with cough and worsening dyspnea over the last 2 days. He awoke suddenly last night gasping for air and could not get comfortable in any position. He has no fever or chills. The patient's other medical problems include hypertension and type 2 diabetes mellitus. He has a 40-pack-year smoking history and drinks beer occasionally.
His temperature is 37.2° C (99° F), blood pressure is 150/90 mm Hg, pulse is 106/min, and respirations are 25/min. Pulse oximetry is 94% on 2 L O2. Body mass index is 35 kg/m2. Jugular venous pressure is measured at 12 cm H2O. He appears in mild respiratory distress. Heart sounds are distant but no murmurs are heard. Lung examination shows bibasilar crackles and scattered bilateral wheezes. There is 1+ pitting ankle edema seen bilaterally.
Laboratory results are as follows:
 Chest x-ray reveals prominent vascular markings and blunting of costophrenic angles. Echocardiogram shows a diffusely hypokinetic left ventricle with ejection fraction of 35%.
Which of the following best explains the normal brain natriuretic peptide value?
Chest x-ray reveals prominent vascular markings and blunting of costophrenic angles. Echocardiogram shows a diffusely hypokinetic left ventricle with ejection fraction of 35%.
Which of the following best explains the normal brain natriuretic peptide value?Free
(Multiple Choice)
4.9/5 (79)
(79) Correct Answer:Verified
VerifiedA
A 65-year-old man with a history of hypertension is brought to the emergency department for acute onset of right-sided weakness and slurred speech, which started an hour ago. He takes no prescription medications and has no history of bleeding.
The patient's blood pressure is 170/96 mm Hg. On examination, he has right lower facial droop, dysarthria, and diminished strength in his right upper and lower extremities.
A non-contrast head CT is negative. His finger stick blood glucose is 90 mg/dL. Intravenous tissue plasminogen activator is administered.
Assuming this patient's symptoms do not resolve rapidly, which of the following is the most appropriate next step in management?
(Multiple Choice)
4.8/5 (78)
(78) A 71-year-old woman is brought to the emergency department due to not feeling well and worsening right leg weakness. The patient had a stroke 2 years ago and has mild residual right leg weakness. Over the last 2 days, her weakness has gotten worse compared to her baseline, and she can hardly ambulate with a cane. The patient has a history of persistent atrial fibrillation and takes daily warfarin.
Her temperature is 38.3 C (101 F), blood pressure is 150/90 mm Hg, pulse is 94/min, and respirations are 14/min. Pulse oximetry shows 97% on room air. Neurologic examination shows spastic right lower extremity weakness and hyperreflexia. A noncontrast head CT reveals an old infarct in the left anterior cerebral artery territory.
Laboratory results are as follows:
 Which of the following is the most likely explanation for this patient's symptoms?
 (Multiple Choice)
4.7/5 (74)
(74) A 27-year-old woman comes to the emergency department after waking with new left-sided facial weakness. She has also had headaches over the last 10 days that are throbbing, 4 of 10 in intensity, located "all over" her head, and associated with photophobia but no nausea. She has had no double vision, limb weakness, numbness, difficulty swallowing, or recent head trauma, but she does note some malaise and mild neck stiffness.
The patient has a history of migraines but says her current headaches are different in quality and more persistent. She has seasonal allergies and takes over-the-counter antihistamines as needed. She traveled to India 4 months ago and is currently living with her grandparents in Connecticut for the summer. She is single and does not use tobacco, alcohol, or illicit drugs.
Temperature is 37 C (98.6 F), blood pressure is 130/80 mm Hg, pulse is 80/min and regular, and respirations are 15/min. BMI is 30 kg/m2. Mucous membranes are dry. Neurologic examination shows slight nuchal rigidity and photophobia. Cranial nerve testing reveals a decreased corneal reflex on the left as well as upper and lower left-sided facial weakness. The remainder of the physical examination is unremarkable.
Which of the following is the most likely complication if this patient's condition is left untreated?
(Multiple Choice)
4.8/5 (87)
(87) A 65-year-old woman comes to the emergency department due to abdominal pain. The pain subsequently subsides, but a 3.5-cm left adrenal mass is seen on abdominal CT scan. No other abnormalities are noted. The mass appears rounded and vascular, and has a high attenuation (25 Hounsfield units). The patient has experienced no headaches, palpitations, mood swings, or recent weight gain. Medical history is notable for hypertension that is well controlled with amlodipine. She has a current 40-pack-year smoking history. Family history is unremarkable.
Blood pressure is 138/90 mm Hg and pulse is 76/min. BMI is 26 kg/m2.
Fasting laboratory results are as follows:
 Which of the following is the most appropriate next step in evaluating this patient?
 (Multiple Choice)
4.8/5 (75)
(75) A 42-year-old woman comes to the emergency department due to shortness of breath. Approximately 2 weeks ago, the patient developed shortness of breath on exertion that has become progressively worse. She also reports mild chest pain with deep inspiration. She has had no weight loss, fever, cough, or sputum production. Medical history includes diet-controlled type 2 diabetes mellitus and locally advanced infiltrating ductal carcinoma of the left breast, for which she underwent neoadjuvant chemotherapy followed by surgical resection and radiation approximately 2 years ago. The patient is a lifetime nonsmoker and has no significant second-hand tobacco exposure. She lives with her family and works as a teacher. Family history is notable for colon cancer in her father.
Temperature is 37.6 C (99.7 F), blood pressure is 122/78 mm Hg, pulse is 92/min, and respirations are 20/min. Oxygen saturation is 92% on ambient air. Physical examination shows moist mucous membranes with no jugular venous distension or lymphadenopathy. Heart rate is regular with no murmurs or gallops. Auscultation reveals decreased breath sounds over the right lower lung with dullness to percussion. Extremities have no edema. The remainder of the examination is normal. Upright chest x-ray reveals the following:
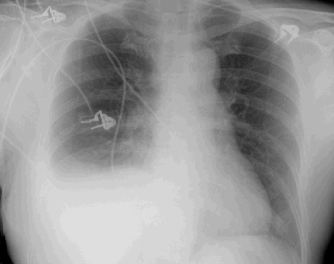 The patient undergoes thoracentesis. Pleural fluid analysis shows 3,500/mm3 nucleated cells, predominantly lymphocytes. Additional pleural fluid analysis results are as follows:
 Gram stain and culture of the pleural fluid are negative. What is the most appropriate next step in management of this patient?
The patient undergoes thoracentesis. Pleural fluid analysis shows 3,500/mm3 nucleated cells, predominantly lymphocytes. Additional pleural fluid analysis results are as follows:
Gram stain and culture of the pleural fluid are negative. What is the most appropriate next step in management of this patient? (Multiple Choice)
4.7/5 (84)
(84) A 76-year-old man is brought to the emergency department by his son due to progressive lethargy and poor oral intake. The son says the patient has had poor appetite, fatigue, constipation, frequent urination, and possible weight loss. The patient lives with his wife, who suffers from mild dementia. He smokes half a pack of cigarettes a day and drinks a 6-pack of beer on weekends. The patient takes over-the-counter painkillers for occasional back pain and antacids for heartburn. Temperature is 36.9 C (98.5 F), blood pressure is 140/90 mm Hg, pulse is 96/min, and respirations are 14/min. Pulse oximetry shows 95% on room air. He is oriented to person only. Mucous membranes appear dry, and the neck is supple. The lungs are clear on auscultation. There are no heart murmurs. The abdomen is soft, and no masses are palpable. The patient moves all of his extremities on command. Laboratory results are as follows:  The patient is started on normal saline and calcitonin. Twelve hours later, blood urea nitrogen is 30 mg/dL, serum creatinine is 1.4 mg/dL, and serum calcium is 15 mg/dL. Which of the following additional measures is recommended at this time for this patient?
 (Multiple Choice)
4.8/5 (84)
(84) A 20-year-old college student is brought to the emergency department due to progressive lethargy and confusion. He is obtunded and unable to answer questions, but his friend says the patient has had shaking chills and diarrhea since last night. He has no prior medical problems other than a nasal fracture following a bar fight 3 days ago, which was reduced and stabilized with nasal packing at another hospital. The patient takes no medications and has no known drug allergies. He lives in a dormitory and recently returned from a hiking trip in North Carolina.
Temperature is 39.4 C (103 F), blood pressure is 84/42 mm Hg, pulse is 126/min, and respirations are 18/min. Examination shows an ill-appearing man. Pupils are equal, round, and reactive. Anterior packing is present in the left nostril. There is diffuse erythema of the mucous membranes and skin, including the palms and soles. Mild pitting edema is present in both legs.
Laboratory results are as follows:
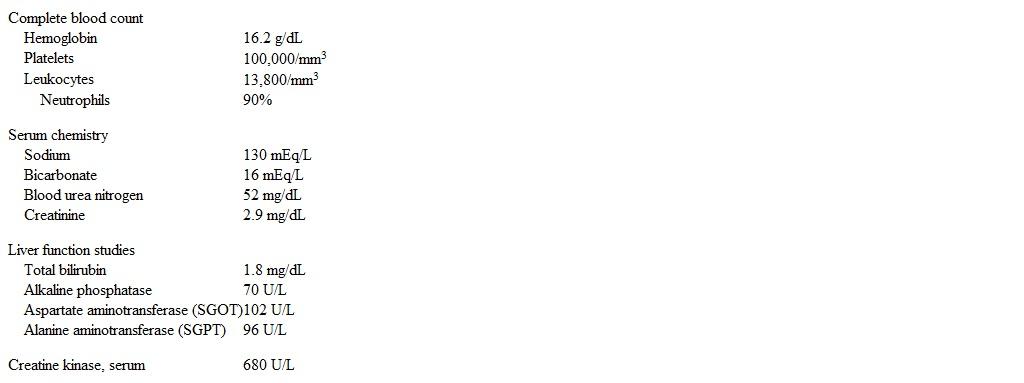 CT scan of the head reveals no abnormalities. Venous access is established, and intravenous fluids are administered.
Which of the following is the most appropriate antimicrobial therapy for this patient?
CT scan of the head reveals no abnormalities. Venous access is established, and intravenous fluids are administered.
Which of the following is the most appropriate antimicrobial therapy for this patient? (Multiple Choice)
4.8/5 (78)
(78) An 82-year-old man is brought to the emergency department by his daughter due to severe depression and a 6.8-kg (15-lb) weight loss over the past month. The daughter reports that he remains depressed, despite treatment with therapeutic doses of sertraline, and is withdrawn from the family. She says, "He no longer plays with the grandchildren, has been eating poorly, and wanders around the house at night when he can't sleep." The daughter became alarmed when she found him talking aloud to his wife, who died 20 years ago. In his 40s, the patient was diagnosed with depression, which responded to a tricyclic antidepressant at that time. Medical history includes hypertension and hypercholesterolemia, both well controlled with medication.
In the hospital, the patient is alert and oriented but gives minimal responses. Efforts to get him to eat and drink are unsuccessful. He reluctantly discloses that he hears voices and has thoughts of suicide.
Vital signs are normal and physical examination is unremarkable aside from weight loss.
Extensive laboratory testing shows mild dehydration but is otherwise within normal limits. CT scan of the brain shows no acute processes.
Which of the following is the most appropriate treatment for this patient?
(Multiple Choice)
4.8/5 (79)
(79) A 70-year-old woman is brought to the emergency department after she tripped and fell at home while getting out of a bathtub. She did not lose consciousness but does have headache and mild right arm pain. Her medical history is significant for advanced breast cancer treated with radical mastectomy and chemotherapy a year ago.
CT of the head is unremarkable. Radiographs of the upper extremities show bone lesions consistent with metastases, but no evidence of fracture. Her serum creatinine level is 1.4 mg/dL (creatinine clearance 30 mL/min), serum calcium level is 9.6 mg/dL, and alkaline phosphatase level is 220 U/L.
The patient is most likely to benefit from which of the following?
(Multiple Choice)
4.7/5 (88)
(88) A 34-year-old man is brought to the emergency department with central chest pain and nausea that started two hours ago. He looks anxious and admits to using cocaine before his chest pain started. He says that he uses cocaine once or twice per month, but has never had similar symptoms. He denies any past medical history and exercises regularly at a gym. He smokes cigarettes and drinks beer on the weekends. He has no family history of coronary artery disease or sudden death.
On physical examination, he is mildly diaphoretic. His blood pressure is 165/85 mm Hg and pulse is 105/min. His oxygen saturation is 98% on room air. Lungs are clear to auscultation. There are no murmurs. Peripheral pulses are brisk and symmetric.
ECG shows sinus tachycardia and a 2 mm ST segment elevation in leads II, III, and avF; a 1 mm ST segment depression is seen in lead I. Telemetry monitoring shows occasional premature ventricular beats. Portable chest X-ray is unremarkable.
He is immediately treated with sublingual nitroglycerin, aspirin, and benzodiazepines. Shortly thereafter, he reports improvement of his symptoms and now rates his chest pain as 3/10, down from the initial 8/10.
Which of the following is the best next step in managing this patient?
(Multiple Choice)
4.7/5 (81)
(81) An 84-year-old man is admitted to the hospital with multilobar pneumonia and respiratory failure that required emergent intubation and mechanical ventilation in the emergency department. He is accompanied by his 2 daughters. Medical history is significant for poorly controlled type 2 diabetes mellitus, end-stage renal disease, moderate chronic obstructive pulmonary disease, and hypertension. The patient was recently diagnosed with hepatocellular carcinoma with bone and lung metastases.
The patient is started on broad-spectrum antibiotics and transferred to the intensive care unit for continued care. Shortly after arrival, his blood pressure is 76/54 mm Hg despite aggressive intravenous fluid hydration. The patient does not have a written advance directive, but his daughters say that he has made it clear that he "wants everything done" in the event of illness.
Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.7/5 (79)
(79) An 82-year-old man comes to the emergency department because of sudden onset back pain. He denies any lower extremity weakness, bowel or bladder incontinence, muscle cramps, or paresthesias. He has no fever or chills. He has a history of chronic lymphocytic leukemia and hyperlipidemia. He has not received any chemotherapy for his leukemia and lost follow-up with physician appointments. He does not take any prescription medications. He denies tobacco, alcohol, or illicit drug use.
His blood pressure is 140/76 mm Hg, pulse is 72/min, and respirations are 14/min. Examination shows cervical lymphadenopathy and splenomegaly. He has point tenderness at the L2 level. The remainder of the examination is within normal limits.
The patient's labs reveal:
 An electrocardiogram is normal. Spinal imaging shows a compression fracture at the level of L2.
Which of the following is the next best step in the management of his hyperkalemia?
An electrocardiogram is normal. Spinal imaging shows a compression fracture at the level of L2.
Which of the following is the next best step in the management of his hyperkalemia? (Multiple Choice)
4.8/5 (89)
(89) A 45-year-old woman is brought to the emergency department after neighbors found her unresponsive at home. No other history is available.
Temperature is 37 C (98.5 F), blood pressure is 100/70 mm Hg, pulse is 90/min, and respirations are 16/min. Pulse oximetry is 96% on room air. The patient is lethargic but arousable, and her speech is slurred. She is oriented to person but not place or time. There are no focal neurologic findings. The remainder of the physical examination is unremarkable.
Laboratory results are as follows:
 Blood alcohol levels are undetectable.
Which of the following conditions is the most likely diagnosis?
Blood alcohol levels are undetectable.
Which of the following conditions is the most likely diagnosis? (Multiple Choice)
4.9/5 (72)
(72) A 65-year-old woman is brought to the hospital for severe chest pain that started 7 hours ago. She was hospitalized 6 weeks ago with ischemic stroke and treated with aspirin and rosuvastatin. During that hospitalization, the patient had paroxysmal atrial fibrillation and was started on warfarin therapy. Her last INR 2 days ago was 2.1. The patient has mild, residual left-sided weakness. Her past medical history is also significant for hypertension.
Blood pressure is 165/90 mm Hg and heart rate is 98/min and regular. Chest examination shows crackles at the lung bases.
Electrocardiogram (ECG) shows normal sinus rhythm with 2 mm ST-segment elevation in leads V1-V4.
Which of the following is an absolute contraindication to fibrinolytic therapy in this patient?
(Multiple Choice)
4.9/5 (72)
(72) A 55-year-old woman is brought to the emergency department due to severe dizziness and unsteadiness. Two days ago, she awoke with a spinning sensation accompanied by severe nausea and vomiting and a feeling of pressure in the right ear. The episode lasted an hour. Over the next 48 hours, the patient had similar events while in bed. She had no tinnitus, headache, blurry or double vision, dysphasia, dysarthria, falls, or focal weakness during the episodes. The patient has no history of neck or head trauma. She was evaluated for similar symptoms 2 months ago, and no medication was prescribed.
Medical history is notable for type 2 diabetes mellitus, which was diagnosed 15 years ago and is complicated by peripheral neuropathy and gastroparesis. The patient also has hypertension, hypothyroidism, and hyperlipidemia. Family history is notable for stroke and heart disease.
Temperature is 37 C (98.6 F), supine blood pressure is 130/85 mm Hg, and supine pulse is 88/min and regular. Weber test shows lateralization to the left ear. Rinne test shows diminished air and bone conduction on the right and normal findings on the left. Sensory examination reveals a length-dependent reduction in pain, temperature, vibratory, and proprioceptive perception in the lower extremities up to the knees and in the upper extremities up to the elbows. Reflexes are absent in the lower extremities and 1+ in the upper extremities, with mute plantar responses. Coordination testing is normal. A bedside Dix-Hallpike maneuver does not elicit nystagmus.
Which of the following is most likely to prevent further symptoms in this patient?
(Multiple Choice)
4.9/5 (83)
(83) A 72-year-old man comes to the emergency department after a brief episode of loss of consciousness. The patient was waiting in line to purchase a movie ticket when he felt warmth and nausea and started sweating. He then collapsed to the ground and was unconscious for 1 to 2 minutes. According to his wife, who witnessed the episode, he had 2 or 3 jerking movements of his arms. He had no tongue biting or urinary incontinence.
The patient was briefly hospitalized after a similar episode 1 year ago and work-up including blood tests, ECG, and telemetry were normal. His medical problems include hypertension, hyperlipidemia, diet-controlled type 2 diabetes mellitus, and diverticulosis.
Blood pressure is 130/84 mm Hg and pulse is 72/min with no orthostatic changes. The patient is alert and interactive. There are no cardiac murmurs or focal neurologic findings.
ECG shows sinus rhythm with normal intervals. Blood cell counts, serum chemistry studies, and initial cardiac troponin I level are within normal limits.
Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (72)
(72) A 27-year-old man is brought to the emergency department after becoming agitated in a grocery store and screaming that voices are tormenting him and telling him to kill himself. The patient has a history of bipolar disorder currently treated with lithium and fluoxetine. In the emergency department, he becomes combative when approached by staff and receives several doses of intramuscular haloperidol and lorazepam. Urine toxicology is negative. The patient is admitted to the inpatient psychiatry unit, where he is placed in seclusion and restraints due to continued agitation. The following day he is calm but appears confused. He is disoriented to time and place and unable to respond to questions.
Temperature is 39.9 C (103.8 F), blood pressure is 180/90 mm Hg, pulse is 112/min, and respirations are 16/min. On examination, the patient is diaphoretic. He has tremors and severe, generalized muscle stiffness but no hyperreflexia or myoclonus. His examination is otherwise normal. Laboratory tests have been ordered but are still pending.
Which of the following is the most likely diagnosis in this patient?
(Multiple Choice)
4.8/5 (64)
(64) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)