



 Chat with AI
Exam 1: Emergency Department

Exam 1: Emergency Department218 Questions
Exam 2: In-patient Facilities128 Questions
Exam 3: Office/Health Center900 Questions
Select questions type


A 64-year-old man comes to the emergency department with sudden onset of epigastric abdominal pain and vomiting. He attended a colleague's retirement party the night before and admits that he had "a little too much to drink." The patient vomited twice when he got home and noticed abdominal pain after the second vomiting episode. He thought the pain was related to "heartburn" and took extra-strength calcium carbonate antacids with little relief. He tried to sleep, but the severe pain kept him awake. The patient has a history of hypertension and takes amlodipine. He is a current smoker with a 40-pack-year history.
His temperature is 38.0° C (100.4° F), blood pressure is 108/64 mm Hg, pulse is 110/min, and respirations are 18/min. Pulse oximetry is 96% on room air. Examination shows a man in moderate distress. There are normal first and second heart sounds. Decreased breath sounds are heard on the left lower lung field with dullness to percussion. There is both right upper-quadrant and epigastric tenderness without rebound or guarding.
Chest x-ray reveals pneumomediastinum and a moderate-sized left pleural effusion.
Which of the following is the best next step in managing this patient?
(Multiple Choice)
4.9/5  (74)
(74) A 60-year-old right-handed woman with a history of breast cancer with known spine metastasis comes to the emergency department because of headaches and mild left arm weakness. The headaches started 1 month ago and have progressively gotten worse. They occur in the right orbitofrontal region, are sharp in quality, fluctuate in intensity, and have recently been waking her from sleep. She noticed 2 weeks ago that her left arm was weaker than usual. She has taken ibuprofen, with only slight improvement of the headaches.
Her temperature is 37°C (98.6°F), blood pressure is 130/80 mm Hg, and pulse is 90/min. Neurologic examination shows a slight left lower facial palsy and a pronator drift in the left upper extremity. Reflexes are 3+ on the left side of the body, with an ipsilateral Babinski sign. The rest of the neurologic examination shows no abnormalities.
Basic blood work is normal. An MRI of the brain with and without gadolinium shows a single ring-enhancing lesion with mild surrounding vasogenic edema and mass effect at the grey-white junction in the right frontal lobe that is diffusion-restriction negative.
Which of the following is the most appropriate next step in the management of this patient?
(Multiple Choice)
4.8/5 (84)
(84) A 61-year-old man comes to the emergency department complaining of nausea and right upper-quadrant abdominal discomfort for 3 days. His other medical problems include hypertension, type 2 diabetes, hypercholesterolemia, and hypothyroidism. His medications include low-dose aspirin, metformin, glipizide, hydrochlorothiazide, lisinopril, atorvastatin, and levothyroxine. He is an active smoker with a 60-pack-year history and drinks 1-2 glasses of wine daily.
His blood pressure is 155/90 mm Hg and pulse is 80/min. Examination shows no abnormalities.
Laboratory results are as follows:
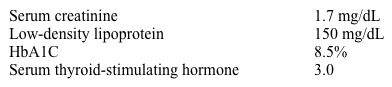 Ultrasound examination shows several small gallstones without cholecystitis and a 3.8-cm abdominal aortic aneurysm.
Which of the following is associated with the highest rate of aneurysm expansion and rupture in this patient?
Ultrasound examination shows several small gallstones without cholecystitis and a 3.8-cm abdominal aortic aneurysm.
Which of the following is associated with the highest rate of aneurysm expansion and rupture in this patient? (Multiple Choice)
4.7/5 (77)
(77) An 87-year-old man is brought to the emergency department with respiratory distress, confusion, and lethargy since this morning. The patient resides in a nursing home and is bedridden. He fell out of bed last night. He had no loss of consciousness prior to the fall or associated trauma, and he was verbally responsive and oriented after the fall. The patient's past medical history is significant for severe osteoarthritis in the knees and hips, hypertension, hyperlipidemia, and mild chronic obstructive pulmonary disease. His medications include amlodipine, simvastatin, and tiotropium.
His temperature is 36.7 C (98 F), blood pressure is 148/90 mm Hg, pulse is 102/min, and respirations are 20/min. Oxygen saturation is 92% on room air. Physical examination shows a frail, elderly man in mild respiratory distress with accessory muscle usage. He is oriented to self only. Jugular venous pressure is estimated at 5 cm H2O. Cardiopulmonary examination reveals irregular tachycardia with bilateral crackles. There are no murmurs or third heart sound. The patient has significant pain with internal rotation of the left lower extremity. Skin examination shows many small (1- to 3-mm) purplish discolorations on the chest that do not blanch with pressure. The remainder of the examination is normal.
Laboratory results are as follows:
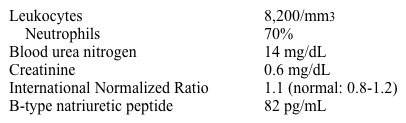 Chest x-ray reveals bibasilar and peripheral haziness. X-rays of the hip reveal left femoral neck fracture.
In addition to orthopedic evaluation, which of the following is the best next step in management of this patient?
Chest x-ray reveals bibasilar and peripheral haziness. X-rays of the hip reveal left femoral neck fracture.
In addition to orthopedic evaluation, which of the following is the best next step in management of this patient? (Multiple Choice)
4.8/5 (67)
(67) A 62-year-old woman comes to the emergency department due to 3 days of fever, chest pain, shortness of breath, and cough. The cough has been occasionally productive of small amounts of bright red blood. The patient was diagnosed with giant cell arteritis a month ago after developing new headaches, jaw claudication, and transient vision loss. She was started on high-dose prednisone, which has since been tapered to 40 mg daily. She also has a history of hypertension, which is well controlled with amlodipine. The patient has a 30-pack-year smoking history.
Temperature is 38.4 (101.1 F), blood pressure is 120/72 mm Hg, pulse is 94/min, and respirations are 18/min; oxygen saturation is 93% on room air. Physical examination shows a frail woman in mild distress with moist mucous membranes and no lymphadenopathy. Lung auscultation reveals occasional crackles in the left lung.
Leukocyte count is 7,400/mm3 with 15% neutrophils, hemoglobin is 13.2 g/dL, and creatinine is 0.8 mg/dL. CT scan of the lungs reveals a 1-cm cavitation and multiple nodules surrounded by ground-glass infiltrates.
The patient is admitted to the hospital and started on empiric broad-spectrum antibiotics.
Further laboratory results are as follows:
 What is the most likely diagnosis in this patient?
 (Multiple Choice)
4.9/5 (87)
(87) A 72-year-old woman with diet-controlled type 2 diabetes mellitus is brought to the emergency department for chest pain and shortness of breath. Her initial blood pressure is 132/72 mm Hg and pulse is 102/min. ECG shows sinus tachycardia and a 2 mm horizontal ST segment depression in the anterior precordial leads. A chest x-ray shows bilateral patchy opacities most consistent with congestive heart failure.
She is treated with aspirin, clopidogrel, furosemide, nitroglycerin infusion, and heparin infusion. Non-invasive positive pressure ventilation is initiated. She is taken to the cardiac catheterization lab, and coronary angiography is performed which shows extensive triple vessel coronary artery disease. Pulmonary artery catheter is placed and no coronary artery intervention is performed.
The patient is transferred to the cardiac care unit. Four hours later, her blood pressure is 84/46 mm Hg and pulse is 116/min. Hemodynamic readings from the pulmonary artery catheter are shown below.
 Which of the following is the most likely cause of this patient's hypotension?
 (Multiple Choice)
4.9/5 (78)
(78) A 66-year-old woman is brought to the emergency department due to agitation, slurred speech, and muscle jerks after her daughter found her confused at home. Medical history includes gastroesophageal reflux, osteoarthritis, hypertension, and bipolar disorder controlled with lithium therapy. The patient cannot recall her other medications, but her daughter reports that a new antihypertensive medication was prescribed 2 weeks ago.
Temperature is 36.7 C (98.1 F), blood pressure is 136/84 mm Hg, pulse is 90/min and regular, and respirations are 16/min. On physical examination, the patient is restless and confused. Neurologic examination shows coarse tremors, sporadic myoclonic jerks, and ataxia. She has no nuchal rigidity and can move all extremities. Deep tendon reflexes are symmetric. The remainder of the physical examination is unremarkable.
Laboratory results are as follows:
 Which of the following medications most likely contributed to this patient's current presentation?
 (Multiple Choice)
5.0/5 (87)
(87) A 49-year-old woman comes to the emergency department with acute-onset hematemesis. She has vomited blood 3 times over the past 3 hours and feels weak and light-headed. She has a history of alcoholic cirrhosis with grade 1 esophageal varices, depression, and prior opiate abuse that is now in remission. The patient takes sertraline, methadone, a multivitamin, folate, and thiamine daily. She does not use tobacco or illicit drugs but drinks 10 ounces of vodka every night.
Temperature is 37.2 C (99 F), blood pressure is 90/50 mm Hg, pulse is 104/min, and respirations are 20/min. The patient appears anxious and uncomfortable. Her abdomen is distended and a fluid wave is present. There is mild asterixis. Rectal examination reveals guaiac-positive brown stools. Skin examination is notable for multiple telangiectasias and palmar erythema.
Laboratory results are as follows:
 Intravenous fluids and octreotide are started, and urgent esophagogastroduodenoscopy is planned.
Which of the following is the best next step in management of this patient?
Intravenous fluids and octreotide are started, and urgent esophagogastroduodenoscopy is planned.
Which of the following is the best next step in management of this patient? (Multiple Choice)
4.7/5 (84)
(84) A 78-year-old man is brought to the emergency department after experiencing 2 episodes of syncope. The first episode occurred yesterday while he sat reading a magazine after a heavy dinner. The second happened today in the bathroom after urination. The patient felt lightheaded and nauseated and had to sit down on the toilet seat before he briefly lost consciousness. He has never had similar episodes before, but he has experienced some lightheadedness during brisk uphill walking.
Over the last several days, the patient has had lower abdominal cramps accompanied by 2 episodes of diarrhea. He was diagnosed with aortic stenosis a year ago after a physical examination showed a murmur, but he refused to see a cardiologist for further evaluation. In the emergency department, he says that he feels "weak but okay."
His blood pressure is 124/60 mm Hg. Jugular venous pressure is estimated at 10 cm H2O. There is a harsh 4/6 systolic mid-peaking murmur at the base of the heart that radiates to both carotids. The second heart sound is soft, and the carotid upstrokes are delayed after the first heart sound. His lungs are clear on auscultation. There is no peripheral edema.
An electrocardiogram is obtained in the emergency department.
Which of the following is the most likely cause of this patient's symptoms?
(Multiple Choice)
4.9/5 (75)
(75) A 20-year-old woman comes to the emergency department complaining of nausea and vomiting. She awoke that morning with the sudden onset of nausea and vomiting. She vomited about 10 times and became concerned when she noticed blood in the vomitus. The patient has no dysphagia or odynophagia. Her other medical problems include a history of menorrhagia and bulimia. She takes naproxen daily for chronic low back pain and does not use tobacco, alcohol, or illicit drugs.
Her blood pressure is 109/60 mm Hg, pulse is 106/min, and respirations are 14/min. Examination shows dry mucous membranes. The abdomen is soft and nontender. There is no hepatomegaly or splenomegaly.
Laboratory results are as follows:
 Test for stool occult blood is negative.
Which of the following is the most appropriate next step in management?
Test for stool occult blood is negative.
Which of the following is the most appropriate next step in management? (Multiple Choice)
4.8/5 (82)
(82) A 60-year-old woman comes to the emergency department because of progressive fatigue and low grade fever for the last 2 weeks. She is from Mexico and is currently visiting her children in the United States. She has never been diagnosed with any chronic medical problems. However, she did receive a blood transfusion 20 years ago when she underwent right femur fracture repair after a motor vehicle accident. She denies tobacco, alcohol, or illicit drug use.
Her temperature is 37.7 C (99.9 F), blood pressure is 130/76 mm Hg, and pulse is 90/min and regular. Her BMI is 27 kg/m2. Physical examination reveals scleral icterus and non-tender rubbery lymph nodes bilaterally in the submandibular, anterior cervical, and axillary areas. Cardiopulmonary examination reveals a 2/6 ejection-type murmur at the left sternal border, and clear lungs. The liver edge is palpated 3 cm below the right costal margin, and the spleen tip is palpated on deep inspiration. There is no skin rash or peripheral edema.
Laboratory results are as follows:
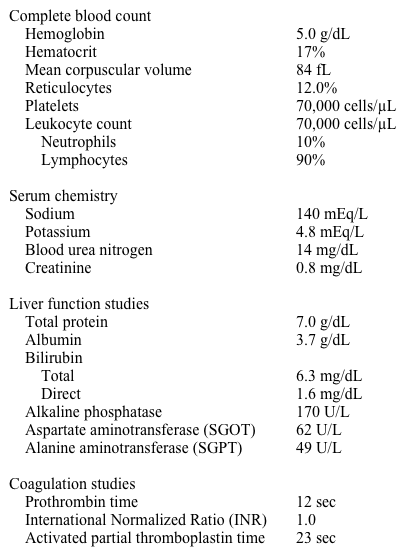 Which of the following would most likely be present in this patient's peripheral blood smear?
 (Multiple Choice)
4.9/5 (74)
(74) A previously healthy 24-year-old woman comes to the emergency department because of fever, chills, and severe throat pain for the last 2 days. She reports having a sore throat 1 week prior, which did not resolve with amoxicillin therapy. She takes no other medications and denies any recent travel or illicit drug use.
Her temperature is 39.4 C (103 F), blood pressure is 90/62 mm Hg, pulse is 114/min, and respirations are 18/min. There is no skin rash. Oral examination reveals moist mucus membranes, erythema involving the oropharynx, and tonsillar enlargement without exudates. The right side of her neck is swollen and tender. There are no heart murmurs. There is no hepatomegaly or splenomegaly.
Laboratory results are as follows:
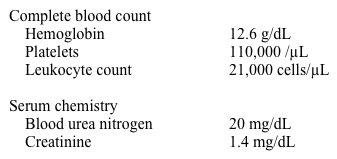 Chest x-ray reveals two round opacities in the right upper lung.
Which of the following is the most likely cause of this patient's current condition?
Chest x-ray reveals two round opacities in the right upper lung.
Which of the following is the most likely cause of this patient's current condition? (Multiple Choice)
4.9/5 (82)
(82) A 67-year-old woman comes to the emergency department due to increased dyspnea on exertion. Her chronic medical problems include obesity, obstructive sleep apnea, moderate chronic obstructive pulmonary disease, coronary artery disease, congestive heart failure, hypertension, hyperlipidemia, rheumatoid arthritis, and hypothyroidism. She was treated with antibiotics and a steroid taper for a "lung infection" 1 month ago. Her cough productive of thick yellowish sputum improved, but she has been feeling increasingly dyspneic when walking up stairs and doing her grocery shopping over the past week. She took some extra doses of furosemide with minimal relief.
The patient denies increased orthopnea but says, "I always sleep on 3 pillows so I can avoid using that PAP mask." She has no fever, chills, or night sweats. She smokes half a pack of cigarettes a day. Surgical history is significant for a 3-vessel coronary artery bypass graft 5 years ago.
Her blood pressure is 160/96 mm Hg, pulse is 78/min, and respirations are 20/min. Pulse oximetry shows 96% on room air. Her BMI is 36 kg/m2. Physical examination shows mild respiratory distress. Lung examination reveals decreased breath sounds on the right with dullness to percussion almost halfway up. There is 1+ pitting edema up to the knees bilaterally.
Laboratory results are as follows:
 Chest x-ray reveals blunting of the costophrenic angle on the left and a moderate right-sided pleural effusion. Thoracentesis is performed on the right and 750 mL of serous fluid is removed. The results of pleural fluid analysis are as follows:
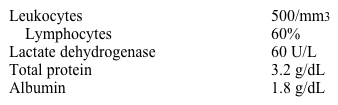 Which of the following is the most likely cause of her pleural effusion?
Chest x-ray reveals blunting of the costophrenic angle on the left and a moderate right-sided pleural effusion. Thoracentesis is performed on the right and 750 mL of serous fluid is removed. The results of pleural fluid analysis are as follows:
Which of the following is the most likely cause of her pleural effusion? (Multiple Choice)
4.9/5 (74)
(74) A 72-year-old man with metastatic prostate cancer comes to the emergency department with shortness of breath and chest pain. His right side hurts when he takes deep breaths. His symptoms started 7 hours ago when he went to bed and could not fall asleep. The patient's baseline exercise tolerance is limited due to exertional dyspnea, but this is the first time he has experienced dyspnea at rest. His other medical problems include hypertension, chronic kidney disease, and colonic diverticular bleeding several years ago. He is a lifetime nonsmoker and does not use alcohol or injection drugs.
Temperature is 36.7 C (98 F), blood pressure is 162/98 mm Hg, pulse is 112/min and regular, and respirations are 20/min. BMI is 30 kg/m2. Oxygen saturation is 87% on room air. Auscultation reveals normal heart sounds with no murmurs and clear lungs. The patient has bilateral 1+ pedal edema. Stool occult blood testing is negative.
Laboratory results are as follows:
 ECG shows sinus tachycardia but is otherwise unremarkable. Supplemental oxygen by nasal cannula is initiated and intravenous heparin infusion is started due to high clinical suspicion of pulmonary embolus. Ventilation perfusion scan is performed and shows intermediate probability.
Which of the following is the best next step in management of this patient?
ECG shows sinus tachycardia but is otherwise unremarkable. Supplemental oxygen by nasal cannula is initiated and intravenous heparin infusion is started due to high clinical suspicion of pulmonary embolus. Ventilation perfusion scan is performed and shows intermediate probability.
Which of the following is the best next step in management of this patient? (Multiple Choice)
4.9/5 (79)
(79) A 20-year-old African American woman with sickle cell disease comes to the emergency department with complaints of severe generalized body pain for 1 day. She has been hospitalized for similar episodes in the past. Her medications include folic acid, hydroxyurea, and hydrocodone as needed for pain.
After initial evaluation, including pertinent laboratory studies and chest x-ray, she is started on 1/2 normal saline at 125 mL/hr and hydromorphone every 3 hours. Over the next 36 hours, the patient complains of worsening chest pain and mild shortness of breath. Her temperature is 38.9 C (102 F), pulse is 112/min, and respirations are 23/min. Oxygen saturation is 93% on 2 L O2. Lung examination shows bilateral crackles. Lower-extremity examination shows tenderness with palpation.
Laboratory results are as follows:
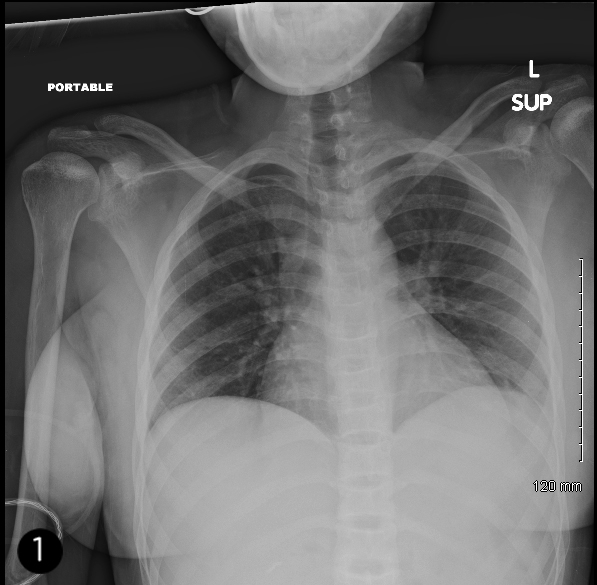
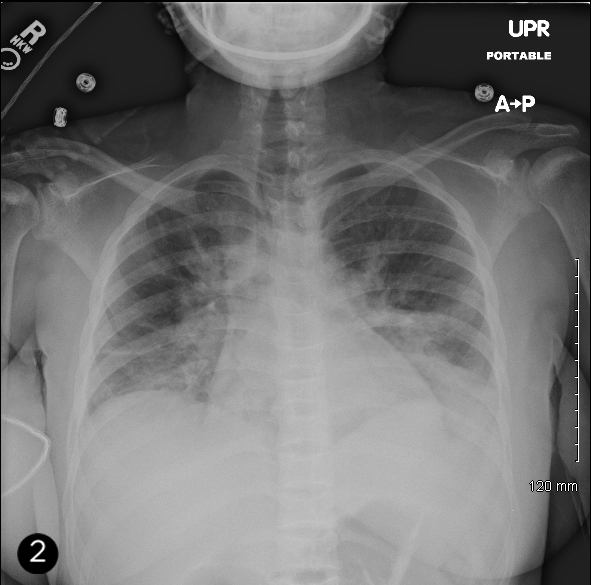
 She has good urine output. Her chest x-ray on admission (Image 1) and repeat x-ray after 36 hours (Image 2) are shown below.
 Which of the following, if instituted on initial presentation, may have helped prevent the clinical worsening that occurred in this patient?
She has good urine output. Her chest x-ray on admission (Image 1) and repeat x-ray after 36 hours (Image 2) are shown below.
Which of the following, if instituted on initial presentation, may have helped prevent the clinical worsening that occurred in this patient? (Multiple Choice)
4.9/5 (81)
(81) A 33-year-old man comes to the emergency department with a 2-day history of generalized weakness, lightheadedness, palpitations, and poor energy. Four weeks ago, he noticed an annular rash on his right thigh that lasted for a couple of days and then faded. He has no fever, weight loss, chest pain, or headache. He lives on Long Island, New York, and jogs 7 miles 3 times a week.
Which of the following is the most likely cardiac finding in this patient?
(Multiple Choice)
4.8/5 (76)
(76) A 64-year-old woman is brought to the emergency department after her husband found her obtunded at home. He found open bottles of her usual medications of sertraline, diphenhydramine, amitriptyline, and lorazepam at her bedside. Her husband does not know how many pills from each bottle may be missing. He reports that the patient appeared more depressed recently and had been expressing increased hopelessness. She has not seen any of her doctors in the past couple of months. The patient has a long-standing history of depression, lower back pain, and insomnia but no other medical problems. She has no known history of cardiac problems or stroke. The patient does not use tobacco, alcohol or illicit drugs. In the emergency department, she is sedated but intermittently arousable.
Temperature is 37.2 C (99 F), blood pressure is 95/45 mm Hg, and pulse is 106/min. Oxygen saturation is 94% on room air. The pupils are mildly dilated. Heart sounds are normal. The lungs are clear. She moves all extremities on command but has hyperreflexia of both lower extremities and exhibits frequent myoclonic jerks. She appears confused.
Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.8/5 (88)
(88) A 48-year-old man comes to the emergency department with a 4-day history of shortness of breath and fever. He is a chronic injection drug user. He has a history of a rash secondary to penicillin but has been treated previously for skin abscesses with cephalexin.
His temperature is 38.5 C (101.4 F). Cardiac examination reveals a faint diastolic murmur at the left sternal border. Skin examination shows needle track marks on both arms.
All 4 bottles of blood cultures obtained on admission grow Staphylococcus aureus (methicillin-susceptible). Intravenous cefazolin is initiated. A transthoracic echocardiogram reveals a 0.9 cm aortic valve vegetation with mild aortic regurgitation and normal left ventricular ejection fraction. On the third day of hospitalization, he is intermittently febrile and develops respiratory failure. Endotracheal intubation and mechanical ventilation is initiated. Chest x-ray reveals bilateral alveolar opacities consistent with pulmonary edema.
Which of the following is the best next step in the management of this patient?
(Multiple Choice)
4.9/5 (74)
(74) A 76-year-old man is brought to the emergency department due to intermittent blurry vision for the past 3 days. Today he feels as though "a curtain is falling in front" of his right eye. Family members have been worried about a decline in his general health over the past month as he has been eating less and has been less socially active. The patient has "felt down" for several weeks and has had headaches, a decreased appetite, and difficulty eating solid foods due to pain while chewing.
Medical history is notable for hypertension, intermittent atrial fibrillation, mild dementia, and a transient ischemic episode 6 months ago. A carotid ultrasonogram performed 6 months ago showed 40% stenosis in the carotid arteries bilaterally. Current medications include triamterene, hydrochlorothiazide, dabigatran, atorvastatin, and aspirin. The patient retired from coal mining 20 years ago and lives alone in an apartment. He does not use tobacco but drinks alcohol on social occasions.
Blood pressure is 142/78 mm Hg, and pulse is 78/min and regular. On physical examination, the pupils are reactive to light. Visual acuity is 20/40 in the left eye and 20/100 in the right eye. There is no scalp tenderness. The oropharyngeal mucosa is dry and no lymph nodes are palpable. Cardiopulmonary examination is unremarkable. The abdomen is soft and there is no organomegaly. Upper and lower limb deep tendon reflexes are 2+ bilaterally. Muscle power is 5/5 in all extremities.
Laboratory results are as follows:
 Chest x-ray reveals no abnormalities.
Which of the following is the most appropriate next step in management of this patient's condition?
Chest x-ray reveals no abnormalities.
Which of the following is the most appropriate next step in management of this patient's condition? (Multiple Choice)
4.9/5 (83)
(83) A 68-year-old man is brought to the emergency department because of mild headache, confusion, and right-sided upper extremity weakness for the last 2 days. The patient is accompanied by his wife, who provides most of the history. The patient was working in his garden 2 days ago when he developed a headache. He thought nothing of it since he was working outdoors on a hot and humid summer day. Over the next 24-hours, the patient became lethargic and developed right-sided weakness. He has not traveled recently and denies insect bites, sick contacts, or flu-like symptoms. His other medical problems include a history of ischemic stroke without residual neurologic deficits, hypertension, hyperlipidemia, and non-paralytic polio as a child. His medications include aspirin, simvastatin, and lisinopril.
His temperature is 38.1 C (100.5 F), blood pressure is 140/90 mm Hg, pulse is 101/min, and respirations are 16/min. Pulse oximetry shows an oxygen saturation of 98% on room air. His general physical examination is unremarkable. On neurological examination, he is obtunded and does not follow commands. There are no obvious cranial nerve deficits. He is able to localize briskly to noxious stimuli with the left arm, but he does not move the right arm. He is able to withdraw briskly to noxious stimuli in the lower extremities (left > right). The sensory examination is unreliable. Reflexes are 2+ on the left side of the body, but absent on the right side. Plantar responses are downgoing bilaterally. Superficial abdominal reflexes are present. Rectal tone is normal.
Non-contrast CT scan of the head showed no bleeding or masses.
Which of the following is the most likely diagnosis?
(Multiple Choice)
4.8/5 (66)
(66) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)