



 Chat with AI
Exam 1: Emergency Department

Exam 1: Emergency Department218 Questions
Exam 2: In-patient Facilities128 Questions
Exam 3: Office/Health Center900 Questions
Select questions type


A 50-year-old man is brought to the emergency department due to fever, malaise, confusion, and worsening headache for the last 8 days. He has a history of advanced AIDS and is noncompliant with antiretroviral therapy. His most recent CD4 lymphocyte count a month ago was 29/mm3. His other medical problems include hypertension and chronic hepatitis C infection.
The patient's temperature is 38.8 C (101.8 F), blood pressure is 110/70 mm Hg, pulse is 94/min, and respirations are 16/min. He is disoriented to place and time and has a left-sided visual field deficit. The remainder of the examination is unremarkable.
CT scan of the head without contrast is normal. A lumbar puncture yields the following results:
 India ink preparation of the cerebrospinal fluid shows encapsulated yeast. The patient is started on amphotericin B.
In addition to antifungal therapy, which of the following is the most effective strategy to improve this patient's outcome?
India ink preparation of the cerebrospinal fluid shows encapsulated yeast. The patient is started on amphotericin B.
In addition to antifungal therapy, which of the following is the most effective strategy to improve this patient's outcome? (Multiple Choice)
4.9/5  (69)
(69) A 47-year-old man is brought to the emergency department due to lightheadedness and palpitations. He denies chest pain, shortness of breath, or nausea. He reports a history of palpitations since he was a teenager and says he can usually stop them by bearing down. However, this maneuver did not work this time so he decided to come to the hospital. His other medical problems include type 1 diabetes mellitus and hypertension. He had a myocardial infarction 5 years ago, but has not had chest pain since then. His exercise tolerance is good.
Blood pressure is 80/40 mm Hg and his pulse is 150/min. Lungs are clear on auscultation. No heart murmurs are appreciated.
ECG is shown in the exhibit. 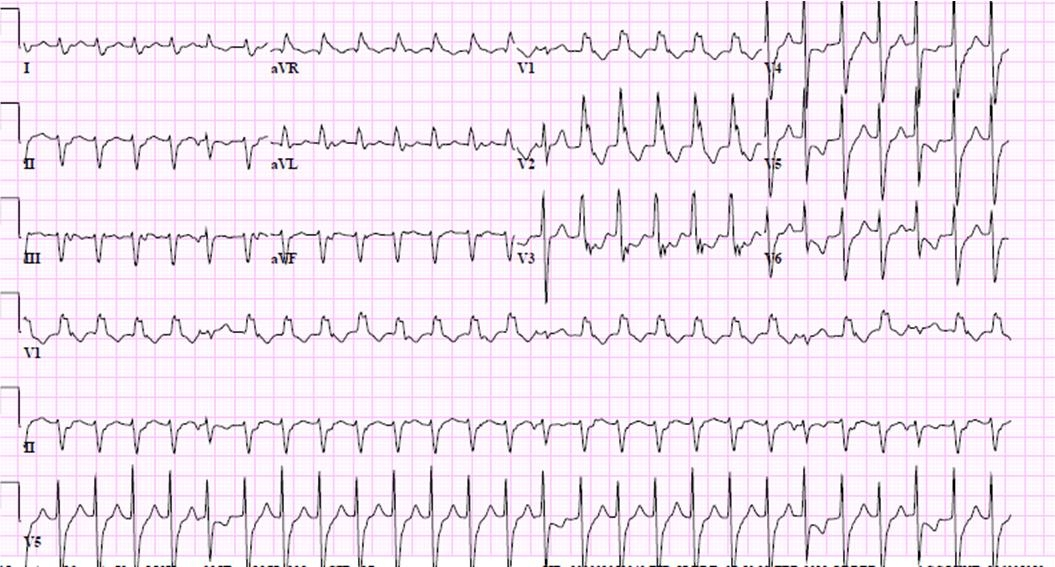 Which of the following is the best next step in managing this patient?
 (Multiple Choice)
4.9/5 (73)
(73) A 38-year-old man comes to the emergency department due to 1 day of left-sided chest and neck pain. He could not get comfortable the night before and eventually fell asleep in a semi-recumbent position. He had a sore throat a week ago. Medical history is also significant for acid reflux disease.
Temperature is 37.2 C (99 F), blood pressure is 132/80 mm Hg, and pulse is 90/min. Heart sounds are normal, and lungs are clear to auscultation. There are no skin rashes.
Laboratory results are as follows:
 ECG shows sinus rhythm with 1- to 2-mm diffuse ST-segment elevation, except for a 2-mm ST-segment depression in lead aVR. Chest x-ray reveals normal cardiac size and clear lung fields.
Which of the following initial therapies is most likely to cause recurrent symptomatic episodes in this patient?
ECG shows sinus rhythm with 1- to 2-mm diffuse ST-segment elevation, except for a 2-mm ST-segment depression in lead aVR. Chest x-ray reveals normal cardiac size and clear lung fields.
Which of the following initial therapies is most likely to cause recurrent symptomatic episodes in this patient? (Multiple Choice)
4.9/5 (68)
(68) A 54-year-old man comes to the emergency department for evaluation of fever and sore throat, and also due to trouble sleeping, poor energy, and hearing voices for the past 3 days. He has a history of hypertension, hypercholesterolemia, and schizoaffective disorder. The patient has been hospitalized several times in the past for auditory hallucinations ordering him to kill himself and has attempted suicide twice in the past 3 years. His symptoms have been stable on his current regimen of lithium and clozapine for the past 8 months. The patient's other medications include metoprolol and atorvastatin. He has started to feel depressed again and is concerned that the voices may get worse. He has no current suicidal ideation.
Temperature is 39.4 C (103 F), blood pressure is 110/70 mm Hg, pulse is 108/min, and respirations are 16/min. Examination is significant for pharyngeal erythema.
Laboratory results are as follows:
 In addition to antibiotic therapy, which of the following is the most appropriate next step in management of this patient?
 (Multiple Choice)
4.9/5 (71)
(71) A 21-year-old woman comes to the emergency department due to fever and headache. The patient began having myalgias 12 hours ago and then rapidly developed fever, progressive headache, nausea, and several episodes of vomiting. She has had no cough, dyspnea, diarrhea, or dysuria. The patient has no prior medical issues and takes no medications. She is a college student and lives in a dormitory on campus. She has not traveled recently and does not know if she has been exposed to sick contacts. The patient drinks 2-4 beers on weekends and does not use tobacco or illicit drugs.
Temperature is 39.2 C (102.7 F), blood pressure is 106/68 mm Hg, pulse is 115/min, and respirations are 20/min. The patient is ill-appearing with scattered petechial skin rash. No sinus tenderness is present, and the oropharyngeal mucosa is moist with no lesions. Auscultation of the heart and lungs is normal. She has neck rigidity but no other focal neurological deficits. Funduscopy shows no papilledema.
Which of the following infection-control measures is most appropriate at the present time for this patient?
(Multiple Choice)
4.9/5 (79)
(79) A 75-year-old man with moderate chronic obstructive lung disease is brought to the emergency department with acute onset of dyspnea that started this afternoon. He was discharged 2 days ago for a chronic obstructive pulmonary disease exacerbation treated with short-term noninvasive positive-pressure ventilation, corticosteroids, and antibiotics. He finished the oral antibiotics yesterday and has been nonambulatory since hospital discharge. He also complains of productive cough of whitish sputum and mild right-sided pleuritic chest pain. His other medical problems include hypertension, chronic lower-extremity edema with superficial ulcers, and severe right knee osteoarthritis.
His temperature is 37.2° C (99° F), blood pressure is 120/73 mm Hg, pulse is 114/min, and respirations are 22/min. Pulse oximetry shows 89% on room air. Jugular venous pressure is estimated at 7 cm H2O. Mild end-expiratory wheezing is heard bilaterally. There is bilateral, chronic-appearing edema of the lower extremities.
Laboratory results are as follows:
 ECG shows sinus tachycardia with nonspecific T-wave changes. Chest x-ray shows hyperinflated lung fields and linear densities at the right lower base consistent with atelectasis.
Which of the following is the best next step in managing this patient?
ECG shows sinus tachycardia with nonspecific T-wave changes. Chest x-ray shows hyperinflated lung fields and linear densities at the right lower base consistent with atelectasis.
Which of the following is the best next step in managing this patient? (Multiple Choice)
4.8/5 (92)
(92) A 20-year-old man is brought to the emergency department because of abdominal pain and vomiting. He has had mid-abdominal pain and dark stools for the last two days and his appetite has decreased. Over the last week, he has been 'feeling down' and has noticed a rash over both thighs. He denies any fever, chills, back pain, or diarrhea.
He suffered from mild intermittent asthma as a child but otherwise has an unremarkable past medical history. He does not smoke or consume alcohol. He denies any illicit drug use except for smoking marijuana several times in the past. He went camping in Vermont three weeks ago and travelled to Eastern Europe six months ago. While in Eastern Europe he had several bouts of diarrhea. He is sexually active with his girlfriend and uses condoms regularly.
His temperature is 36.7 C (98 F), blood pressure is 122/76 mmHg, and pulse is 98/min. On physical examination, no murmurs are heard. His abdomen is mildly tender without rebound. Stool for occult blood is positive. There are crops of purple non-blanching lesions affecting both thighs. Neurologic examination is unremarkable.
Laboratory results are as follows:
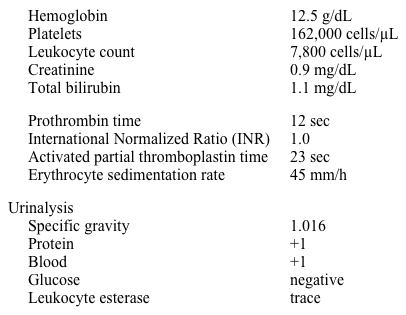 Which of the following is most likely to establish this patient's diagnosis?
 (Multiple Choice)
4.8/5 (73)
(73) A 56-year-old woman is brought to the emergency department after several hours of severe nausea, vomiting, palpitations, and altered mental status. She was diagnosed with Graves' hyperthyroidism 6 months ago and received methimazole, which was stopped 2 months ago due to a skin rash. The patient was treated with radioactive iodine (RAI) 3 days ago. She was not taking any medications before this admission. She does not use tobacco or alcohol.
On examination, the patient is agitated and confused. Temperature is 39.4 C (103 F), blood pressure is 160/90 mm Hg, pulse is 160/min, and respirations are 24/min. Pulse oximetry is 98% on room air. The thyroid is diffusely enlarged but nontender. The patient has a fine hand tremor and mild lid lag. The lungs are clear to auscultation. Her abdomen is soft and nontender. She has no muscle rigidity, and deep tendon reflexes are 2+ bilaterally throughout. Laboratory results are as follows:
 /_
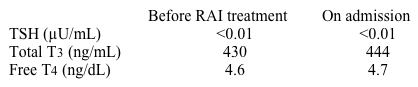 Which of the following is the best next step in management of this patient?
/_
Which of the following is the best next step in management of this patient? (Multiple Choice)
5.0/5 (72)
(72) A 65-year-old woman comes to the emergency department due to 2 days of nausea and vomiting. Her symptoms started a few hours after eating lunch, and she has since been unable to tolerate any oral intake. The patient began to experience epigastric and retrosternal discomfort this morning, and she now has pain in all her joints and muscles. Medical history includes hypertension; type 1 diabetes mellitus; myocardial infarction 2 years ago that was treated with coronary stenting; and severe, degenerative lumbar spinal stenosis. Medications include aspirin, atorvastatin, insulin, lisinopril, metoprolol, and morphine.
Temperature is 36.7 C (98 F), blood pressure is 150/90 mm Hg, pulse is 94/min, and respirations are 18/min. The patient is awake and oriented to time, place, and person. Physical examination is significant for diaphoresis and rhinorrhea. Abdominal examination is significant for epigastric tenderness and hyperactive bowel sounds. ECG shows nonspecific ST-T changes. An older ECG is not available for comparison.
Which of the following is the most likely cause of this patient's clinical presentation?
(Multiple Choice)
4.9/5 (75)
(75) An 82-year-old woman is brought to the emergency department after 2 episodes of large bloody bowel movements. She has no abdominal pain or vomiting. Her past medical history is significant for paroxysmal atrial fibrillation and hypertension. She takes daily low-dose aspirin.
Her blood pressure is 130/80 mm Hg, pulse is 88/min, and respirations are 14/min. Abdominal examination reveals no tenderness or organomegaly.
Laboratory results are as follows:
 While in the emergency department, the patient has another bloody bowel movement accompanied by transient dizziness and diaphoresis. Upper gastrointestinal endoscopy and colonoscopy reveal no source of bleeding.
Which of the following is the most likely additional physical finding on chest examination?
While in the emergency department, the patient has another bloody bowel movement accompanied by transient dizziness and diaphoresis. Upper gastrointestinal endoscopy and colonoscopy reveal no source of bleeding.
Which of the following is the most likely additional physical finding on chest examination? (Multiple Choice)
4.8/5 (75)
(75) A 33-year-old man comes to the emergency department due to a 2-day history of left knee pain and swelling. The patient has not had similar symptoms before and reports no preceding trauma, pain in other joints, skin rash, fever, or chills. Medical history is notable only for seasonal allergies, for which he takes loratadine as needed. The patient does not use tobacco, alcohol, or illicit drugs.
Temperature is 36.7 C (98 F), blood pressure is 110/56 mm Hg, pulse is 78/min, and respirations are 14/min. BMI is 22 kg/m2. Physical examination shows a moderate-sized left knee effusion. The knee is slightly warm but not erythematous. There is no locking of the joint or ligamentous laxity.
Laboratory results are as follows:
 X-ray of the left knee reveals linear calcifications of the menisci and articular cartilage with a moderate effusion but no fracture. Synovial fluid analysis shows leukocyte count of 15,400/mm3 with 80% neutrophils. Gram stain shows no organisms. Crystal analysis is pending.
Which of the following additional tests is most appropriate in evaluation of this patient's symptoms?
X-ray of the left knee reveals linear calcifications of the menisci and articular cartilage with a moderate effusion but no fracture. Synovial fluid analysis shows leukocyte count of 15,400/mm3 with 80% neutrophils. Gram stain shows no organisms. Crystal analysis is pending.
Which of the following additional tests is most appropriate in evaluation of this patient's symptoms? (Multiple Choice)
4.8/5 (76)
(76) A 32-year-old woman, gravida 1 para 0, at 32 weeks gestation is brought to the emergency department due to anterior chest and neck pain that began 3 hours ago. The pain was severe at onset but has decreased to moderate discomfort. She also has had mild nausea and epigastric discomfort. After the onset of the chest pain, the patient experienced tingling and weakness of her right arm accompanied by blurry vision and headache that lasted approximately 20-30 minutes. She has had a healthy pregnancy except for development of gestational diabetes mellitus at 24 weeks gestation. The patient's blood pressure was elevated during her last prenatal visit, and she was started on an antihypertensive medication. She has no other significant medical history. She does not use tobacco, alcohol, or illicit drugs.
On physical examination, the patient appears comfortable. Blood pressure is 176/104 mm Hg in the right arm and 180/99 mm Hg in the left arm, and pulse is 96/min. Oxygen saturation is 94% on room air. Her right pupil measures 4 mm and her left pupil measures 2 mm. There is slight ptosis on the left side. Lung fields are clear to auscultation with equal air entry on both sides. Cardiac examination reveals regular heart sounds with normal S1 and S2. The neurologic examination is otherwise unremarkable. Peripheral pulses are equal in all extremities. There is 2+ pitting peripheral edema of both lower extremities with some engorged varicose veins. There are normal deep tendon reflexes without clonus.
ECG shows sinus rhythm and a 1-mm downsloping ST-segment depression in leads aVL, V5, and V6. Urinalysis shows 1+ ketones, no protein, and no glucose.
Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.7/5 (74)
(74) A 65-year-old woman comes to the emergency department with acute loss of vision in her right eye. Three hours ago, she was watching television when she suddenly noticed the vision in her right eye become cloudy and then go completely black. She has no headache, eye pain, double vision, dysarthria, dysphasia, muscle weakness, or numbness. Past medical history includes type 2 diabetes mellitus and hypertension. Her medications include lisinopril and metformin. She has a 40-pack-year smoking history.
Vital signs are within normal limits. Visual acuity is 20/40 in the left eye and there is no light perception in the right eye. There is a relative afferent pupillary defect on the right. Ocular motility is normal on cardinal signs of gaze testing. The remainder of the physical examination is within normal limits.
Funduscopic examination is shown in the image below.
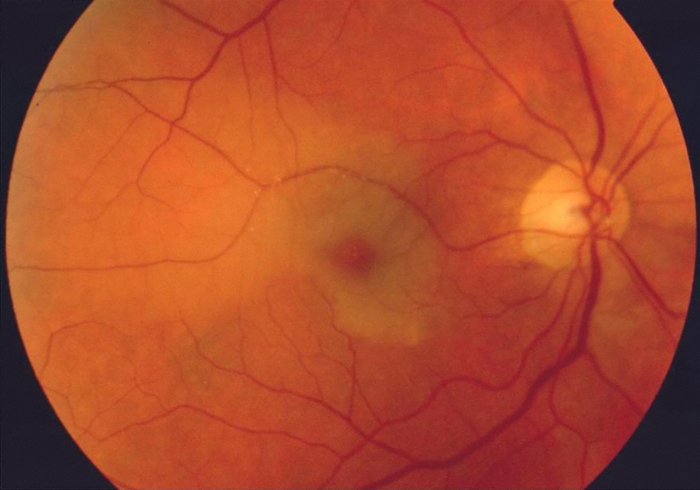 Which of the following is the most likely diagnosis for this patient's acute vision loss?
 (Multiple Choice)
4.8/5 (74)
(74) A 22-year-old woman comes to the emergency department due to heavy vaginal bleeding. The patient has always had heavy menses, but this time the bleeding has not stopped since it started 5 days ago. She has had to change her pad every 1-2 hours. The patient is recovering from an upper respiratory tract infection. Her medications include ibuprofen for headaches and iron supplementation for iron deficiency anemia. She has no other significant medical history. Her mother had heavy menstrual periods and frequent nosebleeds.
Vital signs are within normal limits. Bimanual examination reveals no palpable abnormalities.
Laboratory results are as follows:
 Which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.9/5 (80)
(80) A 65-year-old man is brought to the emergency department with a sudden onset of right-sided weakness and difficulty speaking that began one hour ago. His other medical problems include hypertension and hyperlipidemia. He has no history of stroke, myocardial infarction, recent trauma or surgery, or bleeding. He has smoked 2 packs of cigarettes daily for 30 years. His medications include hydrochlorothiazide, lisinopril, amlodipine, and simvastatin.
His temperature is 37.0 C (98.6 F), blood pressure is 180/100 mm Hg, and pulse is 115/min. On neurological examination, he is awake and alert. He has significant expressive aphasia and difficulty with repetition. He has right-sided hemiparesis (arm > leg) and numbness. His reflexes are increased on the right with an extensor plantar response.
His EKG shows an irregularly irregular rhythm and nonspecific T wave changes.
Laboratory results are as follows:
 A head CT is negative for hemorrhage. After initial evaluation, he is treated with intravenous tPA.
Which of the following is the most important step in the management of this patient within the next 24 hours?
A head CT is negative for hemorrhage. After initial evaluation, he is treated with intravenous tPA.
Which of the following is the most important step in the management of this patient within the next 24 hours? (Multiple Choice)
4.9/5 (95)
(95) An 18-year-old male has been brought to the emergency department for altered mental status. His friends report that he was at a party when he became incoherent and developed slurred speech, so they called 911. No other history is available.
On examination, he is drowsy and has slurred speech. His temperature is 36.7 C (98 F), blood pressure is 90/60 mm Hg, pulse is 96/min and respirations are 22/min. No focal neurologic findings are present and the general physical examination is unremarkable.
The patient's labs reveal:
 Which of the following is the most likely cause of this patient's illness?
 (Multiple Choice)
4.9/5 (87)
(87) A 40-year-old man comes to the emergency department after 2 episodes of coffee-ground vomiting. He reports black, tarry stools for 1 day. He has had no previous episodes and has no history of liver disease, jaundice, weight loss, ascites, edema, dysphagia, or illicit drug use. He has been taking ibuprofen for lower back pain for the past 2 weeks. He is otherwise in good general health and takes no prescription medications.
His supine blood pressure is 120/80 mm Hg and pulse is 84/min; after 1 minute of standing they are 118/76 mm Hg and 90/min. There is no jaundice or scleral icterus. Cardiopulmonary examination is normal. There is mild epigastric tenderness on palpation. There is no hepatomegaly or stigmata of chronic liver disease. The remainder of the examination is within normal limits.
A nasogastric tube is inserted, with return of coffee ground material and some bright red blood with clots.
Laboratory results are as follows:
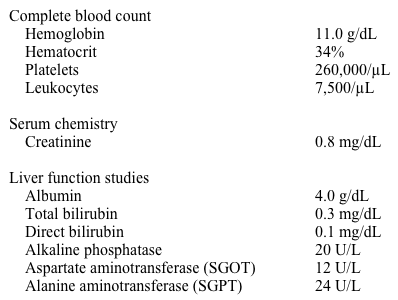 Urgent gastrointestinal endoscopy is scheduled.
Which of the following values for hemoglobin represents the optimal threshold for initiating blood transfusion in this patient?
Urgent gastrointestinal endoscopy is scheduled.
Which of the following values for hemoglobin represents the optimal threshold for initiating blood transfusion in this patient? (Multiple Choice)
4.8/5 (70)
(70) A 52-year-old woman with extensive pelvic ovarian cancer comes to the emergency department because of difficulty with urination. She has noticed decreasing urine volumes for the past two weeks. She denies dysuria, hematuria, or flank pain. Her other medical problems include hypertension and type 2 diabetes. Her current medications include metformin and lisinopril. She has had no urine output over the last 12 hours.
Her blood pressure is 142/70 mm Hg and pulse is 89/min. Lungs are clear on auscultation. Her abdomen is modestly distended and demonstrates fullness in both lower quadrants without a discrete mass. She has 2+ pitting bilateral lower extremity edema to the mid-shin.
Laboratory results are as follows:
 Insertion of a Foley catheter yields no urine. An ultrasound reveals grade 3 bilateral ureteric dilation. A urology consultant is able to advance pigtail catheters into both ureters from the bladder. Her urine output after catheter insertion improves to 600 cc/hr over the next two hours.
Which of the following is the best next step in management for this patient?
Insertion of a Foley catheter yields no urine. An ultrasound reveals grade 3 bilateral ureteric dilation. A urology consultant is able to advance pigtail catheters into both ureters from the bladder. Her urine output after catheter insertion improves to 600 cc/hr over the next two hours.
Which of the following is the best next step in management for this patient? (Multiple Choice)
4.8/5 (73)
(73) A 68-year-old right-handed man is brought by ambulance to the emergency department after his wife found him unresponsive. The wife states that her husband had not been feeling well for the last 12 hours. He woke up this morning "complaining of dizziness, neck pain, unsteadiness, and headache." As the day progressed, his symptoms worsened and he started vomiting. Towards the evening, the patient was lethargic and more confused than at his baseline. He has not had any fevers or chills.
His medical problems include poorly controlled hypertension, hyperlipidemia, ischemic stroke due to untreated high-grade left carotid artery stenosis, COPD on home oxygen, and chronic low back pain treated with oxycontin and hydrocodone. He lives with his wife and depends on her for most of his activities of daily living. For the past several months, his wife has had more difficulty taking care of him and administering his medications properly. She states that the patient has been "abusing his narcotic medications."
His temperature is 37.1 C (98.8 F), blood pressure is 170/110 mm Hg, pulse is 40/min, and oxygen saturation is 85% on room air. His general physical examination reveals a left carotid bruit, S4 gallop, and prominent expiratory wheezes with reduced air flow. On neurological examination, he appears comatose. Cranial nerve testing reveals absence of blink-to-threat, mid-position fixed and dilated pupils, absence of oculocephalic reflex, and presence of corneal, gag, and cough reflexes. Motor examination reveals extensor posturing in the upper and lower extremities. Reflexes are absent and plantar responses are mute. He does not grimace to pain.
Which of the following is the most likely etiology for this patient's presentation?
(Multiple Choice)
4.7/5 (87)
(87) A 58-year-old man with a long-standing diagnosis of schizoaffective disorder is brought to the emergency department for acute change in mental status. He lives in a group home and was assigned a new roommate 2 weeks earlier; the staff reports that the patient has become increasingly paranoid and agitated since then. His antipsychotic medication was changed from quetiapine to fluphenazine last week, but his behavior did not improve despite increasing dosages. The patient's other medications include a selective serotonin reuptake inhibitor and acetaminophen. Over the past several days, he developed a fever and has become increasingly confused.
On arrival, the patient's temperature is 40.0 C (104 F), blood pressure is 170/110 mm Hg, pulse is 115/min, and respirations are 22/min. The patient is diaphoretic, and examination shows diffuse rigidity. There is no evidence of infection. He is disoriented to place and time.
Laboratory evaluation shows leukocytes 11,500/mm3 and creatine kinase 3,500 U/L. Urinalysis is unremarkable.
In addition to supportive measures, which of the following is the most appropriate initial step in management of this patient?
(Multiple Choice)
4.8/5 (72)
(72) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)