



 Chat with AI
Exam 1: Emergency Department

Exam 1: Emergency Department218 Questions
Exam 2: In-patient Facilities128 Questions
Exam 3: Office/Health Center900 Questions
Select questions type


A 22-year-old man comes to the emergency department due to dysphagia for the past 3 hours. He was eating steak with his friends when he suddenly noticed a catching sensation in his throat. He tried to drink a few sips of beer, but the sensation continued to worsen. The patient has also had a hoarse voice for the last hour and difficulty swallowing his saliva. He has never had similar problems before.
Medical history includes seasonal allergic rhinitis, bronchial asthma, and gastroesophageal reflux disease. Current medications include albuterol metered-dose inhaler as needed and over-the-counter omeprazole. The patient has consumed 5 or 6 beers daily for the past 4 years but does not use tobacco or illicit drugs. His mother has atopic dermatitis.
Temperature is 37.5 C (99.5 F), blood pressure is 100/60 mm Hg, pulse is 92/min, and respirations are 14/min. Examination shows no abnormalities except for a lethargic young man who is drooling and speaking in broken sentences. An emergency endoscopy is planned.
In addition to a food bolus, which of the following would be the most likely endoscopic finding?
(Multiple Choice)
4.8/5  (80)
(80) An 83-year-old woman is brought to the emergency department due to chest pressure accompanied by nausea and vomiting. She felt well until 3 days ago when she was watching television and experienced substernal chest discomfort that radiated to her back. The pain lasted nearly an hour before resolving spontaneously; she also had nausea and vomiting at that time. The patient has never had chest pain before and has had no further discomfort since. She attributes the entire experience to drinking expired milk. The patient is currently without symptoms but is seen in the emergency department at the insistence of her daughter, who is a physician. Other medical problems include overactive bladder and osteoarthritis. Medications include oxybutynin and ibuprofen as needed.
Blood pressure is 110/75 mm Hg, pulse is 61/min, and respirations are 12/min. The patient is in no acute distress. Jugular venous pulsations are normal. Lungs are clear to auscultation bilaterally. Apical impulse is normal. No heart murmurs are heard. Pulses are 2+ and symmetrical. There is no edema.
ECG shows normal sinus rhythm with 2-mm Q waves in leads II, III, and aVF. Laboratory results are as follows:
 The patient is admitted to the intensive care unit and scheduled for coronary angiography. Shortly after arriving on the floor, she is noted to be markedly dyspneic. Repeat blood pressure is 90/45 mm Hg, pulse is 125/min, and respirations are 20/min. Lung examination reveals bilateral diffuse crackles. A pulmonary arterial catheter is placed, with the results shown below.
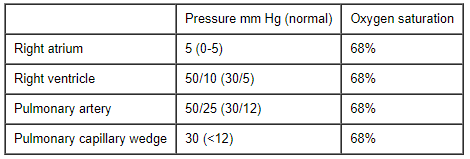 Which of the following is the most likely diagnosis in this patient?
The patient is admitted to the intensive care unit and scheduled for coronary angiography. Shortly after arriving on the floor, she is noted to be markedly dyspneic. Repeat blood pressure is 90/45 mm Hg, pulse is 125/min, and respirations are 20/min. Lung examination reveals bilateral diffuse crackles. A pulmonary arterial catheter is placed, with the results shown below.
Which of the following is the most likely diagnosis in this patient? (Multiple Choice)
5.0/5 (78)
(78) A 75-year-old man with a history of Parkinson disease, bipolar disorder, and hypertension is brought to the emergency department with confusion and fever. His caregivers report that last week he complained of stomach cramps and diarrhea and stopped taking his medications as he thought they were worsening his symptoms. His medications include carbidopa/levodopa, sertraline, lithium, lisinopril, and amlodipine. He does not use tobacco or illicit drugs but drinks 2 or 3 beers on weekends.
On evaluation, the patient is diaphoretic and confused. Temperature is 38.3 C (101 F), blood pressure is 180/95 mm Hg, pulse is 114/min, and respirations are 20/min. The mucous membranes are dry. He has prominent generalized muscular rigidity and bilateral tremor. The abdomen is nontender and bowel sounds are present.
Laboratory results are as follows:
 ECG shows sinus tachycardia and nonspecific T-wave changes. Spinal fluid evaluation shows no abnormalities. Which of the following is the most likely diagnosis?
 (Multiple Choice)
4.9/5 (79)
(79) A 47-year-old man is brought to the emergency department by his wife due to a 2-day history of lightheadedness and generalized weakness. The patient nearly lost consciousness on 2 occasions and has been unable to get out of bed since this morning. He has no chest pain, headaches, or nausea. Other medical problems include chronic low back pain, type 2 diabetes mellitus with evidence of retinopathy and proteinuria, and hypertension for which he was recently started on losartan. His other medications include ibuprofen, amitriptyline, and low-dose aspirin.
On examination, he appears lethargic with mild muscle weakness in both lower extremities. Initial blood pressure is 105/80 mm Hg.
His rhythm strip is shown here.
Which of the following is the most likely cause of this patient's symptoms?
(Multiple Choice)
4.8/5 (80)
(80) A 53-year-old woman comes to the emergency department with left-sided flank pain and dark urine. The patient's symptoms began this morning and are associated with dysuria and urinary urgency. Medical history includes type 2 diabetes mellitus and hypertension. Medications include lisinopril, amlodipine, atorvastatin, glargine insulin, and metformin. She does not use tobacco, alcohol, or illicit drugs.
Vital signs are normal, and physical examination is notable only for left upper abdominal tenderness.
Complete blood count is normal. Additional laboratory results are as follows:
 A noncontrast abdominal CT scan reveals a dense, 4-mm stone in the distal left ureter without hydronephrosis. The patient is treated with intravenous hydration and analgesics, which relieve her symptoms. The stone is passed without further intervention and sent for analysis.
Which of the following is the best next step in evaluation of this patient's condition?
A noncontrast abdominal CT scan reveals a dense, 4-mm stone in the distal left ureter without hydronephrosis. The patient is treated with intravenous hydration and analgesics, which relieve her symptoms. The stone is passed without further intervention and sent for analysis.
Which of the following is the best next step in evaluation of this patient's condition? (Multiple Choice)
4.9/5 (83)
(83) A 66-year-old retired police officer is brought to the emergency department due to abrupt-onset sharp anterior chest pain. The pain started approximately 2 hours ago while he was working on his car in the garage. The patient describes the pain, which radiates to his neck and lower jaw, as "the worst pain of my life." He also has epigastric discomfort. Medical problems include hypertension, hyperlipidemia, and benign prostatic hyperplasia. Medications include hydrochlorothiazide, losartan, tamsulosin, atorvastatin, and daily aspirin. The patient has a 30-pack-year smoking history but quit approximately 5 years ago. He is physically active and jogs 2-3 miles on most days.
Temperature is 37.2 C (99 F), blood pressure is 201/104 mm Hg in the right upper arm and 198/94 mm Hg in the left upper arm, pulse is 90/min, and respirations are 22/min. Pulse oximetry is 95% on room air. The patient appears very uncomfortable due to pain. There is a faint early diastolic murmur at the left sternal border and an S4 at the apex. The lungs are clear to auscultation. Mild epigastric tenderness is present on deep palpation without rebound. There is no peripheral edema, and lower extremity pulses are symmetric.
ECG shows high-voltage QRS complexes in the precordial leads and nonspecific ST-segment and T-wave changes.
Which of the following is the most appropriate initial treatment for this patient?
(Multiple Choice)
4.8/5 (76)
(76) A 67-year-old man comes to the emergency department due to 2 days of fever, malaise, headache, and myalgia. He has also noticed a nonpruritic skin rash on his right leg. The patient has had no abdominal pain, vomiting, or diarrhea. Prior medical problems include hypertension, type 2 diabetes mellitus, and chronic obstructive pulmonary disease. He is an ex-smoker and does not use alcohol or illicit drugs. The patient lives in Texas and a week ago returned from visiting family in Connecticut, where he spent most of his time outdoors.
Temperature is 39.4 C (103 F), blood pressure is 124/84 mm Hg, pulse is 102/min, and respirations are 20/min. Examination shows no scleral icterus or lymphadenopathy. Breath sounds are mildly decreased throughout. The abdomen is soft with no hepatosplenomegaly. There is no neck stiffness. A 4-cm, erythematous skin rash with central clearing is present on the right popliteal area.
Laboratory results are as follows:
 Chest x-ray reveals no parenchymal opacity or pleural effusion.
Which of the following diagnostic studies is most appropriate for this patient?
A)Anti-parvovirus antibodies
B)Antirickettsial antibodies
C)Bone marrow biopsy
D)Borrelia burgdorferi serology
E)Peripheral blood microscopy
Chest x-ray reveals no parenchymal opacity or pleural effusion.
Which of the following diagnostic studies is most appropriate for this patient?
A)Anti-parvovirus antibodies
B)Antirickettsial antibodies
C)Bone marrow biopsy
D)Borrelia burgdorferi serology
E)Peripheral blood microscopy (Not Answered)
This question doesn't have any answer yet
A 34-year-old woman is brought to the emergency department with acute onset of severe headache followed by generalized tonic-clonic seizures. The patient was feeling well until 6 hours ago, when she developed a 10/10 throbbing bilateral headache associated with blurry vision. Her headache is not exacerbated by change in head position, and nothing seems to improve the pain. She denies any nausea, vomiting, photophobia, vertigo, fever, or neck pain. She also denies any recent head or neck trauma. She has had upper respiratory tract symptoms for the last couple of days.
Her other medical problems include chronic migraines and non-essential hypertension related to renal artery stenosis from fibromuscular dysplasia. Her medications include topiramate and multiple anti-hypertensive agents including amlodipine, hydrochlorothiazide, lisinopril, and metoprolol. She also takes birth control pills and vitamins. She has never had a seizure before and has no family history of epilepsy. She works as a secretary and has smoked 2 packs of cigarettes daily for 10 years.
Her temperature is 37 C (98.6 F), blood pressure is 210/140 mm Hg, pulse is 80/min and regular, and respirations are 18/min with normal oxygen saturation. The general physical examination is unremarkable, except for an abdominal bruit. Neurological examination reveals that she is awake and alert, but is only oriented to person and place. Funduscopic examination reveals copper and silver wiring in the retina without papilledema. Pupils are equal, round, and reactive to light. Visual acuity is 20/200 bilaterally with intact visual fields to confrontation. There is no nystagmus and extra-ocular movements are full. The remainder of the neurological examination is unremarkable.
A non-contrast head CT showed hypodense regions with loss of grey-white matter differentiation in the posterior occipital-parietal lobes. An MRI of the brain without gadolinium (shown below) showed a symmetrical, increased T2/FLAIR signal abnormality in the subcortical white matter of the posterior occipital-parietal lobes.
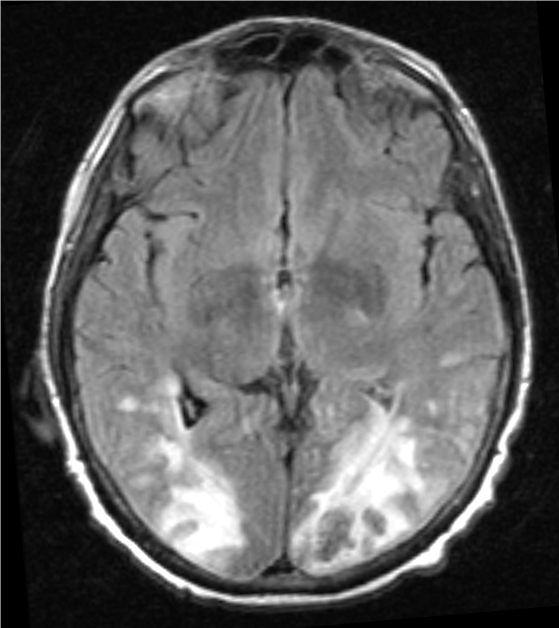 Which of the following is the most likely diagnosis?
 (Multiple Choice)
4.8/5 (93)
(93) A 67-year-old man is brought to the emergency department after a sudden cardiac arrest. He collapsed at home while watching television. His son started CPR as instructed by the 911 operator. Emergency medical services arrived in 7 minutes. The initial rhythm was noted to be ventricular fibrillation, and the patient was successfully defibrillated to normal sinus rhythm with return of spontaneous circulation.
The patient was intubated in the field, and intravenous amiodarone was administered. His medical problems include stable angina, hypertension, and hypercholesterolemia. Home medications include aspirin, metoprolol, enalapril, and atorvastatin.
Blood pressure is 170/100 mm Hg and pulse is 85/min. Examination shows scattered bilateral crackles. Heart sounds are normal. There is no response to painful stimulation. Oculocephalic and corneal reflexes are intact.
ECG shows normal sinus rhythm with ST segment depression in leads I, aVL, and V4-V6. A CT scan of the head without contrast shows no acute intracranial abnormality.
Which of the following is most likely to increase the chance of complete neurologic recovery in this patient?
(Multiple Choice)
4.9/5 (79)
(79) A 40-year-old man is brought to the emergency department by his wife for progressive lethargy, fever, and headache over the last 24-hours. He underwent craniotomy for meningioma resection 1 week ago. Since yesterday evening, the patient has had confusion, headaches, and a few episodes of vomiting. His wife denies any sick contacts, recent travel, flu-like symptoms, or skin rashes.
His temperature is 39.6 C (103.3 F), blood pressure is 140/90 mm Hg, pulse is 110/min and regular, and respirations are 16/min. There is no skin rash. The craniotomy incision is healing normally. On neurological examination, he is obtunded and does not follow commands. There is prominent neck stiffness. He is able to localize to noxious stimuli in the upper extremities and withdraw in the lower extremities.
Stat CT scan of the head shows no bleeding or masses. Lumbar puncture (LP) shows elevated opening pressure, white blood cell count of 1,200 cells/µL with 90% neutrophils, protein of 200 mg/dL, and glucose of 20 mg/dL.
Which of the following is the best next step in this patient's management?
(Multiple Choice)
4.9/5 (77)
(77) A 68-year-old man is brought to the emergency department due to lethargy and fever. He called his daughter this morning and told her that he had been having fever, chills, and headache. When she visited him a few hours later, he was warm to the touch and lethargic and soon had a tonic-clonic seizure. The patient is a widower who lives independently and is in excellent health. He has no history of previous seizure and has not recently traveled. He does not use alcohol or tobacco and has no allergies.
Temperature is 39.4 C (103 F), blood pressure is 80/50 mm Hg, pulse is 98/min, and respirations are 20/min. Pulse oximetry shows 96% on room air. The patient is lethargic and oriented only to person. He responds intermittently to questions but moves all 4 extremities on command. Moderate neck pain and stiffness are present. Deep-tendon reflexes are symmetric. No genital lesions are noted.
Laboratory workup is obtained and head CT scan and lumbar puncture are planned.
Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (83)
(83) A 27-year-old woman, gravida 1 para 0, at 29 weeks gestation comes to the emergency department due to 24 hours of fever and mild nausea. Two days ago, she developed urinary frequency and urgency. The patient has had no vomiting or abdominal pain. Her pregnancy has been complicated by gestational diabetes mellitus that was diagnosed 4 weeks ago and is well controlled with dietary modification. The patient has no known drug allergies.
On examination, she appears uncomfortable but is in no acute distress. Temperature is 38.9 C (102 F), blood pressure is 124/84 mm Hg, pulse is 96/min, and respirations are 18/min. Mucous membranes are moist. The lungs are clear to auscultation. There is mild tenderness to palpation in the suprapubic region but no costovertebral angle tenderness.
Laboratory results are as follows:
 A urine culture is obtained.
Which of the following is the most appropriate treatment at this time?
A urine culture is obtained.
Which of the following is the most appropriate treatment at this time? (Multiple Choice)
4.8/5 (70)
(70) A 73-year-old woman comes to the emergency department due to vision changes. Over the last few days, she has noticed blurred vision and scattered blind spots while watching television. She reports poor appetite and fatigue since an episode of gastroenteritis 2 weeks ago. She has no fever, headache, or muscle weakness but admits feeling unsteady.
Her past medical history is significant for hypertension, type 2 diabetes mellitus, heart failure with reduced ejection fraction (ejection fraction of 15%), and mild chronic obstructive lung disease. Her medications include tiotropium, torsemide, ramipril, carvedilol, spironolactone, digoxin, and empagliflozin. The patient is adherent with her medications and clinic visits. She is a former smoker with a 35-pack-year history.
Her blood pressure is 144/90 mm Hg supine and 140/90 mm Hg standing. Pulse is 52/min in both positions. BMI is 19 kg/m2. The mucous membranes appear dry. Lungs are clear to auscultation and no murmurs are heard on cardiac examination. There is mild epigastric tenderness on deep palpation. There is no peripheral edema. Neurologic examination is unremarkable except for mild unsteady gait.
Fingerstick glucose is 109 mg/dL.
Which of the following is the most likely diagnosis?
(Multiple Choice)
4.8/5 (81)
(81) A 62-year-old man is brought to the emergency department because of watery diarrhea, skin rash, and confusion. He has had diarrhea for the past 1-2 days and took some over-the-counter medicines. He returned from a cruise to Mexico 4 days ago. He ate shellfish and raw oysters with fried rice at a local restaurant 2 days ago.
His other medical problems include alcoholic liver cirrhosis, type 2 diabetes mellitus, hypertension, and mild chronic kidney disease. His medications include spironolactone, long-acting insulin, and propranolol. He is an ex-smoker and drinks 1-2 cans of beer on weekends. He occasionally smokes crack cocaine and marijuana.
His temperature is 38.9 C (102 F), blood pressure is 70/30 mm Hg, pulse is 124/min, and respirations are 22/min. Examination shows bilateral basal crackles. The abdomen is distended and non-tender. His skin shows multiple bullous lesions.
Laboratory results are as follows:
 Despite aggressive fluid resuscitation and antibiotics, the patient dies in the emergency department.
Which of the following is most likely responsible for this patient's initial presentation?
Despite aggressive fluid resuscitation and antibiotics, the patient dies in the emergency department.
Which of the following is most likely responsible for this patient's initial presentation? (Multiple Choice)
4.9/5 (85)
(85) A 76-year-old man is brought to the emergency department due to persistent back pain for the last 2 weeks. Over the last several days he has also had increasing difficulty walking. The patient was diagnosed with locally advanced prostate cancer a year ago and was treated with radiation therapy. His other medical problems include type 2 diabetes mellitus, hypertension, and hyperlipidemia.
Temperature is 36.7 C (98 F), blood pressure is 140/90 mm Hg, and pulse is 70/min. Neurological examination shows mild spastic paraparesis of the lower extremities.
Laboratory values show serum creatinine of 2.1 mg/dL and calcium of 9.8 mg/dL. MRI of the spine reveals a discrete epidural mass at the T8-T9 levels. There is surrounding spinal cord edema.
In addition to intravenous corticosteroids, which of the following would be most helpful to improve mobility in this patient?
(Multiple Choice)
4.9/5 (79)
(79) A 55-year-old man comes to the emergency department with right foot pain. Three days ago, he noticed that he was tripping and falling frequently. He initially experienced pain and tingling in his right lower leg that progressively turned into weakness 24 hours later. Three months ago, he experienced similar pain and weakness in his left hand. His past medical history includes type 2 diabetes mellitus, hypertension, and lumbar degenerative disk disease.
His blood pressure is 150/90 mm Hg and pulse is 90/min. On physical examination, he has palpatory tenderness along the lumbar spine and trophic skin changes with stasis dermatitis in the lower extremities. Cranial nerve examination is unremarkable. Strength is 4/5 in the left hand and 3/5 in the right foot. Motor examination is normal in all other muscle groups. There is absence of pain and temperature sensation up to the knees with preserved vibration and proprioception. Reflexes are normal in the upper extremities and the knees but are absent at the ankles bilaterally. He has a steppage gait.
Which of the following is the most likely diagnosis?
(Multiple Choice)
4.7/5 (86)
(86) A 73-year-old woman comes to the emergency department because of chest discomfort. She was involved in a low velocity motor vehicle accident earlier in the day in which she backed into another car in the parking lot. She was wearing a seatbelt at the time and suffered no injuries. This is her second accident in the last three months, and she is very worried that her children will take away her car as a result.
Approximately one hour after returning home, she noted the onset of substernal chest pressure, described as a "heaviness" which radiates to the jaw bilaterally and shortness of breath. She has never experienced these symptoms before. Her other medical problems include hypertension and hypothyroidism. Her medications include lisinopril, hydrochlorothiazide, levothyroxine, and aspirin.
Her temperature is 36.7 C (98 F), blood pressure is 145/75 mm Hg, and pulse is 104/min. Her BMI is 24 kg/m2. The patient is in mild distress. The estimated jugular venous pressure is 8 mm H2O. There is a 2/6 systolic ejection murmur at the right upper sternal border, which radiates to the carotids bilaterally. Her lungs are clear on auscultation. Her peripheral pulses are 2+ and no peripheral edema is present.
An electrocardiogram demonstrates sinus tachycardia and 2 mm of ST elevation in leads V1 to V4 with T wave inversions. No prior EKG is available for comparison.
 Emergent coronary angiography is performed, which demonstrates no obstructive coronary artery disease. Echocardiogram shows dyskinesis of the mid and apical left ventricle with hyperkinesis of the base and an overall left ventricular ejection fraction of 25%.
Which of the following best explains this patient's symptoms?
Emergent coronary angiography is performed, which demonstrates no obstructive coronary artery disease. Echocardiogram shows dyskinesis of the mid and apical left ventricle with hyperkinesis of the base and an overall left ventricular ejection fraction of 25%.
Which of the following best explains this patient's symptoms? (Multiple Choice)
4.7/5 (61)
(61) A 70-year-old man is brought to the emergency department by his nephew after being found poorly responsive at home. The patient lives alone and had not been seen for 2 weeks. His family has noticed that he has been confused and less active over the past few months. Medical history is unknown, and family members report only that the patient takes several pills a day for "heart issues," blood pressure, and headaches. Emergency department records show a recent visit for back pain, which was treated with opioid analgesics and centrally acting muscle relaxants.
Temperature is 35 C (95 F), blood pressure is 120/100 mm Hg, pulse is 55/min, and respirations are 10/min. The patient is lethargic and oriented only to person. He has a puffy face and hands and an enlarged tongue. Pupils are normal and reactive. The neck is supple. Cranial nerve, cardiac, pulmonary, and abdominal examinations are unremarkable. The patient moves all extremities on command.
Laboratory results are as follows:
 Chest x-ray shows a mildly enlarged cardiac silhouette and no infiltrates. ECG shows sinus bradycardia, a QTc interval of 450 msec, and T-wave flattening. Additional laboratory testing is pending.
Which of the following is the most appropriate next step in management of this patient?
Chest x-ray shows a mildly enlarged cardiac silhouette and no infiltrates. ECG shows sinus bradycardia, a QTc interval of 450 msec, and T-wave flattening. Additional laboratory testing is pending.
Which of the following is the most appropriate next step in management of this patient? (Multiple Choice)
4.8/5 (67)
(67) A 40-year-old man with known HIV infection comes to the emergency department with lethargy and right-sided weakness. He is accompanied by his girlfriend, who says that he has been behaving strangely for the past 3-4 weeks. He has also been complaining of headaches. The patient does not routinely follow up with his physician, and his last CD4 count 3 months ago was 50 cells/µL.
His temperature is 37.2° C (99° F), blood pressure is 140/80 mm Hg, pulse is 88/min, and respirations are 16/min. Pulse oximetry shows 96% on room air. The patient appears lethargic but follows commands. He has poor dentition and oral thrush. No neck stiffness is present. He has a pronator drift in the right upper extremity with slightly increased tone and brisk reflexes. The remainder of the examination is normal.
Diffusion-weighted magnetic resonance imaging of the brain with and without contrast reveals a large (4.2-cm) ring-enhancing deep subcortical white matter lesion with surrounding vasogenic edema and mass effect.
What is the most likely diagnosis in this patient?
(Multiple Choice)
4.8/5 (86)
(86) A 62-year-old man comes to the emergency department because of fever, chills, and productive cough for the last 5 days. Three days ago, he began to experience right-sided chest pain and shortness of breath. The chest pain increases with deep breathing. He was discharged from the hospital one week ago after an elective right knee replacement. His other medical problems include hypertension, type 2 diabetes, and hyperlipidemia. He has smoked one pack of cigarettes per day for 40 years and he drinks 1-2 glasses of wine on the weekends. He does not use illicit drugs.
His temperature is 39.4 C (103 F), blood pressure is 120/70 mm Hg, pulse is 98/min, and respirations are 22/min. The patients pulse oximetry is 92% on room air. Breath sounds are decreased at the right lung base with dullness to percussion. Heart sounds are normal. The right knee scar is healing well. The remainder of the examination is unremarkable.
Laboratory results are as follows:
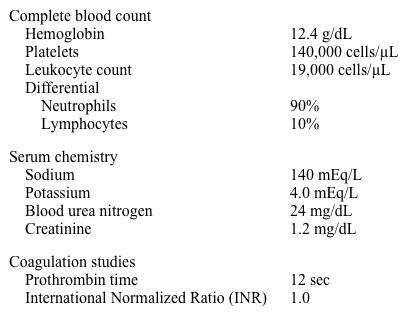 Chest x-ray shows right lower lobe consolidation and pleural effusion. Lateral decubitus film shows free layering pleural effusion.
The patient is started on broad-spectrum antibiotics. Thoracentesis is performed and 250 mL of cloudy pleural fluid is removed. Pleural fluid glucose is 45 mg/dL and pH is 7.18. Gram stain shows many neutrophils and gram-negative rods.
Which of the following is the best next step in management?
Chest x-ray shows right lower lobe consolidation and pleural effusion. Lateral decubitus film shows free layering pleural effusion.
The patient is started on broad-spectrum antibiotics. Thoracentesis is performed and 250 mL of cloudy pleural fluid is removed. Pleural fluid glucose is 45 mg/dL and pH is 7.18. Gram stain shows many neutrophils and gram-negative rods.
Which of the following is the best next step in management? (Multiple Choice)
4.8/5 (89)
(89) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)