



 Chat with AI
Exam 1: Emergency Department

Exam 1: Emergency Department218 Questions
Exam 2: In-patient Facilities128 Questions
Exam 3: Office/Health Center900 Questions
Select questions type


A 56-year-old man comes to the physician because of a chest and epigastric discomfort since this morning. While sitting in the waiting area, he suddenly becomes unresponsive. He has scarce respiratory efforts and there is no palpable pulse over the carotid arteries.
Which of the following is the most appropriate next step in managing this patient?
(Multiple Choice)
4.8/5  (82)
(82) A 36-year-old man with known HIV infection comes to the emergency department because of a two week history of malaise and non-productive cough. He has not been compliant with his HIV medications. He denies any illicit drug abuse. He has never been hospitalized in the past.
His temperature is 38.9 C (102 F), blood pressure is 122/70 mm Hg, and pulse is 112/min. His oxygen saturation is 90% on room air. His BMI is 23 kg/m2. His sternocleidomastoid muscles are prominent bilaterally with each respiration. Cardiac examination reveals tachycardia without any murmurs. Scattered rhonchi are heard on lung auscultation. His abdominal examination is within normal limits.
Laboratory results are as follows:
 Chest x-ray shows bilateral patchy interstitial infiltrates.
Intravenous fluids and high dose intravenous trimethoprim-sulfamethoxazole are started.
The patient should be specifically monitored for which of the following?
Chest x-ray shows bilateral patchy interstitial infiltrates.
Intravenous fluids and high dose intravenous trimethoprim-sulfamethoxazole are started.
The patient should be specifically monitored for which of the following? (Multiple Choice)
4.8/5 (79)
(79) A 72-year-old man is brought to the emergency department due to severe, tearing pain in the anterior and posterior areas of his chest for the last 2 hours. The pain is accompanied by diaphoresis and mild shortness of breath. The patient has never experienced similar pain. Stress testing 6 months ago showed mild ischemia in the inferior wall, which was treated medically. Other medical problems include hypertension, hyperlipidemia, gout, and chronic constipation. The patient is a lifelong nonsmoker.
Blood pressure is 80/60 mm Hg in the right arm and 76/47 mm Hg in the left arm, and pulse is 102/min. The jugular veins are distended when the patient is sitting. Heart sounds are distant and no murmurs are heard on cardiac auscultation. The lungs are clear to auscultation. There is no peripheral edema. The extremities are cold, and peripheral pulses are markedly diminished.
ECG performed in the emergency department is shown in the exhibit.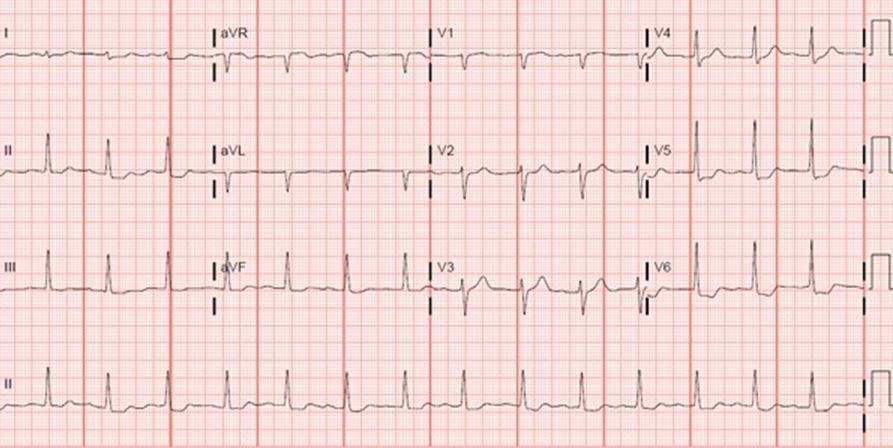 Which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.8/5 (79)
(79) A 26-year-old woman comes to the emergency department with a 1-day history of chills, headache, and muscle aches. A week ago, she returned from a month-long trip to Tanzania. During her travels, she stayed with friends in local hotels and ate mostly at local restaurants. She spent significant time outdoors, including swimming in local lakes. She had taken atovaquone-proguanil for malaria prophylaxis and was compliant with therapy.
The patient's temperature is 38 C (100.4 F). Physical examination shows multiple urticaria-type lesions on the trunk and upper extremities.
Laboratory studies are as follows:
 Which of the following is the most likely diagnosis?
 (Multiple Choice)
4.8/5 (84)
(84) A 32-year-old right-handed woman with no significant past medical history is brought to the emergency department with a generalized tonic-clonic seizure. Before the seizure, her husband noticed the patient fumbling with the buttons on her shirt and smacking her lips. Following the seizure, she appeared to be confused for 30-40 minutes. The patient states that she could not sleep the night before due to a deadline at work. She has no history of head trauma, fevers, headaches, or vision problems.
Her vital signs are within normal limits. She is awake, cooperative, and follows commands. Her speech is fluent and her repetition is appropriate. The remainder of her mental status and neurologic examinations shows no abnormalities.
Magnetic resonance imaging of the brain reveals an infiltrating 2-cm lesion in the temporal lobe that produces no mass effect and is most consistent with a low-grade glioma.
Neurosurgery evaluation is pending.
What is the best next step in management of this patient?
(Multiple Choice)
4.7/5 (83)
(83) A 75-year-old man is brought to the emergency department due to right-sided weakness on awakening this morning. The patient has had no headache, nausea, double or blurry vision, or vertigo. Medical history includes type 2 diabetes mellitus, hypertension, and hyperlipidemia. Medications include metformin, lisinopril, and atorvastatin.
Temperature is 36.7 C (98 F), blood pressure is 168/96 mm Hg, pulse is 92/min, and respirations are 12/min. Physical examination reveals a carotid bruit on the left. Neurologic examination shows mild dysarthria, right central facial palsy, and mild right hemiparesis.
ECG shows normal sinus rhythm. MRI of the brain reveals multiple acute cortical and subcortical infarcts in the left middle cerebral artery territory, as shown in the image below. CT angiography of the head and neck reveals 80%-90% stenosis at the origin of the left internal carotid artery. Echocardiogram shows mild left atrial enlargement, left ventricular hypertrophy, and left ventricular ejection fraction of 65%. The patient receives low-dose aspirin in the emergency department.
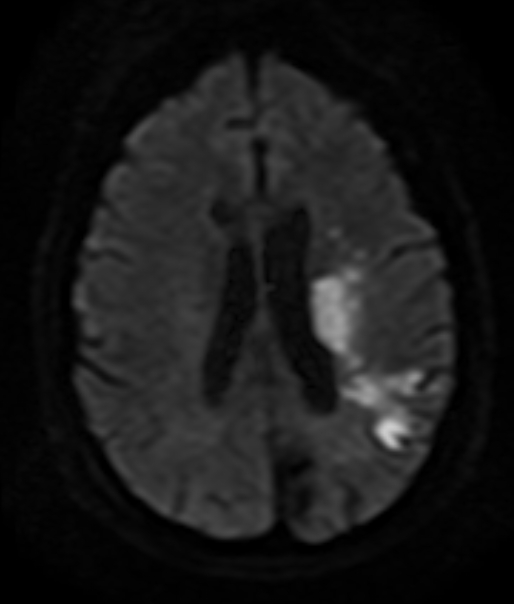 Which of the following is the most appropriate next step in management of this patient?
 (Multiple Choice)
4.9/5 (83)
(83) A 51-year-old woman comes to the emergency department due to fever and generalized weakness. She was diagnosed with metastatic ovarian cancer 3 months ago and is on systemic chemotherapy after undergoing cytoreduction surgery. Cycle 2 of chemotherapy was completed 10 days ago. The patient initially had nausea and vomiting but was feeling better the last few days. However, yesterday afternoon she became quite fatigued, and this morning she had a temperature of 39.1 C (102.4 F). Her oncologist recommended a visit to the emergency department for evaluation. The patient has had no sore throat, sinus pain, cough, shortness of breath, chest pain, diarrhea, or urinary symptoms. She has no other chronic medical problems but had prolonged neutropenia after her first cycle of chemotherapy. She does not use tobacco or alcohol and has no known drug allergies.
Temperature is 38.6 C (101.5 F), blood pressure is 110/70 mm Hg, pulse is 112/min and regular, and respirations are 20/min. Pulse oximetry shows 96% on room air. The patient is alert and cooperative. No lymphadenopathy is present. There is no skin rash or erythema or tenderness around the subcutaneous venous access device. Lungs are clear to auscultation, and no heart murmurs are present. The abdomen is soft and nontender. Neurologic examination shows no abnormalities.
Laboratory results are as follows:
 Chest-x ray reveals no new parenchymal opacities or pleural effusion. Urinalysis reveals no pyuria. Two sets of blood cultures are drawn and intravenous fluids are administered.
Which of the following is the best initial treatment for this patient?
Chest-x ray reveals no new parenchymal opacities or pleural effusion. Urinalysis reveals no pyuria. Two sets of blood cultures are drawn and intravenous fluids are administered.
Which of the following is the best initial treatment for this patient? (Multiple Choice)
4.8/5 (73)
(73) A 34-year-old man with history of type 1 diabetes mellitus comes to the emergency department because of retrosternal chest pain for the past 12 hours. His symptoms started last night and woke him up several times because he could not find a comfortable position. He also describes pain in his left shoulder on deep inspiration. His father died of a heart attack at the age of 46. He quit smoking 8 years ago.
His temperature is 37.8 C (100.2 F), blood pressure is 110/70 mm Hg, and pulse is 100/min. No murmurs are heard on cardiac auscultation. Fine crackles are heard at the left lung base that clear with coughing. An ECG is obtained and shown in this exhibit. 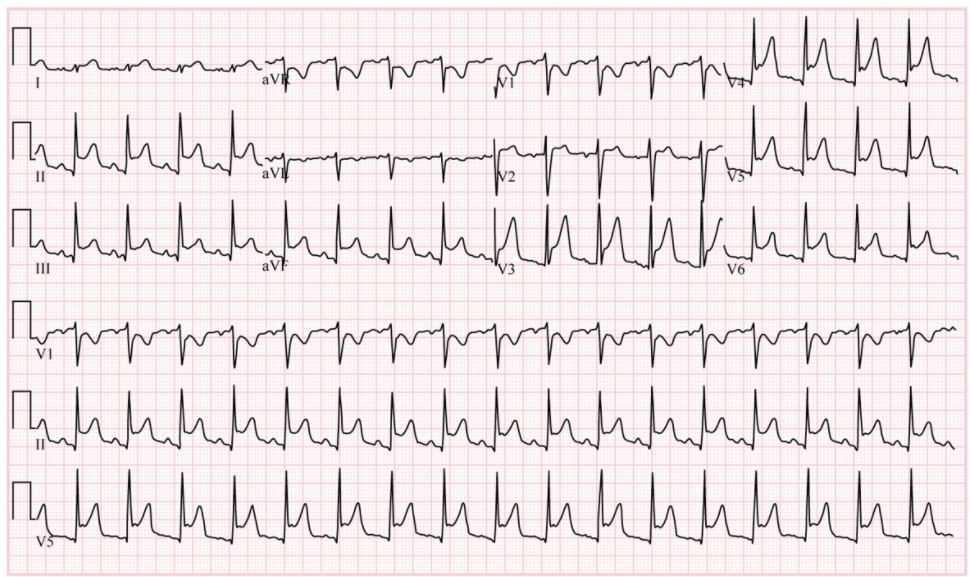 Which of the following changes would be expected on repeat ECG one week later?
 (Multiple Choice)
4.8/5 (80)
(80) A 68-year-old man is brought to the emergency department with hypoxemic respiratory failure. He has had worsening shortness of breath associated with fevers and a cough productive of yellowish sputum for the past 2 days. The patient has a past medical history of stable angina, hypertension, severe chronic obstructive pulmonary disease, and peptic ulcer disease. His trachea is intubated and mechanical ventilation is initiated.
Which of the following is most likely to decrease the risk of stress ulcers associated with gastrointestinal bleeding in this patient?
(Multiple Choice)
4.9/5 (75)
(75) A 27-year-old man comes to the emergency department due to scrotal pain. Three days ago, he was diagnosed with acute epididymitis by his primary care physician and was treated with ceftriaxone and doxycycline. Nuclear acid amplification test for Chlamydia trachomatis was positive. He has persistent pain and states that he has been compliant with his oral doxycycline. He denies anal intercourse.
Examination reveals tenderness and swelling involving the left side of the scrotal sac. The pain is relieved with elevation of the sac and the cremasteric reflex is equivocal. Rectal examination shows a normal-sized and nontender prostate.
Which of the following is the most appropriate next step in management?
(Multiple Choice)
4.9/5 (78)
(78) A 34-year-old man comes to the emergency department due to skin rash that he noticed this morning on his arms and legs. He has also had fever and headache for 3 days. The patient had a root canal 2 weeks ago with mild post-procedure pain and gum swelling. Medical history is otherwise noncontributory. He is an avid biker who enjoys spending time outdoors. The patient does not use alcohol or tobacco. He has a male partner with whom he has been in a stable relationship for the last 2 years.
Temperature is 39.7 C (103.5 F), blood pressure is 122/70 mm Hg, and pulse is 114/min and regular. No lymph node enlargement is present. There is no sinus tenderness to palpation. The lungs are clear to auscultation. There are no heart murmurs. The abdomen is soft and nontender, and the tip of the spleen is not palpated. Maculopapular rash with petechiae is present on the arms and legs. There are no meningeal signs.
Laboratory results are as follows:
 Two blood smears are negative for potential blood-borne pathogens.
Which of the following is the most appropriate next step in management of this patient?
Two blood smears are negative for potential blood-borne pathogens.
Which of the following is the most appropriate next step in management of this patient? (Multiple Choice)
4.9/5 (80)
(80) A 52-year-old construction worker is brought to the emergency department due to the sudden onset of severe substernal chest pain. His initial ECG in the emergency department shows sinus rhythm with left bundle branch block. There is no previous ECG available for comparison.
On physical examination, the patient appears to be in significant distress. Temperature is 37.2 C (99 F), blood pressure is 122/75 mm Hg, pulse is 102/min, and respirations are 22/min. Pulse oximetry is 86% on room air. Lung examination reveals minimal bibasilar rales. Cardiac examination reveals regular rhythm with no significant audible murmurs or pericardial rub.
An emergency cardiac catheterization shows an occluded proximal left anterior descending artery (LAD). The left circumflex and right coronary arteries have mild luminal irregularities. An intra-aortic balloon counterpulsation (IABP) device is inserted, and the patient undergoes successful primary angioplasty of the proximal LAD with drug-eluting stent placement.
Over the next 36 hours, the patient's hemodynamics improve, and IABP support is weaned and eventually removed. He experiences several episodes of asymptomatic monomorphic ventricular ectopy. He feels well and he is able to ambulate with no symptoms. Current medications include low-dose aspirin, clopidogrel, atorvastatin, and lisinopril. The patient is started on low-dose metoprolol succinate and does well over the next 2 days.
ECG shows sinus rhythm with a persistent left bundle branch block pattern. A transthoracic echocardiogram shows a large area of akinesis in the mid- to distal anterior, anterolateral, and anteroapical segments, with a left ventricular ejection fraction of 25%. There is trace mitral and tricuspid regurgitation.
Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.9/5 (70)
(70) A 76-year-old man is brought to the emergency department after having 6 hours of shortness of breath and chest pain. His initial blood pressure is 102/72 mm Hg and pulse is 102/min. His oxygen saturation is 82% on 15 liters of oxygen via face mask. Bilateral rales are heard over the lower to middle lung fields. His initial ECG shows sinus tachycardia and a left bundle branch block. He is intubated and rushed to the cardiac catheterization lab.
He is found to have an occluded proximal left anterior descending artery and mild atherosclerosis involving the other coronary arteries. He has successful percutaneous revascularization with restoration of coronary flow. A pulmonary artery catheter is placed at the end of the procedure for hemodynamic monitoring and he is transferred to the coronary care unit. His current medications include aspirin, clopidogrel, intravenous unfractionated heparin, eptifibatide, furosemide, and propofol. Six hours after the procedure, his blood pressure is 78/48 mm Hg, and his pulse is 120/min and regular. His ECG shows sinus tachycardia and left bundle branch block pattern.
Hemodynamic readings from the pulmonary artery catheter show the following:
 Which of the following is the most likely cause of this patient's hypotension?
 (Multiple Choice)
4.9/5 (76)
(76) A 67-year-old man is brought to the emergency department by his wife due to progressive lethargy over the last 24 hours. Before going to bed, he had a fever, chills, headache, and neck pain and was "feeling tired." His wife had difficulty waking him up this morning. The patient has had no sick contacts, recent travel, flu-like symptoms, or skin rashes. He has a history of type 2 diabetes mellitus, hypertension, hyperlipidemia, and ischemic stroke with a complete recovery of neurologic deficits. The patient takes aspirin, metformin, chlorthalidone, lisinopril, and atorvastatin. He is a retired school teacher and has no history of tobacco, alcohol, or illicit drug use.
Temperature is 39.1 C (102.3 F), blood pressure is 140/90 mm Hg, pulse is 110/min, and respirations are 16/min. Pulse oximetry shows an oxygen saturation of 97% on room air. The patient is obtunded and does not follow commands but is able to localize to pain in the upper extremities and withdraw the lower extremities to noxious stimuli. Physical examination is otherwise unremarkable. Fingerstick glucose level is 190 mg/dL. Blood cultures are drawn.
Which of the following is the best next step in immediate management of this patient?
(Multiple Choice)
4.8/5 (67)
(67) A 52-year-old man comes to the emergency department after 1 day of melena and 2 episodes of coffee-ground emesis. Over the past several months he has had episodic epigastric discomfort, especially several hours after a meal and at night. The patient has had no dysphagia, back pain, or weight loss, and has not used aspirin or nonsteroidal anti-inflammatory drugs. Chronic medical problems include hypertension and hypercholesterolemia. He does not use tobacco, alcohol, or illicit drugs.
Blood pressure is 126/70 mm Hg, and pulse is 86/min with no orthostatic changes. The abdomen is soft and nontender, and rectal examination reveals occult blood-positive black stool.
Laboratory results are as follows:
 Intravenous proton pump inhibitor therapy is started. Upper gastrointestinal endoscopy shows a 2-cm duodenal ulcer with a visible vessel at the base. Endoscopic treatment is performed; the patient has no recurrent hematemesis, and his hemoglobin level remains stable. Gastric mucosal biopsies are negative for Helicobacter pylori.
Which of the following is the most appropriate next step regarding evaluation and treatment for H pylori infection in this patient?
Intravenous proton pump inhibitor therapy is started. Upper gastrointestinal endoscopy shows a 2-cm duodenal ulcer with a visible vessel at the base. Endoscopic treatment is performed; the patient has no recurrent hematemesis, and his hemoglobin level remains stable. Gastric mucosal biopsies are negative for Helicobacter pylori.
Which of the following is the most appropriate next step regarding evaluation and treatment for H pylori infection in this patient? (Multiple Choice)
4.7/5 (83)
(83) A 24-year-old man comes to the emergency department after 1 week of fever, chills, and headache. He also complains of nausea and an episode of vomiting. He has no abdominal pain or diarrhea. Three weeks ago, he returned from travelling in southern Africa, where he volunteered at a medical clinic in rural Malawi for 3 months. He took doxycycline for the entire trip until returning to the United States. He drank mostly bottled water but did eat local cooked food. He had no sexual activity, injected drug use, or freshwater exposure during his travels.
His temperature is 39.4 C (103 F), blood pressure is 120/76 mm Hg, pulse is 106/min, and respirations are 18/min. He is uncomfortable but nontoxic-appearing. There is no skin rash. Pupils are equal, round, and reactive and there is mild scleral icterus but no conjunctival lesions or suffusion. There is no neck stiffness or meningeal signs. Abdominal examination reveals tenderness in the left upper quadrant and mild splenomegaly.
Laboratory results are as follows:
 Which test is most likely to establish the diagnosis in this patient?
 (Multiple Choice)
4.9/5 (73)
(73) A 68-year-old woman is brought to the emergency department due to worsening diarrhea and abdominal pain. The patient has had watery diarrhea every 3-4 hours for the past 2 days, and today she also had mild nausea but has been tolerating oral fluids. The patient was discharged from the hospital 10 days ago after treatment for an Escherichia coli urinary tract infection. Other medical conditions include hypertension, type 2 diabetes mellitus, hyperlipidemia, and chronic kidney disease.
Temperature is 39.3 C (102.7 F), blood pressure is 90/60 mm Hg, and pulse is 120/min. On examination, the patient appears lethargic. There is moderate abdominal distension and diffuse tenderness but no rebound tenderness or rigidity.
Laboratory results are as follows:
 CT scan of the abdomen reveals an 8-cm dilation of the ascending and transverse colon with mucosal thickening. Stool samples for analysis are obtained.
In addition to IV fluids, which of the following is the most appropriate next step in management of this patient?
CT scan of the abdomen reveals an 8-cm dilation of the ascending and transverse colon with mucosal thickening. Stool samples for analysis are obtained.
In addition to IV fluids, which of the following is the most appropriate next step in management of this patient? (Multiple Choice)
5.0/5 (79)
(79) A 64-year-old man with a history of benign prostate hyperplasia comes to the office with 2 days of dysuria, increased urinary frequency, and suprapubic discomfort. The patient had similar symptoms 3 months ago and was treated with antibiotics. This resolved his urinary symptoms, but he developed Clostridium difficile colitis, which necessitated oral vancomycin therapy. The patient currently has no gastrointestinal symptoms. His other medical problems include hypertension and hyperlipidemia.
Temperature is 37.6 C (99.8 F), blood pressure is 124/72 mm Hg, and pulse is 86/min. The abdomen is soft, nondistended, and nontender with normal bowel sounds. There is no costovertebral angle tenderness. The prostate is moderately enlarged, smooth, and nontender.
Urine dipstick is positive for leukocyte esterase and nitrite. His previous urine culture had grown Escherichia coli, which was sensitive to all tested antibiotics.
Which of the following is the most appropriate initial antimicrobial therapy for this patient given his history of C difficile colitis?
(Multiple Choice)
4.9/5 (84)
(84) A 28-year-old woman recently completed her first marathon in 4 hours and 20 minutes. At the finish line, she complains of nausea. Soon thereafter, she starts having a headache and begins to vomit. She is taken to a nearby emergency department. She denies any past medical history.
Her temperature is 37.2 C (99 F), blood pressure is 125/72 mm Hg, and pulse is 84/min. Her mucous membranes appear moist. She is disoriented to time. She experiences a generalized tonic-clonic seizure soon after arrival.
Which of the following is the most likely diagnosis?
(Multiple Choice)
4.9/5 (70)
(70) A 54-year-old man with a history of seizure disorder is brought to the emergency department with progressive lethargy over the last 2 days. He has not had any headache, fever, or flu-like symptoms. He had a severe allergic reaction to levetiracetam in the past and failed phenytoin therapy. He is currently maintained on valproic acid. His last generalized tonic-clonic seizure was 1 week ago and his neurologist doubled the dose of his valproic acid at that time. The patient's past medical history is also significant for type 2 diabetes mellitus, hypertension, and hyperlipidemia. Additional medications include metformin, lisinopril, and atorvastatin.
The patient's temperature is 36.7 C (98 F), blood pressure is 140/90 mm Hg, pulse is 70/min, and respirations are 12/min. Pulse oximetry shows 96% on room air. His BMI is 29 kg/m2. On examination he appears lethargic, but is arousable, oriented to person and place, and follows simple commands.
Laboratory values are as follows:
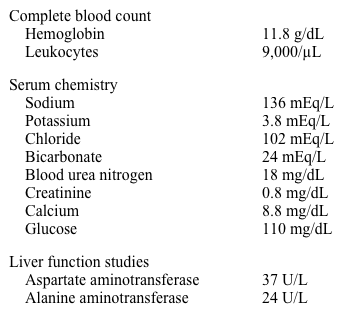 Urinalysis and urine drug screen are normal. Chest x-ray and non-contrast head CT are normal.
Which of the following is the best next step in management of this patient?
Urinalysis and urine drug screen are normal. Chest x-ray and non-contrast head CT are normal.
Which of the following is the best next step in management of this patient? (Multiple Choice)
4.7/5 (95)
(95) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)