



 Chat with AI
Exam 2: In-patient Facilities

Exam 1: Emergency Department218 Questions
Exam 2: In-patient Facilities128 Questions
Exam 3: Office/Health Center900 Questions
Select questions type


A 55-year-old woman was hospitalized 2 days ago for initiation of chemotherapy. The patient was recently found to have a leukocyte count of 117,000/mm3, and a bone marrow biopsy confirmed the diagnosis of acute myeloid leukemia. She has been receiving combination chemotherapy for the past 2 days and has had nausea and several episodes of vomiting. The patient has also been receiving normal saline infusion at 100 mL/hr, rasburicase, and as-needed ondansetron since admission. She has no other medical problems and does not use tobacco, alcohol, or illicit drugs.
Blood pressure is 140/90 mm Hg, pulse is 100/min, and respirations are 18/min. The patient has conjunctival pallor and scattered petechiae. Urine output is approximately 50 mL/hr.
Laboratory results are as follows:
 Which of the following is the most appropriate course of action?
Free
(Multiple Choice)
4.7/5  (84)
(84) Correct Answer: Verified
C
A 72-year-old veteran is admitted to the hospital due to worsening abdominal pain and distension for the past 4 weeks. He recently moved back to his home town to be close to his family. The patient was admitted to the hospital approximately 6 months ago with leg swelling and "fluid in his belly," and a large-volume paracentesis was performed for symptomatic relief.
The patient has a history of hypertension, hyperlipidemia, atrial fibrillation, myocardial infarction, and coronary artery bypass grafting 5 years ago. He also has a history of Hodgkin lymphoma treated with chemotherapy and radiation therapy 20 years ago. He quit smoking 30 years ago but drinks 1 or 2 glasses of wine almost every day and hard liquor occasionally. Medications include aspirin, atenolol, pravastatin, valsartan, warfarin, and over-the-counter vitamin supplements.
The patient's temperature is 37.2 C (99 F), blood pressure is 110/60 mm Hg, pulse is 88/min, and respirations are 22/min. Pulse oximetry is 92% on room air. Two spider angiomata are seen on the upper chest. Jugular venous pressure is elevated at 16 cm H2O. The lungs are clear to auscultation. Cardiac examination reveals irregular heart sounds with no significant murmur or rub. His abdomen is soft with ascites on palpation. There is 2+ pitting lower-extremity edema bilaterally up to the mid-thighs.
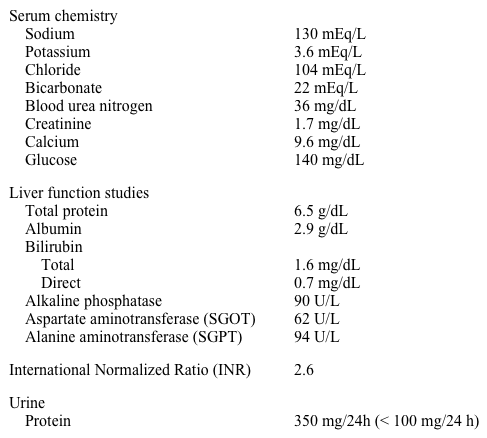
Laboratory results are as follows:
 ECG shows atrial fibrillation and low-voltage QRS complexes in the precordial leads.
Which of the following would help most in establishing this patient's diagnosis?
ECG shows atrial fibrillation and low-voltage QRS complexes in the precordial leads.
Which of the following would help most in establishing this patient's diagnosis?Free
(Multiple Choice)
5.0/5 (77)
(77) Correct Answer:Verified
VerifiedB
An 84-year-old man comes to the emergency department due to a week-long history of dizziness, lightheadedness, and shortness of breath. His symptoms occur at any time but are worse with exertion. He has had no chest pain, palpitations, or syncope. Medical history includes hypertension, hypercholesterolemia, and benign prostatic hyperplasia. His medications are aspirin, lisinopril, atorvastatin, and tamsulosin.
Temperature is 36.7 C (98 F), blood pressure is 120/60 mm Hg, pulse is 36/min, and respirations are 16/min. On examination, the patient appears in no acute distress and has no symptoms. Other than a slow pulse rate, physical examination shows no abnormalities.
Initial laboratory studies, including complete metabolic panel, thyroid function tests, and cardiac markers, are within normal limits.
ECG is shown in the exhibit. 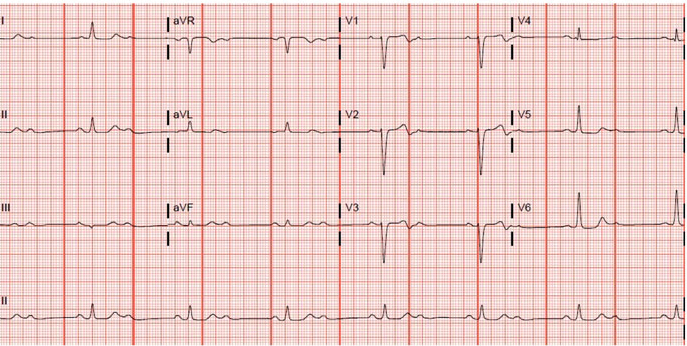 A transthoracic echocardiogram shows normal right and left ventricular size and function with an ejection fraction of 60%, along with mild mitral and tricuspid regurgitation.
Which of the following is the best next step in management of this patient?
A transthoracic echocardiogram shows normal right and left ventricular size and function with an ejection fraction of 60%, along with mild mitral and tricuspid regurgitation.
Which of the following is the best next step in management of this patient?Free
(Multiple Choice)
4.9/5 (70)
(70) Correct Answer:Verified
VerifiedD
A patient dies in the hospital after a rare but fatal adverse event related to a drug-drug interaction. In response, the hospital implements a more comprehensive database of drug-drug interactions in its computerized order entry system. The updated database increases the number of recognized drug interactions from 60,000 to 200,000. A year later, however, the quality improvement team finds that the number of prescribed drugs with high-risk interactions has increased since the database update.
Which of the following is the most likely explanation for this finding?
(Multiple Choice)
4.9/5 (86)
(86) A 64-year-old man with a moderate right-sided pleural effusion seen on initial chest x-ray was admitted for pneumonia. Initial admission testing showed a white blood cell count of 14,800/mm3 with 92% neutrophils. He was started on ceftriaxone and azithromycin, and his symptoms improved over the next few hours. The patient's other medical problems include hypertension, hyperlipidemia, and hypothyroidism. He is a former smoker with a 25-pack-year history.
His blood pressure this morning is 142/90 mm Hg, pulse is 88/min, and respirations are 16/min. Oxygen saturation is 93% on room air. The patient speaks in full sentences, without respiratory distress. Jugular venous pressure is estimated at 5 cm H2O. Lung examination shows decreased breath sounds, decreased tactile fremitus, and dullness to percussion less than halfway up the right chest. A soft second heart sound and 3/6 systolic ejection murmur are heard at the upper right sternal border with radiation to the carotids.
The white blood cell count is 12,200/mm3 with 78% neutrophils. A right lateral decubitus chest x-ray demonstrates a 20-mm free-flowing effusion. Further imaging shows an effusion in the right base without pleural thickening.
Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (72)
(72) A 53-year-old man with end-stage renal disease is admitted to the hospital for complications related to his arteriovenous fistula. Medical history includes type 1 diabetes, diabetic nephropathy, diabetic neuropathy, and diabetic ophthalmopathy. During the daytime nurse's assessments, the patient is consistently hypertensive with systolic blood pressure of 160-170 mm Hg, both pre- and post-dialysis, despite adherence to his antihypertensive regimen. The nurse phones the physician, who orders that the patient be started that evening on hydralazine 25 mg 3 times a day. However, the nurse instead enters an order for hydroxyzine 25 mg 3 times a day. The order for hydroxyzine is processed and approved by the pharmacy. After retrieving the patient's medications, the evening-shift nurse is surprised the patient is taking hydroxyzine as he has not reported any itching. Before administering hydroxyzine, the nurse pages the physician who wrote the order and asks for clarification. The physician recognizes what has happened and corrects the order.
Which of the following is the most appropriate course of action in response to the error?
(Multiple Choice)
4.9/5 (68)
(68) A 65-year-old man is recovering in the post-anesthesia care unit after coronary artery bypass graft procedure for left main artery disease. The patient's operation was uncomplicated and his current condition is stable. Prior to the procedure, the patient requested that no information about his medical condition be released. A close friend of his is designated as the health care power of attorney.
While the patient is recovering from anesthesia, the physician is approached by the patient's wife and daughter, who are very concerned about his condition. They request information about his condition, the results of surgery, and his prognosis.
Which of the following is the most appropriate course of action?
(Multiple Choice)
4.7/5 (72)
(72) An 86-year-old man is admitted to the intensive care unit (ICU) because of multilobar pneumonia. His ICU course was complicated by acute respiratory distress syndrome, which required him to be placed on mechanical ventilation. He has been in the ICU for 3 days and has shown no progress despite broad spectrum antibiotic therapy. He has also developed worsening acute kidney injury, third spacing of fluids, and persistent hypotension despite vasopressor support. His other medical problems include stage 3 chronic kidney disease, congestive heart failure, coronary artery disease, cerebrovascular accident with mild residual right hemiparesis, and advanced prostate cancer.
The patient lives alone at home and has no advance directives on record. He has 2 sons and 3 daughters who have arrived at the ICU and want to speak with the ICU physician. A family meeting is arranged in an adjacent private conference room. After every person is comfortably seated, everyone in the room, in turn, introduces themselves. The family members look apprehensive.
Which of the following is the most appropriate response by the ICU physician?
(Multiple Choice)
4.8/5 (84)
(84) A 43-year-old man with alcoholic pancreatitis is brought to the intensive care unit with acute respiratory failure. His chest x-ray shows bilateral alveolar opacities. His trachea is cannulated and low-tidal volume mechanical ventilation is initiated. Imipenem/cilastatin is continued for necrotizing pancreatitis. Three days later, his oxygen requirement has decreased and his chest x-ray shows improvement.
His temperature is 37.8 C (100 F), blood pressure is 134/72 mm Hg, and pulse is 86/min. The patient's pulse oximetry shows 100% on assist control mode with tidal volumes of 470 mL, respirations of 18/min, fraction of inspired oxygen of 50%, and positive-end expiratory pressure of 5 cm H20. He is not on vasopressor agents. His urine output over the last 6 hours is 50 mL/hr.
Laboratory results are as follows:
 After successful completion of a spontaneous breathing trial, the patient is extubated and placed on nasal cannula oxygen. Five hours later, he complains of shortness of breath. He appears to be in respiratory distress and uses accessory muscles of respiration. His blood pressure is 157/99 mm Hg and his pulse is 122/min. His respiratory rate is 36/min and was 28/min 2 hours earlier. His oxygen saturation is 86% on 50% face mask oxygen. Chest examination shows decreased breath sounds at the right base and bilateral coarse rhonchi.
Which of the following is the most appropriate next step in management?
After successful completion of a spontaneous breathing trial, the patient is extubated and placed on nasal cannula oxygen. Five hours later, he complains of shortness of breath. He appears to be in respiratory distress and uses accessory muscles of respiration. His blood pressure is 157/99 mm Hg and his pulse is 122/min. His respiratory rate is 36/min and was 28/min 2 hours earlier. His oxygen saturation is 86% on 50% face mask oxygen. Chest examination shows decreased breath sounds at the right base and bilateral coarse rhonchi.
Which of the following is the most appropriate next step in management? (Multiple Choice)
4.7/5 (84)
(84) A 60-year-old woman is brought to the hospital for fever, chills, productive cough, and worsening shortness of breath. These symptoms began 3 days ago but have worsened over the last 24 hours. Her other medical problems include type 2 diabetes, hypertension, and psoriatic arthritis. Her medications include methotrexate, metformin, glyburide, lisinopril, and hydrochlorothiazide. She has a 20-pack-year smoking history.
The patient's temperature is 39.3 C (102.7 F), blood pressure is 110/70 mm Hg, pulse is 112/min, and respirations are 22/min. Oxygen saturation is 90% on room air. Examination shows mild respiratory discomfort with crackles over the right lower lung field. The remainder of the examination shows no significant abnormalities.
The patient is admitted to the hospital and started on intravenous antibiotics and normal saline at 150 mL/hr. Over the next 12 hours, she develops worsening shortness of breath and hypotension requiring transfer to the intensive care unit. Her blood pressure is 80/50 mm Hg, respirations are 36/min, and oxygen saturation is 82% on 100% oxygen. She is intubated emergently. Repeat chest x-ray, in the image below, shows diffuse bilateral airspace disease. Laboratory results are as follows: pH 7.38, PaCO2 39 mm Hg, and PaO2 61 mm Hg on FIO2 of 100%.
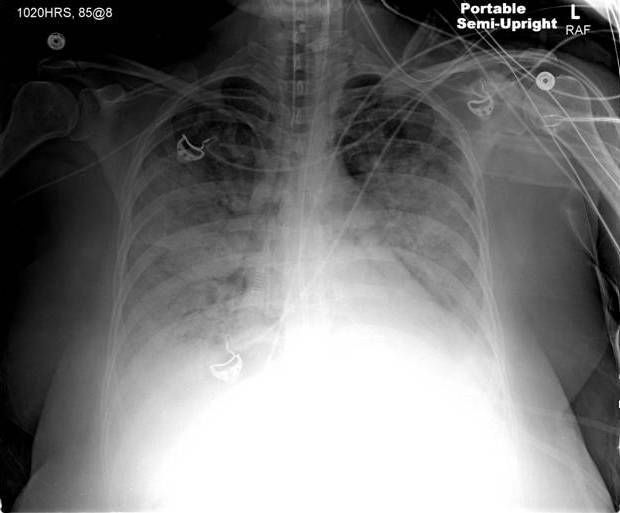 Which of the following is most likely to improve this patient's prognosis?
 (Multiple Choice)
4.9/5 (87)
(87) A 64-year-old woman was found poorly responsive in her apartment and brought to the hospital via ambulance. She has recently become more withdrawn and no longer participates in events at her local senior center during the past few weeks. Her medical history includes severe degenerative arthritis of her hips and knees, type 2 diabetes mellitus, hyperlipidemia, and hypertension. Her medications include aspirin, atenolol, lovastatin, metformin, and NSAIDs in unknown doses. She has no known drug allergies. She has no history of tobacco or alcohol use.
Examination shows that she is lethargic and complains of poor hearing. She is only oriented to person. Her temperature is 37.3°C (99.1°F), blood pressure is 130/76 mm Hg, pulse is 110/min, and respirations are 24/min. Her pulse oximetry shows 94% on room air. Her neck is supple. Examinations of the heart and lungs show no abnormalities. Abdominal examination reveals no tenderness. She has 2+ pulses, with warm extremities. There are no focal neurologic findings.
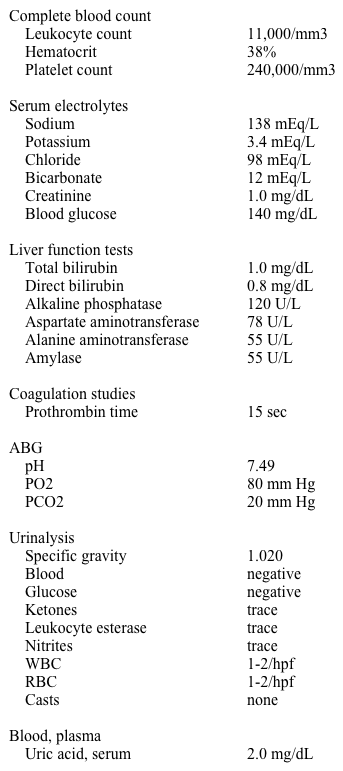
The patient's laboratory studies reveal:
 Chest x-ray shows no abnormalities.
Which of the following interventions would be most beneficial for this patient?
Chest x-ray shows no abnormalities.
Which of the following interventions would be most beneficial for this patient? (Multiple Choice)
4.9/5 (81)
(81) A 70-year-old woman is brought to the hospital for worsening shortness of breath and a cough productive of mucoid sputum. She has no fever or chest pain. The patient has a history of moderate chronic obstructive pulmonary disease (COPD) and has had 2 previous hospitalizations for acute COPD exacerbation over the past year. Her other medical problems include right nephrectomy for renal cell carcinoma 7 years ago, hypertension, chronic low back pain, and degenerative arthritis. Her current medications include tiotropium, albuterol, amlodipine, hydrochlorothiazide, fentanyl patch, and acetaminophen. She has a 48-pack-year smoking history.
The patient is alert and in moderate respiratory distress. Her temperature is 37 C (98.6 F), blood pressure is 140/90 mm Hg, pulse is 98/min, and respirations are 20/min. Oxygen saturation is 86% on room air and 96% on 3 L oxygen. Her BMI is 28 kg/m2. Cardiopulmonary examination shows decreased breath sounds, wheezes with prolonged expiration, and distant heart sounds. There is no jugular venous distension or peripheral edema.
Chest x-ray shows hyperinflation without infiltrates. The patient is started on systemic corticosteroids, bronchodilators, and antibiotics. Four hours later, she appears mildly lethargic but is able to follow commands and cough up secretions. Respirations are 28/min and oxygen saturation is 96% on 3 L oxygen. Her arterial blood gas shows a pH of 7.20, PaCO2 of 70 mm Hg, and PaO2 of 74 mm Hg.
Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.9/5 (76)
(76) A 54-year-old man comes to the emergency department with pain and swelling of his right leg. He injured his leg 2 days ago while playing soccer and noticed the swelling the next day. His medical history is significant for hypertension and chronic kidney disease. His medications include amlodipine, lisinopril, and clonidine. He has not been hospitalized previously.
Laboratory results are as follows:
 Ultrasound examination shows deep venous thrombosis of the right lower extremity extending to the superficial femoral vein. The patient is hospitalized and started on heparin infusion and oral warfarin.
On the second day of hospitalization, his platelet count is 130,000/mm3 and International Normalized Ratio is 1.1. He reports no additional symptoms and the remainder of his laboratory workup is unremarkable. Leg pain and swelling are decreased.
Which of the following is the best next step in management of this patient?
Ultrasound examination shows deep venous thrombosis of the right lower extremity extending to the superficial femoral vein. The patient is hospitalized and started on heparin infusion and oral warfarin.
On the second day of hospitalization, his platelet count is 130,000/mm3 and International Normalized Ratio is 1.1. He reports no additional symptoms and the remainder of his laboratory workup is unremarkable. Leg pain and swelling are decreased.
Which of the following is the best next step in management of this patient? (Multiple Choice)
4.8/5 (80)
(80) A 55-year-old man with known hepatic cirrhosis due to hepatitis C and alcohol abuse is brought to the emergency department with lethargy. His wife states that the patient has been confused for the past 2 days. He has not had any fevers, recent abdominal pain, or vomiting. He eats a regular diet and has no constipation or diarrhea. He was diagnosed with liver cirrhosis 2 years ago and quit drinking alcohol at that time. One year ago, he underwent upper GI endoscopy and was diagnosed with non-bleeding grade 2 esophageal varices. Since then, he has been maintained on propranolol. In addition, he had a large-volume paracentesis 5 months ago and has been taking spironolactone and furosemide. His wife states that he has been compliant with his medications.
His temperature is 36.7 C (98 F), blood pressure is 99/54 mm Hg, and pulse is 92/min and regular. Oxygen saturation is 97% on room air. Abdominal examination shows a distended but non-tender abdomen. There is shifting dullness and a fluid thrill is present. Rectal examination shows brown stool, which is negative for occult blood. There is 2+ pretibial edema. The patient is oriented to person only and has asterixis.
Laboratory results are as follows:
 Urine toxicology screen is negative. Chest x-ray is unremarkable. Urinalysis is negative for infection. Blood and urine cultures are obtained. CT scan of the head shows mild cerebral atrophy, but no masses or bleeding.
Which of the following is the most appropriate next step in management?
Urine toxicology screen is negative. Chest x-ray is unremarkable. Urinalysis is negative for infection. Blood and urine cultures are obtained. CT scan of the head shows mild cerebral atrophy, but no masses or bleeding.
Which of the following is the most appropriate next step in management? (Multiple Choice)
4.9/5 (79)
(79) A 41-year-old previously healthy man is admitted to the hospital with 3 days of nausea, vomiting, and abdominal pain. He was found to have acute necrotizing pancreatitis due to alcohol use. His hospital course was complicated by hypotension requiring 8 L of intravenous fluids. He subsequently developed bilateral infiltrates and refractory hypoxemia requiring intubation and mechanical ventilation. While in the intensive care unit, he develops low-grade fevers and worsening hypoxemia requiring 100% FiO2 and positive end-expiratory pressure of 12. Cultures are obtained and antibiotic coverage is broadened. His blood and urine cultures show no growth 48 hours later. However, sputum culture grows Candida species.
Laboratory results are as follows:
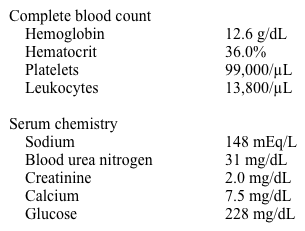 A repeat chest x-ray shows persistent bilateral infiltrates and new small bilateral pleural effusions.
Which of the following is the most appropriate next step in managing this patient's positive sputum culture?
A repeat chest x-ray shows persistent bilateral infiltrates and new small bilateral pleural effusions.
Which of the following is the most appropriate next step in managing this patient's positive sputum culture? (Multiple Choice)
4.9/5 (93)
(93) A 38-year-old man admitted with severe, acute alcoholic pancreatitis is evaluated in the intensive care unit for persistent fever. The patient is intubated and on mechanical ventilation. He is receiving nasojejunal tube feeding and intravenous crystalloids.
His temperature is 38.3 C (101 F), blood pressure is 90/60 mm Hg, pulse is 104/min, and respirations are 18/min. Respiratory secretions are scant. Breath sounds are decreased at the lung bases. There is epigastric tenderness on deep palpation and mild abdominal distension. 2+ presacral edema is present. A peripherally inserted central catheter in the right arm shows no surrounding skin redness or discharge.
Laboratory results are as follows:
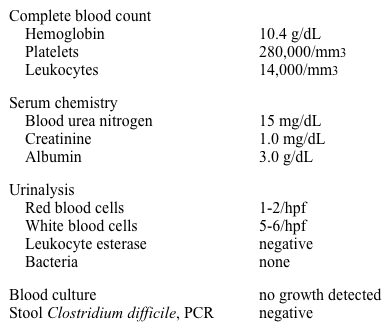 Chest x-ray reveals bilateral, small pleural effusions. A contrast-enhanced abdominal CT scan reveals 40% pancreatic necrosis and moderate-size fluid collections in the retroperitoneum around the pancreas. The gallbladder has some sludge, the common bile duct measures 5 mm, and no intrahepatic ductal dilation is seen.
Which of the following is the best next step in managing this patient?
Chest x-ray reveals bilateral, small pleural effusions. A contrast-enhanced abdominal CT scan reveals 40% pancreatic necrosis and moderate-size fluid collections in the retroperitoneum around the pancreas. The gallbladder has some sludge, the common bile duct measures 5 mm, and no intrahepatic ductal dilation is seen.
Which of the following is the best next step in managing this patient? (Multiple Choice)
4.8/5 (77)
(77) A 53-year-old woman is hospitalized with acute inferior ST elevation myocardial infarction. She did not undergo a revascularization procedure due to delayed presentation. The patient has a distant history of deep vein thrombosis and is a factor V Leiden carrier. Echocardiogram shows inferior and inferolateral wall akinesis with left ventricular ejection fraction of 45%. Before discharge on day 3, she develops severe shortness of breath and is evaluated urgently.
Blood pressure is 84/60 mm Hg and pulse is 112/min and regular. The apical impulse is hyperdynamic and there is a faint early systolic murmur heard at the apex. There is no precordial thrill. Bilateral crackles are heard on lung auscultation. The extremities are cold and clammy.
ECG shows sinus tachycardia with Q waves in leads II, III, and aVF.
Which of the following is the most likely diagnosis?
(Multiple Choice)
4.9/5 (82)
(82) A 45-year-old hospitalized man is evaluated for worsening kidney function. The patient has a history of alcoholic cirrhosis and was admitted 3 days ago due to progressive abdominal pain and lethargy. Evaluation revealed asterixis and 300/mm3 of neutrophils in the ascitic fluid. He was started on intravenous cefotaxime and oral lactulose for treatment of spontaneous bacterial peritonitis complicated by hepatic encephalopathy. The patient's symptoms have gradually improved with treatment, but his serum creatinine has increased from 0.9 mg/dL on admission to 2.1 mg/dL now. Urine output during the last 24 hours is 450 mL. He has no history of kidney disease or other medical problems. The patient's home diuretic therapy with furosemide and spironolactone had been initially continued during the hospitalization but was stopped yesterday. He stopped drinking alcohol after being diagnosed with cirrhosis 3 years ago and does not use tobacco.
Temperature is 37.2 C (99 F), blood pressure is 110/70 mm Hg, pulse is 96/min, and respirations are 18/min. The patient is somnolent but easily roused. There is mild scleral icterus, and jugular venous pressure is normal. Lungs are clear to auscultation. The abdomen is soft, moderately distended with ascites, and nontender. Bowel sounds are normoactive. There is 2+ bilateral lower-extremity pitting edema.
Laboratory results are as follows:
Renal ultrasonography shows no hydronephrosis.
Which of the following is the most appropriate next step in management of this patient's renal dysfunction?
(Multiple Choice)
4.8/5 (92)
(92) A 68-year-old woman is admitted to the hospital due to shortness of breath and lower extremity swelling for the past 6 weeks. Her medical history includes hypertension, hypothyroidism, type 2 diabetes mellitus, hyperlipidemia, obstructive sleep apnea, and stage II chronic kidney disease. The patient had a transient ischemic attack with right carotid endarterectomy 8 years ago. Home medications include aspirin, levothyroxine, hydrochlorothiazide, lisinopril, atorvastatin, and glipizide. She has never used tobacco.
Temperature is 37.2 C (99 F), blood pressure is 122/80 mm Hg, pulse is 84/min, and respirations are 22/min. Pulse oximetry is 92% on 3 L oxygen via nasal cannula. Jugular venous pressure is elevated at 12 cm H2O. Lung examination reveals decreased breath sounds at the bases with bibasilar rales up to the lower one-third of the chest. Cardiac examination reveals a normal S1 and S2 and an audible S4 over the cardiac apex. There is a 1/6 holosystolic murmur heard over the cardiac apex. The patient has 3+ lower extremity edema up to her knees. The remainder of her physical examination is within normal limits.
Laboratory results are as follows:
 ECG results are shown in the exhibit.
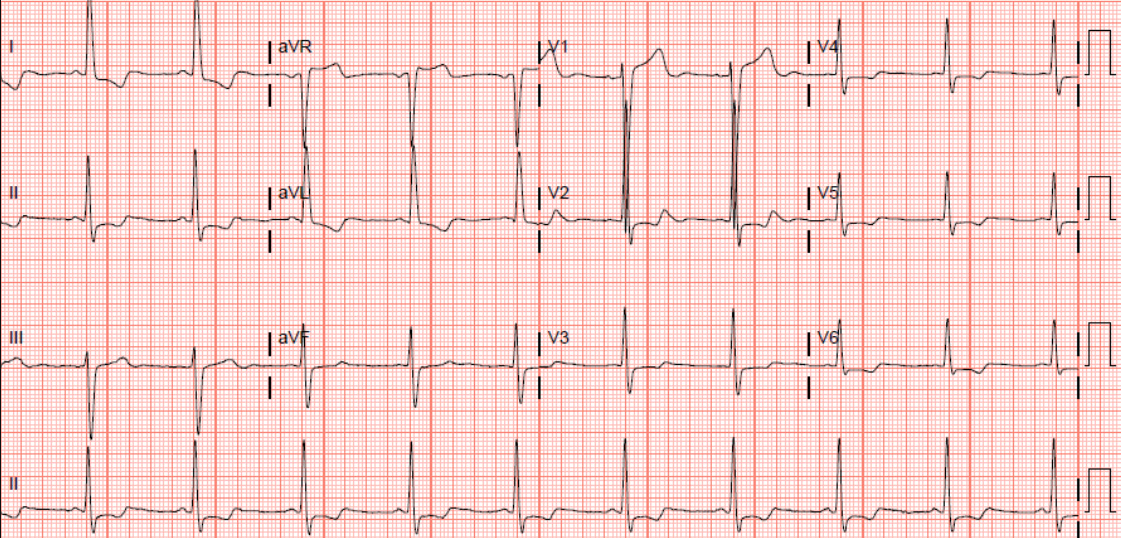 Initial chest x-ray reveals cardiomegaly and bilateral pulmonary vascular congestion, along with small, bilateral pleural effusions.
A transthoracic echocardiogram shows normal left ventricular size and a left ventricular ejection fraction of 65%. Moderate, concentric left ventricular hypertrophy is present. The left atrium is moderately dilated. A central jet of mild mitral regurgitation is present. Pulmonary artery systolic pressure is estimated at 45 mm Hg.
Which of the following is the most appropriate next step in management of this patient?
ECG results are shown in the exhibit.
Initial chest x-ray reveals cardiomegaly and bilateral pulmonary vascular congestion, along with small, bilateral pleural effusions.
A transthoracic echocardiogram shows normal left ventricular size and a left ventricular ejection fraction of 65%. Moderate, concentric left ventricular hypertrophy is present. The left atrium is moderately dilated. A central jet of mild mitral regurgitation is present. Pulmonary artery systolic pressure is estimated at 45 mm Hg.
Which of the following is the most appropriate next step in management of this patient? (Multiple Choice)
4.9/5 (77)
(77) A 79-year-old man on mechanical ventilation is evaluated following a spontaneous breathing trial. The patient has a history of chronic obstructive pulmonary disease with an extensive prior smoking history. He was admitted 3 days ago due to fever, shortness of breath, wheezing, and productive cough. The patient's respiratory distress failed to improve after a trial of noninvasive ventilation, and endotracheal intubation was performed. Treatment with inhaled bronchodilators, systemic glucocorticoids, and empiric antibiotics was begun. His sputum cultures grew methicillin-resistant Staphylococcus aureus and the antibiotics were adjusted. His suctioning requirement decreased significantly to 2 or 3 times daily.
The patient undergoes a spontaneous breathing trial. After 2 hours of continuous positive airway pressure of 5 cm H2O, his temperature is 37.2 C (99 F), blood pressure is 153/76 mm Hg, pulse is 98/min, and respirations are 18/min. His average tidal volume is 300 mL. Pulse oximetry is 98% on 40% FiO2. Examination shows left-sided crackles and normal S1 and S2. The patient is able to follow commands and lift his head off the bed.
Laboratory results are as follows:
 Chest-x ray reveals an infiltrate at the left base that is unchanged from a prior x-ray.
Which of the following is the most appropriate next step in management of this patient?
Chest-x ray reveals an infiltrate at the left base that is unchanged from a prior x-ray.
Which of the following is the most appropriate next step in management of this patient? (Multiple Choice)
4.8/5 (89)
(89) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)