



 Chat with AI
Exam 2: In-patient Facilities

Exam 1: Emergency Department218 Questions
Exam 2: In-patient Facilities128 Questions
Exam 3: Office/Health Center900 Questions
Select questions type


A 65-year-old man is admitted to the hospital for increasing shortness of breath and edema. Over the last 10 days, he has experienced progressively worsening shortness of breath occurring with modest exertion and a cough productive of a small amount of purulent sputum. He denies paroxysmal nocturnal dyspnea, orthopnea, fever, chills, and chest pain. He also reports a 4.5-kg (10-lb) weight gain. His medical problems include chronic obstructive pulmonary disease (COPD), congestive heart failure due to coronary artery disease, type 2 diabetes mellitus, hypertension, degenerative joint disease, and obesity.
His blood pressure is 138/84 mm Hg, pulse is 96/min and regular, and respirations are 20/min. Pulse oximetry reveals an oxygen saturation of 94% while using nasal prongs at 2 liters of oxygen/min. His jugular venous pressure is 10-12 cm H2O. Lung examination reveals diffusely decreased breath sounds with prolongation of the expiratory phase. There are no rales. Cardiac examination reveals an increased P2 and a grade 2/6 systolic murmur along the left sternal border. Abdominal examination is normal. There is 2-3+ bilateral pedal edema.
He is treated with intravenous furosemide and azithromycin, and his symptoms are gradually improving.
Laboratory results obtained 48 hours after admission are as follows:
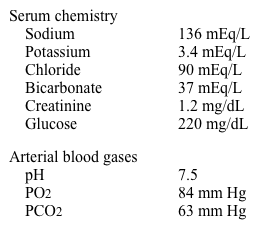 Which of the following is most likely the cause of his acid-base disorder?
 (Multiple Choice)
4.8/5  (74)
(74) A 46-year-old man comes to the emergency department complaining of severe headache for the last 3 hours. He took ibuprofen without much relief. He suffers from tension headaches but says that this headache is nothing like those. He feels nauseated and wants to move to a quiet, dark room.
His temperature is 36.5 C (97.7 F), blood pressure is 160/90 mm Hg, and pulse is 108/min. Examination shows pain and mild stiffness with neck flexion. There are no cranial nerve deficits or muscle weakness.
A noncontrast head computed tomography scan reveals subarachnoid hemorrhage with no evidence of hydrocephalus. The patient is admitted to the intensive care unit. A few hours later, he complains of increasing headache and has 2 episodes of vomiting. Soon after, he develops cardiac arrest with pulseless electrical activity.
Which of the following interventions would have been the most effective in preventing this outcome?
(Multiple Choice)
4.9/5 (69)
(69) A 36-year-old woman comes to the emergency department because of worsening shortness of breath and cough for 4 days. Her medical problems include rheumatoid arthritis, interstitial lung disease on home oxygen, and pulmonary hypertension. Her trachea is cannulated because of respiratory distress and central venous access is obtained.
In the intensive care unit, her temperature is 37.2 C (99 F), blood pressure is 99/67 mm Hg, and pulse is 120 /min. The patient's pulse oximetry shows 100% on assist control mode with tidal volumes of 300 mL, respiratory rate of 20/min, fraction of inspired oxygen (FiO2) of 100%, and positive end-expiratory pressure (PEEP) of 5 cm H2O. Examination reveals right-sided crackles and decreased breath sounds on the left. Heart sounds are regular with a loud second heart sound. The abdomen is soft and non-tender. Examination shows no peripheral edema.
Laboratory values are as follows:
 A chest radiograph is performed.
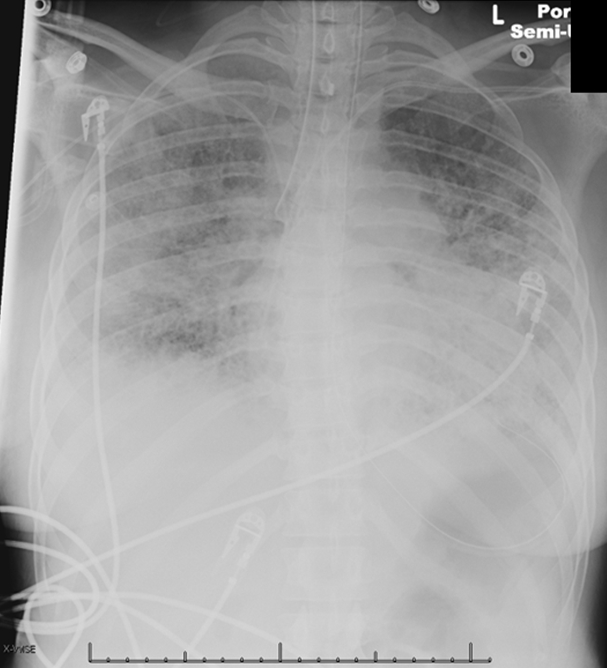 Which of the following is the most appropriate next step in management?
A chest radiograph is performed.
Which of the following is the most appropriate next step in management? (Multiple Choice)
4.7/5 (77)
(77) There has been a continuous increase in the number of urinary tract infections among residents of a local long-term care facility over the last 5 years. Due to comorbidities, many residents are incontinent of urine and have indwelling urinary catheters.
Which of the following measures will most likely decrease the frequency of urinary tract infections in these patients?
(Multiple Choice)
4.8/5 (89)
(89) A 26-year-old primigravid woman at 36 weeks gestation is admitted to the hospital because of vaginal bleeding and lower abdominal pain. Her other medical problems include selective IgA deficiency, allergic rhinitis, and recurrent sinusitis. Her anti-IgA antibody screening is positive.
Evaluation reveals placental abruption. She is scheduled to undergo urgent cesarean section and requires blood transfusion.
Which of the following should be administered to this patient?
(Multiple Choice)
4.7/5 (78)
(78) A 43-year-old woman is seen in the hospital following a laparoscopic cholecystectomy. The patient had no significant operative complications but was observed overnight due to nausea during recovery from anesthesia. The nausea has resolved and she is tolerating a regular diet. The patient reports continuous moderate incisional pain with occasional spikes of increased pain with movement. Medical history is unremarkable and she takes no chronic medications. She does not use tobacco, alcohol, or illicit drugs.
Vital signs are normal. Examination shows intact abdominal incisions with normal bowel sounds and no significant abdominal tenderness. The remainder of the examination is normal.
Which of the following is the most appropriate prescription for home pain control for this patient?
(Multiple Choice)
4.8/5 (81)
(81) A 68-year-old woman is evaluated in the surgical intensive care unit for hypertension. She was admitted to the ICU two days ago after undergoing extensive resection and anastomosis for a small bowel infarction. Her abdomen has not been closed due to the possibility of further surgery if additional infarction ensues. She is currently intubated and supported by mechanical ventilation. She is being treated with broad spectrum intravenous antibiotics, fentanyl, and midazolam. She has a history of persistent atrial fibrillation and has been noncompliant with anticoagulation. Her other medical problems include hypertension, congestive heart failure, coronary artery disease, chronic low back pain secondary to osteoporotic spine fractures, and hyperlipidemia.
She appears diaphoretic and mildly agitated. Her temperature is 38.3 C (101 F), blood pressure is 200/120 mm Hg, pulse is 120/min, respiratory rate is 35/min, and oxygen saturation is 98%. The ventilator settings are as follows:
 Arterial blood gas analysis shows a pH of 7.49, a PaCO2 of 28 mm Hg, and a PaO2 of 90 mm Hg. Serum creatinine is 1.4 mg/dL and lactate level is 1.2 mg/dL.
Which of the following is the most appropriate next step in management?
Arterial blood gas analysis shows a pH of 7.49, a PaCO2 of 28 mm Hg, and a PaO2 of 90 mm Hg. Serum creatinine is 1.4 mg/dL and lactate level is 1.2 mg/dL.
Which of the following is the most appropriate next step in management? (Multiple Choice)
4.7/5 (81)
(81) An 86-year-old nursing home resident is hospitalized because of fever for the past two days. His medical problems include cerebrovascular accident, decubitus ulcer, benign prostatic hyperplasia, urinary incontinence, hypertension, and type 2 diabetes mellitus.
Upon admission, his temperature is 38.9 C (102 F), blood pressure is 88/54 mm Hg, pulse is 98/min, and respirations are 18/min. After 2 liters of intravenous normal saline, his blood pressure is 109/68 mm Hg and his pulse is 82/min. Examination reveals decreased breath sounds and crackles at the right lung base. He has a chronic Foley catheter in place that drains clear urine. His decubitus ulcer looks clean. He denies any urinary discomfort and there is no suprapubic or costovertebral tenderness. His leukocyte count is 15,400 cells/µL and his serum creatinine level is 0.9 mg/dL. A chest x-ray reveals a right lower lobe infiltrate.
The patient is started on intravenous antibiotics. Over the subsequent 48 hours, he improves and becomes afebrile. A urine culture from admission grows Candida albicans. Blood cultures show no growth.
Which of the following is the best next step in management?
(Multiple Choice)
4.7/5 (96)
(96) A 66-year-old woman is hospitalized for the worst headache of her life. CT scan of the head without contrast shows diffuse subarachnoid hemorrhage with intraventricular extension and hydrocephalus. Because of the patient's deteriorating mental status and agitation, her trachea is cannulated and a central venous catheter is placed.
Which of the following is the most effective strategy to decrease this patient's risk for developing catheter-related infection?
(Multiple Choice)
4.8/5 (93)
(93) A 66-year-old woman is admitted to the hospital with a 3-week history of worsening shortness of breath and palpitations. She has had severe dyspnea with minimal exertion. The patient has also experienced bilateral leg swelling and insomnia but no dizziness or chest pain. Medical history is notable for hypertension, type 2 diabetes mellitus, atrial fibrillation, heart failure, and hypercholesterolemia. Current medications are warfarin, amiodarone, metoprolol, metformin, atorvastatin, and lisinopril. Family history is unremarkable. The patient does not use tobacco, alcohol, or illicit drugs.
Blood pressure is 120/66 mm Hg and pulse is 120/min and irregular. On physical examination, there is mild lid lag but no proptosis. Visual field examination is normal. Neck examination shows elevated jugular venous pressure. The thyroid is irregular, enlarged, and nontender, and the left thyroid lobe is larger than the right. Crackles are heard in both lung bases. There is trace pedal edema and no pretibial myxedema.
Laboratory results are as follows:
 Radioactive iodine uptake at 24 hours shows patchy uptake at 5% (normal: 10%-30%).
Which of the following is the most likely cause of the thyroid dysfunction in this patient?
Radioactive iodine uptake at 24 hours shows patchy uptake at 5% (normal: 10%-30%).
Which of the following is the most likely cause of the thyroid dysfunction in this patient? (Multiple Choice)
4.8/5 (79)
(79) A 46-year-old woman is seen in the emergency department for severe headache accompanied by nausea since she awoke this morning. She was diagnosed with hypertension 7 years ago and took medications for 2 years. The patient stopped the medications and did not follow up with doctors as she felt fine. She has a history of remote but not active intravenous drug use. She is a current smoker with a 25-pack-year history.
Her temperature is 37.8° C (100.1° F), blood pressure is 176/105 mm Hg, and pulse is 100/min. She appears lethargic with mild neck stiffness. Cardiac auscultation shows an apical 2/6 holosystolic murmur. Lungs are clear to auscultation bilaterally. Deep abdominal palpation shows bilateral firm flank masses. There is no peripheral edema or skin rash. There is no focal muscle weakness or cranial nerve deficit.
ECG shows sinus tachycardia with left ventricular hypertrophy and secondary ST-segment and T-wave changes.
Laboratory results are as follows:
 Which of the following is the most likely cause of this patient's headache?
 (Multiple Choice)
4.7/5 (73)
(73) An 88-year-old nursing home resident is admitted to the hospital for fever and confusion. She was recently discharged after an episode of aspiration pneumonia, which entailed a prolonged and complicated hospitalization course. She has lost 20 lbs (9 kg) over the past 6 months. She suffers from dementia and requires constant assistance with her activities of daily living. She frequently does not recognize her caregivers and is regularly found to be incontinent of urine and stool. Her other medical problems include hypertension, atrial fibrillation, type 2 diabetes mellitus, and mild residual left-sided hemiparesis from a previous ischemic stroke.
Her temperature is 38.3 C (101 F), blood pressure is 144/87 mm Hg, pulse is 92/min, and oxygen saturation is 92% on 2 L/min O2 via nasal canula. Her BMI is 18.5 kg/m2. Examination reveals dry mucous membranes. Coarse rhonchi are heard over the right lower lung. She has a stage 3 coccygeal pressure ulcer.
Blood cultures are sent and she is started on broad-spectrum antibiotics. Her daughter inquires about nutritional support because her mother is losing weight and "needs to get stronger to fight this infection."
Which of the following statements would best address the daughter's concerns?
(Multiple Choice)
4.9/5 (82)
(82) A 67-year-old man is hospitalized with cough, shortness of breath, orthopnea, and ankle swelling. He is treated with intravenous diuretics. He was diagnosed with non-ST segment elevation myocardial infarction 3 weeks ago and had a right coronary artery stent placed. On discharge, the patient's left ventricular ejection fraction was 40%. On the sixth day of his current hospitalization, he feels better but still complains of some shortness of breath. His platelet count is 62,000/µL, down from 210,000/µL on admission.
The other laboratory results are as follows:
 Subcutaneous injections of unfractionated heparin for deep venous thrombosis prophylaxis are stopped and the nurses are instructed not to use heparin flushes. Appropriate laboratory workup is sent.
Which of the following should be used for preventing thromboembolism in this patient?
Subcutaneous injections of unfractionated heparin for deep venous thrombosis prophylaxis are stopped and the nurses are instructed not to use heparin flushes. Appropriate laboratory workup is sent.
Which of the following should be used for preventing thromboembolism in this patient? (Multiple Choice)
4.9/5 (82)
(82) A 75-year-old man with ischemic cardiomyopathy is hospitalized with acute decompensated heart failure. His left ventricular ejection fraction is 10% and he has not been compliant with his medications.
His blood pressure is 134/78 mm Hg, pulse is 68/min, respirations are 20/min, and oxygen saturation is 96% on 2-liters O2 by nasal cannula. His BMI is 24 kg/m2.
The patient's symptoms improve with intravenous furosemide therapy and he appears comfortable at rest on supplemental oxygen. During the night, the nurse notes frequent episodes of desaturation accompanied by short runs of nonsustained ventricular tachycardia.
Which of the following is the most likely diagnosis?
(Multiple Choice)
4.9/5 (84)
(84) A 61-year-old man comes to the emergency department due to 20 minutes of slurred speech while eating lunch at work. Two months ago, he had an episode of blurry vision in his right eye. The patient has a history of hyperlipidemia and hypertension and takes amlodipine and hydrochlorothiazide. He is an active smoker with a 35-pack-year history.
Blood pressure is 155/90 mm Hg and pulse is 78/min. Oxygen saturation is 94% on room air. BMI is 31 kg/m2. The lungs are clear to auscultation. The spleen tip is palpable on inspiration. There is trace bilateral pedal edema.
Laboratory results are as follows:
 Which of the following is the most likely additional finding in this patient?
 (Multiple Choice)
4.9/5 (71)
(71) A 22-year-old woman is evaluated for fever, diarrhea, and skin rash. The patient was admitted 10 days ago after a motor vehicle collision resulted in a splenic laceration. She underwent an emergency splenectomy and received multiple units of emergency-release type O-negative blood perioperatively. Postoperatively, she received the pneumococcal vaccine but not the meningococcal vaccine as it had been given 2 years ago. The patient had been recovering well with no issues until 2 days ago when she developed a nonpruritic skin rash on her trunk that progressed to involve the face and extremities. She has also had fevers as high as 38.8 C (102 F) and profuse, watery diarrhea. The patient has a history of Hodgkin disease and received her most recent dose of chemotherapy 3 weeks ago.
New findings on the physical examination compared to 2 days ago include a diffuse maculopapular skin rash sparing the palms and soles and mild, nontender hepatomegaly.
Laboratory test results are as follows:
 Stool Clostridium difficile testing is negative.
Which of the following would have been most effective in preventing this patient's current condition?
Stool Clostridium difficile testing is negative.
Which of the following would have been most effective in preventing this patient's current condition? (Multiple Choice)
4.9/5 (81)
(81) A 48-year-old man comes to the emergency department due to fever and cellulitis of the distal right lower extremity. He was initially seen in a clinic 2 days earlier and treated with oral clindamycin, but he subsequently developed increasing erythema. Medical history is notable for nondeforming rheumatoid arthritis treated with hydroxychloroquine and a similar episode of cellulitis 2 years ago that resolved with a course of cefazolin. The patient is admitted to the hospital and treated with cefazolin and leg elevation. His fever rapidly resolves and the area of erythema recedes. However, 3 days after admission, serum creatinine increases from 1.2 to 1.9 mg/dL.
Urinalysis results are as follows:
 Urine stain for eosinophils is negative.
Which of the following is the most likely diagnosis in this patient?
Urine stain for eosinophils is negative.
Which of the following is the most likely diagnosis in this patient? (Multiple Choice)
4.9/5 (87)
(87) A 65-year-old woman with a history of chronic obstructive pulmonary disease is brought to the intensive care unit after being intubated in the emergency department for severe respiratory distress. Intubation was difficult to perform and required 2 attempts. She has had 3 exacerbations in the past 2 years that required hospitalizations, but has never been intubated before. Her other medical problems include rheumatoid arthritis, hypertension, moderate obesity, and a transient ischemic episode 3 years ago. She has smoked 1 pack of cigarettes per day for the past 40 years.
Examination reveals diffuse, scattered wheezes and decreased aeration throughout the lungs. She is started on high-dose methylprednisolone, bronchodilator inhalers, and antibiotics. She received neuromuscular blockade with pancuronium for one day due to severe agitation and patient-ventilator dyssynchrony. Subsequently, she was continued on a lorazepam drip for sedation for 3 days.
On the fifth day of hospitalization, she has markedly improved breath sounds with occasional wheezes. Weaning attempts with pressure support ventilation on the fifth and sixth days of hospitalization were unsuccessful due to low tidal volumes and tachypnea. She has marked muscle weakness in all her extremities and examination shows decreased muscle tone and absent deep tendon reflexes. Sensory examination is indeterminate. Lab studies show a serum creatine kinase of 980 IU/L and normal hepatic and renal function.
Which of the following is the most likely cause for the failed ventilator weaning in this patient?
(Multiple Choice)
4.8/5 (65)
(65) A 49-year-old man with end-stage renal disease is hospitalized because of fever and malaise for the past 2 days. His other medical problems include hypertension and type 2 diabetes mellitus. His renal failure is attributed to uncontrolled hypertension and progressive diabetic nephropathy. He has had several hemodialysis access failures due to infection and thrombosis issues.
His temperature is 38.9 C (102 F), blood pressure is 124/60 mm Hg, pulse is 88/min, and respirations are 18/min. Examination shows a tunneled hemodialysis catheter in the right chest which was placed four weeks ago. There is no drainage, erythema, or tenderness over the catheter entry or tunnel site. Lungs are clear to auscultation and there are no cardiac murmurs. The remainder of the examination shows no abnormalities.
His chest x-ray shows no infiltrates. Blood cultures are sent and he is started on broad-spectrum antibiotics.
Which of the following positive culture results would necessitate immediate catheter removal?
(Multiple Choice)
4.8/5 (77)
(77) A 42-year-old woman is evaluated for palpitations. She describes them as an occasional "fluttering in the chest" that is sometimes precipitated by emotion. Her lifestyle is sedentary, but she has had no shortness of breath, cough, or lower extremity swelling and no history of bleeding. The patient emigrated from Mexico when she was 6 years old. She is a lifetime nonsmoker and does not drink alcohol.
Blood pressure is 135/85 mm Hg. ECG shows a normal sinus rhythm with a heart rate of 65/min.
Resting transthoracic echocardiogram shows moderate left atrial dilation, mitral stenosis with a valve area of 1.5 cm2, pliable leaflets with minimal calcification, mild mitral regurgitation, normal right ventricle size, and an estimated pulmonary artery systolic pressure of 25 mm Hg. Two episodes of atrial fibrillation lasting 20 minutes each are seen on 24-hour Holter monitoring.
What is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (91)
(91) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)