



 Chat with AI
Exam 2: In-patient Facilities

Exam 1: Emergency Department218 Questions
Exam 2: In-patient Facilities128 Questions
Exam 3: Office/Health Center900 Questions
Select questions type


A 30-year-old woman with ulcerative colitis treated with mesalamine is hospitalized for nausea, abdominal pain, and diarrhea. She has had 8-10 bloody bowel movements every day for the past week with associated tenesmus, anorexia, and a 2-kg (4.4-lb) weight loss. The patient reports no recent travel, antibiotic use, or eating anything unusual. She does not use tobacco, alcohol, or illicit drugs.
Temperature is 37 C (98.6 F), blood pressure is 110/70 mm Hg, pulse is 92/min, and respirations are 16/min. Examination shows a mildly distended abdomen. There is mild diffuse tenderness but no involuntary guarding or rebound tenderness. Bowel sounds are present in all quadrants. Stool is positive for occult blood.
Laboratory results are as follows:
 Abdominal and upright chest radiographs are unremarkable with no free air or severe colonic dilatation. Stool testing for Clostridium difficile is negative and stool cultures are sent.
Which of the following is the most appropriate next step in management of this patient?
Abdominal and upright chest radiographs are unremarkable with no free air or severe colonic dilatation. Stool testing for Clostridium difficile is negative and stool cultures are sent.
Which of the following is the most appropriate next step in management of this patient? (Multiple Choice)
4.7/5  (72)
(72) A 63-year-old man is hospitalized with dyspnea due to right lower lobe pneumonia. On the third day of hospitalization, he develops progressive respiratory failure and bilateral lung infiltrates. His trachea was intubated and mechanical ventilation is initiated.
His blood pressure is 146/80 mm Hg, and pulse is 97/min. The patient's pulse oximetry shows 89% on assist-control mode with tidal volumes of 450 mL, respiratory rate of 30/min, fraction of inspired oxygen of 100%, and positive end-expiratory pressure of 12 cm H2O. Examination shows diffuse crackles all over the lung fields, normal first and second heart sounds, and capillary refill of < 2 seconds. There is trace pre-sacral edema.
Laboratory results are as follows:
 His chest-x ray reveals dense bilateral alveolar opacities. Bedside echocardiogram shows left ventricular ejection fraction of 65%. A central line is placed and the central venous pressure is 10 mm Hg.
Conservative fluid management using diuretic therapy in this patient is most likely to positively affect which of the following?
His chest-x ray reveals dense bilateral alveolar opacities. Bedside echocardiogram shows left ventricular ejection fraction of 65%. A central line is placed and the central venous pressure is 10 mm Hg.
Conservative fluid management using diuretic therapy in this patient is most likely to positively affect which of the following? (Multiple Choice)
4.8/5 (99)
(99) An 80-year-old man is hospitalized because of an acute exacerbation of chronic obstructive pulmonary disease. He is started on high-dose systemic steroids, bronchodilator nebulization, and antibiotics. He initially receives non-invasive positive pressure ventilation for 12 hours. On the third day of hospitalization, his breathing improves but he complains of "fluttering in his chest." He denies chest pain or dizziness. He had similar symptoms in the past that were transient and occurred mostly at night. His other medical problems include type 2 diabetes mellitus, hypertension, hypercholesterolemia, chronic kidney disease, and osteoarthritis.
On examination, he appears comfortable. His temperature is 36.7 C (98 F), blood pressure is 110/60 mm Hg, pulse is 124/min, and respirations are 20/min. The patient's pulse oximetry is 96% on 2 liters of oxygen. His jugular venous pressure is normal. Lung auscultation reveals mild bilateral wheezing and prolonged expiration. He has no hepatomegaly, peripheral edema, or thyromegaly.
/_
/_Laboratory results are as follows:
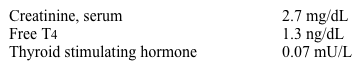 ECG reveals atrial fibrillation with rapid ventricular response.
Which of the following would be the most helpful in diagnosing this patient's thyroid disorder?
ECG reveals atrial fibrillation with rapid ventricular response.
Which of the following would be the most helpful in diagnosing this patient's thyroid disorder? (Multiple Choice)
4.8/5 (88)
(88) A 48-year-old woman is admitted to the hospital from the emergency department due to fatigue and confusion. She had been well until 2 months prior to admission when she began to feel tired and lost her appetite. Over the next several weeks, the patient experienced nausea, constipation, and weight loss. Recently, she has also had difficulty concentrating at work, and on the day of admission her daughter visited her at home and found her confused. The patient has had no fever, chills, or depression. Medical history is notable for rheumatoid arthritis, which was previously treated with methotrexate but has been quiescent in the absence of therapy for several years. She is an ex-smoker with a 30-pack-year smoking history. Her mother died of lung cancer at age 50.
Blood pressure is 138/78 mm Hg and pulse is 89/min. Mucous membranes appear dry. There is no lymph node enlargement. Breast examination is unremarkable. The lungs are clear to auscultation. The spleen is not palpable. There are no skin rashes.
Laboratory results are as follows:
 Serum calcium was normal 6 months ago. Which of the following is the most likely cause of this patient's hypercalcemia?
 (Multiple Choice)
4.9/5 (87)
(87) A physician smells alcohol on the breath of one of her physician colleagues. The concerned physician confronts her colleague, but he adamantly denies consuming any alcohol. Nonetheless, the concerned physician insists that the colleague go home for the day. The colleague initially protests saying, "I just had a couple of beers last night!" However, he eventually leaves for the day voluntarily. The concerned physician plans to discuss the issue further with her colleague the next day and encourage him to get help.
The colleague comes to work the next day again smelling of alcohol. Which of the following is the most appropriate course of action?
(Multiple Choice)
4.7/5 (86)
(86) A 74-year-old man is brought back to the hospital due to fever, shortness of breath, and cough productive of copious yellow sputum. He was hospitalized 2 weeks ago after an ischemic stroke that caused right-sided weakness, dysarthria, and dysphagia necessitating feeding tube placement. The patient has chronic obstructive pulmonary disease, hypertension, and type 2 diabetes mellitus.
The patient's temperature is 39.2 C (102.6 F), blood pressure is 140/90 mm Hg, pulse is 106/min, and respirations are 30/min. Oxygen saturation is 86% on room air and 92% on 2 L oxygen via nasal cannula. He is alert and can follow commands. Physical examination shows respiratory accessory muscle use with suprasternal and subcostal retractions, upper airway gurgling sounds, and drooling. Diffuse wheezes with prolonged expiration and crackles over the right lower lung are heard on chest auscultation.
Laboratory studies show a white blood cell count of 17,500/µL. Chest x-ray reveals right middle lobe air space opacities. Arterial blood gas on 2 L oxygen shows pH of 7.23, PaCO2 of 64 mm Hg, and PaO2 of 65 mm Hg.
Broad-spectrum antibiotics, systemic corticosteroids, and nebulized bronchodilators are administered.
Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
5.0/5 (83)
(83) A 52-year-old woman is undergoing screening colonoscopy and receives midazolam for sedation. Shortly after the procedure is started, she becomes tachycardic and hypertensive. Blood pressure is 240/140 mm Hg, pulse is 180/min, and respirations are 22/min. Oxygen saturation is 92% on 4 L by nasal cannula. ECG shows atrial fibrillation with rapid ventricular response. Fine crackles are heard at the lung bases.
The procedure is aborted and the patient is admitted to the cardiac care unit for further management. Medical history is significant for chronic lower back pain, anxiety disorder, and chronic headaches. Medications include acetaminophen as needed for pain. She has had no previous surgeries.
The following day, she feels fine and wishes to go home. Blood pressure is 112/70 mm Hg, and pulse is 78/min and regular. ECG shows normal sinus rhythm with nonspecific ST-segment and T-wave changes. Complete blood count, serum chemistries, and TSH are unremarkable. Transthoracic echocardiogram shows mild left atrial enlargement and mild mitral regurgitation. Left ventricular systolic function is normal.
Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (81)
(81) A 52-year-old man with alcoholic cirrhosis is admitted for worsening abdominal distension. He claims to have been compliant with his medications, which include spironolactone, furosemide, lactulose, propranolol, folic acid, and thiamine. He has no fever, chills, or abdominal pain. The patient has had no gastrointestinal bleeding in the past, but upper gastrointestinal endoscopy performed 6 months ago was consistent with grade 2 esophageal varices.
His temperature is 36.3 C (97.4 F), blood pressure is 115/70 mm Hg, and pulse is 90/min and regular. Tense ascites is present. His abdomen is nontender. There is 3+ pitting edema to the thighs bilaterally.
Laboratory results are as follows:
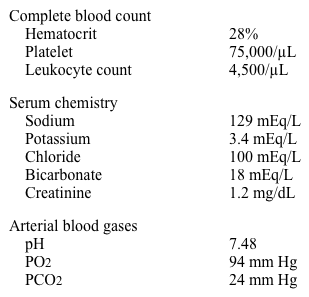 Which of the following is the most likely cause of this patient's acid-base disorder?
 (Multiple Choice)
4.7/5 (87)
(87) An 81-year-old woman is seen for a preoperative assessment prior to hip surgery. The patient presented yesterday evening after tripping while walking and falling from a standing height. She had no head trauma or loss of consciousness, but she injured her left hip. Evaluation revealed a left femoral neck fracture, and surgical repair is planned. Her other medical problems include hypertension, paroxysmal atrial fibrillation, and mild dementia. The patient takes donepezil, dabigatran, and metoprolol. She did not receive dabigatran last night or this morning in the hospital. The patient cannot recall if she took her medications yesterday morning or the day before, and her daughter was unable to determine this from the number of pills remaining in her mother's medication bottles.
Vital signs are within normal limits. Physical examination is notable for bruising and tenderness of the left hip.
Blood cell counts and serum chemistry studies are within normal limits. Other laboratory findings are as follows:
 Which of the following is the most appropriate recommendation regarding surgery and anticoagulation use in this patient?
 (Multiple Choice)
4.7/5 (72)
(72) A 52-year-old woman develops cardiac arrest while hospitalized for the treatment of a pulmonary embolism. Advanced cardiac life support (ACLS) measures, including external chest compressions and endotracheal intubation, are implemented. After the airway is secured, a waveform capnograph is attached to the endotracheal tube and shows that the end-tidal partial pressure of CO2 (EtCO2) is 16 mm Hg. Cardiopulmonary resuscitation is continued along ACLS guidelines. After approximately 5 minutes of resuscitation, the EtCO2 rapidly increases to 38 mm Hg.
Which of the following is the most likely explanation for the change in this patient's capnography finding?
(Multiple Choice)
4.8/5 (78)
(78) A 24-year-old African American man complains of abdominal pain while vacationing in the mountains with his parents. They arrived after 2 days of driving. Thirty-six hours after arrival, the patient experienced upper abdominal pain and nausea. The pain has increased and is localized to the left side of his abdomen. It is sharp, constant, and increased by deep inspiration. He also feels pain on the top of his left shoulder. He vomited a small amount of clear material once. The patient has no history of similar episodes. He considers himself to be in good health with no known medical problems. He does not use tobacco or illicit drugs but drinks 1-2 beers on weekends.
On examination, he looks mildly uncomfortable. His temperature is 37.8 C (100.5 F), pulse is 90/min, and respirations are 24/min. Pulse oximetry is 96% on ambient air. He appears to be splinting his left chest. No rales or rhonchi are heard. He has pain on palpation in the left upper quadrant without rebound tenderness. There is no lower-extremity swelling or tenderness. There are no skin rashes.
Laboratory results are as follows:
 Chest x-ray reveals blunting of the left costophrenic angle.
Which of the following studies would best reveal the underlying cause of this patient's condition?
Chest x-ray reveals blunting of the left costophrenic angle.
Which of the following studies would best reveal the underlying cause of this patient's condition? (Multiple Choice)
4.8/5 (81)
(81) A 52-year-old man comes to the physician because of weight loss and constipation for the past 3 months. He has no abdominal pain, vomiting, or black stools. He has smoked 1 pack of cigarettes daily for 20 years.
His vital signs are within normal limits. Examination shows no abnormalities. Test of the stool for occult blood is positive.
Laboratory results are as follows:
 He undergoes a colonoscopy that shows a nonobstructive mass in the rectum 10 cm from the anal verge. Biopsy during colonoscopy shows moderately differentiated adenocarcinoma. MR imaging shows tumor invading through the muscularis propria into perirectal tissues. CT scan of the chest, abdomen, and pelvis shows no lymph node enlargement or evidence of metastatic disease.
Which of the following is the most appropriate treatment for this patient?
He undergoes a colonoscopy that shows a nonobstructive mass in the rectum 10 cm from the anal verge. Biopsy during colonoscopy shows moderately differentiated adenocarcinoma. MR imaging shows tumor invading through the muscularis propria into perirectal tissues. CT scan of the chest, abdomen, and pelvis shows no lymph node enlargement or evidence of metastatic disease.
Which of the following is the most appropriate treatment for this patient? (Multiple Choice)
4.8/5 (81)
(81) A 74-year-old woman is brought to the emergency department after being found unconscious at home. She was in ventricular fibrillation and received defibrillation followed by tracheal intubation. EKG showed no ST-segment elevation and cardiac enzymes were negative. She was subsequently admitted to the intensive care unit.
Examination shows clear lung fields and regular first and second heart sounds. The abdomen is soft and nontender. The patient withdraws her extremities to painful stimuli but does not follow commands.
Chest-x ray shows no abnormalities.
Which of the following is the most effective strategy to decrease this patient's risk for developing ventilator-associated pneumonia?
(Multiple Choice)
5.0/5 (88)
(88) A 35-year-old woman underwent ultrasound evaluation for dyspepsia. No gallstones were identified; however, the ultrasonogram showed three cortical cysts in the right kidney, two in the left kidney, and two liver cysts. She is in good health and has no urinary symptoms. Her father died at the age of 52 from a stroke. There is no family history of kidney disease.
Her blood pressure is 132/78 mm Hg and pulse is 89/min. Her BMI is 29 kg/m2. Physical examination is unremarkable.
Her serum creatinine is 0.8 mg/dL. Urinalysis is normal.
Which of the following is the most likely diagnosis?
(Multiple Choice)
4.9/5 (75)
(75) An 81-year-old man is transferred from a skilled nursing facility to the hospital due to lethargy and poor oral intake over the last 24 hours. For the past 2 days, he has had increased urinary frequency and dysuria. A urinalysis showed evidence of urinary tract infection, and he was started on oral ciprofloxacin. He was recently hospitalized with acute ischemic stroke, and his hospital course was complicated by pneumonia requiring intravenous antibiotics. He also had an episode of urinary retention requiring Foley catheter placement for 5 days. His other medical problems include mild cognitive impairment, hypertension, and type 2 diabetes mellitus. He has no known drug allergies.
His temperature is 38.9° C (102° F), blood pressure is 92/58 mm Hg, and pulse is 112/min. Lungs are clear to auscultation. His extremities are warm and well perfused.
Foley catheter placement yields 230 mL of cloudy urine.
Laboratory results are as follows:
 Urine culture obtained at the nursing facility 2 days earlier showed extended spectrum beta-lactamase-producing Klebsiella.
Which of the following is the best initial antibiotic regimen for this patient?
Urine culture obtained at the nursing facility 2 days earlier showed extended spectrum beta-lactamase-producing Klebsiella.
Which of the following is the best initial antibiotic regimen for this patient? (Multiple Choice)
4.7/5 (73)
(73) A 78-year-old woman is admitted to the intensive care unit (ICU) with confusion, fever, hypotension, and tachypnea. She is intubated and started on antibiotics for septic shock caused by a urinary tract infection. Norepinephrine infusion is started via an internal jugular venous catheter. The ventilator is set on continuous mandatory ventilation (CMV) mode and the patient is sedated with midazolam and fentanyl infusions. Chest x-ray shows mild subsegmental atelectasis and appropriate positioning of endotracheal and orogastric tubes.
Which of the following is likely to decrease this patient's length of stay in the ICU and reduce the number of days she requires mechanical ventilation?
(Multiple Choice)
5.0/5 (79)
(79) A 68-year-old woman admitted for community-acquired pneumonia 4 days ago is evaluated in the hospital for new-onset jaundice. During morning rounds today, it is noted that she has yellowish discoloration of both eyes. The patient has no abdominal pain, nausea, or prior history of liver disease, but she has a history of hypertension. She does not use tobacco, alcohol, or illicit drugs. Her current medications include azithromycin, ceftriaxone, lisinopril, and acetaminophen as needed.
Her temperature is 36.7 C (98 F), blood pressure is 120/70 mm Hg, and pulse is 72 /min. The patient's pulse oximetry shows 96% on 2 liters oxygen. Examination reveals scleral icterus, rales in the right lower lobe, and normal heart sounds without murmurs. The abdomen is soft and nontender with no organomegaly.
Laboratory results are as follows:
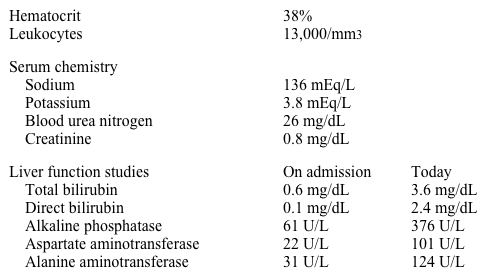 Acute viral hepatitis serologies are negative. Abdominal ultrasound reveals normal liver size and echotexture, a thin-walled nondistended gallbladder, no gallstones or biliary sludge, and a normal common bile duct.
Which of the following is the best next step in management of this patient?
Acute viral hepatitis serologies are negative. Abdominal ultrasound reveals normal liver size and echotexture, a thin-walled nondistended gallbladder, no gallstones or biliary sludge, and a normal common bile duct.
Which of the following is the best next step in management of this patient? (Multiple Choice)
4.9/5 (71)
(71) A 31-year-old farmer is hospitalized with a severe reaction to a bee (Hymenoptera) sting. He developed respiratory distress requiring endotracheal intubation in the field. He was treated with epinephrine and corticosteroids with rapid recovery. The patient has no prior similar incidents and no allergies. He is given an epinephrine autoinjector and instructed on its use.
Which of the following is the most important part of discharge planning in this patient?
(Multiple Choice)
4.9/5 (80)
(80) A 40-year-old woman is seen 48 hours after an uncomplicated repeat caesarean delivery at 39 weeks gestation. She reports sudden-onset shortness of breath and a nonproductive cough. The patient has no fever, chills, nausea, vomiting, or chest pain. Her prenatal course was uncomplicated. She has no chronic medical conditions. The patient's previous pregnancy was uncomplicated; she had a term caesarean delivery for breech presentation.
On examination, the patient appears distressed. Blood pressure is 196/112 mm Hg, pulse is 120/min, and respirations are 32/min. Pulse oximetry is 86% on room air. Auscultation of the lungs shows diffuse inspiratory crackles bilaterally. Jugular venous pressure is normal. Cardiac sounds are normal and there are no murmurs or additional sounds. Abdominal examination is normal. There is 2+ pedal edema to the bilateral mid-calves.
Laboratory results are as follows:
 Chest x-ray reveals bilateral diffuse alveolar infiltrates. ECG shows sinus tachycardia and upsloping ST-segment depressions in the inferior lateral leads.
Which of the following is the most likely diagnosis in this patient?
Chest x-ray reveals bilateral diffuse alveolar infiltrates. ECG shows sinus tachycardia and upsloping ST-segment depressions in the inferior lateral leads.
Which of the following is the most likely diagnosis in this patient? (Multiple Choice)
4.8/5 (67)
(67) A 57-year-old man undergoes bronchoscopy for a persistent cough productive of blood-tinged sputum. He denies chest pain, shortness of breath, wheezing, and weight loss. He is a long-term cigarette smoker. He is allergic to peanuts and shell fish. A physical examination does not reveal any significant abnormalities. He is sedated with fentanyl and midazolam, and a local anesthetic is applied. The bronchoscope is subsequently introduced into the trachea without difficulty. About 10 minutes into the procedure, he is noted to be cyanotic by the medical assistant. The procedure is aborted and supplemental oxygen is administered.
His blood pressure is 112/78 mm Hg, pulse is 115/min, and respiratory rate is 20/min. Pulse oximetry has fallen from 94% pre-procedure to 85% at present. There is central cyanosis. Vesicular breath sounds are heard bilaterally. Myoclonic jerks involving all extremities are apparent. There is no skin rash.
Immediate arterial blood gas analysis shows the following:
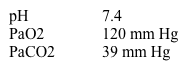 Which of the following is the most likely diagnosis?
 (Multiple Choice)
4.8/5 (82)
(82) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)