



 Chat with AI
Exam 2: In-patient Facilities

Exam 1: Emergency Department218 Questions
Exam 2: In-patient Facilities128 Questions
Exam 3: Office/Health Center900 Questions
Select questions type


A 44-year-old woman is brought to the emergency department with 2 days of abdominal pain. She has had worsening upper abdominal pain associated with nausea and multiple episodes of non-bloody vomiting. She also reports subjective fevers and chills. The patient's past medical history is notable for hypertension. She drinks alcohol socially and does not use tobacco or recreational drugs. Her last drink was a week ago.
Temperature is 38.4 C (101.2 F), blood pressure is 116/60 mm Hg, pulse is 112/min, and respirations are 18/min. BMI is 34 kg/m2. Mucous membranes are dry and there is mild scleral icterus. There is tenderness in the mid-epigastrium and right upper quadrant without rebound or guarding. Rectal examination is notable for brown guaiac-negative stool.
Laboratory results are as follows:
 CT scan of the abdomen shows diffuse pancreatic enlargement and heterogenous attenuation with peripancreatic inflammation. The liver appears normal. The gallbladder has multiple small gallstones with surrounding gallbladder wall edema. The common bile duct is dilated and measures 12 mm.
The patient is made NPO and is started on analgesics, intravenous hydration, and empiric intravenous antibiotics.
Which of the following is the most appropriate next step in management of this patient?
CT scan of the abdomen shows diffuse pancreatic enlargement and heterogenous attenuation with peripancreatic inflammation. The liver appears normal. The gallbladder has multiple small gallstones with surrounding gallbladder wall edema. The common bile duct is dilated and measures 12 mm.
The patient is made NPO and is started on analgesics, intravenous hydration, and empiric intravenous antibiotics.
Which of the following is the most appropriate next step in management of this patient? (Multiple Choice)
4.8/5  (81)
(81) A 25-year-old man sustained a head injury during a motor vehicle accident. He is currently comatose and intubated in the intensive care unit. He has no significant medical problems except for mild asthma. His urine drug screen was negative; however, his blood alcohol level was above the legal limit. He works as a bartender and frequently binges on hard liquor and beer. A non-contrast head CT at the time of admission revealed a hyperdense, extra-axial, space-occupying, right-sided lesion, which was subsequently drained. He was sedated with a propofol infusion, but it was discontinued 12 hours ago.
His temperature is 37 C (98.6 F), pulse is 80/min, blood pressure is 130/85 mm Hg, and respirations are 18/min. He is currently on volume assist-control ventilation with an FiO2 of 40%, tidal volume of 500 cc, and PEEP of 5 cm H2O. He is not triggering the ventilator. The general physical examination is unremarkable except for a hemi-craniectomy along the right side of the head. He is comatose on neurological examination. Cranial nerve and motor responses are absent.
His arterial blood gas analysis shows a pH of 7.42, PaCO2 of 36 mm Hg, and PaO2 of 101 mm Hg.
Which of the following is essential in establishing the diagnosis of brain death in this patient?
(Multiple Choice)
4.8/5 (74)
(74) A 29-year-old woman undergoes thyroidectomy for Graves' disease with ophthalmopathy. She was treated with antithyroid drugs and beta-blockers preoperatively. Physical examination and laboratory results prior to surgery were unremarkable. Her ophthalmopathy was characterized as moderate with no corneal involvement or visual loss.
The patient has no immediate surgical complications. Twenty-four hours after extubation, she reports feeling anxious and is irritable. She has paresthesias of her hands and around her lips. Six hours later, shortly after a nursing shift change, she complains of trouble breathing and has a high-pitched inspiratory sound. A quick inspection of her neck bandages reveals no hemorrhage.
What is the most likely cause of her dyspnea?
(Multiple Choice)
4.7/5 (81)
(81) A 63-year-old man with chronic obstructive pulmonary disease is brought to the emergency department due to fever, chills, and shortness of breath for 5 days. His medications include aspirin, inhaled albuterol, and inhaled ipratropium. The patient has smoked a pack of cigarettes daily for 43 years and drinks 3-4 cans of beer daily. His trachea is intubated in the emergency department due to respiratory distress, and intravenous antibiotics and glucocorticoids are initiated.
In the intensive care unit, temperature is 38.3 C (100.9 F), blood pressure is 130/80 mm Hg, pulse is 132/min, and respirations are 22/min. Pulse oximetry shows 94% on assist-control mode with a tidal volume of 550 mL, respiratory rate of 22/min, fraction of inspired oxygen of 60%, and positive end-expiratory pressure of 5 mm H2O. Examination reveals diffuse crackles over the left lung, normal S1 and S2, and clubbing.
Laboratory studies are as follows:
 Chest-x ray shows a left-sided infiltrate and hyperinflated lungs. The ventilator waveforms show air trapping.
Which of the following is the most appropriate next step in management of this patient?
Chest-x ray shows a left-sided infiltrate and hyperinflated lungs. The ventilator waveforms show air trapping.
Which of the following is the most appropriate next step in management of this patient? (Multiple Choice)
4.8/5 (79)
(79) A 63-year-old man is scheduled for coronary artery bypass surgery. He underwent cardiac catheterization for a 2-month history of effort-limiting angina and was found to have left main coronary artery stenosis. One year ago, the patient underwent drug-eluting stent placement in the right coronary artery. The patient's other medical problems include type 2 diabetes mellitus and obesity. His current medications are low-dose aspirin, clopidogrel, rosuvastatin, metoprolol, and basal-bolus insulin therapy.
Vital signs are within normal limits except for BMI of 35 kg/m2. Cardiopulmonary examination is unremarkable.
ECG shows sinus rhythm with normal intervals, minimal voltage criteria for left ventricular hypertrophy, and no pathologic Q waves. The patient's most recent echocardiogram showed a left ventricular ejection fraction of 50% with no regional wall motion or valvular abnormalities.
Which of the following is the most appropriate management of this patient's antiplatelet medication before surgery?
(Multiple Choice)
4.9/5 (75)
(75) A 74-year-old man recovering from recent ischemic stroke develops right ankle and calf swelling. He has mild, persistent right-sided hemiplegia and has been receiving daily physical therapy for the last week. Compression ultrasonography confirms right-sided popliteal vein thrombosis. The patient is started on a therapeutic dose of enoxaparin twice daily.
When is it appropriate for this patient to resume mobilization and physical therapy?
(Multiple Choice)
4.8/5 (81)
(81) A 55-year-old man is evaluated for acute onset of respiratory distress. He was admitted to the hospital after a highway traffic accident, which resulted in a left femur and wrist fracture. He was immediately taken to the operating room and underwent open reduction and internal fixation. The total blood loss was estimated at 1.1 liters and he was given 2 liters of intravenous normal saline and one unit of packed red blood cells intraoperatively. He was extubated and transferred to the postoperative recovery room. One hour following extubation, he developed acute respiratory distress requiring reintubation. His other medical problems include inferior wall myocardial infarction with right coronary artery stent placement 3 years ago, hypertension, hyperlipidemia, and type 2 diabetes mellitus. His home medications include aspirin, metoprolol, lisinopril, metformin, and rosuvastatin.
His temperature is 38.1 C (100.6 F), blood pressure is 110/70 mm Hg, pulse is 110/min, respirations are 30/min, and oxygen saturation is 90% on 100% FiO2 and 10 mm Hg of PEEP. He is drowsy from the sedation and intravenous hydromorphone infusion. There is no jugular venous distention or lower extremity edema. Pulmonary examination reveals diffuse crackles throughout the lungs. There are no heart murmurs. Skin examination reveals no rashes.
Arterial blood gas shows a pH of 7.47, PaCO2 of 32 mm Hg, and PaO2 of 65 mm Hg.
ECG shows sinus tachycardia. His preoperative chest x-ray was within normal limits. Repeat chest x-ray taken before reintubation is shown below.
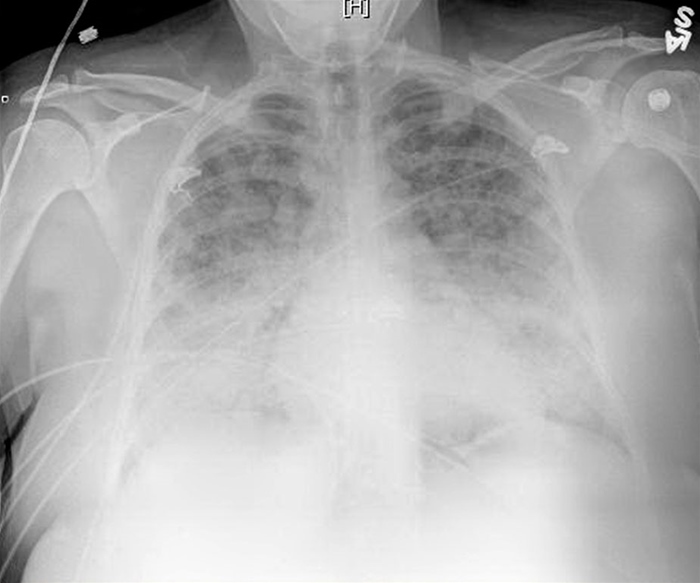 Which of the following is the most likely cause of his current condition?
 (Multiple Choice)
4.9/5 (83)
(83) A 73-year-old smoker is brought to the emergency department with fever and shortness of breath. His medical problems include hypertension and prior ischemic stroke with mild residual right-sided weakness. His trachea is cannulated in the emergency department due to respiratory distress. Intravenous antibiotics are initiated.
In the intensive care unit, his temperature is 38.9 C (102 F), blood pressure is 165/90 mm Hg, pulse is 116 /min, and respirations are 18/min on ventilator. Examination reveals crackles over the right lung field and normal first and second heart sounds. The abdomen is soft and non-tender. Bowel sounds are diminished.
Laboratory results are as follows:
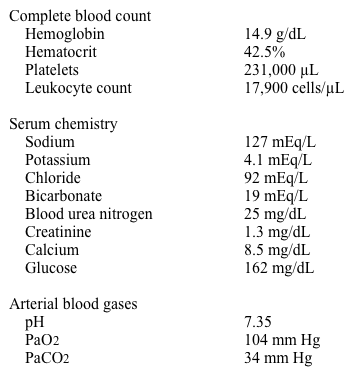 Chest-x ray reveals a dense right middle-lobe infiltrate.
Which of the following is the most appropriate next step in management?
Chest-x ray reveals a dense right middle-lobe infiltrate.
Which of the following is the most appropriate next step in management? (Multiple Choice)
4.9/5 (89)
(89) A 48-year-old man is evaluated in the surgical intensive care unit for tachycardia and hypotension. He underwent a hemicolectomy due to a perforated colonic diverticulum yesterday. The patient has a history of hyperlipidemia but no known history of heart disease. His current medications include piperacillin/tazobactam, famotidine, and benzodiazepines and opioids for sedation.
The patient is intubated and the ventilator is in the assist control mode. His temperature is 39.4 C (103 F), blood pressure is 86/55 mm Hg, and pulse is 142/min. Oxygen saturation is 99% on 40% FiO2.
Examination shows flat neck veins and tachycardia with an irregular rhythm. Breath sounds are heard bilaterally without wheezes or rhonchi. The abdomen is soft but diffusely tender and the incision is clean. The stoma is pink without any fluid output in the bag. The patient's extremities are warm with 2+ pulses and no peripheral edema. His urine output is 10 mL/hr.
Laboratory results are as follows:
 ECG shows atrial fibrillation with rapid ventricular response. There are no significant ST-segment or T wave changes.
Which of the following would be the most appropriate next step in management of this patient?
ECG shows atrial fibrillation with rapid ventricular response. There are no significant ST-segment or T wave changes.
Which of the following would be the most appropriate next step in management of this patient? (Multiple Choice)
4.8/5 (104)
(104) A 60-year-old man is hospitalized for acute pancreatitis. He reports swelling and tenderness in his jaw that appeared 6 months ago. He has no medical problems, takes no medications, and does not use tobacco, alcohol, or illicit drugs. There is no history of trauma to the abdomen. He does not have dry eyes or dry mouth. On admission, ultrasound of the abdomen shows no gallstones. CT of the abdomen reveals a 3x4-cm solid mass in the mid-portion of his pancreas with some surrounding edema. Chest CT reveals bilateral hilar adenopathy. He is started on intravenous fluids, opioids for pain control, and nothing by mouth, and his abdominal pain resolves.
On examination, he is well-nourished and appears comfortable. His blood pressure is 133/78 mm Hg, pulse is 90/min, and oxygen saturation is 98% on room air. There is bilateral enlargement of his parotid glands and some enlargement of his lacrimal glands. The remainder of his examination is within normal limits.
Laboratory results are as follows:
 Serum chemistry and fasting lipid panels, liver function tests, urinalysis, and erythrocyte sedimentation rate are all within normal limits. HIV testing is negative.
Which of the following conditions is the most likely cause of this patient's presentation?
Serum chemistry and fasting lipid panels, liver function tests, urinalysis, and erythrocyte sedimentation rate are all within normal limits. HIV testing is negative.
Which of the following conditions is the most likely cause of this patient's presentation? (Multiple Choice)
4.9/5 (65)
(65) A 60-year-old man with alcoholism is admitted after being found unresponsive in the street. No other history is available.
His temperature is 37.1 C (98.8 F), blood pressure is 130/86 mm Hg, pulse is 110/min and regular, and respirations are 20/min. On examination, the patient is disheveled and appears chronically ill. He has decreased muscle mass and no subcutaneous fat. He responds to painful stimuli and has slurred speech. Carpal spasm was noted in the hand of the arm in which his blood pressure was taken. Mucous membranes are dry and there is no moisture in the axillae. He has nystagmus on end lateral gaze of both eyes. No other focal neurologic findings are present.
Laboratory results are as follows:
 Intravenous thiamine and fluids consisting of 3 L normal saline/5% dextrose containing 40 mEq of potassium are administered over 4 hours. Electrolytes are re-measured with the following results:
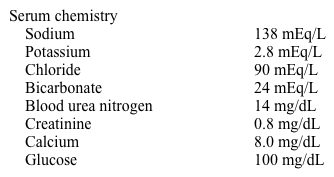 Which of the following is the most likely cause of this patient's hypokalemia?
Intravenous thiamine and fluids consisting of 3 L normal saline/5% dextrose containing 40 mEq of potassium are administered over 4 hours. Electrolytes are re-measured with the following results:
Which of the following is the most likely cause of this patient's hypokalemia? (Multiple Choice)
4.8/5 (86)
(86) A 78-year-old man is brought to the emergency department with severe abdominal pain over the last 6 hours. He has vomited twice since the onset of symptoms. Six months ago, he was diagnosed with severe aortic stenosis with an estimated aortic valve area of 0.8 cm2 and has been followed clinically. The patient's left ventricular ejection fraction was normal. He also has chronic kidney disease with baseline estimated glomerular filtration rate of 50 mL/min.
His temperature is 38.3 C (101 F), blood pressure is 102/65 mm Hg, and pulse is 122/min and regular. Lungs are clear on auscultation. A 3/6 mid-systolic murmur is heard at the right upper sternal border with radiation to the carotids. The carotid pulse is delayed. The abdomen is mildly distended and diffusely tender with prominent rebound tenderness. The extremities are warm. Upright chest x-ray shows free air under the diaphragm.
He receives intravenous fluids and antibiotics.
Which of the following is the best initial management for this patient?
(Multiple Choice)
4.9/5 (77)
(77) A 55-year-old construction worker is brought to the emergency department 2 hours after awakening with severe left chest discomfort. He appears diaphoretic and uncomfortable. He has no other medical problems and has not seen a physician in 5 years.
His blood pressure is 152/88 mm Hg and pulse is 92/min. Examination shows clear lung fields, normal first and second heart sounds, and the presence of a fourth heart sound. His initial EKG shows sinus rhythm with a 3-mm ST-segment elevation in leads V1-V4.
The hospital does not have a cardiac catheterization laboratory and the closest hospital with angioplasty capabilities is 2 hours away. The patient is given a single bolus dose of tenecteplase over 10 seconds. His chest discomfort subsides completely, and a repeat EKG 30 minutes after injection shows near-complete resolution of the ST-segment elevation.
Which of the following is the best next step in managing this patient?
(Multiple Choice)
4.8/5 (86)
(86) A 23-year-old woman with known type 1 diabetes mellitus and systemic lupus erythematosus is admitted with low-grade fever, nausea, and headache. She takes prednisone, hydroxychloroquine, and multiple daily injections of insulin. She also uses decongestants for seasonal allergies and omeprazole for acid reflux disease.
Initial laboratory results are as follows:
 Lumbar puncture shows protein of 23 mg/dL and no white blood cells. Chest x-ray is normal. Urinalysis shows no evidence of infection. The patient is treated with IV fluids and insulin infusion. On the second day of hospitalization, she complains of worsening headache and blurry vision. On physical examination, she appears mildly lethargic. There is right-sided periorbital swelling and tenderness over the maxilla. There is no lymph node enlargement and the neck is supple. Chest examination is unremarkable. The abdomen is soft and nontender. There are no skin rashes.
Repeat laboratory results are as follows:
 This patient would most likely require which of the following?
Lumbar puncture shows protein of 23 mg/dL and no white blood cells. Chest x-ray is normal. Urinalysis shows no evidence of infection. The patient is treated with IV fluids and insulin infusion. On the second day of hospitalization, she complains of worsening headache and blurry vision. On physical examination, she appears mildly lethargic. There is right-sided periorbital swelling and tenderness over the maxilla. There is no lymph node enlargement and the neck is supple. Chest examination is unremarkable. The abdomen is soft and nontender. There are no skin rashes.
Repeat laboratory results are as follows:
This patient would most likely require which of the following? (Multiple Choice)
4.8/5 (73)
(73) A 46-year-old man with known kyphoscoliosis complains of fatigue and progressive shortness of breath over the last year. He can barely walk a block without becoming "short-winded." During his last evaluation, his vital capacity was 40% of predicted value and his FEV1/FVC ratio was 85%. He does not use tobacco, alcohol, or illicit drugs.
The patient's blood pressure is 144/78 mm Hg and pulse is 78/min. Oxygen saturation is 90% on room air. The angle of scoliosis is > 65 degrees and kyphosis deformity is above T10. The remainder of physical examination is unremarkable.
Transthoracic echocardiogram shows normal left ventricular function, mild right ventricular enlargement, and estimated pulmonary artery systolic pressure of 55 mm Hg. Pulmonary function test results are unchanged from prior testing.
This patient is most likely to benefit from which of the following?
(Multiple Choice)
4.9/5 (61)
(61) A 23-year-old woman with a 12-year history of type 1 diabetes mellitus is hospitalized with diabetic ketoacidosis. On admission, her blood pressure is 80/60 mm Hg, pulse is 120/min, and respirations are 28/min. She weighs 60 kg (132 lb). Her oropharynx is very dry. Abdominal examination shows diffuse tenderness without guarding or hepatosplenomegaly. The remainder of her physical examination is within normal limits.
Her clinical status improves significantly with intravenous (IV) fluids and insulin. In the first 2 hours, she receives 2 liters of isotonic saline (NS), and this is later changed to 1/2 NS with potassium chloride (KCl) at 250 mL/hr. The patient is also receiving IV regular insulin infusion. Her blood glucose declines steadily to 188 mg/dL after 6 hours of treatment. She states that she is feeling better but still feels very nauseous.
Laboratory results are as follows:
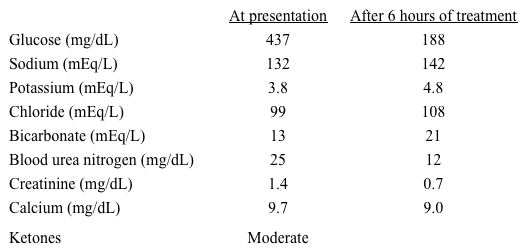 Which of the following is the most appropriate fluid management for this patient?
 (Multiple Choice)
4.8/5 (81)
(81) A 35-year-old woman comes to the emergency department with progressively worsening dyspnea and generalized weakness. She has had a month of double vision and difficulty swallowing that are significantly worse toward the end of the day. Over the past 2 weeks, she has had difficulty raising her arms above her head and walking up and down stairs. The patient has no headache, speech difficulty, muscle aches, numbness, or paresthesias. She also has no rash, insect bites, recent travel, or illness.
On physical examination, the patient has fatigable horizontal binocular diplopia in the primary position and bilateral ptosis. Strength is 4 on a scale of 5 in the proximal muscles of the upper and lower extremities. Sensory examination and reflex testing are unremarkable.
Complete blood count, comprehensive metabolic panel, and chest x-ray are normal. Vital capacity obtained at the bedside is 500 mL. The patient's respiratory status decompensates, requiring endotracheal intubation and admission to the intensive care unit.
Which of the following therapies is the most appropriate for rapidly improving this patient's current condition?
(Multiple Choice)
4.8/5 (81)
(81) An 80-year-old man fell at home and sustained a hip fracture. On the day after repair, physical therapy team members notice that the patient's post-operative hemoglobin is 8.6 g/dL. They recommend a blood transfusion, which may allow the patient greater participation in rehabilitation and a more rapid recovery.
The patient's admitting ECG showed evidence of an old inferior myocardial infarction. At that time, his pre-operative hemoglobin was 11.5 g/dL. Two years ago, he experienced pedal edema and dyspnea with exertion requiring diuretics for presumed mild congestive heart failure.
The patient is currently resting comfortably and has no chest pain or pressure, dyspnea, or fatigue. His blood pressure is 130/84 mm Hg and pulse is 84/min and regular. Oxygen saturation is 97% on room air. Jugular venous pressure is normal. The lungs are clear to auscultation. There is a grade 2/6 systolic murmur along the upper left sternal border. There is trace pedal edema bilaterally to the shin.
Repeat hemoglobin is 8.5 g/dL and mean corpuscular volume is 89 fL.
Which of the following is the most appropriate step in management of this patient's low hemoglobin?
(Multiple Choice)
4.7/5 (83)
(83) A 40-year-old man with known HIV infection is admitted to the hospital with right arm weakness and difficulty with speech. He was diagnosed with HIV infection eight years ago. He has not been adherent with either anti-retroviral treatment or trimethoprim-sulfamethoxazole prophylaxis therapy for several months prior to admission. His most recent CD4 count obtained 12 months ago was 150/µL. He does not smoke, drink alcohol, or use intravenous drugs.
His BMI is 26 kg/m2. After a thorough evaluation, a diagnosis of central nervous system toxoplasmosis was established. He was given intravenous fluids and therapy was initiated with sulfadiazine and pyrimethamine.
Which of the following additional medications should be given to this patient?
(Multiple Choice)
4.9/5 (72)
(72) A 62-year-old man comes to the hospital due to 2 days of bilateral lower extremity swelling and throbbing pain. Two weeks ago he was admitted to a different hospital with a non-ST elevation myocardial infarction. He initially received aspirin, metoprolol, nitrates, heparin, a statin, and a glycoprotein IIb/IIIa inhibitor. Cardiac catheterization showed 3-vessel coronary artery disease and a left ventricular ejection fraction of 40%. The patient underwent on-pump coronary artery bypass grafting. His postoperative course was uncomplicated, and he was discharged home with a normal blood count and serum creatinine levels. He also has a history of hypertension, hyperlipidemia, and type 2 diabetes mellitus. His current medications include aspirin, metoprolol, lisinopril, atorvastatin, metformin, insulin, and fish oil. The patient does not use tobacco, alcohol, or illicit drugs.
Blood pressure is 135/70 mm Hg, pulse is 78/min, and oxygen saturation is 98% on room air. Physical examination reveals clear lungs, normal heart sounds, and bilateral pitting edema. There is no jugular venous distension. The sternotomy scar is clean, dry, and intact. The remainder of the examination is unremarkable.
Laboratory results are as follows:
 Lower extremity ultrasound reveals extensive, bilateral deep venous thrombosis extending into the superficial femoral veins.
Which of the following is the most appropriate next step in management of this patient?
Lower extremity ultrasound reveals extensive, bilateral deep venous thrombosis extending into the superficial femoral veins.
Which of the following is the most appropriate next step in management of this patient? (Multiple Choice)
4.8/5 (90)
(90) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)