



 Chat with AI
Exam 2: In-patient Facilities

Exam 1: Emergency Department218 Questions
Exam 2: In-patient Facilities128 Questions
Exam 3: Office/Health Center900 Questions
Select questions type


A 76-year-old woman is brought to the emergency department due to severe back pain. The patient slipped on a wet tile floor in her bathroom and fell against the toilet; she was unable to stand due to severe pain and was transported to the hospital by ambulance. Medical history is notable for Alzheimer disease and osteoporosis. The patient lives in an assisted living facility.
Vital signs are normal. Examination shows extensive abrasions and ecchymosis across the midback and midline tenderness in the lower thoracic spine. Neurologic examination shows decreased ankle reflexes bilaterally, with normal lower extremity motor strength, sensation, and knee reflexes.
Serum chemistry panel and complete blood count are normal. X-rays of the spine reveal a wedge compression fracture of T12.
Because the patient continues to rate the pain as 9 on a scale of 0-10 despite 2 doses of oral analgesics, she is admitted for parenteral pain control. Which of the following additional measures is indicated at this time?
(Multiple Choice)
4.8/5  (80)
(80) A 22-year-old hospitalized woman is evaluated for thrombocytopenia. Three days ago, she was hospitalized due to lower abdominal pain, vaginal bleeding, and fever. She was diagnosed with a septic abortion, was initiated on cefotetan and doxycycline, and underwent dilation and curettage. Platelet count at admission was 154,000/mm3; yesterday it was noted to be 89,000/mm3, with a further decrease on this morning's results. She has had no epistaxis or visible blood in the urine or stool but has had mild headache and fatigue. The patient has no known medical problems and no history of blood disorders.
Vital signs are normal. Physical examination shows scattered ecchymoses but is otherwise unremarkable, including benign abdominal and pelvic examinations.
Complete laboratory results from today are as follows:
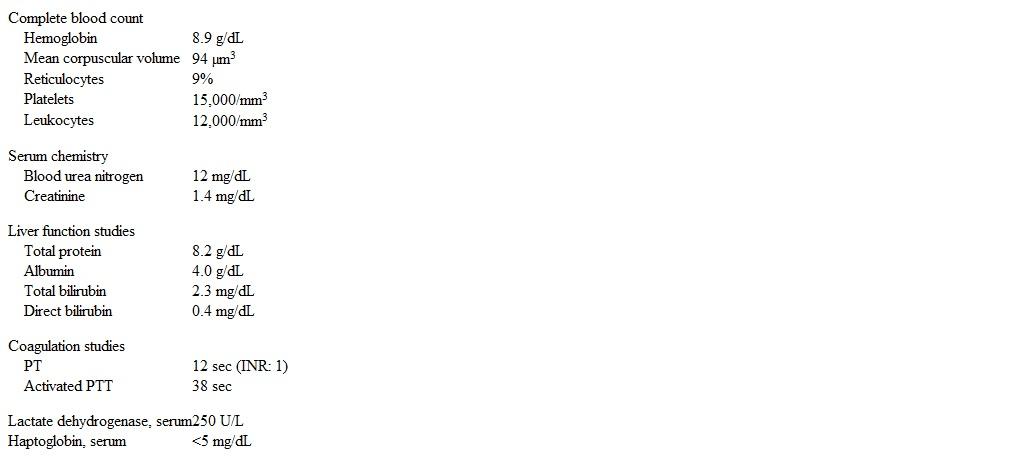 Direct Coombs test is negative. Peripheral blood smear shows decreased platelets, polychromatophilic red blood cells, and multiple schistocytes with no platelet clumping.
Which of the following is the most likely cause of this patient's thrombocytopenia?
Direct Coombs test is negative. Peripheral blood smear shows decreased platelets, polychromatophilic red blood cells, and multiple schistocytes with no platelet clumping.
Which of the following is the most likely cause of this patient's thrombocytopenia? (Multiple Choice)
4.8/5 (71)
(71) A 75-year-old woman with stage 4 breast cancer with brain metastases is admitted to hospice with a life expectancy of 2-4 weeks. She responded poorly to her last chemotherapy treatment and decided with her family that palliative care was best. Although her pain is fairly well controlled, the patient has very poor appetite, little energy, and sleeps for most of the day. She often does not get up for meals and has lost 3.6 kg (8 lb) in the past week. During a family visit, the daughter notices that the patient is quieter than usual and appears very depressed; she says, "She barely responds to us anymore and just cries softly."
Physical examination is unchanged. The patient is alert and oriented. When the physician asks the patient about her mood she says, "Of course I am depressed given my situation. I'm just so hopeless and tired."
In addition to providing support, which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.9/5 (69)
(69) A 60-year-old woman is brought to the emergency department by her husband due to confusion. She has been increasingly confused over the last 2 days. The patient also has a 2-week history of excessive urination, heartburn, nausea, vomiting, and fatigue. She has had no associated fever, chills, chest pain, or respiratory symptoms. Medical history is notable for coronary artery disease, hypertension, and gastroesophageal reflux. The patient takes several medications, including an over-the-counter medication for heartburn, but her husband does not recall their names.
Temperature is 37.2 C (99 F), blood pressure is 146/90 mm Hg, pulse is 90/min, and respirations are 16/min. Pulse oximetry is 96% on room air. Mucous membranes are dry. The patient cannot recall 2 of 3 items acutely. The lungs are clear with no cardiac murmurs or gallops. She has no skin rashes.
Laboratory results are as follows:
 The patient's serum calcium rapidly improves with an infusion of normal saline.
Which of the following is the most likely diagnosis?
The patient's serum calcium rapidly improves with an infusion of normal saline.
Which of the following is the most likely diagnosis? (Multiple Choice)
4.8/5 (80)
(80) A 34-year-old man comes to the emergency department due to 2 days of fever, chills, and drenching sweats. He has had no sore throat, cough, shortness of breath, chest pain, or dysuria. The patient has a history of Crohn disease and recently underwent abdominal surgery to remove a bowel stricture. The postoperative course was complicated by an enterocutaneous fistula, which has been treated over the past 6 weeks with antitumor necrosis factor therapy. This treatment has reduced the amount of drainage from the fistula. He has had no recent abdominal pain or diarrhea. The patient takes nothing by mouth and receives daily total parenteral nutrition. He has no other medical problems and does not use tobacco, alcohol, or illicit drugs.
Temperature is 38.3 C (101 F), blood pressure is 110/60 mm Hg, pulse is 112/min, and respirations are 18/min. The patient is ill-appearing and diaphoretic. The lungs are clear to auscultation. Cardiac examination reveals tachycardia but is otherwise unremarkable. The abdomen is soft and nontender with clear discharge from the infraumbilical fistula site. The right upper arm peripherally inserted central catheter site has no erythema or tenderness.
Leukocyte count is 18,000/mm3, and serum creatinine is 0.9 mg/dL. Chest x-ray reveals no infiltrates. Urinalysis is normal. Blood cultures are obtained, and empiric broad-spectrum intravenous antibiotics are initiated.
Within the next 24 hours, both sets of blood cultures grow budding yeast.
Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.8/5 (75)
(75) A 76-year-old man with chronic obstructive pulmonary disease is admitted to the intensive care unit for pneumonia. On presentation in the emergency department, he had hypercapnia and hypoxic respiratory failure. He was intubated and sedated. After intubation, the patient's blood pressure dropped to 85/58 mm Hg and did not recover with intravenous fluid resuscitation. A central venous catheter was placed and he was started on pressors.
Which of the following procedures is most likely to improve outcome in this patient?
(Multiple Choice)
4.9/5 (83)
(83) A 56-year-old man comes to the emergency department with retrosternal chest pain that began when he was cleaning his backyard a few hours ago. His medical problems include type 2 diabetes mellitus, hypertension, hypercholesterolemia, and obesity. Three weeks ago, his hemoglobin A1C was 9.6% and glyburide was added. He has no overt chronic complications of diabetes. His medications include metformin, glyburide, ramipril, amlodipine, simvastatin, and low-dose aspirin.
His blood pressure is 140/80 mm Hg, pulse is 70/min, and body mass index is 38 kg/m2. The patient appears a little apprehensive, but the examination otherwise shows no abnormalities.
Electrocardiogram shows normal sinus rhythm and non-specific ST-T changes in the lateral chest leads. The initial levels of cardiac troponin I are normal. Chemistry profile is normal except for blood glucose of 266 mg/dL. Chest x-ray is unremarkable.
The patient is admitted to a telemetry bed for monitoring, and serial cardiac enzymes are ordered. He is allowed to eat a diabetic diet. Finger-stick blood glucose measurement before meals and bedtime is ordered.
Which of the following is the best way to manage this patient's diabetes mellitus during hospitalization?
(Multiple Choice)
5.0/5 (79)
(79) A study evaluates the role of MRI in assessing the potential for myocardial recovery after reperfusion. A total of 185 patients undergoing coronary bypass surgery were evaluated by MRI for delayed gadolinium enhancement, indicative of myocardial scar tissue and therefore no viability. Subsequently, the patients were followed for improvement in myocardial contractility after surgery. The following results were obtained.
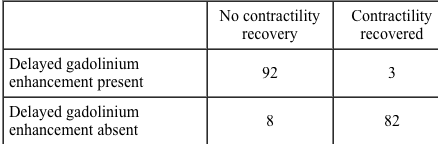 Which of the following best describes the specificity of MRI in assessing for scar tissue?
 (Multiple Choice)
4.8/5 (87)
(87) A 25-year-old woman being treated for infective endocarditis is evaluated for new-onset renal dysfunction. The patient has a 2-year history of injection drug use and presented 3 weeks ago with subjective fevers, pleuritic chest pain, and shortness of breath. Chest CT imaging with contrast revealed peripheral nodular opacities consistent with septic emboli, and blood cultures were positive for Enterococcus faecalis. Echocardiography showed tricuspid valve vegetations without valvular insufficiency or abnormal cardiac function. The patient has been receiving intravenous ampicillin and ceftriaxone, and repeat blood cultures have been negative. Yesterday, she was noted to have elevated serum creatinine on routine weekly laboratory studies. The patient has no nausea, vomiting, flank pain, rash, dysuria, or chills. She continues to void regularly with no changes in appearance or volume of her urine.
Temperature is 38.3 C (100.9 F), blood pressure is 122/64 mm Hg, pulse is 90/min, and respirations are 14/min. Physical examination shows no jugular venous distension, and auscultation of the heart and lungs is normal. There is no abdominal or costovertebral angle tenderness. No rash or edema is present.
Repeat laboratory results are as follows:
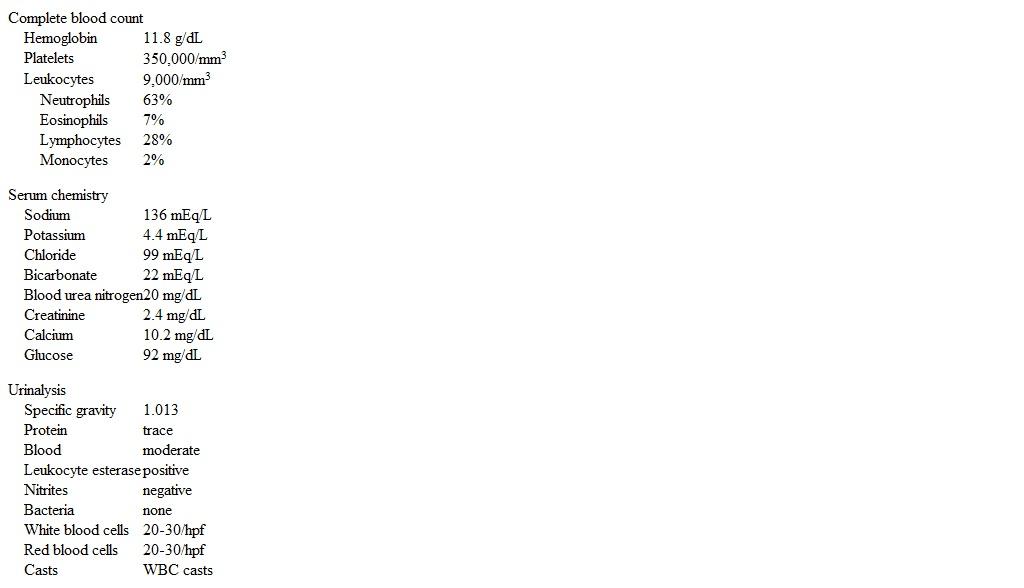 Which of the following is the most likely diagnosis in this patient?
 (Multiple Choice)
4.8/5 (90)
(90) A 78-year-old man is evaluated for gallstones. The patient has a history of benign prostate hyperplasia and was admitted to the hospital earlier today with lower abdominal discomfort and difficulty voiding. Evaluation revealed a distended urinary bladder and serum creatinine of 1.3 mg/dL. A urinary catheter was placed, draining 400 mL of cloudy urine. He was started on empiric antibiotics and an alpha-adrenergic antagonist. Abdominal ultrasonography revealed no hydronephrosis, but 2 large gallstones were seen with no gallbladder wall thickening or dilation of the common bile duct. The patient has had intermittent abdominal bloating and mild nausea in the past but reports no fever, chills, pain in the right upper quadrant, or jaundice. Other medical problems include hypertension and type 2 diabetes mellitus.
Temperature is 36.6 C (98 F), blood pressure is 144/83 mm Hg, and pulse is 78/min. BMI is 44 kg/m2. Physical examination reveals mild suprapubic and epigastric tenderness on deep palpation, which does not accentuate on inspiration. There is no rebound tenderness.
Laboratory results are as follows:
 Which of the following is the best next step in management of this patient's gallstones?
 (Multiple Choice)
4.8/5 (83)
(83) A 47-year-old man is hospitalized due to worsening shortness of breath over the last 2 days. He complains of orthopnea requiring 2 pillows to sleep. The patient has a history of coronary artery disease and underwent coronary artery bypass grafting 2 years ago. He has been nonadherent with his medications.
His temperature is 98.6° F (37° C), blood pressure is 157/90 mm Hg, pulse is 113/min, and respirations are 34/min. Pulse oximetry shows 88% on 100% O2 non-rebreather face mask. He appears to be in respiratory distress and is using accessory muscles of respiration. Jugular venous pressure is estimated at 12 cm H2O. Examination shows a third heart sound and bibasilar crackles. There is 1+ pitting peripheral edema bilaterally to the shins.
The patient's chest-x ray is shown below.
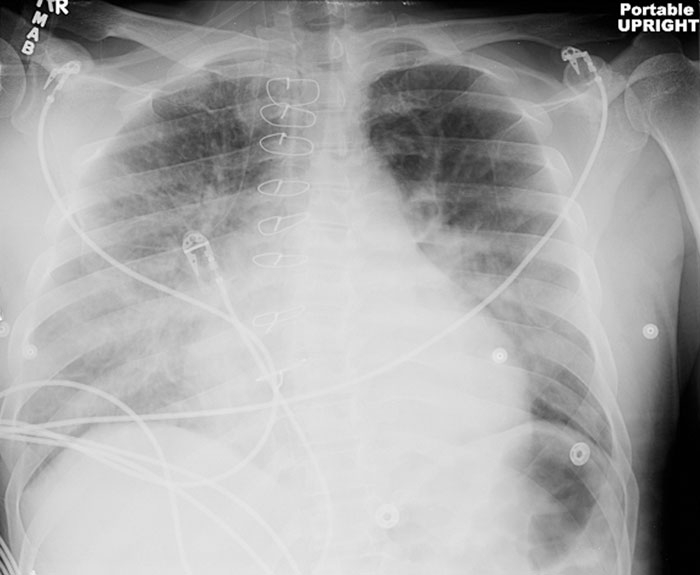 ECG shows sinus tachycardia with nonspecific T-wave changes.
Which of the following best describes how noninvasive positive pressure would benefit this patient?
ECG shows sinus tachycardia with nonspecific T-wave changes.
Which of the following best describes how noninvasive positive pressure would benefit this patient? (Multiple Choice)
4.8/5 (67)
(67) A 22-year-old woman is brought to the emergency department with confusion after a tonic-clonic seizure. She has no prior history of seizures, headaches, or recent febrile illness. The patient has suffered from recurrent nosebleeds for years with several visits to urgent care clinics for nasal packing. She takes no medications.
The patient's blood pressure is 134/85 mm Hg and pulse is 98/min. She has no meningeal signs and moves all her extremities. Deep-tendon reflexes are 2+ bilaterally.
Laboratory results are as follows:
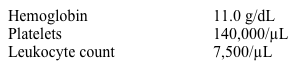 Additional physical examination findings are shown in the photograph below.
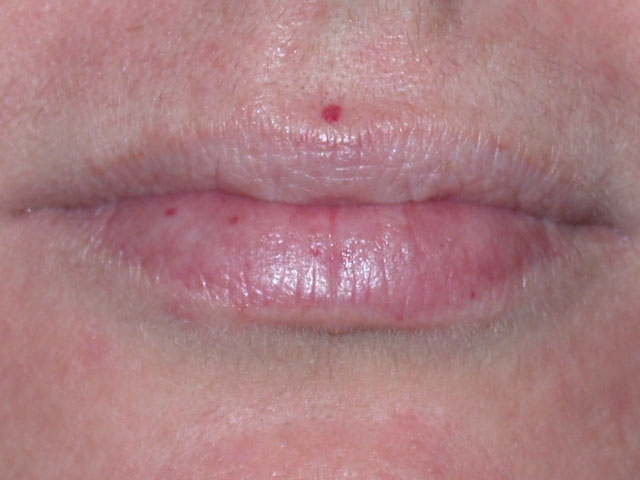 Which of the following is the most likely diagnosis?
Additional physical examination findings are shown in the photograph below.
Which of the following is the most likely diagnosis? (Multiple Choice)
4.9/5 (73)
(73) A 72-year-old woman is sent to the hospital after 2 days of agitation and combative behavior. The patient has Alzheimer dementia and lives in a skilled nursing facility. The nursing staff at the facility report that she is calm at baseline and spends most of her time in bed or in a wheelchair. She is normally minimally interactive with staff members but reportedly brightens when her son comes to visit. The patient has a history of generalized anxiety disorder but is currently not taking any medications for it.
In the emergency department, the patient is anxious and agitated. She is disoriented to place and time and frequently tries to get out of bed. She intermittently mumbles to herself and accuses the nurse of stealing her handbag. Urinalysis is both leukocyte esterase and nitrite positive and contains 100 white blood cells/high-power field. A urine culture has been sent to the laboratory.
In addition to empiric antibiotics for urinary tract infection, which of the following is the most appropriate management for this patient?
(Multiple Choice)
4.9/5 (83)
(83) A 70-year-old woman is admitted to the hospital with a fractured hip after a fall.
Laboratory results are as follows:
 Which of the following medications is most likely responsible for her acid-base abnormality?
 (Multiple Choice)
4.8/5 (67)
(67) A 76-year-old woman comes to the emergency department due to fatigue, nausea, and abdominal pain for the past 2 weeks. She feels weak and has not been eating much. She also has "black spots" in her vision when she watches television. Medical history includes hypertension, type 2 diabetes mellitus, persistent atrial fibrillation, myocardial infarction with coronary artery bypass grafting 10 years ago, and ischemic cardiomyopathy with an ejection fraction of 30%. The patient was hospitalized 6 months ago with an episode of decompensated heart failure but has had no recent illnesses. Medications include aspirin, furosemide, valsartan, carvedilol, atorvastatin, spironolactone, digoxin, warfarin, and insulin.
Temperature is 36.7 C (98 F), blood pressure is 120/74 mm Hg, and pulse is 50/min. Mucous membranes are dry and the neck veins are flat. The lungs are clear to auscultation. Heart sounds are regular with a faint ejection systolic murmur present over the aortic area. The abdomen is soft with mild, diffuse tenderness over the epigastric area with deep palpation. Neurologic examination is unremarkable.
Laboratory results are as follows:
 ECG shows a regular narrow-complex rhythm at 48/min, no P waves, and occasional ventricular premature beats. While in the emergency department, the patient also has an asymptomatic 9-beat run of nonsustained ventricular tachycardia that resolves spontaneously.
Which of the following is the best treatment for this patient?
ECG shows a regular narrow-complex rhythm at 48/min, no P waves, and occasional ventricular premature beats. While in the emergency department, the patient also has an asymptomatic 9-beat run of nonsustained ventricular tachycardia that resolves spontaneously.
Which of the following is the best treatment for this patient? (Multiple Choice)
4.9/5 (75)
(75) A 79-year-old man is found poorly responsive in his apartment by a neighbor in the middle of July. The apartment is not air conditioned and the last few days have been extremely hot. The patient's neighbors state that he lives alone and appeared fully functional in their interactions with him. No additional medical history is available.
On physical examination, he appears obtunded and responds slowly to commands. His temperature is 42.2° C (108° F), blood pressure is 90/60 mm Hg, pulse is 104/min, and respirations are 16/min. The patient's pulse oximetry shows 96% on room air. Mucous membranes are dry. His neck is supple, and jugular veins are flat in the supine position. Cardiopulmonary examination is within normal limits. There are no skin rashes. Deep tendon reflexes are 2+ and symmetrical. There is no muscular rigidity.
An electrocardiogram demonstrates sinus rhythm with nonspecific ST-segment changes. A chest film shows no significant abnormalities. Laboratory workup is pending.
In addition to volume resuscitation, which of the following is the best initial therapy for this patient?
(Multiple Choice)
4.8/5 (67)
(67) A 39-year-old man is admitted to the hospital for acute alcoholic pancreatitis. His initial APACHE II score was 20, suggestive of severe disease. Within the first 48 hours, he received a total of 10 liters of intravenous fluid resuscitation. Because of decreasing oxygenation, he was intubated and started on mechanical ventilation. Due to increased oxygen requirements, both PEEP and FiO2 were progressively increased. Over the past 12 hours, his urine output decreased and his serum creatinine increased from 1.2 mg/dL at admission to 2.2 mg/dL at present.
His blood pressure is 110/70 mm Hg and pulse is 98/min. Jugular venous pressure is elevated. Lung examination reveals bilateral crackles at the lung bases. His abdomen is diffusely tender and tensely distended. Bowel sounds are diminished. There are no flank or periumbilical ecchymoses. There is 3+ pitting edema to mid-thighs bilaterally.
Urinalysis results are as follows:
 Which of the following would most likely establish the cause of the acute kidney injury?
 (Multiple Choice)
5.0/5 (91)
(91) A 47-year-old man with known HIV infection is admitted for shortness of breath and non-productive cough. He has not been adherent with his medications and has not received medical attention for two years. His other medical problems include hepatitis C, lower extremity neuropathy, and tonic-clonic seizures. His last seizure episode was 7 years ago. He receives 2 L of intravenous normal saline in the emergency department and is started on trimethoprim-sulfamethoxazole and prednisone for presumed pneumocystis pneumonia.
Forty-eight hours later, his serum creatinine increased from 1.3 to 1.6 mg/dL.
His temperature is 37.8 C (100 F), blood pressure is 102/70 mm Hg supine and 105/68 mm Hg standing, and pulse is 112/min. He has crackles in both posterior lung bases. His liver is palpated 2 cm below the costal margin. There is no peripheral edema.
Urinalysis results are shown below:
 Which of the following is the most likely cause of his elevated creatinine?
 (Multiple Choice)
4.7/5 (94)
(94) A 48-year-old man is admitted to the hospital for recurrent, diffuse abdominal pain. The pain has occurred intermittently for the past 8 months and is worse after eating. Four months ago, the patient underwent emergency laparoscopic surgery with resection of necrotic gallbladder and omental tissue, but he continued to have symptoms. In addition, the patient has experienced intermittent testicular pain and a 13.7-kg (30-lb) weight loss since the onset of symptoms. Medical history is notable for chronic hepatitis B, exercise-induced asthma, acid reflux disease, and renal stones. The patient has a 25-pack-year smoking history and drinks alcohol occasionally. His medications include an albuterol inhaler and omeprazole as needed.
Temperature is 38 C (100.5 F), blood pressure is 180/100 mm Hg, pulse is 78/min, and respirations are 12/min. On examination, the patient appears anxious and diaphoretic. Cardiopulmonary examination is normal. Abdominal palpation elicits diffuse tenderness without any rebound or guarding. Bowel sounds are present. No abdominal masses are palpable, and the stool is negative on guaiac testing. The right testicle appears swollen and tender. There are no skin rashes.
Laboratory results show normal serum chemistry, liver function studies, and complete blood count. Other study results are as follows:
 Blood cultures, urinalysis, and urine culture are normal. Chest x-ray and ECG are also normal.
Which of the following is the most likely diagnosis?
Blood cultures, urinalysis, and urine culture are normal. Chest x-ray and ECG are also normal.
Which of the following is the most likely diagnosis? (Multiple Choice)
4.9/5 (75)
(75) A 55-year-old woman is hospitalized for shortness of breath, productive cough, and pleuritic chest pain. Her medical problems include major depression and schizophrenia, and her medications are unknown. In the emergency department, her trachea is intubated due to respiratory distress, a right internal jugular catheter is placed, and normal saline is administered as repeat boluses.
In the intensive care unit, her temperature is 38.9 C (102 F), blood pressure is 85/42 mm Hg, and pulse is 115/min. The patient's pulse oximetry shows 90% on assist-control mode with a respiratory rate of 16/min, tidal volumes of 470 mL, fraction of inspired oxygen of 70%, and positive end-expiratory pressure of 10 cm H20. Examination shows bibasilar crackles and normal first and second heart sounds. The abdomen is soft and nontender. There is no peripheral edema. The extremities are warm to the touch with faint pulses. Mean central venous pressure is 14 mm Hg.
Laboratory results are as follows:
 Chest x-ray shows bilateral diffuse alveolar opacities.
Which of the following interventions is the best next step in management of this patient?
Chest x-ray shows bilateral diffuse alveolar opacities.
Which of the following interventions is the best next step in management of this patient? (Multiple Choice)
5.0/5 (89)
(89) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)