



 Chat with AI
Exam 2: In-patient Facilities

Exam 1: Emergency Department218 Questions
Exam 2: In-patient Facilities128 Questions
Exam 3: Office/Health Center900 Questions
Select questions type


A 61-year-old man with a history of coronary artery disease, hypertension, and chronic obstructive pulmonary disease is evaluated for persistent fever in the cardiac intensive care unit. He underwent coronary artery bypass grafting (CABG) six days ago. He has been receiving mechanical ventilation, and is unable to be weaned off the ventilator. Four days after his surgery, he developed fever, increased oxygen requirements, and abundant secretions from the endotracheal tube. He was started on intravenous piperacillin-tazobactam.
His current temperature is 38.9 C (102 F), blood pressure is 124/84 mm Hg, pulse is 96/min, respirations are 18/min, and oxygen saturation is 90% on 60% FiO2 and 5 mm Hg of PEEP.
Laboratory results are as follows:
 Chest x-ray shows a dense right lower lobe infiltrate. Blood cultures sent two days ago return negative.
Which of the following is the best additional therapy for this patient?
Chest x-ray shows a dense right lower lobe infiltrate. Blood cultures sent two days ago return negative.
Which of the following is the best additional therapy for this patient? (Multiple Choice)
5.0/5  (84)
(84) A 32-year-old African American man is admitted to the hospital due to dizziness. For the past 2 weeks he has had decreased appetite, nausea, dry cough, constipation, and excessive urination. He has had no fever or night sweats and was in good health prior to these symptoms. The patient has no other medical problems and takes no medications. He has 10-pack-year history of smoking. He admits to drinking a few beers on weekends but does not use illicit drugs.
His blood pressure is 110/70 mm Hg and pulse is 110/min. Lung examination shows normal breath sounds. The remainder of the examination is normal.
Laboratory results are as follows:
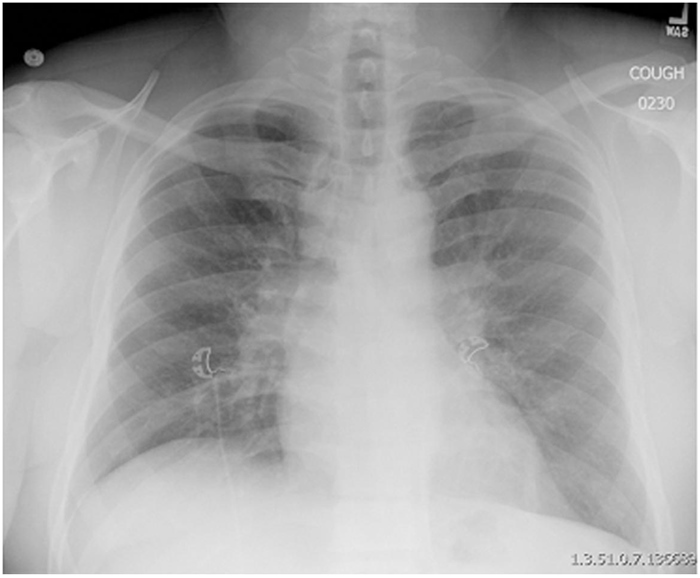
 Chest x-ray is shown below.
 In addition to intravenous fluids, which of the following medications is most appropriate for this patient?
Chest x-ray is shown below.
In addition to intravenous fluids, which of the following medications is most appropriate for this patient? (Multiple Choice)
4.9/5 (86)
(86) A 69-year-old man is admitted to the hospital due to 2 days of high fevers, chills, headache, nausea, and diarrhea. He has also had intermittent abdominal pain associated with 4 nonbloody bowel movements over the past 24 hours. The patient has a history of rheumatoid arthritis and takes infliximab and hydroxychloroquine. He lives with his wife in Florida and has had no sick contacts or recent travel outside of the state. He is the primary caretaker of a domesticated bird.
Temperature is 39.4 C (103 F), blood pressure is 118/80 mm Hg, pulse is 112/min, and respirations are 16/min. The patient is ill-appearing. Pulmonary examination is normal. Bowel sounds are hyperactive, and the abdomen is soft and mildly tender. Neurological examination shows no focal abnormalities.
Laboratory results are as follows:
 Chest x-ray reveals no focal infiltrate. Intravenous empiric antibiotics and fluids are administered. Blood cultures sent on admission grow Gram-positive rods in all 4 bottles after 12 hours.
Which of the following is the most likely etiology of this patient's illness?
Chest x-ray reveals no focal infiltrate. Intravenous empiric antibiotics and fluids are administered. Blood cultures sent on admission grow Gram-positive rods in all 4 bottles after 12 hours.
Which of the following is the most likely etiology of this patient's illness? (Multiple Choice)
4.9/5 (66)
(66) A 65-year-old woman comes to the emergency department due to worsening cough and difficulty breathing. The patient had similar symptoms a month ago and was found to have right-sided pneumonia. The symptoms resolved with antibiotic treatment but recurred 2 days ago. During the previous hospitalization, the patient also reported progressive muscle weakness and fatigue of several months' duration. She subsequently underwent muscle biopsy, which revealed dermatomyositis; oral prednisone therapy was initiated 2 weeks ago. She still has significant muscle weakness. The patient also has had poor oral intake and frequent coughing while eating, and has lost 6.8 kg (15 lb) over the last 3 months. The patient feels mildly depressed but has had no suicidal ideation. She is a lifelong nonsmoker and does not drink alcohol.
Temperature is 38.6 C (101.5 F), blood pressure is 122/78 mm Hg, pulse is 89/min, and respirations are 20/min. Bronchial breath sounds and rhonchi are present over the right lung base. Muscle strength is moderately decreased in the proximal muscles. There is a scaly skin rash over the extensor surfaces of both hands.
Laboratory results are as follows:
 Chest x-ray shows a right lower lobe lung infiltrate.
Which of the following is most likely responsible for this patient's pulmonary symptoms?
Chest x-ray shows a right lower lobe lung infiltrate.
Which of the following is most likely responsible for this patient's pulmonary symptoms? (Multiple Choice)
4.8/5 (82)
(82) An 83-year-old man with mild cognitive impairment is transported from an assisted living facility with a 2-day history of abdominal pain and decreased oral intake. He has no vomiting, fever, or urinary symptoms. He underwent coronary artery bypass grafting 6 years ago. The patient also had a stent placed in his superficial femoral artery 3 years ago for claudication due to peripheral artery disease.
His temperature is 37.3° C (99.2° F), blood pressure is 127/77 mm Hg, and pulse is 102/min. He appears uncomfortable. Examination shows dry membranes. The abdomen is distended, diffusely tender, and tympanic to percussion. There is no rebound tenderness or rigidity.
Laboratory results are as follows:
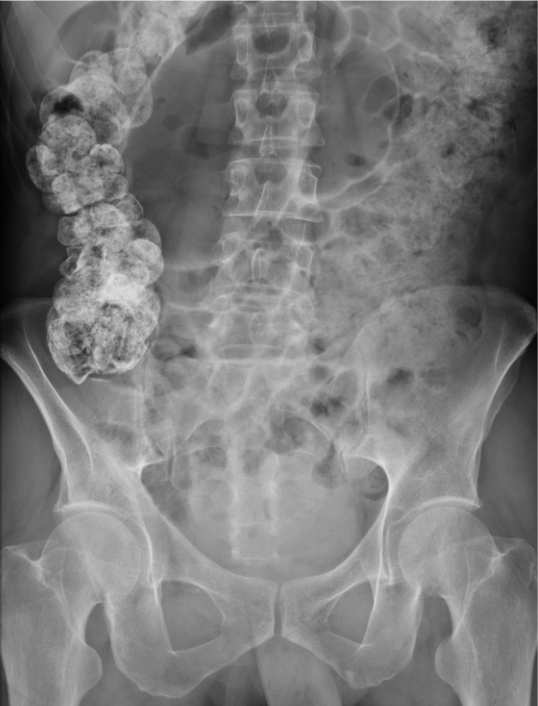
 Contrast abdominal imaging, shown below, reveals a large, air-filled sigmoid colon with absence of air in the rectum.
 Which of the following is the best next step in managing this patient?
Contrast abdominal imaging, shown below, reveals a large, air-filled sigmoid colon with absence of air in the rectum.
Which of the following is the best next step in managing this patient? (Multiple Choice)
4.8/5 (61)
(61) A 62-year-old woman comes to the emergency department with a 2-week history of palpitations and mild shortness of breath. The patient has a history of hypertension and type 2 diabetes mellitus. She is a lifetime nonsmoker and has no family history of heart disease. Blood pressure is 144/70 mm Hg and pulse is 145/min and irregular. Oxygen saturation is 95% on room air. Lung examination reveals minimal rales at both bases. There are no heart murmurs.
ECG shows atrial fibrillation with rapid ventricular response. Transthoracic echocardiogram shows mild left atrial dilation and a diffusely hypokinetic left ventricle with an ejection fraction of 40%. Chemistry panel, serial troponin I, and TSH levels are normal.
The patient is treated with metoprolol and anticoagulation. On the third day of hospitalization, despite increasing doses of metoprolol, she still has palpitations. Blood pressure is 128/67 mm Hg, and pulse is 122/min and irregular.
Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (81)
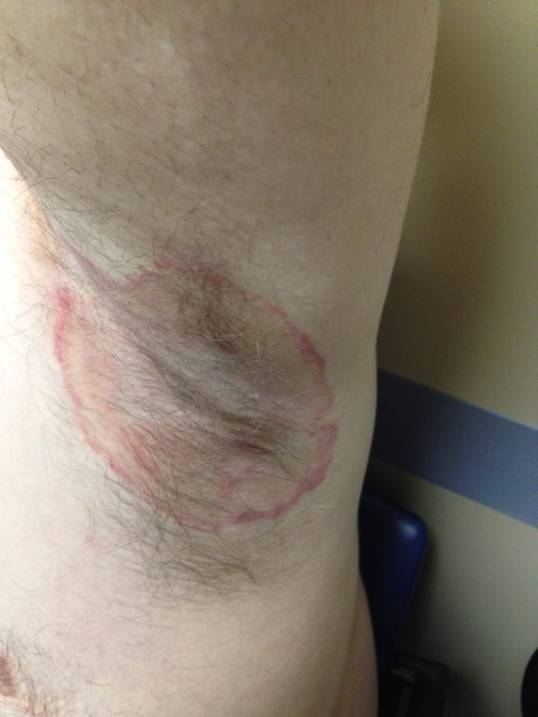
(81) A 55-year-old man comes to the physician with an intensely pruritic rash under his left arm. He has used an old prescription of 1% triamcinolone cream for the past 2 weeks without relief and believes that the rash is expanding. The patient was diagnosed with Sjögren's syndrome 6 months ago when he developed dry eyes, dry mouth, and positive anti-SS-A and anti-SS-B antibodies. Labial salivary gland biopsy at that time showed lymphocytic infiltration of salivary glands, confirming the diagnosis. He was treated with hydroxychloroquine, topical moisturizing eye drops, and artificial saliva. His other medical problems include type 2 diabetes mellitus, which has been well controlled with metformin. Physical examination findings are shown in the image below.
 Complete blood count and comprehensive metabolic panel are unremarkable. His hemoglobin A1C is 6.1%.
After confirming the diagnosis, which of the following is the most appropriate next step in management of this patient?
Complete blood count and comprehensive metabolic panel are unremarkable. His hemoglobin A1C is 6.1%.
After confirming the diagnosis, which of the following is the most appropriate next step in management of this patient? (Multiple Choice)
4.7/5 (76)
(76) A 65-year-old woman with a history of chronic obstructive pulmonary disease (COPD) is brought to the intensive care unit after being intubated for respiratory failure. She initially presented to the emergency department with severe respiratory distress, fever, chills, and productive cough. She smokes 1 pack of cigarettes per day and has been intubated in the past for COPD exacerbation. Her other medical problems include hypertension, coronary artery disease, congestive heart failure, and colonic diverticulosis. She has no history of diabetes mellitus.
Her leukocyte count is 15,000 cells/µL and her serum creatinine is 1.2 mg/dL. Liver function tests are within normal limits. Chest x-ray shows bilateral lower lobe infiltrates. She is started on high-dose methylprednisolone, inhaled bronchodilators, and antibiotics. Over the following 12 hours, her fingerstick blood glucose levels ranged from 210 to 280 mg/dL.
Which of the following is the most appropriate next step in management?
(Multiple Choice)
4.9/5 (73)
(73) A 58-year-old man with a history of chronic obstructive pulmonary disease develops acute respiratory distress syndrome secondary to community-acquired pneumonia. He has been stable on mechanical ventilation with peak and plateau pressures <30 cm H2O, and his oxygen requirements have decreased over the past 2 days.
On his third day in the intensive care unit, he is ventilated on assist control mode, with a respiratory rate of 16/min, positive end-expiratory pressure of 10 cm H2O, and FiO2 of 0.6 (60%). The patient's peak pressure ventilator alarm has been on for the past 10 minutes and his respirations appear more labored. Pulse has increased from 85 to 120/min, and respiratory rate has increased from 16 to 32/min. The peak pressure is 44 cm H2O and the plateau pressure is 24 cm H2O. On chest auscultation, breath sounds are coarse and mildly decreased on the left side.
Which of the following actions would be most likely to improve the patient's current symptoms?
(Multiple Choice)
4.8/5 (85)
(85) A 64-year-old man hospitalized with acute myocardial infarction 3 days ago has chest pain that is worse on deep inspiration and radiates to the trapezius ridge. He underwent cardiac catheterization on admission and was found to have occlusion of the distal left anterior descending artery that could not be revascularized. He was treated with low-dose aspirin, clopidogrel, atorvastatin, metoprolol, and valsartan.
Physical examination shows a friction rub at the lower left sternal border.
Echocardiogram shows apical hypokinesis, left ventricular ejection fraction of 50%, and trivial pericardial effusion.
Which of the following is the best management for this patient?
(Multiple Choice)
4.9/5 (88)
(88) A 36-year-old man is brought to the emergency department after waking up with dyspnea, nonproductive cough, fever, and malaise. He had been feeling well prior to these symptoms and has no chronic medical problems. The patient and his wife are on vacation in Florida and are staying in an "old and dusty" rental house. Last night they went to a bar and then relaxed in a hot tub.
Temperature is 38.9 C (102 F), blood pressure is 144/89 mm Hg, and pulse is 104/min. Pulse oximetry is 89% on room air. Chest examination reveals bilateral fine crackles. There are no skin rashes.
Laboratory results are as follows:
 Liver function tests are normal. Chest x-ray reveals mildly increased interstitial markings in the middle and lower lung fields bilaterally.
Which of the following is most likely responsible for this patient's current symptoms?
Liver function tests are normal. Chest x-ray reveals mildly increased interstitial markings in the middle and lower lung fields bilaterally.
Which of the following is most likely responsible for this patient's current symptoms? (Multiple Choice)
4.8/5 (68)
(68) A 55-year-old man with chronic alcohol abuse underwent right-sided hemicolectomy for complicated diverticulitis 10 days ago. During his hospitalization, he developed abdominal wall hematomas at subcutaneous heparin injection sites. His preoperative laboratory blood work showed a hemoglobin of 5.4 g/dL, platelets of 87,000/µL, and normal coagulation parameters. The patient received 8 units of packed red blood cells during the perioperative period. His hospital course has been complicated by an abdominal wound infection and alcohol withdrawal symptoms.
His temperature is 38.1 C (100.6 F), blood pressure is 98/56 mm Hg, and pulse is 108/min. His body mass index is 18 kg/m2. The lungs are clear to auscultation and no murmurs are appreciated. The incision site is erythematous and tender. The patient has a palpable spleen tip. There is no evidence of active mucosal bleeding. His mental status is normal.
Laboratory results are as follows:
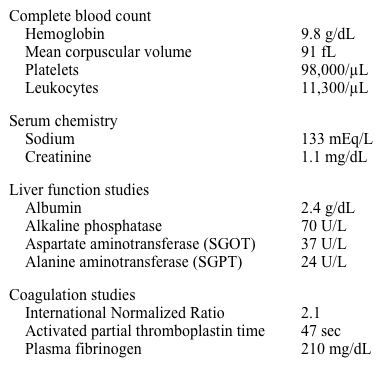 Factor V and VIII levels are normal, and factor VII level is decreased.
Which of the following is the most likely cause of this patient's coagulopathy?
Factor V and VIII levels are normal, and factor VII level is decreased.
Which of the following is the most likely cause of this patient's coagulopathy? (Multiple Choice)
5.0/5 (86)
(86) A 79-year-old nursing home resident is admitted to the hospital for nausea, vomiting, and abdominal distension. He has had little oral intake over the last 48 hours. This morning, workers at his facility noticed that his abdomen was distended. The patient's medical history is remarkable for advanced dementia, coronary artery disease, hypertension, cerebrovascular accident, atrial fibrillation with rapid ventricular response, chronic low back pain, and gastroesophageal reflux disease. Medications include aspirin, furosemide, hydrocodone with acetaminophen, metoprolol, calcium, vitamin D, simvastatin, and omeprazole. He was hospitalized for a myocardial infarction 3 months ago.
The patient's temperature is 36.7 C (98 F), blood pressure is 131/78 mm Hg, pulse is 98/min, and respirations are 18/min. Pulse oximetry shows an oxygen saturation of 98% on room air. BMI is 22 kg/m2. Lungs are clear to auscultation. The abdomen is distended and nontender. Bowel sounds are present with increased tympany to percussion throughout.
Laboratory results are as follows:
 Abdominal radiograph reveals marked dilation of the cecum, right hemicolon, and transverse colon with a maximal colonic diameter of 11.3 cm. Abdominal CT scan confirms colonic dilation with no evidence of mechanical obstruction or bowel wall thickening.
Intravenous fluids are administered along with potassium and magnesium supplementation.
Which of the following is the best initial management for this patient?
Abdominal radiograph reveals marked dilation of the cecum, right hemicolon, and transverse colon with a maximal colonic diameter of 11.3 cm. Abdominal CT scan confirms colonic dilation with no evidence of mechanical obstruction or bowel wall thickening.
Intravenous fluids are administered along with potassium and magnesium supplementation.
Which of the following is the best initial management for this patient? (Multiple Choice)
4.9/5 (80)
(80) An 89-year-old man is hospitalized because of upper GI bleeding. He presented two days ago with hematemesis, black stools, and lethargy. His trachea was intubated for airway protection in the emergency department. An endoscopy was performed and showed a deep ulcer with a bleeding vessel in the gastric antrum. Hemostasis was achieved with epinephrine injection, cauterization, and endoclips. He received 8 units of packed red blood cells and has not required additional transfusions for the past 24 hours. His other medical problems include hypertension, chronic kidney disease, hypothyroidism, and colon cancer requiring colectomy and adjuvant chemotherapy 9 years ago.
The patient undergoes a spontaneous breathing trial in the intensive care unit. After two hours of 5 cm H2O continuous positive airway pressure (CPAP), his temperature is 36.1 C (97 F), blood pressure is 110/60 mm Hg, pulse is 94/min, and respirations are 28/min. The patient's pulse oximetry shows 97% on 40% FiO2. His tidal volumes are 200 mL on average. He follows commands adequately. Examination reveals good air entry on both sides and bibasal crackles. No cardiac murmurs are appreciated. There is 2+ bilateral pretibial edema. Muscle strength is 5/5 in both upper and lower extremities.
Laboratory results are as follows:
 His chest-x ray shows bilateral airspace opacities.
Which of the following is the most appropriate next step in management?
His chest-x ray shows bilateral airspace opacities.
Which of the following is the most appropriate next step in management? (Multiple Choice)
4.8/5 (89)
(89) A 55-year-old construction worker is brought to the emergency department with sudden onset of diaphoresis and severe chest discomfort. His symptoms woke him up 3 hours earlier. On arrival, his blood pressure is 98/60 mm Hg, pulse is 86/min, and oxygen saturation is 98% on 3 L oxygen by nasal cannula. He has persistent chest discomfort, and his skin is cold and clammy. Neck veins are mildly distended. Lung fields are clear and cardiac examination is unremarkable. His initial EKG reveals 3-mm ST segment elevation in leads II, III, and aVF.
He is referred for emergency cardiac catheterization and is found to have an acute occlusion of the proximal right coronary artery. There is mild, diffuse coronary atherosclerosis present in the left coronary circulation. Left ventriculography reveals mild hypokinesis of the inferior wall with an LV ejection fraction of 55%. He undergoes primary percutaneous coronary intervention with a bare metal stent and has TIMI II flow restored at the end of the procedure. He is started on aspirin, prasugrel, atorvastatin, and intravenous eptifibatide and is transferred to the coronary care unit.
Thirty minutes later, his blood pressure drops to 80/54 mm Hg. He has minimal residual chest discomfort but no other symptoms. His physical examination is unchanged. An urgent EKG shows minimal, less than 1 mm, persistent ST-segment elevation along with small Q waves in inferior leads.
Which of the following is the next best step in management of this patient?
(Multiple Choice)
4.8/5 (92)
(92) A 75-year-old man comes to the emergency department with 6 hours of intermittent chest pain. He has no nausea, vomiting, syncope, shortness of breath, or diaphoresis. His medical problems include type 2 diabetes mellitus, hypertension, and hyperlipidemia.
The patient's blood pressure is 142/78 mm Hg and pulse is 82/min. Cardiac and pulmonary examinations are within normal limits.
Electrocardiogram shows normal sinus rhythm with 1.5-mm horizontal ST-segment depression in leads II, III, and aVF. Initial troponin I level is 2.2 ng/mL (normal <0.012 ng/mL).
The patient receives antiplatelet agents, nitroglycerin, and anticoagulation. He reports complete resolution of symptoms.
Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (69)
(69) A 63-year-old man with diabetes is hospitalized with right foot methicillin-resistant Staphylococcus aureus osteomyelitis complicated by sepsis and respiratory failure. He spends 3 days in the intensive care unit on mechanical ventilation but is now extubated and has resumed eating. He has generalized weakness, mild cough, and foot pain. The patient has no chest pain, abdominal pain, bleeding, or diarrhea. He has no prior history of pneumonia, heart failure, or coagulopathy. His current medications include intravenous vancomycin, subcutaneous heparin, short- and long-acting subcutaneous insulin, and omeprazole. His vital signs are within normal limits.
Laboratory values show hemoglobin of 12.2 g/dL, creatinine of 1.4 mg/dL, and albumin of 2.5 mg/dL. Coagulation profile is unremarkable.
Which of the following should be strongly considered when transferring this patient to the medical floor?
(Multiple Choice)
4.9/5 (71)
(71) A 63-year-old hospitalized woman develops severe shortness of breath that awakens her from sleep. She underwent elective right hip replacement for severe osteoarthritis 5 days ago. She has no history of coronary artery disease. She has received enoxaparin subcutaneously for deep vein thrombosis prophylaxis.
Her blood pressure is 78/50 mm Hg, pulse is 130/min, respirations are 34/min, and oxygen saturation is 70% on room air. Jugular venous distension is present. Her lungs are clear to auscultation. There are no murmurs. Her extremities are cold and clammy.
A 12-lead ECG shows sinus tachycardia. Portable chest x-ray is ordered and preparations are made for endotracheal intubation.
Which of the following is the most appropriate next step in management?
(Multiple Choice)
4.8/5 (78)
(78) A 72-year-old woman with a history of hypertension and coronary artery disease was admitted to the hospital 2 months ago with dizziness and palpitations. The patient was diagnosed with persistent atrial fibrillation but has been doing well since. She takes 20-minute walks on most days of the week for exercise with no chest pain or shortness of breath.
The patient had coronary artery bypass graft surgery 7 years ago for stable angina and also has gastroesophageal reflux disease, right knee osteoarthritis, and chronic constipation. Her current medications include aspirin, metoprolol, digoxin, simvastatin, warfarin, and valsartan. She also takes antacids frequently for heartburn and upper abdominal discomfort.
Her blood pressure is 146/80 mm Hg, and pulse is 76/min and irregularly irregular. BMI is 31 kg/m2. A faint ejection-type systolic murmur is heard at the right upper sternal border. Her peripheral pulses are 2+ and there is trace edema in the leg with the vein harvest scar.
Laboratory results are as follows:
 Her last echocardiogram showed normal left ventricular systolic function and mild mitral regurgitation.
Compared to warfarin, dabigatran has a lower risk of which of the following?
Her last echocardiogram showed normal left ventricular systolic function and mild mitral regurgitation.
Compared to warfarin, dabigatran has a lower risk of which of the following? (Multiple Choice)
4.7/5 (97)
(97) A 54-year-old man is hospitalized due to progressive dyspnea on exertion and orthopnea. Evaluation reveals jugular venous distension, bibasilar crackles, and pitting edema of the bilateral lower extremities. Echocardiography shows decreased left ventricular contractility with an ejection fraction of 30%. Coronary angiography reveals no obstructive coronary artery disease. Symptoms gradually improve with intravenous furosemide. On the fourth day of hospitalization, the patient begins to experience severe right foot and ankle pain. The pain started suddenly during the night with no antecedent trauma. He had an episode of right knee pain several years ago, which improved with over-the-counter analgesics. The patient has a history of hypertension and HIV. CD4+ cell count was 450/mm3 2 months ago. Antiretroviral therapy has been continued since admission.
Temperature is 38 C (100.4 F). Examination shows redness, warmth, tenderness, and decreased range of motion in the right ankle and midfoot. There is no skin rash.
Leukocyte count is 13,200 cells/mm3 and serum creatinine is 1.0 mg/dL. Radiography of the right foot and ankle shows no fracture or dislocation, but significant soft tissue swelling and a heel spur are seen.
Which of the following is most likely contributing to this patient's foot pain?
(Multiple Choice)
4.8/5 (93)
(93) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)