



 Chat with AI
Exam 1: Emergency Department

Exam 1: Emergency Department218 Questions
Exam 2: In-patient Facilities128 Questions
Exam 3: Office/Health Center900 Questions
Select questions type


A 45-year-old homeless man is found unresponsive on the street and brought to the emergency department. The ambient temperature outside is -6.7 C (20 F). He has no evidence of trauma and no other medical history is available.
The patient's blood pressure is 88/60 mm Hg, pulse is 60/min, and respirations are 22/min. Rectal temperature is 29 C (84.2 F). He is cold to the touch, responds only to deep pain, and is not shivering. Cardiopulmonary and abdominal examinations are within normal limits.
ECG shows atrial fibrillation with a slow ventricular response. The patient is intubated in the emergency department and blood work, including blood cultures, is sent. A chest x-ray is ordered.
In addition to passive and active external rewarming and general supportive care, which of the following is the most appropriate therapy for the patient at this time?
(Multiple Choice)
4.8/5  (81)
(81) A 33-year-old man with a history of asthma and chronic rhinosinusitis comes to the emergency department complaining of shortness of breath. He developed an upper respiratory infection 3 days earlier and woke today with increased sinus headache and mild dyspnea. He started diphenhydramine, albuterol, and ibuprofen. He also took his normal dose of fluticasone/salmeterol 250/50 and nasal fluticasone but became increasingly dyspneic over the next 3 hours. He has had sinus surgery twice (most recently last year) and removal of nasal polyps 2 years ago.
The patient is in mild respiratory distress. His pulse is 115/min, respirations are 23/min, and pulse oximetry is 98% on 2L oxygen by nasal canula. Examination reveals significant rhinorrhea, diffuse bilateral wheezes, conjunctival injection, and facial erythema. He is given methylprednisolone and albuterol nebulizer treatments, with improvement of his symptoms over the next 24 hours.
In addition to tapering doses of prednisone, which of the following would most likely benefit this patient?
(Multiple Choice)
4.9/5 (74)
(74) A 36-year-old woman comes to the emergency department due to right lower leg pain and ankle edema. Her symptoms began 2 days ago after a 14-hour flight from India. The patient has had no leg trauma, fever, chest pain, or shortness of breath. She has a history of asthma and takes inhaled albuterol as needed. The patient has no family history of blood clots.
Temperature is 36.8 C (98.2 F), blood pressure is 142/72 mm Hg, pulse is 98/min, and respirations are 16/min. BMI is 26 kg/m2. Cardiopulmonary examination shows no abnormalities. There is 2+ right lower extremity pitting edema extending to the mid-calf, and right foot dorsiflexion results in right calf pain. Left lower extremity examination is normal. Stool guaiac is negative. Laboratory results are as follows:
 Compression ultrasonography of the right lower extremity shows no evidence of deep venous thrombosis. D-dimer is 65 µg/mL (normal: <0.5).
Which of the following is the most appropriate next step in management of this patient?
Compression ultrasonography of the right lower extremity shows no evidence of deep venous thrombosis. D-dimer is 65 µg/mL (normal: <0.5).
Which of the following is the most appropriate next step in management of this patient? (Multiple Choice)
4.9/5 (75)
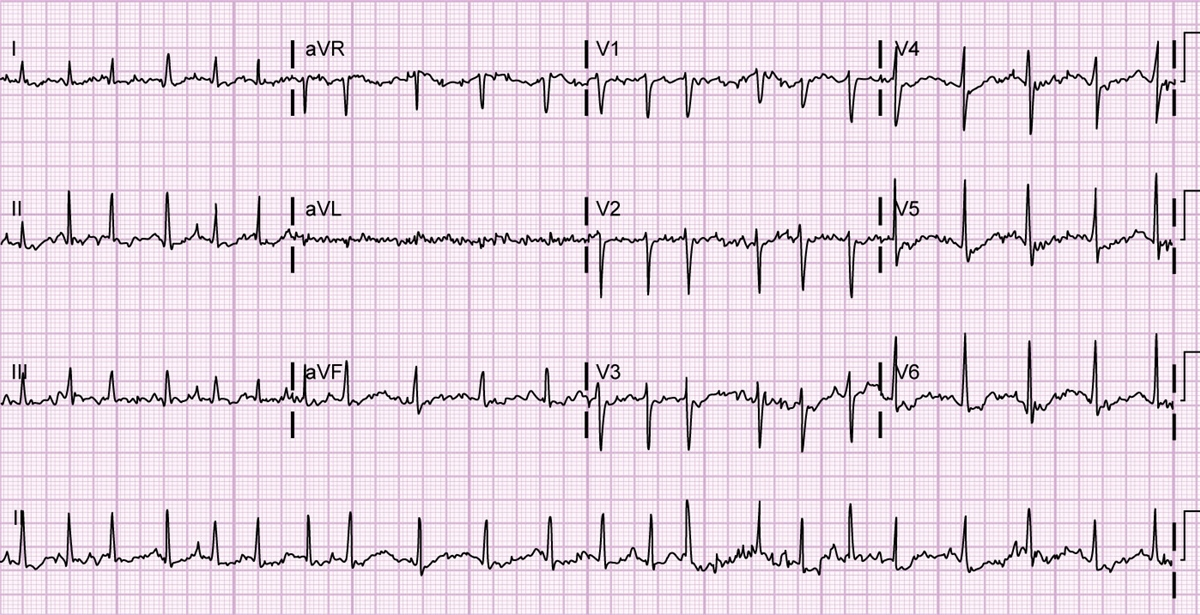
(75) A 72-year-old man is brought to the emergency department due to 3 days of worsening cough and shortness of breath. The cough is productive of a small amount of white sputum. The patient has no chest pain. He has a history of hypertension, gout, chronic obstructive pulmonary disease, and coronary artery disease for which he underwent coronary artery bypass grafting. He also had mitral valve repair 6 years ago. The patient has a 40-pack-year smoking history and continues to smoke a pack of cigarettes a day.
Blood pressure is 136/72 mm Hg, pulse is 132/min, and respirations are 26/min. Oxygen saturation is 92% on room air. The patient appears to be in moderate respiratory distress. Jugular venous pulse is difficult to measure due to use of accessory muscles. Lung auscultation shows decreased air entry in both lung fields. There is diffuse and scattered wheezing heard throughout the lung zones. Heart sounds are irregular with a faint holosystolic murmur heard over the cardiac apex. There is 1+ bilateral pitting ankle edema.
Laboratory results are as follows:
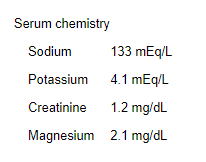 ECG is shown in the exhibit.
 Which of the following is the best treatment for this patient's cardiac condition?
ECG is shown in the exhibit.
Which of the following is the best treatment for this patient's cardiac condition? (Multiple Choice)
4.7/5 (67)
(67) A 60-year-old woman is brought to the emergency department after an episode of syncope. She also has generalized weakness and mild nausea. The patient was recently hospitalized for acute decompensated heart failure, and her left ventricular ejection fraction was estimated at 35% by echocardiography. Her discharge medications include furosemide, carvedilol, lisinopril, aspirin, and atorvastatin. At her outpatient visit a week ago, her lisinopril dose was increased and she was started on spironolactone.
Her temperature is 36.8 C (98.2 F), blood pressure is 120/82 mm Hg, pulse is 74/min, and respirations are 16/min. Pulse oximetry is 95% on room air. Jugular venous pressure is 8 cm H2O. Scattered bibasilar crackles are present. The patient has a grade 2/6 systolic ejection murmur along the right sternal border without radiation. She has 1+ pedal edema to the knees bilaterally.
Her ECG shows no P waves and a wide complex regular rhythm at 74/min. ECG done a week ago showed normal sinus rhythm, narrow QRS complexes (90 msec), and non-specific T wave abnormalities.
The patient would most likely benefit from which of the following?
(Multiple Choice)
4.9/5 (82)
(82) A 72-year-old man comes to the emergency department because of palpitations and shortness of breath for the past 24 hours. His medical problems include hypertension, hyperlipidemia, type 2 diabetes mellitus, obstructive sleep apnea, and emphysema. He uses 2 liters of oxygen only during the night. He cannot recall his medications, but uses an unknown daily inhaler for his "lung disease." He quit smoking 12 years ago.
His blood pressure is 132/54 mm Hg and pulse is 155/min. There is faint end expiratory wheezing noted over both lungs. No murmurs are appreciated. There is bilateral 1+ edema in his lower extremities.
An ECG is performed in the emergency department and is shown in this exhibit. 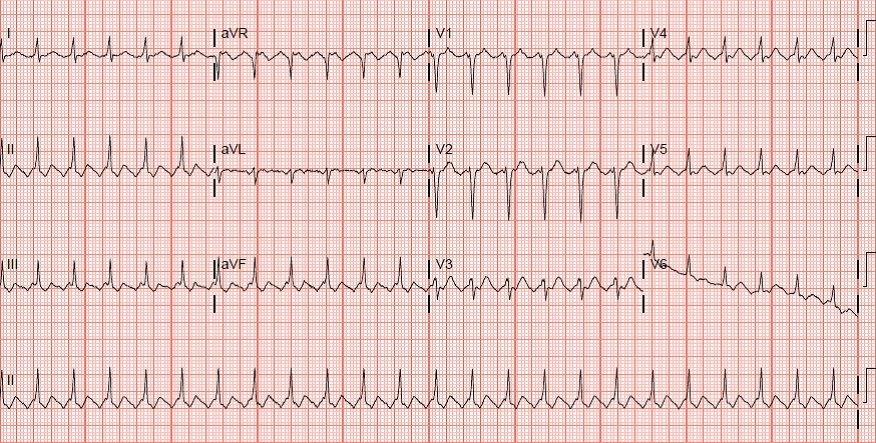 He is admitted to the hospital and started on a diltiazem infusion. The next morning, he continues to have a rapid pulse at 155/min. Transthoracic echocardiogram shows left atrial dilation, normal left ventricular systolic function, and an estimated pulmonary artery systolic pressure of 50 mm Hg.
Which of the following is the best management option for this patient?
He is admitted to the hospital and started on a diltiazem infusion. The next morning, he continues to have a rapid pulse at 155/min. Transthoracic echocardiogram shows left atrial dilation, normal left ventricular systolic function, and an estimated pulmonary artery systolic pressure of 50 mm Hg.
Which of the following is the best management option for this patient? (Multiple Choice)
4.7/5 (78)
(78) A 78-year-old woman is brought to the emergency department with left hip pain after a mechanical fall at home. Her medical history includes knee osteoarthritis, hypertension, hyperlipidemia, and a myocardial infarction requiring bare-metal stent placement 14 months earlier. Her medications include acetaminophen, low-dose aspirin, and simvastatin. She had previously been prescribed a beta blocker but stopped taking it a couple months ago due to fatigue. At baseline, she is able to eat, dress, and use the bathroom without assistance. The patient is able to walk up only half a flight of stairs before stopping due to knee pain. She has no chest pain, shortness of breath, or palpitations. She is a lifetime nonsmoker.
The patient appears comfortable after intravenous morphine injection. Blood pressure is 154/80 mm Hg and pulse is 64/min. Oxygen saturation is 96% on room air. Physical examination shows an externally rotated and shortened left leg. No murmurs are heard on cardiac auscultation. Lungs are clear to auscultation.
Laboratory results are as follows:
 ECG demonstrates normal sinus rhythm with Q waves in the inferior leads. X-ray of the left hip and pelvis demonstrates a displaced intertrochanteric fracture. Transthoracic echocardiogram obtained 6 months earlier reveals inferior wall hypokinesis, a left ventricular ejection fraction of 50%, evidence of mild diastolic dysfunction, and no major valvular abnormalities.
Which of the following is the most appropriate next step in management of this patient?
ECG demonstrates normal sinus rhythm with Q waves in the inferior leads. X-ray of the left hip and pelvis demonstrates a displaced intertrochanteric fracture. Transthoracic echocardiogram obtained 6 months earlier reveals inferior wall hypokinesis, a left ventricular ejection fraction of 50%, evidence of mild diastolic dysfunction, and no major valvular abnormalities.
Which of the following is the most appropriate next step in management of this patient? (Multiple Choice)
4.7/5 (69)
(69) A 60-year-old woman comes to the emergency department for acute onset of low back pain radiating down her left leg after lifting heavy boxes at home. She denies any muscle weakness and has no problems with bowel or bladder function. She states that her back pain worsens with coughing or bearing down. Her past medical history is significant for type 2 diabetes mellitus and hypertension. She recently received a flu shot which made her experience mild flu-like symptoms. She has smoked two packs of cigarettes daily for many years, but denies alcohol use.
Her temperature is 37 C (98.6 F), blood pressure is 140/90 mm Hg, and pulse is 90/min and regular. Neurological examination reveals 5/5 muscle strength in all four extremities with 2+ reflexes. Straight leg raise sign is positive on the left. Sensory examination reveals reduced pinprick and temperature sensation along the posterolateral region of the left leg.
Basic metabolic panel is normal. Plain radiograph of the lumbar spine shows only degenerative changes.
Which of the following is the most appropriate next step in management?
(Multiple Choice)
5.0/5 (78)
(78) An 18-year-old man comes to the emergency department due to retrosternal chest pain and pain with swallowing. The patient has a burning pain that began abruptly the previous morning and then gradually worsened. He has been limiting himself to soft foods as the pain is much worse with swallowing solids. The patient has a history of tension headaches that have become more frequent lately, which he attributes to long hours of studying for exams. His only medication is ibuprofen as needed for headaches, and he has no drug allergies. The patient's mother has Crohn disease. He drinks alcohol socially, smokes a half pack of cigarettes daily, and does not use illicit drugs. The patient is sexually active and uses condoms inconsistently.
Temperature is 36.7 C (98.1 F), blood pressure is 118/76 mm Hg, pulse is 88/min, and respirations are 14/min. There are no oropharyngeal lesions or palpable lymphadenopathy. The lung auscultation and cardiac examination are normal. The abdomen is soft without rebound or guarding.
Which of the following is the most appropriate next step in management of this patient's symptoms?
(Multiple Choice)
4.8/5 (84)
(84) A 48-year-old man comes to the emergency department due to the sudden onset of nausea, vomiting, and cramping abdominal pain. The patient has also had 2 episodes of watery diarrhea. The symptoms began 4 hours after eating at a buffet restaurant, and his sister, who had the same food, experienced similar symptoms. The patient was recently diagnosed with hemochromatosis and is receiving periodic phlebotomy.
Vital signs are within normal limits with no orthostatic changes. The abdomen is soft with mild, generalized tenderness. There is no guarding, rebound tenderness, or hepatosplenomegaly. Bowel sounds are increased.
Laboratory results are as follows:
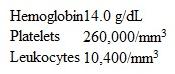 Which of the following is the most likely causative organism of this patient's current illness?
 (Multiple Choice)
4.8/5 (81)
(81) A 56-year-old woman comes to the emergency department with a two-day history of substernal chest pain and mild shortness of breath. She takes levothyroxine for hypothyroidism and alendronate for osteoporosis. She has been under a great deal of stress at her job lately because many of her co-workers were recently terminated. Her mother died from a stroke at the age of 65 and her father had a heart attack at the age of 67. She smokes a half-pack of cigarettes per day and drinks alcohol socially. She denies any illicit drug abuse.
Her blood pressure is 122/70 mm Hg and pulse is 100/min and regular. Her oxygen saturation is 98% on room air. Lungs are clear on auscultation.
An EKG shows deep T wave inversions in the anterior precordial leads. Her troponin I level is 2.2 ng/ml (normal < 0.012).
The patient is taken to cardiac catheterization, which shows no evidence of coronary artery disease. On left ventriculogram, the apex is non-contractile while the base is hypercontractile.
Which of the following is the most likely prognosis for this patient?
(Multiple Choice)
4.7/5 (72)
(72) A 72-year-old woman comes to the emergency department for a rash on her forehead. The rash has been present for 3 days and is getting worse. She also complains of moderate frontal headache, malaise, and fever. The patient has no neck pain, nausea, or vomiting. She has not had similar symptoms before. She is otherwise healthy and takes no medications.
Her temperature is 38.5 C (101.3 F). Her forehead is shown in the photograph below.
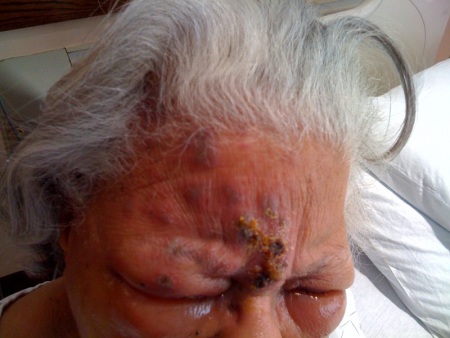 In addition to admission to the hospital and intravenous acyclovir, which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.9/5 (82)
(82) A 45-year-old man with known HIV infection comes to the emergency department due to a rash that began on his hands 4-5 weeks ago but then spread to involve his upper arms, shoulders, and ears. He has no fever, trauma, recent travel, or insect bites. He lives in a shelter and has poor medical follow-up. The patient was treated in the past for Candida esophagitis and Pneumocystis jirovecii pneumonia. His CD4+ cell count 6 months ago was 50/µL. His temperature is 36.7 C (98 F), blood pressure is 126/80 mm Hg, and pulse is 80/min. Photographs of the patient's skin examination are shown below.
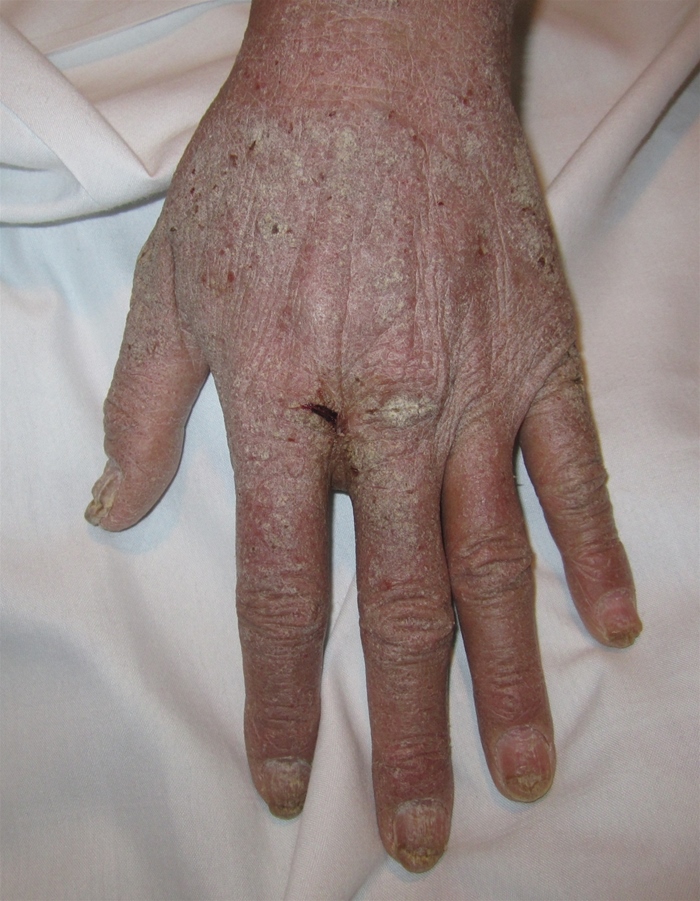
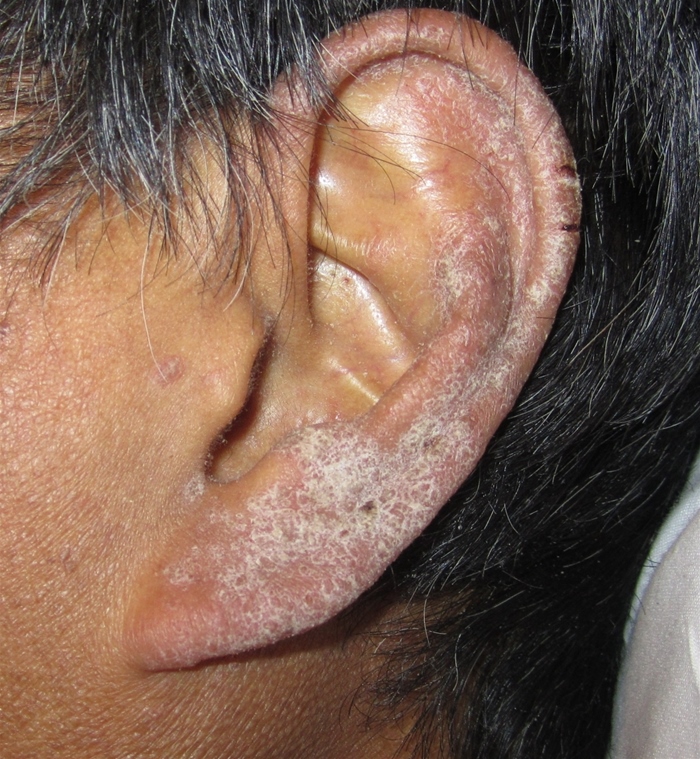 Which of the following is the most likely diagnosis?
 (Multiple Choice)
4.8/5 (85)
(85) A 76-year-old man is brought to the hospital due to a 1-day history of confusion. For the past 3 days, he has also had nasal congestion, sore throat, and a non-productive cough. Family members say that he has been acting strangely, asking the same questions repeatedly, talking to his deceased brother, and getting out of bed multiple times at night. The patient has a history of hypertension and benign prostate hyperplasia. His medications include amlodipine, tamsulosin, and over-the-counter cold medicine. He does not use tobacco, alcohol, or illicit drugs.
His temperature is 37.2 C (99 F), blood pressure is 140/80 mm Hg, and pulse is 92/min. On examination, the patient appears to be in distress and is disoriented. Moderate pharyngeal erythema without exudate is present. Cardiopulmonary examination is normal. The abdomen is soft with tenderness and a palpable mass in the suprapubic region. His prostate is enlarged and smooth. There is no neck rigidity and he moves all extremities with equal strength. Laboratory results are as follows:
 Which of the following is the most appropriate next step in management of this patient?
 (Multiple Choice)
4.7/5 (79)
(79) A 59-year-old woman with schizoaffective disorder is brought to the emergency department by her daughter due to restlessness, sweating, diarrhea, and agitation over the last 24 hours. She was seen 3 days ago in an urgent care clinic for acute lower back pain. Physical examination showed no significant abnormalities and no further testing was ordered. The patient was given renewal prescriptions for haloperidol and benztropine and a new prescription for tramadol, and sent home. She is known to have osteoarthritis, chronic kidney disease, hypertension, and type 2 diabetes mellitus. Her other medications include acetaminophen, glipizide, sitagliptin, sertraline, and hydrochlorothiazide.
Temperature is 38.9 C (102 F), blood pressure is 146/94 mm Hg, pulse is 110/min and regular, and respirations are 16/min. Oxygen saturation on room air is 97%. The patient appears restless and startles easily. She has slow, continuous horizontal eye movements. Her neck is supple. Cardiopulmonary and abdominal examinations are within normal limits. She has a tremor and is hyperreflexic in her arms and legs. She has sustained bilateral patellar and ankle clonus, and Babinski sign is present bilaterally. Muscle tone is increased diffusely.
Which of the following is the most likely diagnosis in this patient?
(Multiple Choice)
4.8/5 (78)
(78) A 34-year-old woman comes to the emergency department with sharp, right-sided chest pain that worsens with inspiration, movement, coughing, and sneezing. She developed dry cough, malaise, fever, and rhinorrhea 3 days ago. The patient has pain when sitting up; she lies on her right side and sits with her torso hunched during the interview. She has a 15-pack-year smoking history and takes an estrogen-progestin oral contraceptive.
Temperature is 37.4 C (99.4 F), pulse is 78/min, and respirations are 16/min. Pulse oximetry shows oxygen saturation of 97% on room air. BMI is 22 kg/m2.
Lung examination reveals a scratching sound in the right base. There is no lower extremity edema.
Chest x-ray and ECG are unremarkable. D-dimer is within normal limits.
Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (80)
(80) A 32-year-old woman comes to the emergency department with sudden-onset unremitting fevers, chills, and joint pains for the past 2 days. She describes severe, "unbearable" pain in her right shoulder, left elbow, and left knee. She has not had any nausea, vomiting, or diarrhea. Three days ago, the patient returned from a 2-week honeymoon in the Dominican Republic. She spent time camping and swimming in the ocean. Her husband has no symptoms.
The patient's temperature is 39 C (102.2 F), blood pressure is 114/64 mm Hg, pulse is 96/min, and respirations are 18/min. She has no skin rash. Her lungs are clear bilaterally and there are no heart murmurs. Her abdomen is soft and nontender. Joint examination shows swelling in the left elbow and left knee without localized effusions or tenderness. Laboratory results are as follows:
 Which of the following is the most likely diagnosis?
 (Multiple Choice)
4.9/5 (79)
(79) A 36-year-old woman comes to the emergency department with abdominal pain and distention that started 5 days earlier and has become progressively worse. She initially thought she was experiencing bloating but the symptoms persisted despite poor appetite. The patient has a history of migraines. She underwent ovarian cyst resection 5 years ago. Her medications include over-the-counter analgesics, oral contraceptive pills, and daily multivitamins. She does not use tobacco, alcohol, or illicit drugs.
Her temperature is 37.2° C (99° F), blood pressure is 110/70 mm Hg, and pulse is 98/min. BMI is 25 kg/m2. The estimated jugular venous pressure is 7 mm H2O. Lungs are clear to auscultation. No murmurs are heard. The abdomen is distended and there is positive fluid shift test. The liver edge is tender and is palpated 4 cm below the right costal margin. The spleen is not palpable. There is trace lower-extremity edema.
Liver function test results are as follows:
 Ultrasound-guided paracentesis yields 1.5 L of clear fluid. Fluid analysis shows a white cell count of 120/mm3 and albumin of 2.4 g/L. Cytology is pending.
Which of the following is the most likely diagnosis?
Ultrasound-guided paracentesis yields 1.5 L of clear fluid. Fluid analysis shows a white cell count of 120/mm3 and albumin of 2.4 g/L. Cytology is pending.
Which of the following is the most likely diagnosis? (Multiple Choice)
4.8/5 (70)
(70) A 44-year-old construction worker comes to the emergency department with nausea and fatigue over the last 2 days. He strained his back at work 7 days ago. He could not move for several days and took over-the-counter painkillers and applied hot packs. The patient still has significant back pain and limited mobility. He smokes 1 pack of cigarettes a day. He drinks alcohol daily and heavily on weekends. In addition, he also admits to using intravenous heroin on occasion.
He was hospitalized for pneumonia 6 months ago and treated with intravenous antibiotics. The echocardiogram during that admission showed normal left ventricular systolic function, mildly dilated right ventricle, and mild pulmonary hypertension.
His temperature is 37.2° C (99° F), blood pressure is 94/50 mm Hg, and pulse is 112/min. There is mild scleral icterus. Several needle tracks are seen on both forearms. No heart murmurs are present. The lungs are clear. There is no abdominal distention. Moderate right upper-quadrant tenderness is present. The spleen is not palpable. There is no peripheral edema.
Laboratory results are as follows:
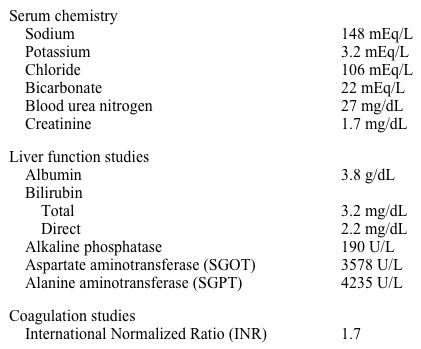 Which of the following is the most likely cause of this patient's current condition?
 (Multiple Choice)
4.9/5 (82)
(82) A 32-year-old woman is brought to the emergency department by her husband for new-onset "shaking spells" and high anxiety. She is a yoga teacher and has a history of chronic back pain, generalized anxiety disorder, and dysthymia. Her current medications include venlafaxine, ibuprofen, and tramadol. Her husband says that she recently began taking St. John's wort for depression.
Her temperature is 38.3 C (101 F), blood pressure is 160/90 mm Hg, and pulse is 144/min. On examination, her voice is tremulous, and there are tremors in her lower extremities. The patient is flushed and diaphoretic. Lower-extremity and ocular clonus is present. Mild rigidity is noted in the lower extremities. Left foot and patellar deep-tendon reflexes are 4+ and 3+, respectively.
Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.8/5 (78)
(78) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)