



 Chat with AI
Exam 1: Emergency Department

Exam 1: Emergency Department218 Questions
Exam 2: In-patient Facilities128 Questions
Exam 3: Office/Health Center900 Questions
Select questions type


A 72-year-old man is seen in the emergency department due to chest pain. He reports 2 days of mid-sternal chest pain, left shoulder pain, fatigue, and occasional sweating. He sleeps on his right side because sleeping on his back "hurts too much." He has a known history of coronary artery disease and underwent coronary artery bypass grafting (CABG) 4 weeks ago. The post-operative course was complicated by new-onset temporary atrial fibrillation and several days of post-operative fever.
His temperature is 38.2 C (100.8 F), blood pressure is 120/75 mmHg, pulse is 89/min, and pulse oximetry is 96% on room air. His cardiac and pulmonary examinations are within normal limits. His chest examination reveals a well-healing sternotomy site with mild erythema, but no tenderness to palpation.
ECG shows sinus rhythm with left bundle branch block, which was present on his ECG three weeks ago. Chest x-ray reveals cardiomegaly with sternotomy wires present and a small left-sided pleural effusion.
Which of the following best explains this patient's current complaints?
(Multiple Choice)
4.9/5  (71)
(71) A 70-year-old woman presents to the emergency department because of anorexia, nausea, and diarrhea. She has had these symptoms for the past 3 days. She recently completed a course of antibiotics for bronchitis. Her medical problems include osteoporosis, type 2 diabetes mellitus, hypertension, glaucoma, and osteoarthritis. Her current medications include metformin, fosinopril, chlorthalidone, ibandronate, acetazolamide, and acetaminophen. Her temperature is 37.4 C (99.4 F), blood pressure is 120/70 mm Hg, pulse is 84/min, and respirations are 16/min. On examination, she appears uncomfortable. Her abdomen is mildly tender in both of the lower quadrants. Test of the stool for blood is positive.
The patient's laboratory studies reveal:
 Which of the following is responsible for this patient's acid-base disorder?
 (Multiple Choice)
4.8/5 (73)
(73) A 57-year-old woman comes to the emergency department due to black stools and 2 episodes of hematemesis over the last 24 hours. Her other medical problems include hypertension, type 2 diabetes mellitus, hypercholesterolemia, and migraine headaches. Current medications include metformin, glyburide, simvastatin, ramipril, and low-dose aspirin. The patient has also been taking naproxen for frequent headaches over the last week. She has smoked a pack of cigarettes per day for 20 years and drinks 1 or 2 cans of beer daily.
Temperature is 36.7 C (98.1 F), blood pressure is 122/70 mm Hg, pulse is 96/min, and respirations are 16/min. Examination reveals a soft abdomen that is mildly tender over the epigastrium. There is no rebound tenderness or rigidity.
Laboratory results are as follows:
 After initial fluid resuscitation, the patient undergoes upper gastrointestinal endoscopy in the emergency department; it reveals a 1.5-cm ulcer in the gastric antrum. There is no active bleeding and the ulcer is covered with an adherent clot. Endoscopic hemostatic therapy is performed.
Which of the following is the most appropriate course of action for this patient?
After initial fluid resuscitation, the patient undergoes upper gastrointestinal endoscopy in the emergency department; it reveals a 1.5-cm ulcer in the gastric antrum. There is no active bleeding and the ulcer is covered with an adherent clot. Endoscopic hemostatic therapy is performed.
Which of the following is the most appropriate course of action for this patient? (Multiple Choice)
4.8/5 (77)
(77) A 54-year-old man with a history of alcohol abuse is brought to the emergency department after an episode of tonic-clonic seizures. He has a history of recurrent seizures and has been treated intermittently with phenytoin. Other medical issues include a mood disorder and anxiety. The patient lives in a homeless shelter. He has a 30-pack-year smoking history. He is treated with lorazepam and phenytoin in the emergency department.
Blood pressure is 122/70 mm Hg and pulse is 112/min and regular. BMI is 17 kg/m2. Dentition is poor and the gums are swollen with some evidence of bleeding. Small, mobile lymph nodes are palpated in the submandibular region. The lungs are clear to auscultation. The liver is palpated 2 cm below the subcostal margin. No ascites is present. Multiple scattered petechiae are seen on both the upper and lower extremities.
Laboratory results are as follows:
 Serum free phenytoin level is markedly low.
Which of the following best explains this patient's findings?
Serum free phenytoin level is markedly low.
Which of the following best explains this patient's findings? (Multiple Choice)
5.0/5 (76)
(76) A 65-year-old woman with a history of diabetes mellitus and hypertension is brought to the emergency department due to double vision and right eye pain. She awoke 2 days ago with right periorbital pain, and several hours later, she noticed double vision that became worse with accommodation. The double vision has been persistent and does not fluctuate throughout the day. The patient has had no headaches, blurry vision, dysarthria, dysphasia, weakness, numbness, or balance problems. Medications include aspirin, lisinopril, and metformin. The patient does not use tobacco, alcohol, or illicit drugs.
Blood pressure is 150/90 mm Hg seated and pulse is 80/min. Neurologic examination shows both horizontal and vertical binocular diplopia with left lateral and upward gazes. There is complete ptosis of the right eyelid, with the eyeball in the down-and-out position. The right pupil is 5 mm, midposition, and nonreactive to light; the left pupil is 3 mm, midposition, and reactive to light. The anisocoria improves with the ambient light off. No eye proptosis, conjunctival injection, periorbital edema, chemosis, or ocular bruit is present. Funduscopic examination reveals no papilledema. The rest of the neurologic examination is normal. Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.7/5 (63)
(63) A 62-year-old man comes to the emergency department due to sudden-onset chest pain. The patient is diagnosed with unstable angina. He undergoes cardiac catheterization and receives a drug-eluting stent to the left circumflex artery. Medical issues include hypertension, hypercholesterolemia, osteoarthritis, and chronic kidney disease. The patient was hospitalized 6 months earlier for upper gastrointestinal bleeding related to ibuprofen use. He is treated with aspirin, prasugrel, lisinopril, atorvastatin, and metoprolol.
Laboratory results are as follows:
 Echocardiogram shows a left ventricular ejection fraction of 55%. Which of the following additional therapies is indicated in this patient?
 (Multiple Choice)
4.7/5 (76)
(76) A 62-year-old man comes to the emergency department after "coughing up a 6-ounce cupful of blood." He describes about 3 days of increased yellowish sputum production associated with mild increase in dyspnea on exertion. On the previous 2 days he had slight blood streaking in the sputum. He has no prior history of hemoptysis. He has no fever, chills, weight loss, or night sweats.
His past medical history is significant for HIV and tuberculosis treated 12 years ago with directly observed therapy for 9 months. He is compliant with highly active antiretroviral therapy. He is an ex-IV drug user with a 50-pack-year history of tobacco use.
On examination, the patient is very anxious-appearing with mild respiratory distress and some dried blood on his lips. Pulse is 104/min, respirations are 20/min, and SaO2 is 90% on room air. Lung examination shows mild diffuse wheezing. He coughs up an additional 25 cc of blood while being examined.
Laboratory results are as follows:
 The CT scan is shown below.
 Which of the following is the most likely diagnosis?
The CT scan is shown below.
Which of the following is the most likely diagnosis? (Multiple Choice)
4.9/5 (92)
(92) A 16-year-old girl is evaluated in the emergency department for syncope. She has no other medical conditions and does not use tobacco, alcohol, or illicit drugs. Her blood pressure is 95/65 mm Hg and pulse is 106/min. The remainder of the physical examination is within normal limits. Laboratory values are as follows.
 The patient's urine chloride is low at 8 mEq/L.
Which of the following is the most likely diagnosis?
The patient's urine chloride is low at 8 mEq/L.
Which of the following is the most likely diagnosis? (Multiple Choice)
4.7/5 (73)
(73) A 65-year-old man comes to the emergency department due to acute onset of headache, double vision, slurred speech, and left-sided weakness. The patient describes his headache as a throbbing pain at the back of the head. He has had no nausea, vomiting, hiccups, numbness, or difficulty swallowing. The patient has a history of hypertension and hyperlipidemia. Medications include aspirin, lisinopril, and atorvastatin. He is a retired truck driver and smokes a pack of cigarettes a day.
Blood pressure is 170/90 mm Hg and pulse is 90/min with regular rhythm. Funduscopic examination is normal with no papilledema. There is no nystagmus; however, there is complete ptosis of the right eye that is depressed and deviated to the right. The right pupil is dilated and nonreactive to light. Confrontational visual fields are normal. There is left lower facial droop. The cough and gag reflexes are intact. The tongue is midline with no fasciculations. There is left-sided hemiplegia with an extensor plantar response. There is also increased cogwheel rigidity in the left upper extremity.
A non contrast CT scan of the head is negative for acute hemorrhage.
A lesion in which of the following areas is most likely responsible for this patient's symptoms?
(Multiple Choice)
4.8/5 (78)
(78) A 46-year-old woman comes to the emergency department because of progressively worsening shortness of breath, wheezing, dry cough, and sinus pressure for the last 2 weeks. She has had no fever, chills, or night sweats. She has a history of asthma and recurrent sinus infections over the past 10 years. The patient has used albuterol and inhaled corticosteroids for several years, but they no longer seem to help. She also has had joint pains for the last 2 months, for which she takes aspirin as needed.
Other medical conditions include hypertension, gastroesophageal reflux disease, and seasonal allergies. Medications include lisinopril, omeprazole, and loratadine as needed. The patient lives with her husband and has 2 cats. She has not traveled recently. She does not use tobacco, alcohol, or illicit drugs. The patient's father died of an unknown kidney disease, and her mother has a history of diabetes.
Temperature is 36.8 C (98.2 F), blood pressure is 130/70 mm Hg, pulse is 84/min, and respirations are 16/min. Erythematous tonsils are present without exudates. The patient has bilateral maxillary sinus tenderness to palpation. Bilateral nasal polyps are present. Lung examination reveals diffuse inspiratory and expiratory wheezes. The remainder of the physical examination is unremarkable.
Laboratory results are as follows.
 A chest x-ray demonstrates ill-defined opacities bilaterally.
Which of the following is the most likely diagnosis?
A chest x-ray demonstrates ill-defined opacities bilaterally.
Which of the following is the most likely diagnosis? (Multiple Choice)
4.9/5 (76)
(76) A 28-year-old man comes to the emergency department due to cramping abdominal pain, nausea, anorexia, and multiple episodes of loose stools for the last 2 days. The patient is a medical student who returned from rural Indonesia a week ago after volunteering at a hospital for a month. Several days into his travel, he experienced watery diarrhea that spontaneously resolved within a few days. After his return, he had fever and sore throat for which his primary care physician prescribed amoxicillin, which he finished taking 2 days ago. The patient has no chronic medical conditions, takes no other medications, and has no known allergies. His older brother has ulcerative colitis and his mother has hypertension.
Temperature is 39 C (102.2 F), blood pressure is 94/45 mm Hg, and pulse is 112/min and regular. The abdomen is soft and diffusely tender with maximum tenderness in the right lower quadrant. There is no rebound tenderness or rigidity.
Laboratory results are as follows:
 Which of the following is the most likely cause of this patient's condition?
 (Multiple Choice)
4.9/5 (66)
(66) A 62-year-old man comes to the emergency department because of nausea and abdominal pain. He describes the pain as a pressure located in the epigastric area which feels like it is "pushing up" into his chest. It began approximately 30 minutes before his arrival and he thinks it is related to having eaten some spicy food the night before. The pain initially improved while leaning forward, but it is now present in any position. The patient has no shortness of breath or palpitations. He has a history of benign prostatic hyperplasia that is well-controlled with tamsulosin. He does not smoke or use illicit drugs but drinks 4-5 alcoholic beverages daily, and occasionally consumes more.
His blood pressure is 135/75 mm Hg in the right arm and 130/75 mm Hg in left arm, pulse is 70/min, and respirations are 14/min. Pulse oximetry shows 98% oxygen saturation on room air. The patient is in moderate pain and is diaphoretic. There is a 2/6 systolic murmur at the apex which radiates to the axillae. The lungs are clear to auscultation. The remainder of the physical examination is within normal limits.
Laboratory results are as follows:
 A 12-lead electrocardiogram is shown in this exhibit.
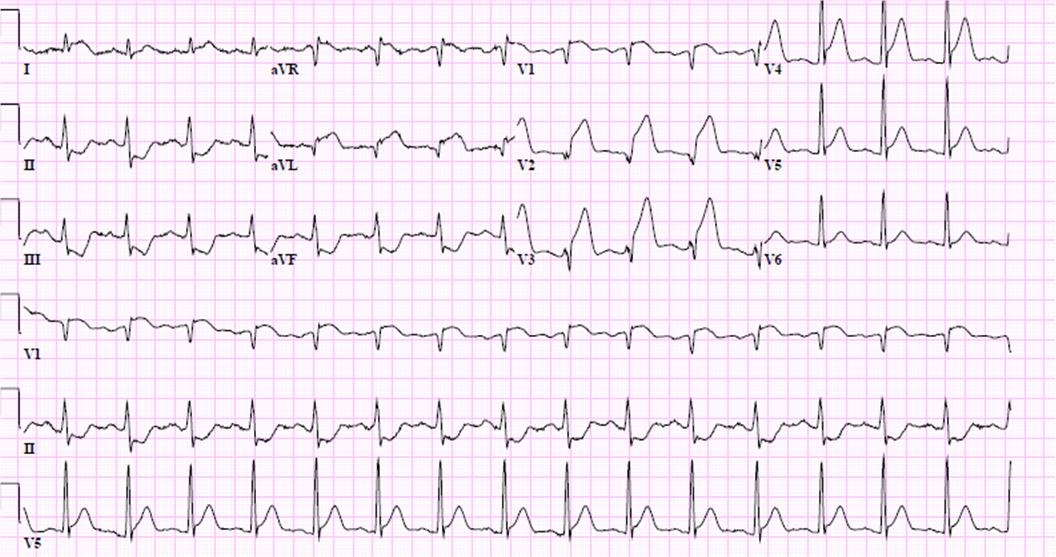 Which of the following is the most appropriate next step in the management of this patient?
A 12-lead electrocardiogram is shown in this exhibit.
Which of the following is the most appropriate next step in the management of this patient? (Multiple Choice)
4.9/5 (89)
(89) An 85-year-old nursing home resident is brought to the emergency department due to worsening cough, difficulty breathing, and decreased responsiveness for 3 days. Medical conditions include hypertension, type 2 diabetes mellitus, and dementia. Following evaluation that reveals leukocytosis and lung infiltrates, the patient's respiratory distress progressively worsens. Endotracheal intubation is performed; mechanical ventilation is begun; the patient is given intravenous fluids and antibiotics; a central venous catheter is placed; and she is admitted to the intensive care unit (ICU).
In the ICU, the patient requires increasing ventilatory support with elevated airway pressures. Temperature is 35.6 C (96 F), blood pressure is 84/40 mm Hg, pulse is 112/min, and respirations are 16/min. Pulse oximetry shows 92% on assist-control mode with a tidal volume of 300 mL, fraction of inspired oxygen (FiO2) of 60%, and positive end-expiratory pressure (PEEP) of 5 cm H2O. Examination reveals decreased breath sounds on the right, rhonchi on the left, and normal S1 and S2. The abdomen is soft and nontender. There is no extremity edema.
Arterial blood gases and chest x-ray are shown below.

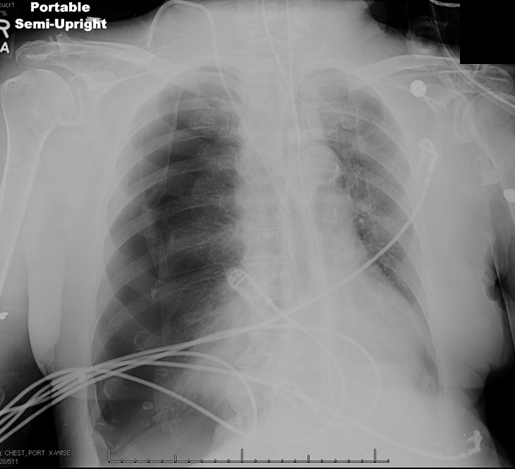 Which of the following is the most appropriate next step in management of this patient?
 (Multiple Choice)
4.7/5 (78)
(78) A 65-year-old man is brought to the emergency department by his caregiver due to confusion. The patient was in his usual state of health last night, but this morning he was found in bed very sleepy and confused. He had also soiled the bed with urine and stool, which he had never done before. The patient had a right middle cerebral artery ischemic stroke a month ago and was recently discharged from a rehabilitation facility. He was treated for pneumonia with oral antibiotics at the rehabilitation facility 2 weeks ago. His other medical issues include hypertension, hyperlipidemia, and benign prostate hyperplasia. Current medications include aspirin, atorvastatin, chlorthalidone, metformin, and tamsulosin. He has no known drug allergies.
Temperature is 37.2 C (99 F), blood pressure is 152/84 mm Hg, pulse is 90/min, and respirations are 18/min. The patient is somnolent and awakens to voice. Mucous membranes are moist. The lungs are clear to auscultation and there are no heart murmurs. The abdomen is soft and nontender. Neurological examination shows residual left hemiparesis from prior stroke.
Laboratory results are as follows:
 Serum creatinine was 0.9 mg/dL at hospital discharge a month ago. Calculated urinary fractional excretion of sodium is 0.8%.
Which of the following is the most likely cause of this patient's acute kidney injury?
Serum creatinine was 0.9 mg/dL at hospital discharge a month ago. Calculated urinary fractional excretion of sodium is 0.8%.
Which of the following is the most likely cause of this patient's acute kidney injury? (Multiple Choice)
4.9/5 (89)
(89) A 30-year-old previously healthy man comes to the emergency department due to back pain and difficulty walking. His symptoms began 4 days ago with lower back pain, which he attributed to moving furniture around his apartment. The patient also experienced a tingling sensation in his feet and hands and by the next day had difficulty walking. His weakness has gradually progressed and he has also experienced frequent episodes of palpitations, excessive sweating, and dyspnea. The patient has not travelled recently and reports no recent respiratory or gastrointestinal illness or vaccinations. He takes no medications, drinks alcohol occasionally, and does not use tobacco or illicit drugs. He has had 2 sexual partners over the past year and uses condoms inconsistently.
On examination, the patient is alert and cooperative. Bilateral pupils react sluggishly to light and accommodation. His speech is slightly dysarthric with mild weakness of the buccinators. Bilateral upper extremity motor strength is 4/5 with hyporeflexia, and bilateral lower extremity tone is decreased with 3/5 motor strength and areflexia. Vibration and proprioception sensations are reduced in the feet bilaterally. Coordination and gait testing are limited by weakness. There is no spine tenderness or neck rigidity.
Which of the following would be most helpful in establishing the diagnosis in this patient?
(Multiple Choice)
4.7/5 (82)
(82) A 73-year-old man with a history of moderate chronic obstructive pulmonary disease comes to the emergency department with fever, malaise, night sweats, and a cough producing thick, yellowish sputum over the past 4 weeks. He has been using inhalers (tiotropium, formoterol, albuterol) as prescribed, but his symptoms have not improved. He smokes a half pack of cigarettes daily and has a 45-pack-year history. Medical history is also significant for hypertension, hyperlipidemia, Zenker diverticulum, and type 2 diabetes mellitus. He does not use alcohol or illicit drugs. Temperature is 37.7 C (99.8 F), blood pressure is 128/82 mm Hg, pulse is 94/min, and respirations are 16/min. Oxygen saturation is 95% on room air. Physical examination is within normal limits.
Laboratory results are as follows:
 Chest x-ray reveals a right lower-lobe cavitary lesion with an air-fluid level.
What is the most appropriate next step in management of this patient?
Chest x-ray reveals a right lower-lobe cavitary lesion with an air-fluid level.
What is the most appropriate next step in management of this patient? (Multiple Choice)
4.7/5 (71)
(71) A 42-year-old man comes to the emergency department due to fatigue, chest pain, and shortness of breath for the past 5 days. He has had difficulty falling asleep at night due to chest discomfort. The patient had a "bad case of the flu" 3 weeks ago and still has a persistent cough. He is otherwise healthy and has no other medical problems. He has a 20-pack-year smoking history and drinks 3 or 4 beers on weekends.
Blood pressure is 92/54 mm Hg and pulse is 112/min. Blood pressure decreases to 75/42 mm Hg during inspiration. Jugular venous pressure is estimated at 16 cm H2O. There are minimal crackles present at both lung bases. Heart sounds are faint on cardiac auscultation. Lower extremities are cool with feeble pulses.
Chest x-ray is shown in the exhibit. 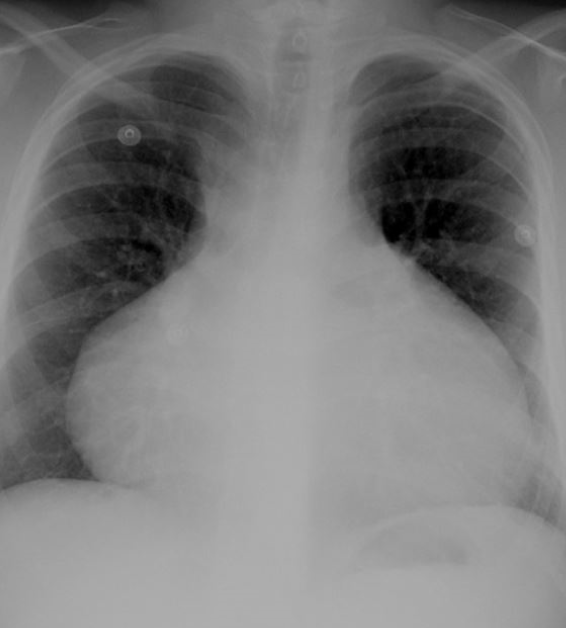 An echocardiogram in this patient would most likely show which of the following?
 (Multiple Choice)
4.9/5 (79)
(79) A 71-year-old man is brought to the emergency department because of a 2-day history of excruciating left thigh pain, weakness, and nausea. His medical problems include type 2 diabetes mellitus, hypertension, and benign prostatic hyperplasia. He is a lifetime non-smoker.
His blood pressure is 85/40 mm Hg and pulse is 114/min and regular. Mucous membranes are dry. Examination reveals magenta-bronze discoloration, crepitus, tenderness, and significant swelling over the left thigh.
Laboratory results are as follows:
 A Foley catheter was placed and 200 mL of concentrated urine was drained. Intravenous antibiotics, analgesics, and bolus fluids were administered. CT scan of the thigh showed gas gangrene. He was emergently taken to the operating room for debridement. Four days later, the patient feels better. The Foley catheter is removed and he urinates without difficulty. Two sets of blood cultures sent on admission grow Clostridium septicum.
Which of the following additional studies would be indicated in this patient?
A Foley catheter was placed and 200 mL of concentrated urine was drained. Intravenous antibiotics, analgesics, and bolus fluids were administered. CT scan of the thigh showed gas gangrene. He was emergently taken to the operating room for debridement. Four days later, the patient feels better. The Foley catheter is removed and he urinates without difficulty. Two sets of blood cultures sent on admission grow Clostridium septicum.
Which of the following additional studies would be indicated in this patient? (Multiple Choice)
4.8/5 (90)
(90) A 45-year-old man comes to the emergency department after an episode of coffee-ground emesis. During the past 6 months, he has had intermittent abdominal pain and heartburn partially relieved by over-the-counter antacids. The patient also complains of explosive diarrhea that has not responded to dietary modifications. Two months ago, he stopped consuming milk without relief. He is a lifetime nonsmoker.
His blood pressure is 133/70 mm Hg and pulse is 89/min. There are no orthostatic changes. He has moderate epigastric tenderness without rebound.
Laboratory results are as follows:
 Upper gastrointestinal endoscopy shows 2 small ulcers in the duodenal bulb with clean bases and a 1.2-cm ulcer in the very proximal jejunum.
Which of the following is most likely to establish the diagnosis in this patient?
Upper gastrointestinal endoscopy shows 2 small ulcers in the duodenal bulb with clean bases and a 1.2-cm ulcer in the very proximal jejunum.
Which of the following is most likely to establish the diagnosis in this patient? (Multiple Choice)
4.9/5 (86)
(86) A 61-year-old woman comes to the emergency department due to fever, chills, and left flank pain that began abruptly last evening. A month ago, the patient was treated for a urinary tract infection with a short course of ciprofloxacin. She otherwise has no medical problems and currently takes no medications. She has no history of hospitalizations or surgeries.
Temperature is 39.4 C (103 F), blood pressure is 80/40 mm Hg, pulse is 120/min, and respirations are 24/min. Pulse oximetry shows 94% on room air. Mucous membranes are dry and jugular veins are flat. Cardiopulmonary auscultation reveals clear lung fields and normal heart sounds without murmurs. The abdomen is soft and nontender. Left costovertebral angle tenderness is present. Skin examination is normal. The extremities are warm with no edema. Neurologic examination is within normal limits.
Laboratory results are as follows:
 Broad-spectrum antibiotics and intravenous fluids are initiated, and the patient is admitted to the intensive care unit. Enoxaparin is given for prophylaxis against deep vein thrombosis. On hospital day 2, urine and blood cultures are positive for Escherichia coli and antibiotics are narrowed based on culture sensitivities. Repeat laboratory testing is similar to admission, except platelet count has dropped to 105,000/mm3.
Which of the following is the most appropriate next step in management of this patient?
Broad-spectrum antibiotics and intravenous fluids are initiated, and the patient is admitted to the intensive care unit. Enoxaparin is given for prophylaxis against deep vein thrombosis. On hospital day 2, urine and blood cultures are positive for Escherichia coli and antibiotics are narrowed based on culture sensitivities. Repeat laboratory testing is similar to admission, except platelet count has dropped to 105,000/mm3.
Which of the following is the most appropriate next step in management of this patient? (Multiple Choice)
4.8/5 (85)
(85) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)