



 Chat with AI
Exam 1: Emergency Department

Exam 1: Emergency Department218 Questions
Exam 2: In-patient Facilities128 Questions
Exam 3: Office/Health Center900 Questions
Select questions type


A 44-year-old man comes to the emergency department due to a diffuse, painful skin rash that began abruptly 2 days ago. He has also had fever and malaise but no cough, shortness of breath, abdominal pain, diarrhea, dysuria, or joint pains. Three years ago, the patient was diagnosed with plaque psoriasis involving the scalp, elbows, and knees. He was treated with a high-potency topical corticosteroid ointment, which has improved his symptoms. He stopped using the ointment a week ago. He also has a history of untreated chronic hepatitis C. The patient is sexually active and uses condoms inconsistently.
Temperature is 38.7 C (101.8 F), blood pressure is 130/70 mm Hg, and pulse is 98/min. There is no scleral icterus or lymphadenopathy. Oropharyngeal mucous membranes are normal. Skin examination reveals erythema and lesions as shown below involving his trunk, neck, and extremities.
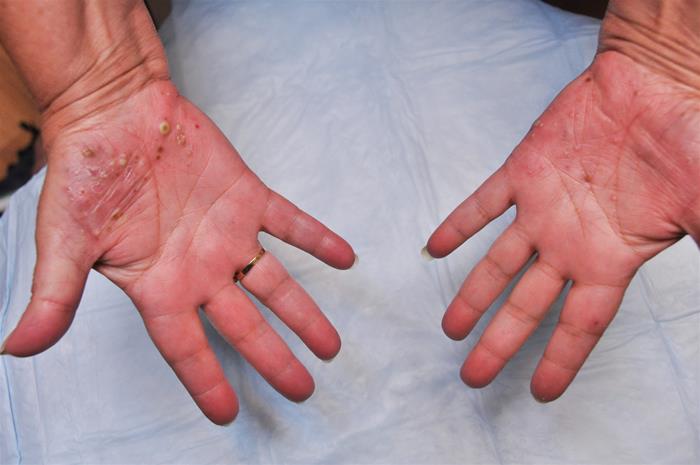 Which of the following is the most likely diagnosis?
 (Multiple Choice)
4.9/5  (87)
(87) A 32-year-old woman with a history of migraine headaches comes to the emergency department with severe left-sided headache and nausea that started 3 hours ago. Earlier in the morning she had blurry vision and saw halos around lights. She took ibuprofen an hour ago but vomited shortly afterward.
Her vital signs are within normal limits. The patient feels uncomfortable when her eyes are examined with a flashlight. The pupils are equal and reactive. Muscle strength and tone are normal and deep-tendon reflexes are symmetrical. She is treated with intravenous metoclopramide. One hour later, she complains of neck pain. Physical examination shows sustained contraction of the posterior neck muscles associated with neck extension and tenderness.
What is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (72)
(72) A 34-year-old woman comes to the emergency department for vaginal bleeding. The patient initially had vaginal spotting yesterday, but the bleeding has become increasingly heavy. She also has had lower abdominal pain with nausea for the past hour. Her last menstrual period was 7 weeks ago. She is sexually active and does not use contraception due to a history of infertility. The patient has had no surgeries and takes no daily medications.
Blood pressure is 100/50 mm Hg and pulse is 92/min. BMI is 41 kg/m2. The abdomen is tender in bilateral lower quadrants with involuntary guarding. Pelvic examination reveals a closed cervix with active bleeding from the cervical os. Bimanual examination reveals a small, mobile uterus and right adnexal tenderness.
Hemoglobin is 9.8 g/dL and quantitative β-hCG is 7,135 IU/L. Transvaginal ultrasound shows a thickened endometrial stripe, a 4-cm complex right adnexal mass, and a small amount of free fluid in the posterior cul-de-sac.
Which of the following is the most likely diagnosis in this patient?
(Multiple Choice)
4.9/5 (81)
(81) A 27-year-old man comes to the emergency department with severe right eye pain. Over the last 3 days, he has had several episodes of "unbearable" eye pain that lasts 30-40 minutes and then resolves completely.
He would not sit down for a physical examination and paces around the room in pain. His right eye shows conjunctival injection with a constricted pupil. There is notable right-sided excessive lacrimation and rhinorrhea.
Which of the following is the best next step in managing this patient?
(Multiple Choice)
4.9/5 (69)
(69) A 72-year-old woman comes to the emergency department due to acute dizziness for 6 hours. The patient awoke this morning with the persistent sensation of "the room spinning around," which becomes worse with head movement. She also has nausea and vomiting, but no headache or vision problems. Nothing seems to relieve her symptoms.
Her other medical problems are hypertension and hyperlipidemia. Home medications include amlodipine and atorvastatin.
Temperature is 36.7 C (98 F), blood pressure is 160/90 mm Hg, and pulse is 84/min. On examination, the patient has bidirectional nystagmus. Muscle strength, light touch and pain sensation, and reflexes are normal throughout. The patient's gait is unsteady and she tends to fall toward the right side.
Blood sugar is 140 mg/dL and electrolytes are normal. Noncontrast CT scan of the head is normal. ECG reveals normal sinus rhythm.
Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.7/5 (84)
(84) A 28-year-old woman is brought to the emergency department after passing out at work. The patient was diagnosed with type 2 diabetes a year and a half ago with a hemoglobin A1c of 8.2%. She was started on metformin at that time; however, within 2 months the medication was discontinued due to intolerable gastrointestinal side effects. The patient was then switched to glipizide, achieving good glycemic control within 3 months. However, approximately 6 months ago the patient began experiencing hypoglycemic episodes with associated dizziness and decreased level of consciousness. The glipizide dose was decreased, but she continued to report hypoglycemic episodes. The patient's primary care physician recommended that she switch to a different antidiabetic agent, but the patient preferred to continue glipizide. Over the previous 6 months, the patient has been seen in the emergency department on numerous occasions and has been hospitalized once. Her most recent hemoglobin A1c 2 weeks ago was 8.1%. Currently, the patient's only medication is glipizide, which she insists she is taking as prescribed.
Supine blood pressure is 122/83 mm Hg and pulse is 62/min. After 5 minutes of standing, blood pressure is 117/79 mm Hg and pulse is 71/min. The patient is currently drinking apple juice, chatting cheerfully with the nurse, and in no apparent distress. Physical examination is within normal limits.
Laboratory results drawn prior to any intervention are as follows:
 Which of the following is the most likely explanation for this patient's symptoms?
 (Multiple Choice)
4.8/5 (87)
(87) A 60-year-old woman comes to the emergency department due to 2 weeks of worsening bilateral headaches, blurry vision, dizziness, and tingling sensation in her feet. She has had no fevers, night sweats, unintentional weight loss, or jaw pain but has had several episodes of epistaxis. The patient has a history of hypertension and takes chlorthalidone. She does not use tobacco, alcohol, or illicit drugs.
Temperature is 37.2 C (99.0 F), blood pressure is 166/98 mm Hg, pulse is 85/min, and respirations are 14/min. Physical examination shows moist mucous membranes, normal tympanic membranes, and no sinus tenderness. Bilateral pupils are equal and reactive. Visual acuity is decreased in both eyes, and funduscopic examination reveals dilated, segmented, and tortuous retinal veins. Facial sensation and strength are normal. Bilateral upper- and lower-extremity muscle strength is normal. There is decreased pinprick sensation and loss of ankle reflex bilaterally.
Laboratory results are as follows:
 Which of the following is the most appropriate next step in management of this patient?
 (Multiple Choice)
4.7/5 (77)
(77) A 19-year-old man from Arizona is brought to the emergency department by his parents due to a high-grade fever, chills, and headache. He also complains of severe pain in the groin and axillary areas, which was preceded by swelling. Two days prior to this event, the patient's father was changing carpet in the patient's room and noticed a dead rat.
His temperature is 39.6 C (103.3 F), blood pressure is 100/70 mm Hg, and pulse is 98/min. Examination shows multiple severely tender, non-fluctuant, enlarged nodules in the axillary and groin regions. The skin over these areas is edematous and erythematous. Blood cultures are obtained.
Which of the following organisms is most likely responsible for this patient's infection?
(Multiple Choice)
4.7/5 (85)
(85) A 65-year-old man presents to the emergency department because of a nosebleed, which started 6 hours ago. He has not been able to stop it with recumbency and nasal pressure. He had a similar nosebleed 2 years ago and was told by an ENT physician that he has telangiectasias in his nasal septum. He has not noted any bleeding or bruising elsewhere. There is no history of aspirin use, although he has taken a few ibuprofens recently. He is known to have chronic kidney disease with a serum creatinine of 6.8 mg/dL. A fistula has been placed in his arm anticipating the commencement of dialysis soon. He has hypertension, hyperlipidemia, osteoarthritis, and gout. Current medications include atenolol, amlodipine, calcium carbonate, reduced-dose allopurinol, and furosemide.
His blood pressure is 142/86 mm Hg without orthostatic changes, pulse is 84/min, and respirations are 16/min. Bright red blood is seen oozing around his left naris, which is filled with bloody tissue paper. Some bright red blood is seen in his posterior pharynx. His lung, cardiovascular, and abdominal exams are normal. There is no edema.
The patients labs reveal:
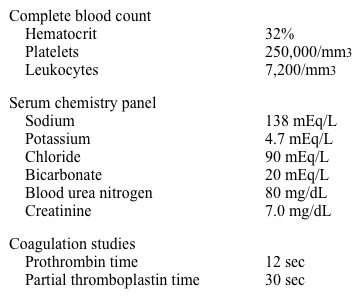 After anterior and posterior nasal packing, oozing into and around the packing continues.
Which of the following is the most appropriate next step in management?
After anterior and posterior nasal packing, oozing into and around the packing continues.
Which of the following is the most appropriate next step in management? (Multiple Choice)
4.8/5 (89)
(89) A 34-year-old woman comes to the emergency department due to right-sided weakness and difficulty speaking since she awoke 5 hours ago. The patient has no fever, weight loss, fatigue, headache, loss of consciousness, or vision problems. According to her husband, she had a similar episode 6 months ago that resolved quickly and was attributed to her migraine headaches. The patient has had one previous miscarriage at 12 weeks gestation. She smokes a half-pack of cigarettes per day and does not use illicit drugs. The patient has a family history of migraines.
Temperature is 37.2 C (99 F), blood pressure is 143/77 mm Hg, and pulse is 87/min. There are no carotid bruits. Cardiac auscultation reveals no murmurs. There is right hemiparesis and mild expressive aphasia.
Laboratory results are as follows:
 ECG shows normal sinus rhythm. CT scan of the head shows no intracranial mass and no evidence of bleeding; CT angiography of the head and neck shows no significant large vessel stenosis or occlusion.
Which of the following is the best next step in management of this patient?
ECG shows normal sinus rhythm. CT scan of the head shows no intracranial mass and no evidence of bleeding; CT angiography of the head and neck shows no significant large vessel stenosis or occlusion.
Which of the following is the best next step in management of this patient? (Multiple Choice)
4.9/5 (87)
(87) A 62-year-old man with a history of coronary artery disease comes to the emergency department with 2 days of fever and fatigue. Over the last 24 hours, he has developed progressive fatigue and confusion. The patient's past medical history is notable for a coronary catheterization 2 weeks ago with placement of an intracoronary stent in the right posterior descending artery. He was discharged home within 24 hours. He has no other medical history or prior surgeries. The patient lives in New York with his wife, who has been well. He has no recent travel and currently works as an accountant.
On physical examination, the patient appears uncomfortable but is clinically stable. His temperature is 38.6 C (101.5 F), blood pressure is 122/70 mm Hg, and pulse is 114/min and regular. There is no lymph node enlargement. There is no tenderness to palpation over the sinuses. The lungs are clear on auscultation. No heart murmurs are appreciated. The abdomen is soft and nontender. The tip of the spleen is not palpated. There is no rash. Laboratory results are as follows:
 He is initially treated with vancomycin and piperacillin-tazobactam. Forty-eight hours later, blood cultures from admission grow methicillin-resistant Staphylococcus aureus.
What is the best next step in management of this patient's infection?
He is initially treated with vancomycin and piperacillin-tazobactam. Forty-eight hours later, blood cultures from admission grow methicillin-resistant Staphylococcus aureus.
What is the best next step in management of this patient's infection? (Multiple Choice)
4.7/5 (96)
(96) An 82-year-old nursing home resident with a history of hypertension and chronic obstructive pulmonary disease (COPD) is brought to the emergency department after 2 days of fever, cough, and lethargy. He was treated with acetaminophen at the nursing home, but was found to be very confused this morning. His oral intake has also been poor. His daily medications include lisinopril, hydrochlorothiazide, and tiotropium. He has never been hospitalized for a COPD exacerbation or pneumonia. At the nursing home, there have been two cases of mild febrile illness over the past two weeks.
In the emergency department, he is ill-appearing and obtunded. His temperature is 39.4 C (103 F), blood pressure is 107/60 mm Hg, pulse is 68/min, and respirations are 26/min. Pulmonary examination reveals crackles at the left lung base. Bowel sounds are hyperactive and his abdomen is soft. There are no meningeal signs present.
Laboratory studies reveal:
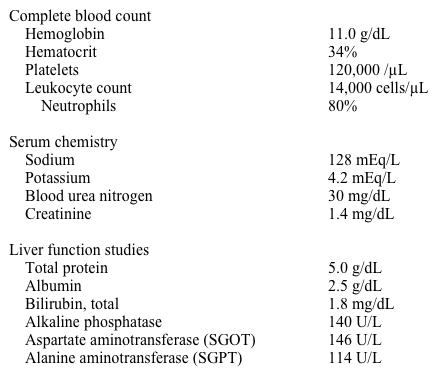 A chest x ray reveals an ill-defined infiltrate at the left lung base.
Piperacillin-tazobactam and vancomycin are started empirically. Over the next 48 hours, his clinical status continues to deteriorate. A repeat chest x ray reveals progressive infiltrates with worsening left lower lobe consolidation.
This patient's condition is most likely to respond to which of the following?
A chest x ray reveals an ill-defined infiltrate at the left lung base.
Piperacillin-tazobactam and vancomycin are started empirically. Over the next 48 hours, his clinical status continues to deteriorate. A repeat chest x ray reveals progressive infiltrates with worsening left lower lobe consolidation.
This patient's condition is most likely to respond to which of the following? (Multiple Choice)
4.8/5 (87)
(87) A 23-year-old woman comes to the emergency department less than an hour after being stung by a wasp. She has a history of asthma and felt some chest tightness soon after the sting. The patient administered 2 inhalations of her rescue albuterol, and her breathing subsequently improved. She also has generalized itching and crampy abdominal pain.
Blood pressure is 108/66 mm Hg, pulse is 94/min, respirations are 16/min, and SaO2 is 95% on room air. The patient is breathing comfortably, without accessory muscle usage. Lung auscultation shows mild wheezing with good air entry. The abdomen is soft but mildly tender with slightly increased bowel sounds.
Which of the following is the most appropriate first step in management of this patient?
(Multiple Choice)
4.8/5 (76)
(76) A 32-year-old woman comes to the emergency department due to right flank pain for the last 12 hours. The patient describes severe, intermittent pain lasting 20-30 minutes at a time. She has also had nausea and several episodes of vomiting but no fever, chills, dysuria, or diarrhea. The patient had similar symptoms 2 years ago and was found to have a renal calculus. The stone passed spontaneously and no analysis was performed. She has no other medical conditions and takes no medications.
Temperature is 36.8 C (98.2 F), blood pressure is 132/74 mm Hg, pulse is 90/min, and respirations are 16/min. BMI is 32 kg/m2. Physical examination shows dry mucous membranes. There is mild right flank tenderness without guarding or rebound tenderness.
Blood cell counts are within normal limits, serum creatinine is 1.4 mg/dL, and blood urea nitrogen is 33 mg/dL. Urinalysis shows moderate blood with numerous erythrocytes and a pH of 6.5. Urine pregnancy test is negative. Noncontrast abdominal CT scan reveals a high-density, 15-mm calculus in the proximal right ureter without hydronephrosis.
Intravenous analgesics, antiemetics, and fluids are administered. Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.9/5 (79)
(79) A 24-year-old man comes to the emergency department in January due to fever and shortness of breath. A week ago, he developed fever, malaise, muscle aches, and rhinorrhea. The symptoms largely resolved 2 days ago, but this morning the patient began having productive cough of green-yellow sputum, shortness of breath, and pleuritic chest pain. He has had no recent travel or other significant illness. The patient has not received the influenza vaccine. He has a history of type 1 diabetes mellitus and takes insulin.
Temperature is 39.1 C (102.4 F), blood pressure is 135/67 mm Hg, pulse is 104/min, and respirations are 22/min. Pulse oximetry shows 90% on room air. The patient is ill-appearing and in mild respiratory distress. He coughs frequently during the examination. Lung examination shows bronchial breath sounds and crackles in the right lower lung field.
Leukocyte count is 14,000/mm3 with 82% neutrophils. Chest x-ray shows a dense right lower-lobe consolidation with a small area of lucency and small right-sided pleural effusion. Rapid influenza test is positive.
Which of the following empiric treatments is most appropriate for this patient?
(Multiple Choice)
4.8/5 (87)
(87) A 67-year-old man with chronic obstructive pulmonary disease (COPD) is seen in the emergency department for increasing dyspnea. His most recent FEV1 was 0.8 L and he is on chronic oxygen therapy. Two days ago, he began coughing up increased sputum and felt more short of breath. One day ago, he noticed that his sputum became purulent and his shortness of breath worsened. He denies chest pain, hemoptysis, fever, abdominal pain, or nausea. He receives an annual influenza vaccination and obtained vaccination for S. pneumoniae three years ago. He denies any other new symptoms and does not have diarrhea, nausea, or vomiting. He has hypertension, hyperlipidemia, and type 2 diabetes mellitus. His current medications include albuterol, tiotropium, lovastatin, hydrochlorothiazide, and metformin.
On examination, he appears dyspneic. His temperature is 36.7 C (98 F), blood pressure is 130/90 mm Hg, pulse is 96 /min, and respirations are 20 /min. He has difficulty speaking in complete sentences. There is no asterixis. Cardiac examination demonstrates a right ventricular lift, but is otherwise normal. All breath sounds are decreased. There is prolongation of the expiratory phase of respiration. There are no rales or rhonchi. Abdominal examination is normal. Extremity examination shows 1+ pedal edema bilaterally to the mid-shin.
Fingerstick blood glucose is 90 mg/dL. A metabolic panel shows that his serum creatinine is 1.0 mg/dL.
Which of the following arterial blood gases (ABG) would be most compatible with his clinical picture?
(Multiple Choice)
4.8/5 (80)
(80) A 58-year-old woman comes to the emergency department with 5 days of progressive headaches and dizziness. She is a business executive who is very active in her spare time. She takes no medications.
Her vital signs are within normal limits. Examination shows bilateral normal reflexes and sensation and no neck stiffness. Pupils are equal and reactive to light. Gag reflex is intact. There is no peripheral lymphadenopathy.
Laboratory results are as follows:
 CT scan of the head with contrast shows a solitary frontal 2x3 cm lesion at the gray-white matter junction with vasogenic edema confirmed on magnetic resonance imaging. CT scan of the chest, abdomen, and pelvis reveals a spiculated 2.5 cm right upper-lung mass with ipsilateral bronchial lymphadenopathy but no other evidence of metastatic disease.
Which of the following is the most appropriate next step in management of this patient's brain lesion?
CT scan of the head with contrast shows a solitary frontal 2x3 cm lesion at the gray-white matter junction with vasogenic edema confirmed on magnetic resonance imaging. CT scan of the chest, abdomen, and pelvis reveals a spiculated 2.5 cm right upper-lung mass with ipsilateral bronchial lymphadenopathy but no other evidence of metastatic disease.
Which of the following is the most appropriate next step in management of this patient's brain lesion? (Multiple Choice)
4.8/5 (72)
(72) A 35-year-old woman comes to the emergency department with progressively worsening exertional dyspnea and generalized weakness. She also complains of cough, especially during and after meals. Over the past 3 weeks she has had episodes of blurry vision and difficulty raising her arms above her head and walking up and down stairs. She has no hemoptysis, muscles aches, slurred speech, headaches, numbness, or paresthesias. Her medical history is significant for hypothyroidism and hypertension. There is no family history of malignancy. She is an active smoker with a 20-pack-year history.
Vital signs are within normal limits. The patient has subjective fatigable horizontal binocular diplopia. Her neck flexors and proximal muscles of the upper and lower extremities are 4/5 in strength. Sensory examination and reflex testing are unremarkable.
Vital capacity obtained at the bedside is 0.5 L (< 50% of predicted).
Complete blood count, comprehensive metabolic panel, thyroid-stimulating hormone, and chest x-ray are normal. Noncontrast computed tomography scan of the chest shows mild centrilobular emphysema and a 2.6-cm mediastinal mass. There is no regional lymphadenopathy.
Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.7/5 (66)
(66) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)