



 Chat with AI
Exam 1: Emergency Department

Exam 1: Emergency Department218 Questions
Exam 2: In-patient Facilities128 Questions
Exam 3: Office/Health Center900 Questions
Select questions type


A 52-year-old man comes to the emergency department with fevers, cough, and headache. The headache has worsened over the last week with localization to the right side and is associated with nausea. Yesterday he noted left-hand weakness and difficulty grasping objects. He has no history of travel outside of the northeastern United States or exposure to domestic animals or sick contacts. The patient underwent liver transplantation for primary biliary cirrhosis 8 months ago and had an uneventful postoperative course. His medications include prednisone and tacrolimus. His preoperative tuberculin skin testing was negative and he has had no postoperative infections. He is physically active and had walked 2-3 miles a day until 1 week ago.
His temperature is 38.2 C (100.8 F), blood pressure is 124/84 mm Hg, pulse is 96/min, and respirations are 18/min. Crackles are present over the right upper lung field. There are no heart murmurs. The abdomen is soft without organomegaly. There are no skin rashes. Neurological examination is notable for left-hand weakness and decreased sensation of the left hand and forearm.
Chest x-ray reveals patchy alveolar opacities in the right upper lobe and a 3-cm abscess in the right middle lobe. Head CT scan shows an abscess in the right cerebral hemisphere. A transesophageal echocardiogram reveals no vegetations.
Which of the following conditions is most consistent with this patient's clinical presentation?
(Multiple Choice)
4.9/5  (76)
(76) A 45-year-old woman is brought to the emergency department by her husband due to fever and confusion. He notes that the patient began having fever, headache, nausea, and vomiting yesterday. She was also disoriented and made many odd statements to her children. The patient has a history of type 1 diabetes mellitus and chronic kidney disease and underwent simultaneous pancreas-kidney transplantation 2 years ago. She takes maintenance immunosuppressive therapy.
Temperature is 38.9 C (102 F), blood pressure is 108/60 mm Hg, pulse is 105/min, and respirations are 21/min. The patient is lethargic and ill-appearing. No skin rash is present. The lungs are clear to auscultation, and there are no heart murmurs. The abdomen is soft and nontender. The patient is oriented only to self and moves all extremities to pain. No nuchal rigidity or signs of meningismus are elicited.
Leukocyte count is 15,500/mm3, serum creatinine is 0.9 mg/dL, and plasma glucose is 90 mg/dL. Blood cultures are obtained, and empiric antibiotics are administered. CT scan of the head shows no hemorrhage or mass, and lumbar puncture is subsequently performed. Cerebrospinal fluid (CSF) results are as follows:
 CSF Gram stain reveals numerous gram-positive bacilli. Which of the following is the best treatment?
 (Multiple Choice)
4.9/5 (69)
(69) A 68-year-old man comes to the emergency department due to lightheadedness that occurs mainly upon standing. This has gotten worse today. He has fallen on 2 occasions, but he has not sustained any injuries. He has not had any chest pain or pressure, palpitations, or shortness of breath at rest. He has a history of coronary artery disease with a bare metal stent placed in the right coronary artery 2 years ago. His other medical problems include chronic obstructive lung disease, osteoarthritis, benign prostatic hyperplasia, and hypertension.
His medications include clopidogrel, aspirin, metoprolol, atorvastatin, ramipril, and a tiotropium inhaler. The dose of ramipril was increased recently and he was also started on tamsulosin for urinary symptoms. He quit smoking at the time of his stent placement after a 50 pack-year smoking history. He does not drink alcohol.
He does not appear to be in acute respiratory distress. His blood pressure is 97/70 mm Hg, pulse is 112/min and regular, and respirations are 16/min. His oxygen saturation is 98% on room air. His BMI is 20 kg/m2. His mucous membranes are moist. The neck veins appear distended while sitting and demonstrate a rapid "x" descent. There is a 4 cm left supraclavicular lymph node which is hard and mobile on palpation. The lungs have scattered expiratory wheezes. There are occasional heart beats that are auscultated at the apex but not felt in the radial pulse. There is 2+ lower extremity edema, more on the right compared to the left.
ECG shows sinus tachycardia, right bundle branch block, low-voltage QRS complexes, and nonspecific ST segment and T wave changes.
Which of the following is the most likely cause of this patient's current symptoms?
(Multiple Choice)
4.9/5 (81)
(81) A 72-year-old man comes to the emergency department due to right-sided numbness and weakness. The patient says his right side felt numb when he awoke at 5:00 AM, and he was unable to get out of bed due to right arm and leg weakness. The patient called an ambulance and arrived at the emergency department within 45 minutes. He was feeling well with no symptoms when he went to bed last night at 10:00 PM and does not know when his symptoms began. The patient has never had similar symptoms and has no headache, head trauma, fever, or chills. Medical conditions include hypertension and hyperlipidemia, but the patient is nonadherent with medical care and has not seen his primary care physician for the past several years. He has smoked a pack of cigarettes daily for 40 years.
Temperature is 36.5 C (97.7 F), blood pressure is 202/104 mm Hg, and pulse is 84/min and regular. The patient is alert but has frequent word-finding difficulty. Right facial droop is present. Motor strength and sensation to pinprick are decreased in the right upper and lower extremities. Babinski reflex is present on the right. Bedside swallow assessment shows no signs of aspiration.
Noncontrast CT scan of the head reveals no evidence of subarachnoid or intracerebral hemorrhage. Blood cell counts, serum chemistry studies, and coagulation tests are within normal limits. Blood glucose is 120 mg/dL. An ECG shows sinus rhythm with no acute ischemic changes, and chest radiograph is normal.
Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.9/5 (75)
(75) A 65-year-old man is brought to the emergency department due to left arm weakness and slurred speech, which he first noticed on waking this morning. He is accompanied by his wife, who says that his symptoms improved markedly 2 hours after they appeared but then significantly worsened again an hour ago. The patient has a history of coronary artery disease, hypertension, type 2 diabetes mellitus, and hyperlipidemia. A bare metal stent was placed in his left circumflex artery 7 years ago. The patient also has chronic kidney disease with an estimated glomerular filtration rate of 60 mL/min/1.73 m2. Medications include aspirin, metformin, carvedilol, and lisinopril. The patient has a 40-pack-year history. His mother had polycystic kidney disease, and his father died of a heart attack.
Blood pressure is 175/105 mm Hg and pulse is 65/min and regular. On neurologic examination, the patient is awake and alert. He has a left homonymous hemianopia, right forced gaze deviation, reduced sensation on the left side of the face, and left lower facial paresis. He also has left-sided hemiplegia with an extensor plantar response.
Which of the following is most likely responsible for this patient's current condition?
(Multiple Choice)
4.9/5 (72)
(72) A 35-year-old woman comes to the emergency department with fever, chills, and sore throat for the past 4 days. Except for a temperature of 38.3 C (101.0 F), her other vital signs are within normal limits. Examination shows pharyngeal and tonsillar erythema without exudates and bilateral tender cervical lymphadenopathy. The remainder of the examination is normal. Point-of-care testing for group A streptococcus is negative. The patient is diagnosed with viral pharyngitis and prescribed symptomatic therapy. She returns 3 days later due to a persistent fever, sore throat, and progressive dysphagia.
Her temperature now is 38.9 C (102.0 F), blood pressure is 118/78 mm Hg, pulse is 90 /min, and respirations are 16 /min. Physical examination remains unchanged from 3 days ago except that she appears more ill. Point-of-care testing for the Epstein-Barr virus is negative.
Which of the following is the most appropriate next step in management?
(Multiple Choice)
4.8/5 (94)
(94) A 40-year-old man comes to the emergency department and reports, "I think I have pinkeye." He was feeling well until 4 days ago when he developed fever, malaise, rhinorrhea, and a dry cough. He then noticed bilateral eye redness, irritation, and mucoid drainage. A red rash formed on his neck and trunk yesterday morning and spread to his face by the evening. The patient has no ill family members but recently returned from a missionary trip to Bangladesh. He is up to date on his vaccinations.
Temperature is 39 C (102.2 F), blood pressure is 122/76 mm Hg, pulse is 90/min, and respirations are 16/min. Examination shows conjunctival erythema and edema. Small white papules are present on the buccal mucosa. Chest is clear to auscultation. Skin examination shows an erythematous, maculopapular rash that blanches on palpation, as shown in the exhibit. 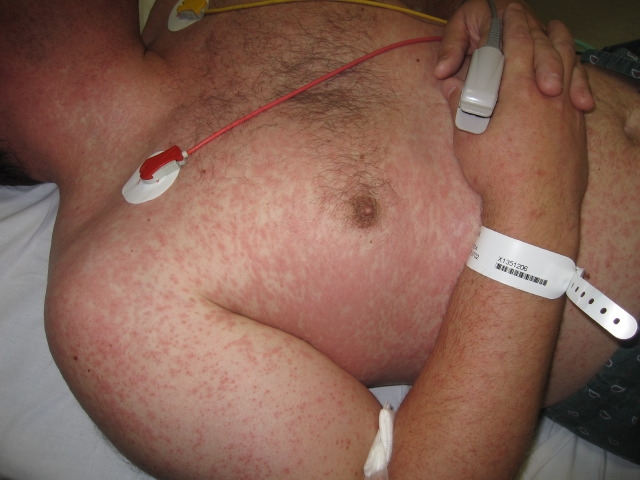 Laboratory results are as follows:
 Which of the following is the most appropriate next step in management of this patient's illness?
Laboratory results are as follows:
Which of the following is the most appropriate next step in management of this patient's illness? (Multiple Choice)
4.9/5 (75)
(75) A 36-year-old woman comes to the emergency department with 2 days of mild right eye pain worsened by eye movement. She also describes a persistent black spot in the center of her vision. She has no recent respiratory infection, fever, or headache.
On examination, there is no eye redness or exudate. Funduscopic examination shows mild hyperemia of the right optic disk.
MRI of the head shows several scattered ovoid-shaped, periventricular white matter lesions.
Which of the following is the best initial treatment for this patient?
(Multiple Choice)
4.8/5 (78)
(78) A 65-year-old man comes to the emergency room because of "head spinning" for the last 4 hours. He states that he has severe difficulty with his balance and feels like he is leaning to the right. He denies headache, double vision, muscle weakness, nausea, or vomiting. His past medical history is significant for hypertension, type 2 diabetes mellitus, hyperlipidemia, and mild intermittent asthma. He had a mild upper respiratory infection three weeks ago with a persistent sore throat until last week. His daily medications include glyburide, aspirin, lisinopril, and atorvastatin. He is an ex-smoker with a 35 pack-year smoking history.
His temperature is 36.7 C (98.6 F), blood pressure is 155/92 mm Hg, and pulse is 87/min with regular rhythm. On neurological examination, he is alert and cooperative. Cranial nerve examination reveals an up-beat torsional jerk nystagmus. Mild dysmetria is present on the right upon the finger-to-nose test.
His fingerstick glucose is 75 mg/dL. A non-contrast head CT shows no intracranial bleeding and is otherwise unremarkable.
Which of the following is the next best step in the management of this patient?
(Multiple Choice)
4.8/5 (80)
(80) A 39-year-old woman comes to the emergency department due to mild shortness of breath and right-sided pleuritic chest pain that began this morning. The patient underwent a mastectomy for left-sided breast cancer 2 weeks ago. She has a history of hives after eating seafood.
Blood pressure is 148/96 mm Hg, pulse is 114/min, and respirations are 21/min. Oxygen saturation is 91% on room air.
Chest x-ray is unremarkable and urine pregnancy test is negative. Creatinine is 0.8 mg/dL.
Which of the following is the most appropriate diagnostic approach?
(Multiple Choice)
4.8/5 (58)
(58) A 62-year-old man comes to the emergency department due to 2 hours of chest discomfort. He was eating a light dinner when he developed rapidly worsening mid-chest discomfort associated with nausea and weakness. For the last few days, the patient has also experienced "stomach flu" symptoms with episodic nausea and vomiting and decreased oral intake. Two weeks ago, he was diagnosed with an acute inferior wall myocardial infarction and received a bare metal stent to the right coronary artery. His hospital course was uncomplicated. Pre-discharge echocardiogram showed inferior and posterior wall hypokinesis and a left ventricular ejection fraction of 50%.
Temperature is 37.2 C (99 F), blood pressure is 98/64 mm Hg, and pulse is 55/min. Oxygen saturation is 99% on room air. BMI is 23 kg/m2. The patient appears uncomfortable. There is no jugular venous distention and the lungs are clear. A grade 2/6 holosystolic murmur is heard at the apex. The abdomen is nontender with no hepatomegaly. Peripheral pulses are symmetric.
ECG shows sinus bradycardia with 2-mm ST-segment elevation in leads II, III, and aVF.
Which of the following is the most likely diagnosis?
(Multiple Choice)
4.8/5 (75)
(75) A 43-year-old woman comes to the emergency department due to a 2-hour history of vertigo, occipital headache, and lip numbness. She reports having seen "floating lights" earlier, but her vision was not compromised. The patient has a history of migraine headaches without aura. She does not use tobacco, alcohol, or illicit drugs. Current medications include a combination estrogen-progestin oral contraceptive.
Blood pressure is 130/77 mm Hg and pulse is 98/min. Neurologic examination shows mild dysarthria but is otherwise normal.
MRI of the brain without contrast shows no acute intracranial abnormality.
Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.9/5 (87)
(87) A 72-year-old man with end-stage renal disease comes to the emergency department due to abdominal pain for the past 6 hours. The pain started in the lower left abdomen at the end of the hemodialysis session and has remained steady in intensity. The pain does not radiate and is unchanged with movement. The patient rushed to the hospital after noticing bright red blood in the bowel movement 30 minutes ago. He has had mild nausea but no vomiting, back pain, fever, or urinary symptoms. Medical problems include hypertension, type 2 diabetes mellitus, hyperlipidemia, depression, and gastritis. The patient developed anuric end-stage renal disease due to hypertensive and diabetic nephropathy and has been receiving maintenance hemodialysis for the past several years. He reports no recent antibiotic use or travel and has not eaten anything out of the ordinary. The patient is a former smoker with a 30-pack-year history and does not use alcohol or illicit drugs.
Temperature is 37.4 C (99.3 F), blood pressure is 110/80 mm Hg, pulse is 88/min and regular, and respirations are 16/min. Abdominal examination shows tenderness in the left lower quadrant with decreased bowel sounds, but there is no rebound tenderness or rigidity. Rectal examination reveals stool mixed with bright red blood.
Laboratory results are as follows:
 Which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.8/5 (61)
(61) A 31-year-old man comes to the emergency department because of a high-grade fever and multiple painful skin nodules that began 2 days ago. The skin lesions are red and painful, and gradually developed on both arms before spreading to the chest and legs. He also notes fatigue, poor appetite, dry cough, and mild shortness of breath. One week ago, the patient was helping his father in the garden.
The patient had an allogeneic bone marrow transplantation for acute leukemia 3 months ago complicated by pneumonia, catheter-associated bacteremia, and chronic gastrointestinal graft-versus-host-disease. His medications include prednisone, valganciclovir, and trimethoprim/sulfamethoxazole.
His temperature is 39.4 C (103.0 F), blood pressure is 90/60 mm Hg, pulse is 106/min, and respirations are 28/min. Examination shows dry mucus membranes, diffuse crackles in the lung fields, and mild splenomegaly. Skin examination reveals dry skin with multiple raised, erythematous, and tender nodules on his upper extremities, lower extremities, and upper chest.
Laboratory results are as follows:
 The patient is admitted to the hospital and started on empiric antibiotic therapy. Blood cultures are obtained and grow mold-like organisms.
Which of the following is the most likely cause of his condition?
The patient is admitted to the hospital and started on empiric antibiotic therapy. Blood cultures are obtained and grow mold-like organisms.
Which of the following is the most likely cause of his condition? (Multiple Choice)
4.8/5 (93)
(93) A 66-year-old man comes to the emergency department due to abdominal pain and nausea. He has had no vomiting or bloody stools. Yesterday he underwent a screening colonoscopy, which revealed scattered diverticulosis and 2 polyps that were then removed. The patient's other medical conditions include hypertension and gastroesophageal reflux disease.
Temperature is 38.1 C (100.6 F), blood pressure is 110/70 mm Hg, and pulse is 98/min. Mucous membranes are moist. The abdomen is tender in the periumbilical and left lower quadrants with no rebound tenderness.
Laboratory results are as follows:
 Upright abdominal radiographs show no free air under the diaphragm.
Which of the following is the best next step in management of this patient?
Upright abdominal radiographs show no free air under the diaphragm.
Which of the following is the best next step in management of this patient? (Multiple Choice)
4.9/5 (87)
(87) A 23-year-old woman comes to the emergency department after an episode of syncope. She began feeling unwell 6 days ago with fever, throbbing pain behind the eyes, diffuse myalgias, and abdominal pain. Her fever improved 2 days ago, but she noticed an erythematous skin rash developing on her trunk and upper and lower extremities. A few hours prior to admission, the patient had an episode of epistaxis and a syncopal episode when cleaning the bathroom. She has no other medical problems. She returned from a trip to southern Mexico 10 days ago and states that one of her travel companions also has had fevers and myalgias. The patient received the typhoid vaccine before her trip.
Her temperature is 37.2 C (99 F), blood pressure is 86/60 mm Hg, pulse is 108/min, and respirations are 14/min. Examination shows mild abdominal tenderness with no hepatosplenomegaly. Examination of the hands is shown below.
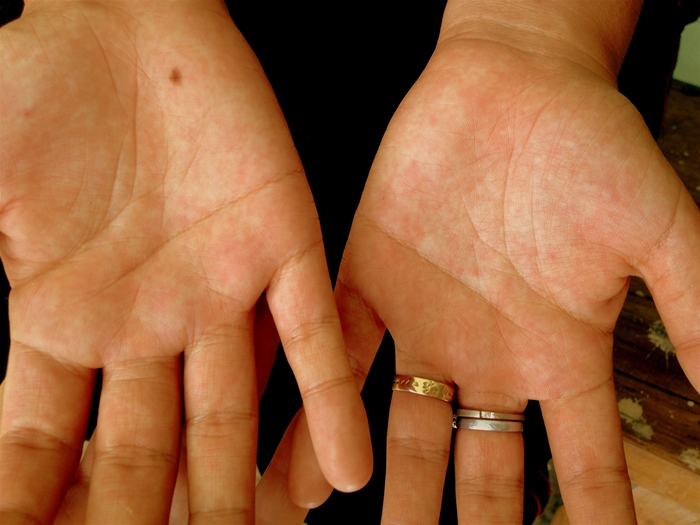 Laboratory studies are as follows:
 Urinalysis is normal. Which of the following is the most likely diagnosis?
Laboratory studies are as follows:
Urinalysis is normal. Which of the following is the most likely diagnosis? (Multiple Choice)
4.8/5 (83)
(83) A 23-year-old woman is brought to the emergency department with fever, rash, and decreased level of consciousness. She is accompanied by her boyfriend. The patient became increasingly confused throughout the morning and eventually unarousable, prompting him to call an ambulance.
After initial evaluation, lumbar puncture is performed and empiric antibiotic therapy is started. Cerebral spinal fluid shows Gram-negative diplococci. She is admitted to the intensive care unit.
Which of the following individuals needs antibiotics for post-exposure prophylaxis?
(Multiple Choice)
4.8/5 (76)
(76) A 42-year-old woman comes to the emergency department with fever and a skin rash. She was diagnosed with trigeminal neuralgia and started on carbamazepine 3 weeks ago.
The patient's temperature is 38.9 C (102 F). There is diffuse confluent erythema involving 60% of the body, palpable generalized lymphadenopathy, and symmetrical facial swelling. There are no mucosal lesions.
Her aspartate aminotransferase level is 150 U/L, eosinophil count is 800/mm3, and serum creatinine is 0.9 mg/dL.
Which of the following is the most likely diagnosis?
(Multiple Choice)
4.8/5 (64)
(64) A 41-year-old man with a history of bipolar disorder is brought to the emergency department by his mother for confusion and agitation that she noticed while visiting today. The patient denies suicidal ideation and intentional overdose of his medication or illicit drugs. His only known medication is lithium.
His temperature is 37.2° C (99° F), blood pressure is 94/52 mm Hg, pulse is 89/min, and respirations are 18/min. The patient's pulse oximetry is 96% on room air. Examination shows dry mucous membranes, clear lung fields, and normal first and second heart sounds. The patient has a flat affect and does not answer most questions. He has a significant tremor in both hands.
 Electrocardiogram shows normal sinus rhythm. Intravenous fluids are initiated.
Which of the following is the most appropriate next step in management?
Electrocardiogram shows normal sinus rhythm. Intravenous fluids are initiated.
Which of the following is the most appropriate next step in management? (Multiple Choice)
4.9/5 (87)
(87) A 73-year-old man is brought to the emergency department by his daughter for mild confusion, double vision, and frequent falls over the past 2-3 weeks. He has also been having headaches, decreased appetite, and nausea. His past medical history is significant for diet-controlled type 2 diabetes mellitus and hypertension. The patient underwent resection of a malignant melanoma 2 months ago.
His blood pressure is 142/88 mm Hg and heart rate is 67/min. He appears comfortable and answers questions appropriately. There is no nuchal rigidity. Neurologic examination shows diplopia, mild weakness and spasticity of the right arm, and ataxic gait.
Which of the following is the next best step in management of this patient?
(Multiple Choice)
4.9/5 (86)
(86) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)