



 Chat with AI
Exam 3: Office/Health Center

Exam 1: Emergency Department218 Questions
Exam 2: In-patient Facilities128 Questions
Exam 3: Office/Health Center900 Questions
Select questions type


A 49-year-old woman, gravida 1 para 1, comes to the office due to leakage of urine. The patient first noticed intermittent loss of urine a few years ago. The leakage has progressively worsened and now she is constantly leaking a small amount of urine. The patient soaks through a thin incontinence pad 2 or 3 times a day. She has no dysuria, hematuria, or urge to void.
The patient has type 1 diabetes mellitus managed with an insulin pump. Her last hemoglobin A1c was 10.4%. At age 30 she had an operative vaginal delivery complicated by a large perineal laceration. She does not use tobacco, alcohol, or illicit drugs.
Vital signs are normal. Pelvic examination reveals leakage of urine that increases with Valsalva. Postvoid residual volume is increased. There is decreased sensation to light touch and pinprick involving the perineum and both feet.
Laboratory results are as follows:
 Which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.9/5  (81)
(81) A 28-year-old primigravid woman at 20 weeks gestation comes to the office for asthma follow-up. Her asthma has been managed with combination mometasone-formoterol for relief as needed. She has never been hospitalized for asthma. Prior to pregnancy, the patient used a reliever inhaler no more than 1 or 2 times per month. However, over the past 2 months, she has used her inhaler several days per week. The patient also reports occasionally awakening at night with cough and wheezing. She denies any specific asthma triggers and does not own any pets.
Temperature is 36.7 C (98 F), blood pressure is 110/70 mm Hg, pulse is 84/min, and respirations are 16/min. Pulse oximetry is 96% on room air. The patient is not in acute distress and is breathing comfortably. Lung examination demonstrates good air entry with scattered expiratory wheezing bilaterally.
Results of spirometry are as follows:
 Which of the following is the most appropriate pharmacotherapy?
 (Multiple Choice)
4.8/5 (80)
(80) A 45-year-old woman comes to the office with 3 months of right foot pain. Her symptoms started with nighttime numbness at the bottom of the right foot that has progressed to burning and aching pain. She also has vague discomfort while standing or sitting, especially when wearing shoes. The patient has a history of rheumatoid arthritis, which has been stable with weekly etanercept and as-needed ibuprofen. She does not use tobacco, alcohol, or illicit drugs.
Examination shows swollen hand joints without tenderness and mild radial deviation of the wrist. She has mild hallux valgus deformity without focal tenderness on foot examination. Light tapping behind the right medial malleolus elicits tingling. There is intact sensation to light touch and vibration.
Which of the following is the most likely cause of this patient's foot pain?
(Multiple Choice)
5.0/5 (88)
(88) A 28-year-old man comes to the emergency department due to worsening dyspnea, cough, and blood-streaked sputum for the last 3 days. He has had no fatigue, fever, chills, upper respiratory symptoms, skin rash, eye symptoms, or joint pains. The patient has no history of lung disease but takes ibuprofen occasionally for knee pain. He does not use tobacco, alcohol, or illicit drug. His father had a myocardial infarction at age 65 and his mother has rheumatoid arthritis.
Blood pressure is 150/90 mm Hg, pulse is 100/min, and respirations are 24/min. Bilateral crackles are present in both lung bases and mid-lung fields. Extremity examination reveals 1+ pitting edema to the mid-shins bilaterally. The remainder of the examination is unremarkable.
Laboratory results are as follows:
 Chest x-ray shows diffuse pulmonary opacities.
Which of the following is the most likely diagnosis in this patient?
Chest x-ray shows diffuse pulmonary opacities.
Which of the following is the most likely diagnosis in this patient? (Multiple Choice)
4.8/5 (79)
(79) A 57-year-old woman returns to the physician because of a worsening, productive cough and generalized weakness. She was healthy until approximately 3 months ago when she was diagnosed with her first episode of pneumonia and treated with antibiotics. She felt better but had a lingering cough. Three weeks ago, she was admitted to the hospital for another episode of pneumonia and was treated with 10 days of antibiotics. She has lost approximately 10 pounds (4.5 kg) in these 3 months. One expectorated sputum culture from the last admission grew Mycobacterium avium-intracellulare complex (MAC) at 20 days incubation. Testing for HIV infection was negative.
Her other medical problems include type 2 diabetes mellitus, allergic rhinitis, and chronic hypertension. She gets sinus infections once every 2 to 3 years requiring antibiotics. Four months ago, she was diagnosed with Bell's palsy and was treated with a course of prednisone and acyclovir, with complete recovery. Her medications include lisinopril, hydrochlorothiazide, metformin, nasal fluticasone, and loratadine. She has never smoked.
Her temperature is 37.8 C (100.1 F), blood pressure is 112/78 mm Hg, and pulse is 98/min. Examination reveals patchy crackles in both lungs. Heart sounds are normal. There are no skin rashes or swollen joints.
Her chest-x ray and CT scan show multiple nodular opacities with some cavities. Some bronchiectatic changes are noted in the right middle lobe and left lingula. Serum chemistries are within normal limits.
Which of the following is the most appropriate next step in management?
(Multiple Choice)
4.8/5 (62)
(62) A 32-year-old man comes to the physician at his wife's insistence for evaluation of depression and anxiety. He was recently fired from his job as a computer technician due to frequent lateness, mistakes, and failure to meet deadlines. The patient feels discouraged about losing his job, but explains that "it was impossible to sit still staring at a boring computer screen all day." He is worried about finding a new job and his finances. The patient still enjoys sports and socializing with friends and has no sleep or appetite disturbance. His wife complains that he is "impossible to live with" because he never listens and leaves the house in a total mess. The patient considers himself to be very intelligent and creative but has been an underachiever since grade school, when he frequently got in trouble. He has no psychiatric history. The patient drinks 1 or 2 beers on most days and last used marijuana 6 months ago. He does not use other drugs.
Which of the following is the most likely diagnosis?
(Multiple Choice)
5.0/5 (76)
(76) A 32-year-old right-hand-dominant woman living in New Hampshire comes to the physician complaining of right wrist pain for the past 3 months. She has no history of tick bites, recent travel, or illness in the family. Review of systems is negative for fever, pain or swelling in any other joints, skin rash, or recent gastrointestinal or genitourinary infections. The patient is sexually active in a monogamous relationship. She delivered her first child 4 months ago. She smokes marijuana occasionally.
Her temperature is 37.2° C (99° F), blood pressure is 110/78 mm Hg, pulse is 78/min, and respirations are 12/min. She weighs 80 kg (176 lb). There is a sharp tenderness on palpation of the radial styloid at the wrist. The pain is aggravated on ulnar deviation of the wrist after she is asked to make a fist over the thumb. There is no synovitis or tenderness noted on any other joints. The right hand x-ray is shown below.
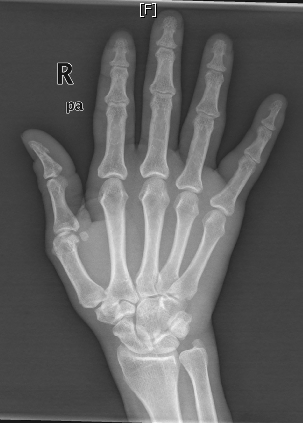 Which of the following is the most likely diagnosis?
 (Multiple Choice)
4.9/5 (91)
(91) An 83-year-old community-dwelling woman comes to the physician for routine follow-up. She has lost approximately 10 lbs (4.5 kg) over the past year and her clothes no longer fit. She states she has a good appetite and intact senses of both taste and smell. She has dentures which fit well and no oral complaints. She lives alone and performs all of her own activities of daily living; however, she no longer drives and needs help with the maintenance of her home. She denies swallowing difficulties, nausea or vomiting, abdominal pain, or change in bowel habits. She denies any cough, chest pain, or lower extremity swelling. Her mood is good 'most of the time.'
Her other medical problems include osteoporosis, type 2 diabetes, osteoarthritis, stress urinary incontinence, and impaired hearing and vision. Her medications include hydrochlorothiazide, lisinopril, glyburide, ibuprofen, and alendronate.
Her blood pressure is 130/84 mm Hg and pulse is 84/min. Her BMI is 19.4 kg/m2. She is well-groomed and pleasant. General physical examination including breast examination is unremarkable. Her score on a Mini-Mental State Exam is 26/30. Stool test for occult blood is negative. Fingerstick blood glucose is 120 mg/dL. Laboratory results are as follows:
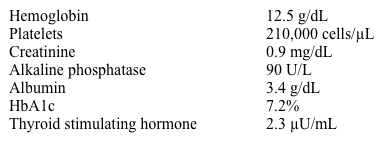 Which of the following is most likely to establish the cause of this patient's weight loss?
 (Multiple Choice)
4.8/5 (78)
(78) A 52-year-old man comes to the office due to progressive erectile dysfunction and loss of libido for the last 8 months. He is unable to obtain an erection and also has malaise and poor energy. The patient has no history of headaches, visual loss, anabolic steroid use, daytime sleepiness, or prior testicular injury. His other medical problems include type 2 diabetes mellitus, hypertension, and hyperlipidemia. Medications include metformin, atorvastatin, and ramipril. The patient is married and has 2 children.
Blood pressure is 120/80 mm Hg and pulse is 66/min. BMI is 31 kg/m2. The patient has normal secondary sexual characteristics without gynecomastia. Peripheral vision is intact on confrontation testing. The testes are normal in size with a soft consistency. The remainder of the physical examination is normal.
Laboratory results are as follows:
 Repeat serum testosterone is 136 ng/dL, with serum FSH of 5 mU/mL, LH of 4 mU/mL, and prolactin of 10 ng/mL. Which of the following is the most appropriate next step in addressing this patient's current condition?
 (Multiple Choice)
4.9/5 (74)
(74) A 60-year-old man comes to the office due to 3 months of progressive weakness and fatigue. The patient could previously walk 1-2 miles with no difficulty but now gets tired walking across his house. He has had no excessive daytime sleepiness and feels refreshed after a full night of sleep. The patient reports no fever, night sweats, dyspnea, cough, feelings of depression, or anhedonia but has lost 7 kg (15.4 lb) in the last 3 months. His appetite is unchanged, and he is eating the same food as usual but finds that he gets full more quickly than usual. The patient also reports vague abdominal discomfort but has had no dysphagia, melena, or changes in bowel habits. His medical problems include hypertension and hyperlipidemia. The patient is a former smoker with a 30-pack-year history, and he drinks alcohol occasionally. He has not recently traveled.
Vital signs are within normal limits. BMI is 26 kg/m2. There is no scleral icterus, lymphadenopathy, rash, or extremity edema. The thyroid is normal to palpation. Cardiopulmonary examination shows no abnormalities. A firm, nontender mass is palpable in the left upper abdominal quadrant down to the level of the umbilicus. There is no hepatomegaly. Stool test for occult blood is negative.
Laboratory results are as follows:
 The peripheral blood smear is shown in the exhibit.
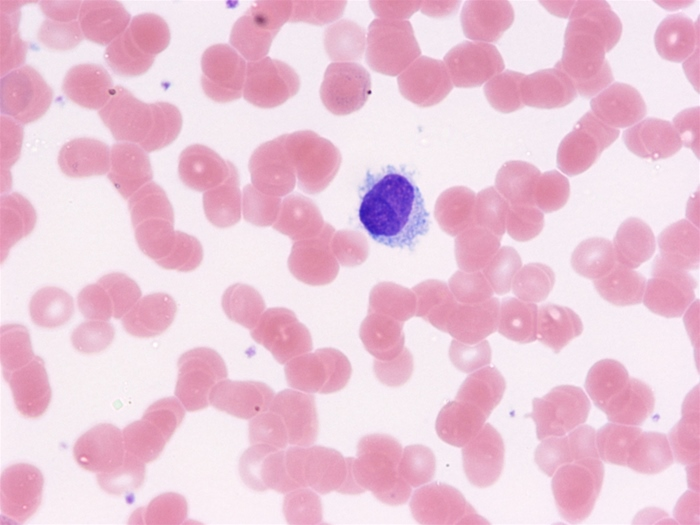 Which of the following is the most appropriate next step in management of this patient?
The peripheral blood smear is shown in the exhibit.
Which of the following is the most appropriate next step in management of this patient? (Multiple Choice)
4.7/5 (96)
(96) A 42-year-old woman comes to the office for evaluation of amenorrhea for the past 3 months. She previously had relatively regular menses, typically occurring monthly with 4-5 days of moderate bleeding. The patient has had 1 or 2 irregular cycles each year, but usually went no more than 6-8 weeks without a menstrual period. She has had increasing fatigue and a 2.7-kg (6-lb) weight gain over the past few months, but has had no changes in vision or in heat or cold intolerance. She has no chronic medical conditions. The patient had a cesarean delivery with a bilateral tubal ligation 10 years ago.
Blood pressure is 130/80 mm Hg and pulse is 78/min. BMI is 23 kg/m2. Cardiopulmonary examination is normal. The abdomen is soft and nontender. Pelvic examination reveals a uniformly enlarged, anteverted uterus; there are no adnexal masses.
Which of the following is the most likely diagnosis in this patient?
(Multiple Choice)
4.8/5 (77)
(77) A 32-year-old man comes to the physician because of facial pain and fever. He developed a "cold" one week ago with symptoms consisting of mild malaise, sore throat, clear nasal discharge, and productive cough of small amounts of gray sputum. He felt that he was improving, but now has 1 day of fever, chills, purulent nasal discharge, and facial fullness with pain. His pain is worsened by bending over. He also reports aching of his upper left molars. He is in good health, takes no medications, and has no HIV risk factors. He has no known drug allergies.
His temperature is 39.2 C (102.5 F), pulse is 90/min, and respirations are 14/min. He appears uncomfortable. There is pain to light tapping over his left maxillary region. There is swelling of his turbinates and purulent nasal discharge in his left naris. There are no nasal polyps. His pharynx shows no erythema or exudates. Cardiopulmonary examination is within normal limits.
Which of the following is the best next step in management?
(Multiple Choice)
4.8/5 (88)
(88) A 72-year-old man comes to the physician for a follow-up visit. Three months ago, he was diagnosed with localized prostate cancer with no evidence of metastatic disease. He was treated with definitive external beam radiation therapy. The patient completed his treatment 2 weeks ago. He now complains of pelvic discomfort and increased urinary frequency. These began at the end of his radiation treatment but have improved partially since treatment was completed.
Vital signs are within normal limits. Examination shows a normal-appearing external anorectal area. The abdomen is soft and bowel sounds are normal.
Urinalysis is normal. Laboratory results are as follows:
 This patient is at the greatest risk for which of the following long-term complications?
 (Multiple Choice)
4.7/5 (71)
(71) A 33-year-old life-long asthmatic comes to the physician with 3 weeks of productive cough of thick brownish sputum, increased wheezing and dyspnea, right-sided pleuritic chest pain, chills, and fever. On occasion, his sputum is streaked with blood. He also notes fatigue and feeling "out of it." His asthma is generally managed with budesonide/formoterol inhaler, and his last exacerbation requiring steroid taper was approximately 2 months ago.
He also took prednisone 20 mg for 4 days at the onset of symptoms three weeks ago "because I had some in the house anyway." The steroids helped somewhat, but the symptoms worsened when he ran out of medication. He has had 2 previous "lung infections on the left side" with similar presentation in the past 3 years. The patient has never been intubated or admitted to an intensive care unit. He denies smoking or recent travel. He had a negative test for HIV 7 months ago.
His temperature is 38.3 C (101 F), blood pressure is 130/80 mm Hg, pulse is 70 /min, and respirations are 16 /min. Pulse oximetry shows 96% on room air. Examination shows diffuse wheezing throughout the lungs.
Laboratory results are as follows:
 Chest x-ray reveals a right upper-lobe infiltrate and possible early bronchiectasis on the left side.
In addition to initiating glucocorticoid therapy, what is the next step in establishing the diagnosis?
Chest x-ray reveals a right upper-lobe infiltrate and possible early bronchiectasis on the left side.
In addition to initiating glucocorticoid therapy, what is the next step in establishing the diagnosis? (Multiple Choice)
4.7/5 (81)
(81) A 42-year-old woman comes to the physician before undergoing tooth extraction. She recently saw a dentist for lower jaw pain and was told that she needs extraction of a left lower molar. She has a past history of rheumatic heart disease and had mitral valve replacement at 35 years of age with a mechanical valve. She moved to the United States from the Philippines 3 years ago. Her past medical history is otherwise unremarkable. She takes warfarin daily and has been taking amoxicillin for the past 7 days for presumed "tooth infection."
Physical examination reveals crisp opening and closing clicks of a mechanical prosthetic mitral valve. No abnormal murmurs are heard. Her last INR was 2.6.
Which of the following is the most appropriate management for this patient?
(Multiple Choice)
4.7/5 (82)
(82) A 40-year-old obese man comes to the physician because of exertional dyspnea, fatigue, and poor energy over the past year. He was diagnosed with obstructive sleep apnea and started on nocturnal continuous positive airway pressure (CPAP) six months ago with mild improvement of his symptoms. He reports compliance with CPAP "most of the time." He denies cough, chest pain, dizziness, or syncope. His other medical problems include hypertension, glucose intolerance, and pain in both hips and knees which increases at the end of the day. He does not use tobacco, alcohol, or illicit drugs.
His blood pressure is 152/90 mm Hg, pulse is 70/min, and respirations are 16/min. Oxygen saturation is 94% on room air. His BMI is 44 kg/m2. Jugular venous pressure is difficult to estimate. Lungs are clear to auscultation. Heart sounds are distant but no murmurs are heard. There is 2+ symmetric peripheral edema.
His hemoglobin level is 16.2 g/dL and his serum TSH is 2.5 mU/L.
Chest x-ray shows low lung volumes but is unremarkable otherwise. Spirometry shows an FEV1 of 70% predicted and an FEV1/FVC ratio of 90%. Transthoracic echocardiography is limited by body habitus, but shows mild right ventricular enlargement.
Which of the following is the best next step in managing this patient?
(Multiple Choice)
4.9/5 (79)
(79) A 46-year-old woman is being evaluated for tiredness, low energy level, and poor exercise tolerance. She also complains of joint pains and takes non-steroidal anti-inflammatory agents. Her past medical history is significant for hypertension and type 2 diabetes mellitus.
Her blood pressure is 130/80 mm Hg, pulse is 96/min, and respirations are 12/min. Her BMI is 32 kg/m2. The cardiac, pulmonary, and abdominal examinations are within normal limits. Her skin shows areas of hypopigmentation consistent with vitiligo in the upper extremities bilaterally.
Her laboratory studies are shown below.
 Bone marrow aspiration is performed, and the aspirate is stained with Prussian blue for iron. It shows dense iron staining in macrophages but no staining of erythrocyte precursors.
Which of the following is the most likely diagnosis?
Bone marrow aspiration is performed, and the aspirate is stained with Prussian blue for iron. It shows dense iron staining in macrophages but no staining of erythrocyte precursors.
Which of the following is the most likely diagnosis? (Multiple Choice)
4.8/5 (74)
(74) A 77-year-old woman is brought to the office by her husband due to memory impairment and increasingly bizarre nighttime behavior over the last year. The patient stopped driving last year as she frequently became lost in familiar neighborhoods. She can no longer cook without supervision as she occasionally forgets to turn off the burner. The patient has said she sees a man outside her window at night, but her husband has never found anyone there. She has also begun to vocalize in her sleep; more recently, she has kicked and punched her husband while sleeping. The patient has become increasingly distractible and sometimes stops responding mid-conversation for brief periods.
Blood pressure is 122/78 mm Hg supine and 98/68 mm Hg standing. Pulse is 64/min supine and 85/min standing. Physical examination is significant for very mild bilateral limb rigidity in the upper extremities on passive range of motion, which the patient does not find bothersome. Gait is somewhat slowed; the patient's husband reports that she has fallen more than once. She scores 21 out of 30 on the Montreal Cognitive Assessment.
Which of the following is the most likely diagnosis?
(Multiple Choice)
4.8/5 (85)
(85) A 74-year-old man comes to the physician for follow-up of type 2 diabetes mellitus. His diabetes is managed with diet and metformin, and he has shown good compliance with medical visits. The patient has no history of chest pain, dyspnea, lightheadedness, syncope, or falls. He does not use tobacco, alcohol, or illicit drugs.
Blood pressure and pulse are 145/75 mm Hg and 67/min while supine, and 122/64 mm Hg and 72/min after standing for 2 minutes. Physical examination is otherwise unremarkable. His last HbA1c was 7% and creatinine was 0.8 mg/dL. The postural blood pressure changes are reproduced during the subsequent visit, but the patient consistently reports no symptoms.
This patient has an elevated risk for which of the following?
(Multiple Choice)
4.8/5 (83)
(83) A 63-year-old woman is admitted to the hospital for sudden-onset shortness of breath and chest heaviness that began 2 hours ago. She had a similar episode of shortness of breath with hypertensive urgency 8 months ago. An echocardiogram at that time showed left ventricular hypertrophy, modest diastolic dysfunction, and an ejection fraction of 60%. Stress testing showed no evidence of ischemia. The patient's medical problems include a 5-year history of intermittent claudication, hypertension, hyperlipidemia, and type 2 diabetes mellitus. She is a former smoker with a 35-pack-year history. She works as an accountant and admits to feeling stressed at work.
Blood pressure is 210/100 mm Hg, pulse is 110/min, and respirations are 20/min. BMI is 34 kg/m2. Pulses are equal in all 4 extremities. She appears dyspneic. Jugular venous pressure is normal. There are bibasilar lung crackles and a prolonged expiratory phase of respiration.
ECG shows sinus tachycardia, left ventricular hypertrophy, and nonspecific T-wave abnormalities. Chest x-ray reveals pulmonary edema. The patient is treated with intravenous furosemide, antihypertensive agents, and noninvasive positive-pressure ventilation.
Four hours later, her symptoms resolve and she appears comfortable. Blood pressure is 144/89 mm Hg and pulse is 75/min.
Laboratory results are as follows:
 Urinalysis shows 1+ protein.
This patient should be evaluated for which of the following conditions?
Urinalysis shows 1+ protein.
This patient should be evaluated for which of the following conditions? (Multiple Choice)
4.9/5 (90)
(90) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)