



 Chat with AI
Exam 3: Office/Health Center

Exam 1: Emergency Department218 Questions
Exam 2: In-patient Facilities128 Questions
Exam 3: Office/Health Center900 Questions
Select questions type


A 54-year-old woman comes to the physician with complaints of weakness and skin rash. She thinks that her symptoms could be related to medications she started on over the last 6 months. She was diagnosed with hypertension and hyperlipidemia and takes valsartan, amlodipine, chlorthalidone, and atorvastatin. It has become progressively more difficult for her to perform activities of daily living. She has no family history of skin disease.
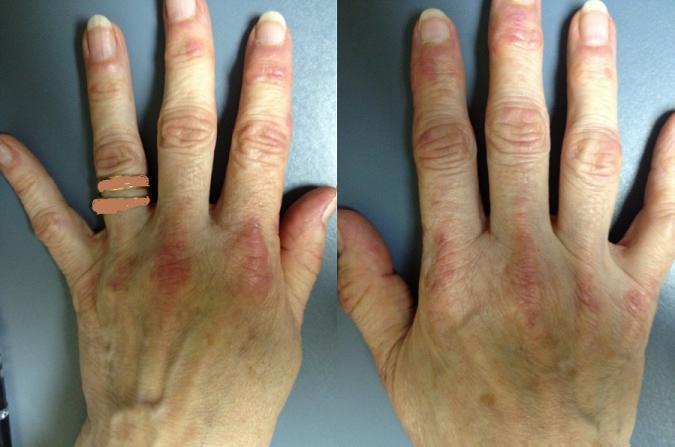
Her vital signs are normal. BMI is 33 kg/m2. Physical examination findings are shown in the pictures below. She has decreased muscle strength (4/5) in the quadriceps muscles bilaterally. Deep-tendon reflexes are 1+ and symmetrical. The remainder of the physical examination is within normal limits.
 Laboratory results are as follows:
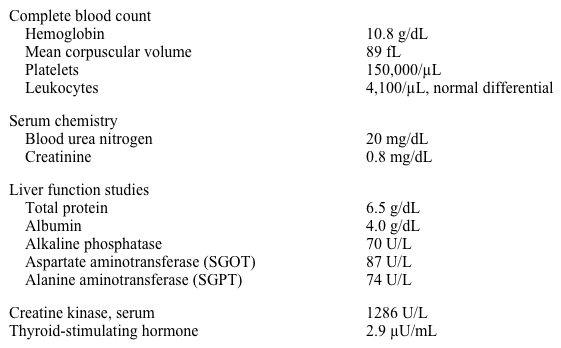 Which of the following is the most likely diagnosis?
Laboratory results are as follows:
Which of the following is the most likely diagnosis? (Multiple Choice)
4.9/5  (59)
(59) A 46-year-old man with kyphoscoliosis comes to the office due to fatigue and progressive shortness of breath over the last year. He has no other medical problems and does not use tobacco.
On examination, the angle of scoliosis is 67 degrees, and kyphosis deformity is above the level of T10.
Which of the following is the main mechanism of respiratory compensation in this patient?
(Multiple Choice)
4.8/5 (86)
(86) An asymptomatic 52-year-old man is evaluated for a nonobstructing mass in his left colon (32 cm from the anorectal verge) found on routine screening colonoscopy. There were no other lesions. The mass was biopsied and diagnosed as grade II colon adenocarcinoma. His other medical problems include hypertension treated with lisinopril and amlodipine. The patient is a former smoker with a 20-pack-year history. He drinks 1 or 2 cans of beer per week. His father died of lung cancer at age 80.
Temperature is 36.7 C (98 F), blood pressure is 140/80 mm Hg, pulse is 72/min, and respirations are 18/min. BMI is 25 kg/m2. Lungs are clear to auscultation. No enlarged lymph nodes are present. Abdominal examination reveals no masses. The liver span is normal, and the spleen cannot be palpated.
Laboratory results are as follows:
 CT scan of the chest, abdomen, and pelvis shows a 2.5-cm left colonic lesion that appears to invade the serosa and an enlarged 1.5-cm adjacent lymph node. Two 1.5-cm masses with irregular borders are seen within the right lobe of the liver close to, but not abutting, the capsule. There are no other imaging abnormalities.
Which of the following is the most appropriate course of action in management of this patient?
CT scan of the chest, abdomen, and pelvis shows a 2.5-cm left colonic lesion that appears to invade the serosa and an enlarged 1.5-cm adjacent lymph node. Two 1.5-cm masses with irregular borders are seen within the right lobe of the liver close to, but not abutting, the capsule. There are no other imaging abnormalities.
Which of the following is the most appropriate course of action in management of this patient? (Multiple Choice)
4.9/5 (69)
(69) A 45-year-old woman comes to the physician with exertional shortness of breath and lower-extremity swelling over the last 6 weeks. She has no chest pain, dizziness, or orthopnea. She also suffers from chronic diarrhea that has not responded to dietary modifications. Colonoscopy with biopsies done 6 months ago was unremarkable. The patient has been taking herbal supplements for hot flashes that she describes as severe. She does not use tobacco or illicit drugs but does drink a few beers on weekends.
Her blood pressure is 142/80 mm Hg and pulse is 98/min. Her body mass index is 26 kg/m2. Purplish, blanching telangiectasias are seen on her upper lip and nose. Jugular venous distention is present. A 3/6 holosystolic murmur is heard at the lower sternum that increases with inspiration. Lungs are clear to auscultation. The liver is enlarged and pulsatile. There is 2+ edema of both lower extremities. The remainder of the examination is within normal limits.
Laboratory results are as follows:
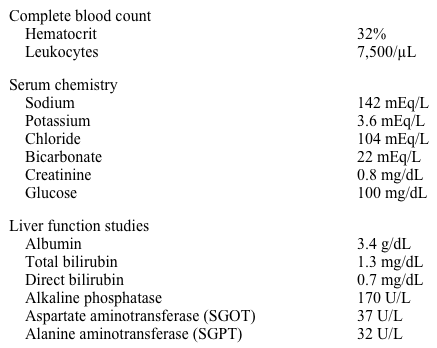 Which of the following is the most likely diagnosis?
 (Multiple Choice)
4.9/5 (77)
(77) An 85-year-old woman comes to the office for follow-up of chronic conditions. She has occasional knee pain due to osteoarthritis, for which she takes ibuprofen. The patient also has a history of hypertension treated with amlodipine; her blood pressure had been well controlled in the past, but several readings over the past year have been high. She insists that she takes her medications as prescribed, but pharmacy records indicate that she has not picked up her medication on several occasions. The patient's husband passed away a year ago, and since then she has lived with a family friend to share expenses. She has no difficulty cooking, cleaning, dressing, or bathing. She cries sometimes when she thinks about him, but she also enjoys memories of good times they had together.
Temperature is 36.7 C (98 F), blood pressure is 162/96 mm Hg, pulse is 78/min, and respirations are 12/min. Examination shows no swelling or warmth of the joints. There is a small effusion in the right knee and mild restriction on extension of both knees. There is no joint laxity or instability. The remainder of the examination is unremarkable.
Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.9/5 (71)
(71) A 65-year-old man is brought to the office due to a 2-year history of progressive cognitive decline. The patient has difficulty finding the right words and recognizing faces, and he has stopped driving because he gets lost on the streets. Over the past 6 months, he has had frequent falls, dizziness on standing, and urinary incontinence. The patient increasingly requires his wife's help to perform activities of daily living.
His seated blood pressure is 120/80 mm Hg and standing blood pressure is 100/70 mm Hg. Pulse increases from 90/min when sitting to 100/min when standing. Mini-mental state examination score is 16/30. The patient's face appears masked, but the rest of the cranial nerves are intact. He has bilaterally symmetrical cogwheel rigidity and bradykinesia in the arms but no tremor. His gait is slow and wide-based. The remainder of the patient's neurologic examination shows no abnormalities.
Basic blood work and spinal fluid analysis results are unremarkable. An MRI of the brain reveals diffuse cerebral and pontocerebellar atrophy that is out of proportion to the patient's stated age. A routine electroencephalogram shows diffuse slowing.
Which of the following is the most likely diagnosis?
(Multiple Choice)
4.8/5 (89)
(89) A 32-year-old woman comes to the office at her husband's insistence for evaluation of weight loss. She is unconcerned about her weight loss and explains that she is training for a marathon and would like to lose more to reach an ideal running weight. The patient has lost 15.0 kg (33 lb) in the last 6 months and has not had a menstrual period for the past 2 months. Medical history is significant for depression in her 20s that responded well to selective serotonin reuptake inhibitors. Current medications include multivitamins, polyethylene glycol for constipation, and calcium and green tea extract supplements. She has no depressed or anxious mood, cold or heat intolerance, or change in sleep pattern.
Temperature is 36.4 C (97.5 F), blood pressure is 105/60 mm Hg, pulse is 56/min and regular, and respirations are 12/min. There is no orthostasis. BMI is 16 kg/m2. There is no edema. The abdomen is soft and nontender.
Complete blood count and blood chemistry studies are normal. Pregnancy test is negative.
In addition to referral for nutritional rehabilitation, which of the following is the most appropriate treatment for this patient?
(Multiple Choice)
4.8/5 (73)
(73) Following 2 case reports about the potential for allopurinol to improve outcomes in patients with congestive heart failure, a research team plans a study to test this association. An investigation is undertaken at a hospital to systematically evaluate if patients taking allopurinol for gout are hospitalized less frequently for exacerbations of congestive heart failure. Community physicians are asked by the principal investigator to refer appropriate patients for the study.
Which of the following will help ensure protection of the patients' right to privacy with respect to their personal health information?
(Multiple Choice)
5.0/5 (74)
(74) A 24-year-old man is brought to the physician for a follow-up appointment. He initially presented 4 weeks ago with an acute episode of psychosis and personality changes, and he was prescribed low dose risperidone. He subsequently developed tremor and gait abnormalities. The patient's father died from liver failure at age 40. His mother is alive at age 60 and is a smoker with mild emphysema. He has two siblings who are alive and healthy. The patient drinks 2-3 beers daily and has smoked two packs of cigarettes per day for the last five years.
His vital signs are within normal limits. The patient's BMI is 23 kg/m2. Lungs are clear to auscultation. Examination reveals a nontender abdomen. The liver is palpable 3 cm below the right costal margin. A bilateral resting tremor is noted in his hands.
Laboratory studies obtained 4 weeks ago during his first visit are shown below.
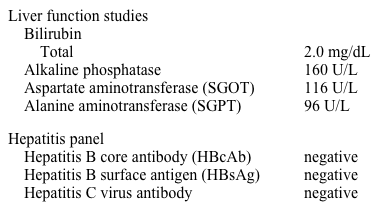 Complete blood count, renal function panel, urinalysis, and thyroid function testing are within normal limits. Urine toxicology screen is negative.
Which of the following is the most appropriate next step in management?
Complete blood count, renal function panel, urinalysis, and thyroid function testing are within normal limits. Urine toxicology screen is negative.
Which of the following is the most appropriate next step in management? (Multiple Choice)
4.7/5 (73)
(73) A 23-year-old man comes to the office with symptoms of daytime sleepiness. The patient initially attributed his sleepiness to the frequent travel required by his job, but he grew more concerned when he fell asleep in the middle of a business meeting last week. At night, the patient initially falls asleep quickly, but then wakes up frequently throughout the night. He couldn't move when he first woke up one morning this week, and he has recently begun to hear "demonic" voices at night as he lies in bed. The patient has a history of remitted major depressive disorder. The patient's brother has schizophrenia.
Vital signs and physical examination are within normal limits.
A daytime, multiple sleep latency test shows a short sleep latency of 4 minutes (normal >10 minutes).
Which of the following is the most appropriate therapy?
(Multiple Choice)
4.9/5 (84)
(84) An asymptomatic 30-year-old woman comes to the physician for a routine health maintenance examination. She has a history of non-Hodgkin lymphoma (NHL) diagnosed at age 20, for which she received combination chemotherapy and radiation therapy to the chest. Follow-up PET/CT scans showed no relapse of the disease. Her last PET/CT scan was 5 years ago. She does not use tobacco, alcohol, or drugs. She has no family history of cancer.
Vital signs are within normal limits. Examination shows no lymphadenopathy. Breast examination does not reveal any nodules or nipple retraction. Cardiopulmonary examination shows no abnormalities.
Which of the following is the most appropriate next step in the management of this patient?
(Multiple Choice)
4.9/5 (88)
(88) A 28-year-old woman comes to the physician because of a low platelet count incidentally discovered on routine blood work. She was recently seen by a psychiatrist for depression. She admits to depressed mood, easy fatigability, insomnia, and feelings of worthlessness for the past 6 months. She denies any history of bleeding problems. She does not take any medications, including herbal products or dietary supplements. She denies recent travel, vaccinations, or infections. She does not use tobacco, alcohol, or illicit drugs. She is not currently sexually active and denies ever being pregnant. There is no family history of bleeding disorders or cancer.
Her vital signs are within normal limits. Complete physical examination is unremarkable.
Laboratory results are as follows:
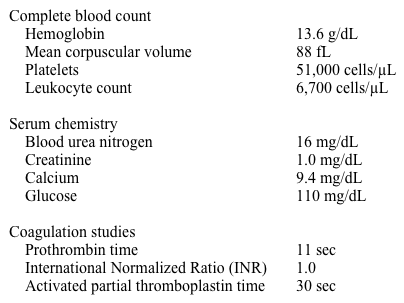 Peripheral blood smear shows thrombocytopenia, giant platelets, and an absence of platelet clumping. Red and white blood cell morphology is within normal limits.
Testing for HIV is negative.
Which of the following is the most appropriate next step in management for her thrombocytopenia?
Peripheral blood smear shows thrombocytopenia, giant platelets, and an absence of platelet clumping. Red and white blood cell morphology is within normal limits.
Testing for HIV is negative.
Which of the following is the most appropriate next step in management for her thrombocytopenia? (Multiple Choice)
4.7/5 (70)
(70) A 68-year-old man with chronic kidney disease secondary to diabetic nephropathy and hypertension comes to the office for a follow-up visit. The patient has had mild fatigue but no anorexia, nausea, vomiting, chest pain, or shortness of breath. Medical history includes hyperlipidemia, coronary artery disease, and hand osteoarthritis that limits manual dexterity. The patient lives alone and has occasional help from an aide. He is compliant with medications and recommended dietary restrictions. Physical examination reveals clear lungs, no heart murmur, and trace pedal edema.
Laboratory results show hemoglobin 11.8 g/dL and serum potassium 4.9 mEq/L. Estimated glomerular filtration rate (eGFR) is 19 mL/min/1.73 m2, which was 26 mL/min/1.73 m2 a year ago.
After a thorough discussion, the patient is interested in renal replacement therapy. Which of the following is the most appropriate next step in management?
(Multiple Choice)
4.7/5 (82)
(82) A 26-year-old man comes to the physician for a pre-employment physical evaluation. He has no known medical problems.
The patient weighs 65 kg (143.3 lb) and is 190.5 cm (6' 3") tall. There is a faint early diastolic murmur best heard in the second right intercostal space. He has mild scoliosis. Physical examination findings in the extremities are shown in the exhibits.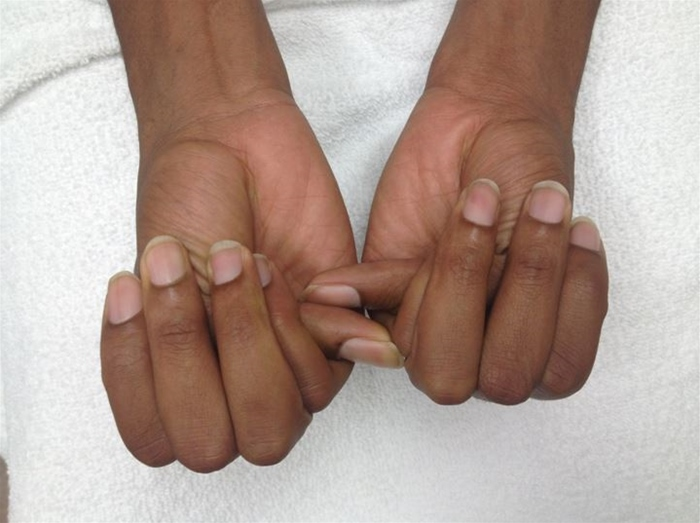
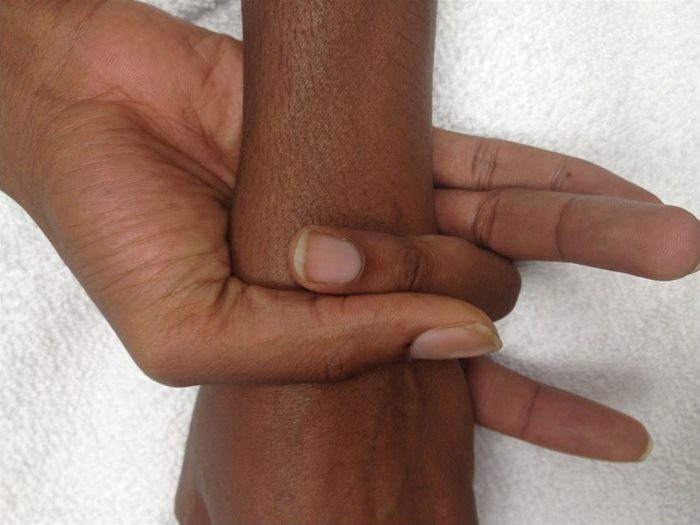 Which of the following is the most appropriate next step in management of this patient?
 (Multiple Choice)
4.8/5 (76)
(76) A 36-year-old man with a 3-year history of celiac disease comes to the physician with fatigue, low-grade fevers, abdominal pain, and diarrhea for 3 months. He was symptom free for 2 years when he followed a strict gluten-free diet. However, in the past year, he developed symptoms twice due to poor dietary compliance. The patient's other medical problems include type I diabetes mellitus and depression. His father died of colon cancer at age 55. His mother has diabetes, and a sister has celiac disease.
His temperature is 38.3° C (101° F), blood pressure is 110/80 mm Hg, and pulse is 80/min. The abdomen is soft but tender in the periumbilical area. There is no rebound tenderness or rigidity. Rectal examination shows dark stools positive for blood.
Laboratory results are as follows:
 Which of the following is the most likely cause of this patient's current symptoms?
 (Multiple Choice)
4.9/5 (80)
(80) A 36-year-old woman is seen in a clinic for follow-up evaluation. She was diagnosed with rheumatoid arthritis 3 months ago and was started on methotrexate and hydroxychloroquine.
Which set of clinical features and serologic results at this visit is likely to predict the worst outcome in this patient?
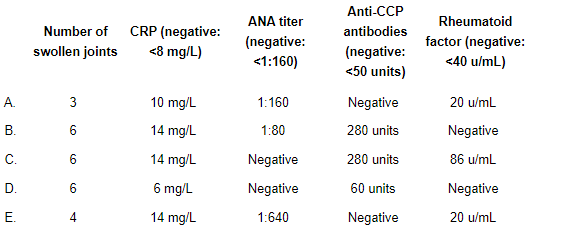
(Multiple Choice)
4.8/5 (72)
(72) An 18-year-old man comes to the office due to a painful left elbow lesion. The patient has a history of atopic dermatitis and recently had a moderate to severe flare with a "weeping" rash in the creases of his elbows and knees. A few days ago, he noticed a small red nodule in his left elbow crease that progressively enlarged and became painful. He has not had fever or chills. The patient has no other medical problems, and his only medication is topical corticosteroid. He does not use alcohol, tobacco, or illicit drugs.
Temperature is 36.7 C (98.1 F), blood pressure is 126/80 mm Hg, pulse is 80/min, and respirations are 12/min. Skin examination shows a 4-cm tender and fluctuant lesion in the left antecubital area with erythema and induration of the surrounding skin. The flexural surfaces of the knees and elbows have an eczematous skin rash with lichenification. The remainder of the physical examination is within normal limits.
Incision and drainage of the fluctuant lesion yields approximately 3 mL of purulent material, which is sent to the laboratory for culture and sensitivity.
Which of the following is the most appropriate recommendation regarding antimicrobial therapy for this patient?
(Multiple Choice)
4.8/5 (83)
(83) A 62-year-old man comes to the physician with weight loss, fatigue, and dyspnea at rest. He has no increased cough or sputum production. His medical problems include hypothyroidism and chronic obstructive pulmonary disease (forced expiratory volume in 1 second 18% predicted) requiring home oxygen. He has had 2 emergency department visits and 1 hospital admission in the last 6 months for chronic obstructive pulmonary disease exacerbations. He has a 50-pack-year smoking history and does not want to quit. He spends most of his free time sitting on the couch because he is limited by dyspnea. His medications include inhaled albuterol, tiotropium, inhaled mometasone and formoterol, montelukast, megestrol, low-dose oral prednisone, and levothyroxine.
His temperature is 37.2° C (99° F), blood pressure is 150/80 mm Hg, pulse is 114/min, and respirations are 23/min. His BMI is 18 kg/m2. The patient's pulse oximetry shows 94% on 4 L O2. Physical examination shows pursed lip breathing, decreased breath sounds throughout, loud second heart sound, and 2+ pretibial edema bilaterally.
Laboratory results from his last admission are as follows:
 Which of the following is the most appropriate next step in management?
 (Multiple Choice)
4.8/5 (66)
(66) A 70-year-old man seeks advice regarding testosterone replacement therapy. The patient recently married a younger woman and has been reading reports in the news media regarding the therapy's potential benefits. He has diminished sexual desire and moderate erectile dysfunction that responds to sildenafil. The patient rarely has a morning erection. His ability to perform endurance exercise at a high level is significantly lower than it was 10 years ago. Other medical problems include hypertension, type 2 diabetes mellitus, benign prostatic hyperplasia (American Urological Association score of 10), and hyperlipidemia. There is no family history of prostate cancer.
Blood pressure is 134/88 mm Hg and pulse is 84/min. BMI is 30 kg/m2. Neck circumference is 20 in (51 cm). Cardiovascular, pulmonary, abdominal, and extremity examinations are normal. The testes appear normal for age. Digital rectal examination shows a symmetrical prostate that is mildly enlarged.
Laboratory results are as follows:
 Which of the following is the best advice regarding testosterone replacement for this patient?
 (Multiple Choice)
4.9/5 (73)
(73) A 72-year-old man comes to the office due to increased urinary frequency and pain during urination. The patient has had mild urinary hesitancy and frequent nocturia for several years but was not bothered until he began experiencing intermittent burning pain during urination 3 months ago. The patient has also been urinating several times during the day as well as at night and has had urgent need to urinate. He has had no fever, abdominal or back pain, or hematuria. The patient was given oral trimethoprim-sulfamethoxazole a month ago after testing revealed a urinary tract infection. His symptoms improved while taking the antibiotics but recurred after finishing the 1-week course of treatment. Medical history is notable for hypertension and gout. He is a former smoker with a 30-pack-year history and does not drink alcohol. The patient worked in a petroleum refinery for many years before retiring at age 65.
Temperature is 36.7 C (98 F), blood pressure is 130/84 mm Hg, and pulse is 72/min. The abdomen is soft and nontender with no masses or hepatosplenomegaly. There is no costovertebral angle tenderness. Digital rectal examination shows a diffusely enlarged and moderately tender prostate.
Leukocyte count is 9,200/mm3. Urinalysis results are as follows:
 Which of the following is the most likely cause of this patient's current urinary symptoms?
 (Multiple Choice)
4.9/5 (83)
(83) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)