



 Chat with AI
Exam 3: Office/Health Center

Exam 1: Emergency Department218 Questions
Exam 2: In-patient Facilities128 Questions
Exam 3: Office/Health Center900 Questions
Select questions type


A 52-year-old African American man comes to the physician because of foggy vision in both eyes. He denies any headache, nausea, or vomiting. He was diagnosed with extensive cellulitis and osteomyelitis of the right foot 4 weeks ago and has been taking oral linezolid. His other medical problems include sarcoidosis, pulmonary hypertension, lower extremity venous stasis, deep vein thrombosis, type 2 diabetes for 5 years, hypertension, and chronic kidney disease.
His medications include warfarin, prednisone (10 mg/day), insulin, hydralazine, clonidine, metoprolol, valsartan, and furosemide. He has been compliant with his medication regimen. He quit smoking 7 years ago and denies the use of alcohol or illicit drugs. He is allergic to vancomycin.
His temperature is 36.7 C (98 F), blood pressure is 150/90 mm Hg, and pulse is 72 /min. His BMI is 32 kg/m2. Visual acuity is 20/400 in both eyes with considerable optic disc edema, hyperemia, and reduced color perception. A right carotid bruit is present. Examination shows jugular venous distention, a few fine crackles in all lung fields, normal first and second heart sounds, and a palpable liver 2 cm below the costal margin. Bilateral 1+ pitting lower extremity edema to the mid shin and a resolving right leg cellulitis is present.
Which of the following is the most immediate next step in management?
(Multiple Choice)
4.7/5  (75)
(75) A 22-year-old man comes to the physician after an episode of bloody stool 3 weeks earlier. He has had similar episodes in the past with no intervention, but the last time he went to the emergency department. After initial evaluation and laboratory workup, he was discharged with outpatient follow-up. The patient has no other medical problems and takes no medications. He was adopted at a young age. He smokes 1 pack of cigarettes a day but does not use alcohol or illicit drugs.
Physical examination shows multiple brown spots on the lips and buccal mucosa. The abdominal examination is unremarkable. Rectal examination reveals brown stool with no hemorrhoids or perianal lesions.
Which of the following conditions is this patient at the highest risk of developing?
(Multiple Choice)
4.8/5 (80)
(80) A 35-year-old man comes to the office due to 4 weeks of generalized malaise, left-sided headache, and weakness of the right hand. The patient has a history of intravenous drug use, which led to hepatitis C and HIV infections. He has refused antiretroviral therapy, and his last known CD4 count was 298/mm3 3 months ago. He has never had an HIV-related opportunistic infection or been hospitalized.
Temperature is 37.2 C (99 F), blood pressure is 110/70 mm Hg, and pulse is 106/min. Examination shows no oral thrush or enlarged lymph nodes. Erythematous macules are present on both palms. A 3/6 holosystolic murmur is heard at the cardiac apex. The lungs are clear to auscultation. The abdomen is nontender. There are no meningeal signs. Motor strength is 4/5 in the right upper extremity and 5/5 in the remaining extremities. Reflexes are 3+ in the right upper extremity with a noted extensor plantar response on the right.
Laboratory results are as follows:
 CT scan of the head with and without contrast reveals a 2.4-cm, ring-enhancing, round mass with vasogenic edema and mild mass effect at the grey-white matter junction in the left frontal lobe.
Which of the following is the most likely diagnosis?
CT scan of the head with and without contrast reveals a 2.4-cm, ring-enhancing, round mass with vasogenic edema and mild mass effect at the grey-white matter junction in the left frontal lobe.
Which of the following is the most likely diagnosis? (Multiple Choice)
4.8/5 (81)
(81) A 68-year-old HIV-negative man comes to the physician due to 5 months of worsening cough with an associated 4.5-kg (10-lb) weight loss. He also reports fatigue and decreased appetite. He has no recent travel history, sick contacts, new medications, or exposure to new environmental agents. The patient's other medical problems include moderate chronic obstructive pulmonary disease, hyperlipidemia, and type 2 diabetes mellitus. His medications include fluticasone/salmeterol inhaler, albuterol, metformin, aspirin, and atorvastatin. His immunizations are up to date. The patient has a 30-pack-year smoking history but quit 5 years ago. He drinks alcohol socially and does not use illicit drugs.
His temperature is 37.0 C (98.6 F), blood pressure is 130/70 mm Hg, and respirations are 14/min. Pulse oximetry shows 94% oxygen saturation on room air. Lung examination shows crackles over the right lower lung with mild wheezes diffusely. The remainder of the physical examination is within normal limits.
The patient's routine blood work shows normal chemistry and complete blood count. CT scan of the chest obtained following an abnormal chest x-ray reveals an infiltrate in the right middle lobe and bronchiectasis and nodules in the right middle and upper lobe. Two of 2 separate sputum cultures grow mycobacteria identified as Mycobacterium avium complex by a rapid nuclear acid probe.
Which of the following is the best management for this patient?
(Multiple Choice)
4.9/5 (87)
(87) A 26-year-old woman comes to the physician because of a constant dry cough, low grade fevers, and night sweats for the last 4 weeks. She initially attributed her symptoms to a respiratory infection, but they have been progressively worsening. She denies shortness of breath or chest pain. Furthermore, she has lost approximately 5 lbs (2.3 kg) over the past 4 weeks. She denies any other medical problems and takes no medications with the exception of over-the-counter cough syrup. She denies recent travel or sick contacts. She does not use tobacco, alcohol, or illicit drugs.
Her temperature is 100.4 F (38.0 C), blood pressure is 110/80 mm Hg, and pulse is 90/min. Physical examination shows multiple, bilateral, firm, rubbery, 2 to 3 cm-sized lymph nodes in the cervical, supraclavicular, and axillary region. Cardiopulmonary examination is unremarkable. There is no hepatosplenomegaly.
Chest imaging shows a widened mediastinum, hilar fullness, and clear lungs. HIV and heterophile antibody testing is negative.
Which of the following is the most appropriate next step in management?
(Multiple Choice)
4.8/5 (73)
(73) A 70-year-old retired farmer seeks evaluation for 2 "lumps" on his skin. One is on his lower lip and the other is on his ear. These have been present for "a while" and seem to be getting larger. He recently saw a television show on skin cancer and thought he should get these checked. He has no other health concerns.
His vital signs are normal. The lip lesion is shown in the photograph below. The lesion reduces in size when compressed.
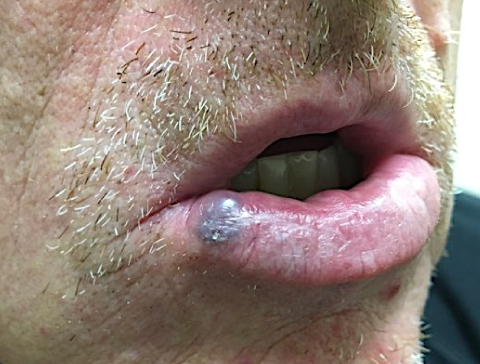 What is the most likely diagnosis?
 (Multiple Choice)
4.7/5 (68)
(68) A 37-year-old man comes to the office due to generalized fatigue and weight loss over the last 6 months. He has not had skin rash, fevers, night sweats, cough, or diarrhea. The patient was diagnosed with HIV 6 years ago and does not take antiretroviral medications.
Vital signs are normal and BMI is 18 kg/m2. Physical examination shows small, mobile submandibular lymph nodes. Mucous membranes are moist with no lesions. The lungs are clear to auscultation. There is no organomegaly on abdominal examination.
Laboratory results are as follows:
 In addition to antiretroviral therapy, prophylaxis against which of the following pathogens should be initiated in this patient?
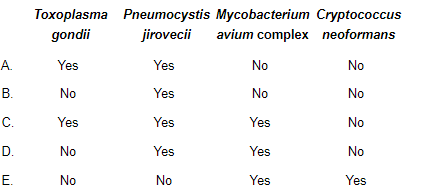
In addition to antiretroviral therapy, prophylaxis against which of the following pathogens should be initiated in this patient?
(Multiple Choice)
4.9/5 (85)
(85) A 33-year-old woman comes in for a follow-up appointment. She was seen 6 months ago for a rash on her face, profound fatigue, and arthritis. The patient was diagnosed with systemic lupus erythematosus and started on hydroxychloroquine and low-dose prednisone. She has experienced marked improvement in her symptoms and has resumed her usual activities.
Physical examination shows a faint facial rash but is otherwise unremarkable.
Current laboratory results are as follows:
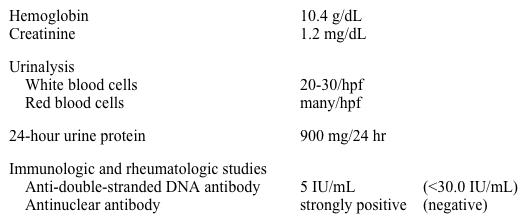 Which of the following is the most appropriate next step in management?
 (Multiple Choice)
4.9/5 (79)
(79) A 23-year-old woman comes to the office due to thick, yellow vaginal discharge for the past few days. She has had no fever or chills and has not recently changed personal hygiene items or sexual practices.
The patient takes oral contraceptives, does not use condoms, and has had the same male sexual partner for the past 3 years. Pap testing last year was normal.
On speculum examination, the cervix is erythematous and swollen and bleeds when touched with a cotton applicator. Pelvic examination reveals a small uterus with no cervical motion tenderness and no adnexal tenderness. The rest of the physical examination is normal.
Wet mount microscopy shows white blood cells, a few nonmotile bacteria, no clue cells, and no hyphae. A urine pregnancy test is negative.
Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (78)
(78) A 60-year-old woman is evaluated for occasional short-lived episodes of dizziness. She has had no headaches, blurry vision, muscle weakness, or syncope. The patient has no history of heart disease or stroke. She takes over-the-counter acetaminophen for low back pain and is a lifetime nonsmoker.
Blood pressure is 144/90 mm Hg and pulse is 82/min. There are no rashes. Neurologic examination shows no abnormalities.
Laboratory results are as follows:
 Further workup shows the presence of the JAK2 V617F mutation.
Because of her current condition, this patient is at greatest risk for which of the following?
Further workup shows the presence of the JAK2 V617F mutation.
Because of her current condition, this patient is at greatest risk for which of the following? (Multiple Choice)
4.9/5 (89)
(89) A 22-year-old woman comes to the physician seeking evaluation for hair loss. She developed a small, discrete patch of hair loss a few years ago that resolved spontaneously without scarring. In the past 3 weeks, she has developed another patch that is larger than the previous one and is causing her significant anxiety. She denies pulling on her hair. There is no associated itching or burning of her scalp. The patient has no other significant medical history. Her only medication is birth control pills. She is in graduate school and is under a lot of stress from her studies.
On examination, she appears healthy and her vital signs are normal. A photograph of her scalp is shown below.
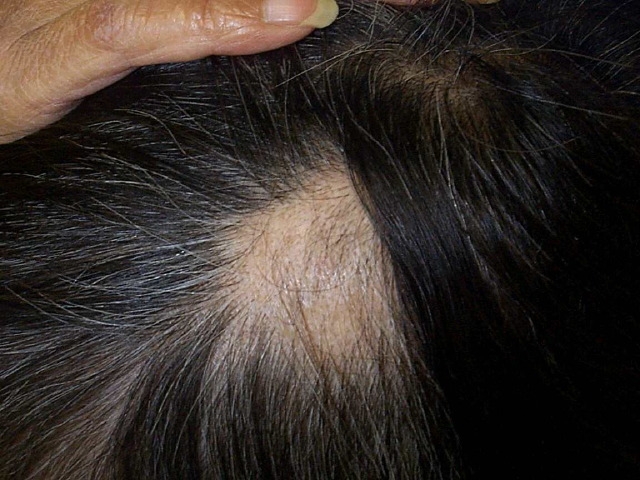 Some hairs in the margin are larger on top than at their base and are extractable with minimal traction. There is no evidence of scalp inflammation and there are no nail abnormalities.
Laboratory results are as follows:
 What would be the most appropriate therapy for this patient?
Some hairs in the margin are larger on top than at their base and are extractable with minimal traction. There is no evidence of scalp inflammation and there are no nail abnormalities.
Laboratory results are as follows:
What would be the most appropriate therapy for this patient? (Multiple Choice)
4.9/5 (93)
(93) A 56-year-old man with a history of alcohol abuse is hospitalized due to aspiration pneumonia of the right lower lung. While being treated, he develops severe hypoxemia requiring transfer to the intensive care unit for initiation of mechanical ventilation. Temperature is 37.1 C (98.8 F), blood pressure is 120/62 mm Hg, and pulse is 95/min. Pulmonary examination is significant for bilateral crackles. There is no jugular venous distension or peripheral edema. Repeat chest x-ray demonstrates diffuse, bilateral alveolar opacities.
Initial ventilator settings demonstrate a tidal volume of 510 mL (8 mL/kg of predicted body weight), positive end-expiratory pressure of 10 cm H2O, respiratory rate of 35/min, and FiO2 of 80%. Tidal volume is reduced to 380 mL (6 mL/kg of ideal body weight) over several hours; the other ventilator parameters are unchanged. Plateau pressure is 27 cm H2O. Arterial blood gas results are as follows:
 What is the best next step in management of this patient?
 (Multiple Choice)
4.8/5 (78)
(78) A 62-year-old man comes to the physician with gait instability. One week ago, he suddenly developed nausea, vomiting, and dizziness. In the past 2 days, he has been "seeing double" and has fallen several times due to problems with balance. His review of systems is positive for unintentional weight loss over the last 3 months. The patient uses alcohol occasionally and has a 60-pack-year smoking history.
He is afebrile and vital signs are normal. Physical examination shows horizontal nystagmus, dysarthria, and unsteady gait.
Chest x-ray shows a right upper lobe lung mass. MRI of the brain with and without contrast is normal.
Which of the following is the most likely cause of this patient's gait disturbance?
(Multiple Choice)
4.9/5 (68)
(68) A 62-year-old man with known diabetes mellitus and hyperlipidemia comes to the physician with right hip pain for the last 3 months. The pain is aching, brought on by walking (especially uphill), and goes away quickly with standing still. It is sometimes accompanied by leg weakness, causing the patient to hold on to stationary objects.
The patient's other medical problems include gallstones, hyperlipidemia, benign prostate hyperplasia, and erectile dysfunction. He takes long-acting insulin at night. His dose of simvastatin was recently increased due to an elevated LDL cholesterol level.
Which of the following physical findings is most consistent with this patient's diagnosis?
(Multiple Choice)
4.8/5 (86)
(86) A 47-year-old woman recovering from an upper respiratory infection comes to the office with a 3-day history of ear discomfort. The patient feels that her right ear is "plugged" and hears popping sounds in the ear when chewing or yawning. She also reports some pressure and slight pain in the ear.
Her temperature is 37.2 C (99 F), blood pressure is 134/80 mm Hg, pulse is 84/min, and respirations are 14/min. Neck examination is normal and there is no lymphadenopathy. The left tympanic membrane is normal, but the right one appears mildly retracted. Romberg test and heel-to-toe gait are normal. A tuning fork placed in the middle of the head lateralizes to the right. The remainder of the physical examination is unremarkable.
What is the best next step in management of this patient?
(Multiple Choice)
4.7/5 (62)
(62) A 39-year-old man with a history of chronic constipation comes to the physician with severe anal pain for the past 2 months. Bowel movements worsen the pain, and there is also persistent pain without stool passage. He reports a small amount of blood on the toilet paper after bowel movements. His family history is notable for irritable bowel syndrome in his mother and sister.
The patient's blood pressure is 138/78 mm Hg, pulse is 84/min, and respirations are 14/min. Physical examination shows a soft and nontender abdomen with normoactive bowel sounds. There is no hepatomegaly or splenomegaly. Rectal examination is limited due to significant pain on insertion of the finger and a tight anal sphincter. Small external hemorrhoids are noted.
Laboratory results are as follows:
 Colonoscopy is notable for moderate-size internal hemorrhoids, mild diverticulosis, and posterior anal fissure on external examination under sedation.
In addition to dietary modification and stool softeners, which of the following is the most appropriate next step in management?
Colonoscopy is notable for moderate-size internal hemorrhoids, mild diverticulosis, and posterior anal fissure on external examination under sedation.
In addition to dietary modification and stool softeners, which of the following is the most appropriate next step in management? (Multiple Choice)
4.9/5 (82)
(82) A 35-year-old woman comes to the physician for a follow-up visit. She was recently diagnosed with systemic lupus erythematosus after a 2-month history of fatigue and a skin rash. She was advised to use over-the-counter hydrocortisone cream for the facial rash but it did not help. Her previous medical history is insignificant. The patient has never been pregnant. She does not use tobacco and drinks only 1 or 2 alcoholic beverages a week. She currently takes no prescription medications.
Her vital signs are normal. Skin findings are shown in the image below.
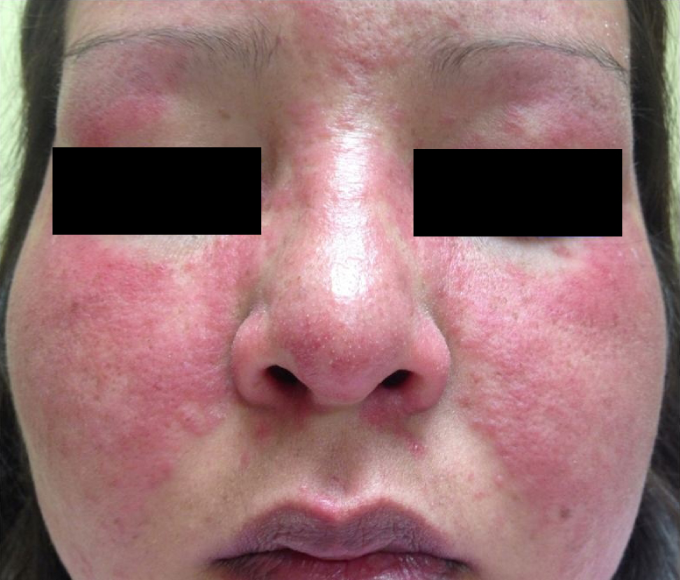 Which of the following is the best therapy for this patient's rash?
 (Multiple Choice)
4.8/5 (78)
(78) A 28-year-old woman comes to the physician with fatigue and low energy. She was started on depot medroxyprogesterone acetate injections 6 months ago and relates her symptoms to the therapy and resulting cessation of her menstrual cycles. The patient was diagnosed with diarrhea-predominant irritable bowel syndrome 8 months ago, and continues to have intermittent symptoms of that as well. She also has a history of generalized anxiety disorder. Her current medications include a multivitamin and simethicone for excessive flatulence.
Laboratory results are as follows:
 A peripheral smear is shown in the image below:
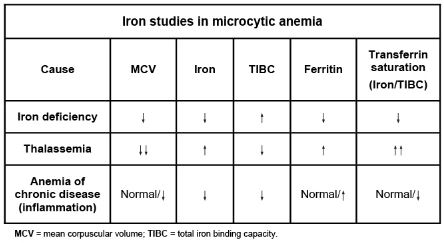 Which of the following is the best diagnostic test to confirm the diagnosis?
A peripheral smear is shown in the image below:
Which of the following is the best diagnostic test to confirm the diagnosis? (Multiple Choice)
4.9/5 (86)
(86) A 64-year-old man with diet-controlled type 2 diabetes mellitus, ischemic cardiomyopathy, and systolic heart failure comes to the physician for follow-up. The patient has New York Heart Association functional class II symptoms and shows no signs of fluid overload. His daily medications include furosemide, carvedilol, lisinopril, atorvastatin, and low-dose aspirin.
The patient's blood pressure is 155/90 mm Hg and pulse is 60/min.
His potassium level is 4.2 mEq/L and serum creatinine level is 0.9 mg/dL.
Adding losartan to this patient's current regimen is most likely to result in which of the following?
(Multiple Choice)
4.9/5 (85)
(85) A 28-year-old woman comes to the office for a routine evaluation. During the review of systems she reports weight gain, fatigue, bloating, flatulence, constipation, mild acne, and menstrual irregularity. The patient describes difficulty losing weight despite trying numerous low-calorie diets. She is depressed about her weight and feels that her appearance has always been a source of insecurity. She is also unhappy with her current position as an administrative assistant but lacks the motivation to look for another job. The patient has an active social life with friends but is not in a relationship. She smokes marijuana 1 or 2 times a month and has used cocaine at parties twice in the past year.
Temperature is 37.1 C (98.8 F), blood pressure is 110/60 mm Hg, and pulse is 68/min. On physical examination, the patient has mild facial acne and is slightly overweight. BMI is 27 kg/m2. The oropharynx is remarkable for painless, mildly swollen parotid glands. The remainder of the physical examination is normal.
Complete blood count is normal and serum electrolytes are notable for mildly decreased serum potassium, slightly elevated serum bicarbonate, and mildly decreased serum chloride levels. Thyroid function tests, liver function tests, and urinalysis are unremarkable.
Which of the following is the most likely diagnosis in this patient?
(Multiple Choice)
4.8/5 (89)
(89) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)