



 Chat with AI
Exam 3: Office/Health Center

Exam 1: Emergency Department218 Questions
Exam 2: In-patient Facilities128 Questions
Exam 3: Office/Health Center900 Questions
Select questions type


A 37-year-old man with 3 months of bloody diarrhea comes to the physician for follow-up after a colonoscopy showed superficial ulcerations from the rectum to the mid descending colon. The biopsies showed chronic active colitis. He was started on prednisone and is currently taking 20 mg. He has 3 nonbloody bowel movements daily. The patient has no other medical problems. He quit smoking 5 months ago. He does not use alcohol or illicit drugs.
Vital signs are normal. The abdomen is soft and nontender. Bowel sounds are present. There is no hepatomegaly or splenomegaly. Rectal examination is normal with no skin tags or external hemorrhoids, but stool is guaiac positive.
Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.8/5  (75)
(75) A 53-year-old man is seen for a routine health examination. He has a 30-year history of schizophrenia and was recently diagnosed with type 2 diabetes mellitus. The patient's other medical conditions include hypercholesterolemia and seborrheic dermatitis. Medications include metformin, lovastatin, and haloperidol. The patient's schizophrenia had been controlled for many years on olanzapine until he was hospitalized 6 months ago for an acute psychotic episode that occurred when he was forced to move into a group home following the death of his father. Since discharge, his psychotic symptoms have been well controlled on a stable dose of haloperidol.
On examination, the patient is cooperative but makes little eye contact. He appears extremely anxious and restless. He shifts frequently in his chair and crosses and uncrosses his legs continually. Vital signs are within normal limits. The remainder of the physical examination, apart from moderate obesity, is unremarkable. Laboratory studies, including comprehensive metabolic panel, complete blood count, and TSH, are within normal limits. Hemoglobin A1c is 7%.
Which of the following is the most likely explanation for this patient's symptoms?
(Multiple Choice)
4.9/5 (79)
(79) A 69-year-old man comes to the office with a 6-month history of dry cough and progressive exertional dyspnea. The patient smoked a pack of cigarettes a day for 40 years but quit 15 years ago. He owns 2 parrots and a cat. He feels that his symptoms improved somewhat while on vacation 2 months ago.
On examination, blood pressure is 138/92 mm Hg, pulse is 84/min, and respirations are 18/min. Pulse oximetry is 90% on room air. Chest auscultation shows bilateral crackles with mild end-expiratory wheeze and a 2/6 systolic murmur at the left sternal border. Digital clubbing is present.
Pulmonary function testing shows a restrictive defect with impaired gas exchange. A CT scan of the chest reveals bilateral patchy ground-glass opacities, mostly in the mid-upper lung fields. There is no lymphadenopathy.
Which of the following is the most likely diagnosis?
(Multiple Choice)
4.8/5 (81)
(81) A 72-year-old man comes to the physician complaining of 2 weeks of muscle cramps and stiffness in his legs. He also feels fatigued and has to rest after walking several blocks. His past medical history is significant for coronary artery disease, type 2 diabetes mellitus, paroxysmal atrial fibrillation, and hyperlipidemia.
The patient underwent coronary revascularization with placement of 2 drug-eluting stents in his left anterior descending artery 6 months ago. His medications include metformin, low-dose-aspirin, clopidogrel, metoprolol, valsartan, and atorvastatin. He was recently started on amiodarone due to recurrent episodes of highly symptomatic atrial fibrillation.
The patient's blood pressure is 129/72 mm Hg and pulse is 65/min. His body mass index is 30 kg/m2. There is no muscle tenderness on physical examination. His muscle strength is 5/5 bilaterally and deep-tendon reflexes are 2+ and symmetrical bilaterally.
Laboratory results are as follows:
 His atorvastatin is discontinued and his symptoms resolve completely within 4 weeks.
Which of the following is the best next step in management of this patient?
His atorvastatin is discontinued and his symptoms resolve completely within 4 weeks.
Which of the following is the best next step in management of this patient? (Multiple Choice)
4.7/5 (91)
(91) A 35-year-old immigrant from Eastern Europe comes to the office due to dry cough, malaise, and fatigue. He has had joint aches and involuntary weight loss over the past 3 months. His other medical problems include severe allergies that manifest as nasal stuffiness, headache, and ear pain. He takes over-the-counter decongestants. He is a construction worker, smokes a pack of cigarettes a day, and drinks 6 cans of beer once a week. His mother suffers from severe rheumatoid arthritis.
His temperature is 37.2 C (99 F), blood pressure is 122/70 mm Hg, and pulse is 89/min. He has tenderness on palpation of bilateral maxillary sinuses. Tympanic membranes are full and bulging bilaterally. Pulmonary auscultation reveals occasional rhonchi. There are no heart murmurs. The tip of the spleen is not palpable. There are no skin rashes or joint swelling.
Laboratory results are as follows:
 Liver panel is unremarkable. Urinalysis is positive for blood and protein, and urine sediment analysis reveals multiple red blood cells casts. Chest x-ray is shown below.
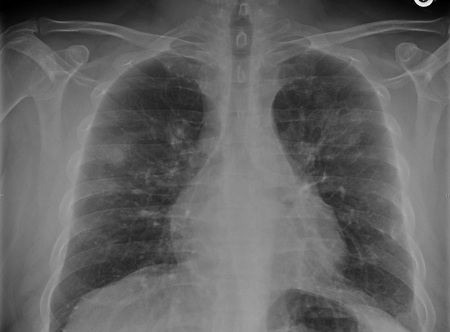 Which of the following is most likely to establish this patient's diagnosis?
Liver panel is unremarkable. Urinalysis is positive for blood and protein, and urine sediment analysis reveals multiple red blood cells casts. Chest x-ray is shown below.
Which of the following is most likely to establish this patient's diagnosis? (Multiple Choice)
4.9/5 (76)
(76) A 36-year-old woman comes to the office due to episodic shortness of breath and cough productive of a trace amount of whitish sputum, occurring once or twice a week for the last 6 months. Symptoms seem worse when it is hot and humid and at night, but they do not disturb her sleep. Medical history is significant for allergic rhinitis, gastroesophageal reflux disease, and obesity. Medications include cetirizine, intranasal fluticasone, and pantoprazole. The patient smoked a pack of cigarettes daily at age 18-25. She feels well today and has no respiratory complaints.
Vital signs are within normal limits. BMI is 32 kg/m2. Examination of the nasal passages shows boggy, edematous turbinates and no polyps. Pulmonary auscultation demonstrates clear breath sounds bilaterally with no wheezing. The remainder of the examination is normal.
The patient returns to the clinic for pulmonary function tests several days later, reporting that "my allergies and breathing are acting up again." Spirometry data are as follows:
 Which of the following inhaled medication regimens would be most appropriate for initial management of this patient's condition?
 (Multiple Choice)
4.8/5 (89)
(89) An asymptomatic 85-year-old woman is brought to the physician for a routine followup visit. She has a history of progressively worsening Alzheimer's dementia for 8 years. In the past 6 months, she has become nonverbal and can no longer walk. Her son reports that she is eating less, and he is concerned that she is not ingesting enough calories. She is not resistant to care and has had no behavioral disturbances. The patient lives with her son, who assists her with all activities of daily living. Her other medical problems include hypertension, hypercholesterolemia, and a hospitalization for aspiration pneumonia in the past year. Her medications include donepezil 10 mg once daily, lisinopril, and simvastatin. She has no known drug allergies.
The patient's vital signs are within normal limits. She weighs 50 kg (110.2 lb). Her weight 6 months earlier was 55 kg (121 lb). She is awake but not oriented to person, place, or time. There is a small stage II decubitus ulcer on her sacrum. The remainder of the examination shows no other abnormalities.
Which of the following is the most appropriate course of action?
(Multiple Choice)
4.8/5 (68)
(68) An 80-year-old woman was admitted from a nursing home for progressive lethargy. She was in her usual state of health until she developed constipation three days ago. She was given several doses of lactulose and subsequently developed diarrhea that persisted for 24-48 hours. Since that time, she has refused to leave her bed and has become progressively less responsive.
She is known to have significant cognitive impairment, osteoporosis, hypertension, degenerative joint disease, and mild COPD. She has not taken any medications for two days.
Her temperature is 36.5 C (97.7 F), blood pressure is 90/45 mm Hg, pulse is 115/min, and respirations are 16/min. She appears lethargic but arousable. Her mucous membranes are dry and her skin turgor is markedly diminished. Her neck is supple. Cardiac, lung, and abdominal examinations reveal no significant findings. She moves all her extremities well and the deep tendon reflexes are 2+ and symmetric.
The patient's labs reveal:
 Her EKG shows sinus tachycardia and tall T waves in anterior precordial leads.
Which of the following is the best initial therapy for this patient?
Her EKG shows sinus tachycardia and tall T waves in anterior precordial leads.
Which of the following is the best initial therapy for this patient? (Multiple Choice)
5.0/5 (80)
(80) A 32-year-old paramedic comes to the office for a routine health maintenance examination. He has had headaches for the past several months as well as episodes of nosebleeds. He has no other medical problems. The patient does not use tobacco or illicit drugs but drinks 1 or 2 cans of beer daily. He has no family history of heart failure or sudden death.
Temperature is 36.1 C (97 F); blood pressure is 188/96 mm Hg in the right arm, 184/94 mm Hg in the left arm, and 114/76 mm Hg in the right leg; pulse is 68/min, and respirations are 14/min. Height is 180 cm (5 ft 11 in). Examination reveals no audible carotid bruits. There is a 2/6 mid-systolic murmur heard at the left sternal border as well as a continuous "rumbling" sound heard in the back over the interscapular area.
Diagnostic testing is most likely to demonstrate which of the following findings?
(Multiple Choice)
5.0/5 (73)
(73) An 18-year-old woman comes to the physician complaining of headaches for the past 3 months. She says that the headaches occur almost daily, are holo-cranial, and have a pulsatile quality. They are especially bothersome at night. She has no photophobia, phonophobia, nausea, vomiting, fever, or neck stiffness. The patient has no other medical problems and takes no medications.
Her blood pressure is 144/90 mm Hg and pulse is 77/min. Her BMI is 34 kg/m2. Visual field examination is unremarkable. Cranial nerves are intact. Muscle strength is normal and the deep-tendon reflexes are symmetric. Romberg's test and urine pregnancy test are negative.
Magnetic resonance imaging and magnetic resonance venography of the head reveal an empty sella but no other significant abnormalities.
Which of the following is the best next step in managing this patient?
(Multiple Choice)
4.9/5 (88)
(88) A 53-year-old woman comes to the hospital with right upper-quadrant abdominal discomfort and fatigue for the last 8 weeks. She also complains of jaundice and generalized joint pain. She has no nausea or vomiting. Her past medical history is significant for hypothyroidism for which she takes levothyroxine. Family history includes hypertension and ulcerative colitis. The patient lives in Florida and has not traveled recently. She does not use tobacco, alcohol, or illicit drugs.
Her blood pressure is 166/90 mm Hg, pulse is 96/min, and respirations are 14/min. Physical examination shows pale skin and scleral icterus. Cardiopulmonary examination is within normal limits. There is tenderness to palpation in the right upper quadrant. The liver edge is palpable 3 cm below the costal margin. There is no ascites, splenomegaly, or lower-extremity edema.
Laboratory results are as follows:
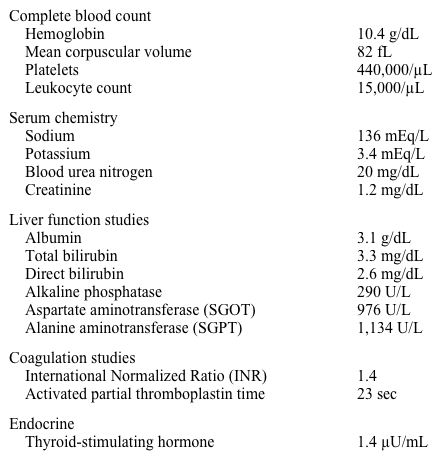 Viral hepatitis antibody panel and HIV testing are negative. Right upper-quadrant ultrasound shows hepatomegaly with normal liver echo texture and no gallstones. The common bile duct measures 6 mm.
Which of the following is the best initial test for this patient?
Viral hepatitis antibody panel and HIV testing are negative. Right upper-quadrant ultrasound shows hepatomegaly with normal liver echo texture and no gallstones. The common bile duct measures 6 mm.
Which of the following is the best initial test for this patient? (Multiple Choice)
4.7/5 (76)
(76) A 28-year-old woman comes to the office for consultation. The patient has a history of recurrent genital herpes simplex virus (HSV) type 2 infections but has no symptoms at present. She has 3 or 4 symptomatic episodes a year. The patient has no other sexually transmitted infections or medical problems and takes no medications. She has a new male sexual partner who is HSV-seronegative.
Which of the following is the most effective strategy for decreasing this patient's risk of transmitting HSV to her partner?
(Multiple Choice)
4.9/5 (71)
(71) A 30-year-old woman comes to the physician with the complaint of cold hands. Symptoms occur during winter months or when she reaches into the freezer at home. The coldness is often associated with intense pallor and a bluish color. On recovery, the hands feel warm and appear red and flushed. With severe attacks, the patient has numbness and tingling in the hands. On rare occasions, she can also feel the sensation in her toes. She denies skin rashes, joint pain, acid reflux, dyspnea, or chest pain.
She has no other medical problems and takes no medication. Family history is unremarkable. She does not use tobacco, alcohol, or illicit drugs.
Her blood pressure is 122/70 mm Hg and pulse is 78/min. Lungs are clear on auscultation. No bruits are heard in the periumbilical area. Peripheral pulses are symmetric and full. Skin examination is normal.
Which of the following is the best next step in this patient's evaluation?
(Multiple Choice)
4.7/5 (86)
(86) A 75-year-old man is admitted to the hospital with fever, chills, productive cough, and difficulty breathing. His initial evaluation shows leukocytosis and right lower lobe consolidation. Appropriate antibiotic therapy is started and the patient has gradual improvement. On the third hospital day, he awakens with sudden pain and swelling of the right knee. The patient has a history of chronic knee pain that he attributes to standing "all day, all my life" as an assembly line worker, but he has never had pain of this intensity. Medical history is notable for hypertension, type 2 diabetes mellitus, and gastroesophageal reflux disease.
Temperature is 37 C (98.6 F), blood pressure is 150/90 mm Hg, pulse is 84/min, and respirations are 14/min. On examination, the patient appears uncomfortable. The right knee joint is swollen, red, warm, and tender, and he is unable to bend the knee due to pain.
Blood cell counts and serum chemistry studies are within normal limits. Blood culture performed at the time of admission shows no growth. Synovial fluid analysis reveals 20,600/mm3 leukocytes with 90% neutrophils; Gram stain is negative and no crystals are visualized. Synovial fluid culture and repeat blood cultures are sent. Right knee x-ray is shown in the exhibit.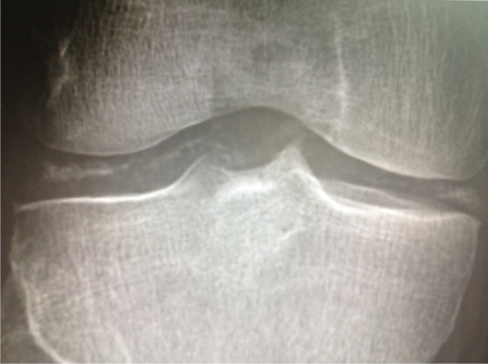 Which of the following is the most likely cause of this patient's knee pain?
 (Multiple Choice)
4.9/5 (93)
(93) A 64-year-old man comes to the office for routine follow-up. He has a history of chronic obstructive pulmonary disease and notes mild dyspnea when walking long distances or ascending several flights of stairs, which is unchanged from his previous visits. Six months ago, the patient was diagnosed with testosterone deficiency after work-up for fatigue and decreased libido revealed low serum testosterone levels. He was initiated on injectable testosterone replacement therapy and notes a significant improvement in his symptoms. Other medical problems include hypertension and gastroesophageal reflux. The patient is an ex-smoker with a 20-pack-year history.
Blood pressure is 126/78 mm Hg and pulse is 72/min. Oxygen saturation while breathing ambient air is 96% at rest and 90% after several minutes of walking. Breath sounds are distant with no wheezing. Heart sounds are normal. The abdomen is soft and nontender. Prostate size is normal.
Laboratory results are as follows:
 Which of the following is the most appropriate next step in management of this patient?
 (Multiple Choice)
4.8/5 (71)
(71) A 55-year-old-man comes to the office due to erectile dysfunction. He has normal libido but has been unable to maintain a satisfactory erection to have intercourse. The patient often wakes up in the morning with an erection. He has no history of testicular injury or peripheral vision loss. Medical history includes end-stage renal disease resulting from idiopathic focal segmental glomerulosclerosis. Peritoneal dialysis was started 6 months ago due to intractable fluid retention despite high-dose diuretic therapy, and he is being evaluated for possible renal transplant. The patient does not use tobacco, alcohol, or illicit drugs.
Temperature is 37.1 C (98.7 F), blood pressure is 138/82 mm Hg, pulse is 76/min, and respirations are 12/min. BMI is 25 kg/m2. Visual fields are normal on confrontation. Testes are normal in size and consistency, and cremasteric reflex is present. There is trace edema at the ankles and feet.
Laboratory results are as follows:
 Which of the following is the most appropriate next step in management of this patient's erectile dysfunction?
 (Multiple Choice)
4.8/5 (74)
(74) A 50-year-old woman comes to the office due to both of her feet feeling "asleep." Her symptoms have progressively worsened over the last 2 years and she occasionally stumbles while walking. She has no fatigue, weakness, pain, or other neurologic symptoms. The patient considers herself to be in good health and has no known medical problems. She has an average diet and does not drink alcohol.
Vital signs and general physical examination are within normal limits. BMI is 30 kg/m2. Neurologic examination indicates bilateral decreased sensation to light touch and pinprick extending downward from the ankles. Ankle reflexes are absent and muscle strength is normal.
Which of the following would confirm the most likely cause of this patient's current symptoms?
(Multiple Choice)
4.9/5 (68)
(68) A 39-year-old man comes to the clinic for voluntary HIV testing. He learned recently that a former sexual partner tested positive for HIV infection and was started on antiretroviral therapy. The patient has been feeling well. He was born and raised in Ecuador and currently resides in New York City, where he works as a nurse at a local nursing home. He enjoys camping and swimming in the pool in his neighborhood. He is the primary caretaker for 2 pet cats and a pet parakeet, all of which are healthy.
Vital signs are normal. Examination shows no abnormalities.
Laboratory testing reveals the following:
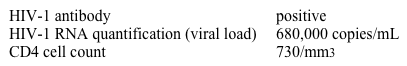 Antiretroviral therapy is planned.
The patient is at greatest risk for infection with which of the following organisms at this time?
Antiretroviral therapy is planned.
The patient is at greatest risk for infection with which of the following organisms at this time? (Multiple Choice)
4.7/5 (72)
(72) A 71-year-old man comes to the physician for routine evaluation. He has no symptoms and considers himself healthy. He walks several miles a day and jogs twice a week for 5 miles. The patient has no history of chest pain or syncope. Five years ago he had inguinal hernia repair without complications. His father died at age 90 of "old age" and his mother died of breast cancer. He has never smoked.
His blood pressure is 126/70 mm Hg and pulse is 72/min and regular. He has no jugular venous distension when sitting. The apical impulse is displaced to the left. A 2/6 holosystolic murmur is heard at the apex. The lungs are clear, and there is no organomegaly. The pulses are full bilaterally and there is no peripheral edema. ECG shows normal sinus rhythm with abnormal Q waves in leads V2 to V4. Transthoracic echocardiography shows left ventricular enlargement, anterior wall and apical akinesis, and left ventricular ejection fraction of 35%. There is mild mitral regurgitation. He declines coronary angiogram.
Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.7/5 (87)
(87) A 21-year-old woman is referred for evaluation of sleep and appetite disturbance. The patient is a college senior who initially went to student health services following a romantic breakup a week ago. Her sleep has returned to normal, but "my eating is still out of control." The patient has been eating entire containers of ice cream and bags of cookies and chips. She says, "I'm sure one of the reasons he dumped me was because of my weight and disgusting body." The patient acknowledges that, throughout college, she has had a pattern of eating very large amounts of food several times a week and daily while preparing for final exams. She does not vomit but takes laxatives and exercises for several hours after one of these eating episodes. The patient has no medical issues but reports that her menstrual cycle is irregular. Her older sister has a history of anorexia nervosa.
Temperature is 37 C (98.6 F), blood pressure is 108/62 mm Hg, pulse is 88/min, and respirations are 14/min. BMI is 21 kg/m2. Physical examination is unremarkable. Pregnancy test is negative.
Which of the following is the most likely diagnosis?
(Multiple Choice)
4.9/5 (95)
(95) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)