



 Chat with AI
Exam 3: Office/Health Center

Exam 1: Emergency Department218 Questions
Exam 2: In-patient Facilities128 Questions
Exam 3: Office/Health Center900 Questions
Select questions type


An 80-year-old man comes to the office for routine follow-up. He lives alone and is independent in his activities of daily living. He still drives infrequently but has his groceries delivered. His spouse of 50 years died 2 years ago. The patient denies feeling down and is still interested in music and playing golf but remarks that he is not going out as much as he once did. He admits to lacking companionship and feeling lonely. He has hypertension, hyperlipidemia, benign prostatic hyperplasia, and osteoarthritis of the knees. The patient takes 5 medications daily and is adherent with his medical regimen. He drinks 1 or 2 glasses of wine a day.
On physical examination, the patient is well dressed and groomed. Blood pressure is 130/84 mm Hg and pulse is 80/min. BMI is 25 kg/m2. Mini-Mental Status Examination score is 27/30. He has slight tenderness to palpation of the joint line of his left knee but has full range of motion. The rest of the examination is within normal limits.
Which of the following is the strongest risk factor for functional decline and increased mortality in this patient?
(Multiple Choice)
4.7/5  (85)
(85) A 39-year-old man comes to the office due to a skin rash on his lower extremities. Two weeks ago, he had a sore throat and was prescribed a 10-day course of amoxicillin, which he completed. His sore throat resolved, but he developed a nonpruritic rash on his legs 4 days ago. The patient reports no joint pain, abdominal pain, diarrhea, or urinary symptoms. Medical history is unremarkable, and he takes no other medications. He smokes a pack of cigarettes a day, drinks 4-6 beers on weekends, and does not use illicit drugs. The patient has had several sexual partners in his lifetime and uses condoms inconsistently.
Temperature is 36.7 C (98 F), blood pressure is 110/80 mm Hg, pulse is 80/min, and respirations are 12/min. A 0.5-cm mobile and nontender lymph node is palpable in the submandibular area. There is no pharyngeal erythema. Skin examination reveals a palpable and nonblanching rash, as shown in the exhibit.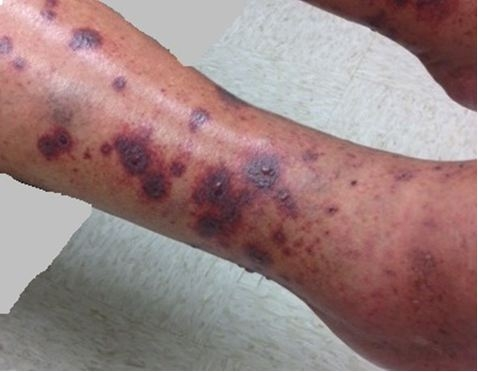 Laboratory results are as follows:
 Which of the following is the most likely cause of this patient's skin rash?
Laboratory results are as follows:
Which of the following is the most likely cause of this patient's skin rash? (Multiple Choice)
4.8/5 (77)
(77) A 32-year-old woman comes to the office with ear pain. She has seasonal allergies for which she has been taking over-the-counter decongestants. Two days ago, the patient began having throbbing right ear pain that became intense yesterday. The pain is much better today, but she noticed a white discharge on her pillow when she awoke this morning.
Otoscopic examination shows a cloudy and red tympanic membrane with an area of perforation.
Which of the following is the most likely outcome of this patient's condition?
(Multiple Choice)
4.9/5 (78)
(78) A 50-year-old man comes to the physician because of a non-healing skin lesion on his right thigh. The lesion first appeared as a boil; however, it increased in size over the last one month and has started draining purulent material. There is no history of trauma or insect bites. He also complains of malaise and constant right foot pain that improves with ibuprofen. Three months ago, he was treated for community-acquired pneumonia with 7 days of antibiotics and his symptoms have somewhat improved. He still has an occasional productive cough. He also thinks he might have lost some weight. He has no history of asthma or respiratory disease. His current medications include metformin, glipizide, and sitagliptin for diabetes, and rosuvastatin for hyperlipidemia. He is a lifetime non-smoker. He lives in upstate New York and often visits his friends in Long Island and Connecticut. He travels to Mississippi once or twice a year to visit his daughter.
His temperature is 37.8 C (100 F), blood pressure is 124/84 mm Hg, pulse is 96/min, and respirations are 18/min. Rales are heard over the right upper lung lobe. There are no heart murmurs. The abdomen is soft and no organomegaly is appreciated. Right foot examination reveals exquisite tenderness in the lateral midfoot. Skin examination shows a 2 x 2 cm beefy red granulomatous plaque with mild creamy exudate.
Foot CT scan reveals two lytic lesions and a large focal cyst in the mid foot. Chest imaging shows patchy alveolar opacities involving the right upper lung lobe; there is no hilar lymphadenopathy.
Which of the following is the most likely diagnosis?
(Multiple Choice)
5.0/5 (89)
(89) A 32-year-old woman, gravida 1 para 0, comes to the office at 30 weeks gestation for thrombocytopenia evaluation. The patient was found to have a platelet count of 110,000/mm3 during routine blood tests performed at 28 weeks gestation. She reports no history of blood disorders and has had no easy bruising, epistaxis, gingival bleeding, or blood in the urine or stool. Her pregnancy has been uneventful, and her only medication is a prenatal vitamin. The patient drank alcohol occasionally but stopped after conceiving. She does not use tobacco or illicit drugs.
Vital signs are within normal limits. There is no scleral icterus or lymphadenopathy. Skin examination shows no petechiae or ecchymosis. The uterus is appropriate in size for gestational age. Bilateral lower extremity 1+ pitting edema is present.
Laboratory testing performed today reveals the following:
 Peripheral smear shows no platelet clumping. Urinalysis reveals 1+ proteinuria. An anatomy ultrasound reveals normal fetal development, and the first trimester HIV screening was negative.
Which of the following is the most appropriate next step in management of this patient?
Peripheral smear shows no platelet clumping. Urinalysis reveals 1+ proteinuria. An anatomy ultrasound reveals normal fetal development, and the first trimester HIV screening was negative.
Which of the following is the most appropriate next step in management of this patient? (Multiple Choice)
4.8/5 (61)
(61) A 66-year-old man comes to the office for a follow-up visit. The patient was hospitalized 3 months ago for an upper gastrointestinal bleed. A duodenal ulcer with oozing hemorrhage was found on endoscopy and treated with thermal coagulation. Testing for infection with Helicobacter pylori was negative. The patient had taken nonsteroidal anti-inflammatory drugs frequently before the bleed but no longer uses them. His hemoglobin at discharge was 9.2 g/dL. Since this hospitalization, the patient has not noticed any melena, hematochezia, lightheadedness, changes in urine appearance or output, or abdominal pain. However, over the last 3 days, he has developed subjective fever, nausea, and malaise. Other review of systems is negative. The patient's other medical history includes hypertension, chronic kidney disease (baseline creatinine 1.3-1.5 g/dL), osteoarthritis, and hyperlipidemia. Medications include lisinopril, amlodipine, carvedilol, omeprazole, and atorvastatin. He has no known drug allergies.
Temperature is 38.1 C (100.6 F), blood pressure is 142/82 mm Hg, pulse is 85/min, and respirations are 16/min. Examination shows moist mucous membranes, no jugular venous distension, normal breath sounds, and no peripheral edema. The patient's abdomen is soft and nontender. Laboratory results are as follows:
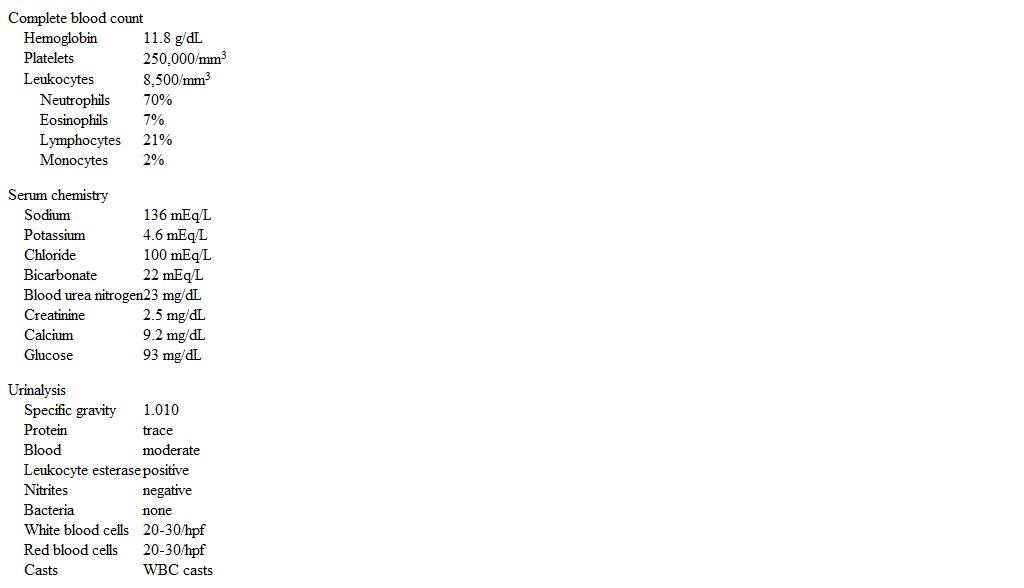 Which of the following is the most appropriate next step in management of this patient?
 (Multiple Choice)
4.9/5 (79)
(79) A 34-year-old woman comes to the office due to generalized weakness and extreme fatigue. She has had a sore throat, rhinorrhea, and cough productive of a small amount of clear sputum for the past 3 days. The patient has also experienced intermittent anorexia, nausea, and weight loss over the last several months. She has a history of primary hypothyroidism and takes 100 µg of levothyroxine daily. The patient does not use tobacco, alcohol, or illicit drugs.
Temperature is 37.6 C (99.8 F), blood pressure is 90/60 mm Hg, and pulse is 110/min. Cardiac, lung, and abdominal examinations are unremarkable.
Laboratory results are as follows:
 Which of the following is the most likely cause of this patient's current symptoms?
 (Multiple Choice)
4.8/5 (79)
(79) A 78-year-old woman comes to the physician with a red and swollen right foot for the last 2 weeks. She also reports mild pain that is relieved with acetaminophen. There is no associated fever, chills, or morning stiffness. She has not fallen or had trauma to the foot. The patient's other medical problems include coronary artery disease, hypertension, and type 2 diabetes mellitus complicated by peripheral neuropathy and chronic kidney disease. Her medications include aspirin, lisinopril, metoprolol, insulin, and gabapentin.
Vital signs are within normal limits. Her body mass index is 32 kg/m2. Examination shows warmth, erythema, and edema to the plantar surface of the right foot. There is a visible collapse of the arch of the right mid-foot. No skin ulcers or sinus tracts are present.
X-ray reveals advanced degenerative changes with dislocation of the mid-foot. Fluid aspiration from the right tarsus shows 200/mm3 red blood cells and 200/mm3 white blood cells (60% neutrophils). No crystals are seen and the Gram stain is negative.
Which of the following is the most appropriate next step in management?
(Multiple Choice)
4.8/5 (84)
(84) A 60-year-old woman comes to the office due to back pain. For the last 3 months, the patient has had dull, achy pain in the lumbar area radiating to the buttocks bilaterally. The pain is worse with lifting heavy boxes and is not relieved with acetaminophen or heating pads. She has had no fever, weight change, dysuria, incontinence, abdominal pain, or muscular weakness. The patient's medical history is notable for hypertension, for which she takes chlorthalidone, and osteoarthritis of the knees and hands. She does not use tobacco, alcohol, or illicit drugs.
Blood pressure is 148/98 mm Hg and pulse is 84/min. BMI is 32 kg/m2. Examination shows normal range of motion in the lumbar spine. Lower extremity strength, sensation, and reflexes are normal. Straight leg raise causes worsening of pain in the back but no radiation of pain.
Laboratory results are as follows:
 MRI of the lumbar spine shows a mild L4-L5 disc bulge without neural impingement and moderate facet arthropathy at multiple levels.
Which of the following interventions is most likely to be beneficial for this patient?
MRI of the lumbar spine shows a mild L4-L5 disc bulge without neural impingement and moderate facet arthropathy at multiple levels.
Which of the following interventions is most likely to be beneficial for this patient? (Multiple Choice)
4.8/5 (84)
(84) A 58-year-old man comes to the office due to tremor in his right hand. The patient first noticed the tremor a year ago, and it has progressively worsened to the point that he has difficulty writing. He often becomes self-conscious and feels embarrassed in social situations. The patient has had no headache, vision impairment, difficulty speaking or swallowing, sleep disturbances, bowel or bladder incontinence, extremity weakness or numbness, or memory loss. He has a history of hypertension for which he takes lisinopril. The patient is an attorney and does not use tobacco, alcohol, or illicit drugs. Family history is unremarkable.
Neurologic examination shows a Mini-Mental State Examination score of 29/30. A low-frequency tremor is noted in the right hand when resting the arm on a chair. The tremor is exacerbated by mental distraction such as counting backward and becomes less prominent with voluntary activity such as reaching for a pen. When the patient writes, his words become progressively smaller and illegible. There is mild rigidity of the bilateral upper extremities with decreased arm swing during ambulation. The remainder of the neurologic examination shows no other abnormalities.
Blood cell counts, serum chemistry studies, and thyroid function tests are within normal limits. MRI of the brain shows no abnormalities.
Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.7/5 (84)
(84) A 71-year-old woman comes to the physician because of increasing mid-back pain for the last 2 weeks. The pain has not improved with ibuprofen and acetaminophen combined with oxycodone. The pain limits her ambulation, dressing, and housekeeping.
Her temperature is 36.5 C (97.7 F), blood pressure is 130/70 mm Hg, pulse is 86/min, and respirations are 14/min. Her back examination shows moderate tenderness in the mid-back along the vertebral column. She has an otherwise unremarkable examination.
A lateral spine film reveals diffuse osteopenia with a vertebral compression fracture of T10. Blood for a complete blood count, metabolic panel, alkaline phosphatase, and 25-hydroxy vitamin D has been obtained.
Which of the following is most likely to provide early pain relief in this patient?
(Multiple Choice)
4.9/5 (79)
(79) A 73-year-old man comes to the office due to 2 months of worsening fatigue. The patient used to walk 1-2 miles each day but recently began having difficulty covering this distance. He has had no chest pain, shortness of breath, fever, joint pain, or abdominal issues. The patient underwent coronary artery bypass grafting 5 years ago. His other medical problems include hypothyroidism, hypertension, hyperlipidemia, and benign prostatic hyperplasia. He quit smoking 10 years ago and drinks 1 or 2 glasses of wine with dinner almost every day. His medications include aspirin, levothyroxine, atorvastatin, tamsulosin, metoprolol, and lisinopril.
Temperature is 37 C (98.6 F), blood pressure is 130/80 mm Hg, pulse is 78/min, and respirations are 14/min. Pulse oximetry shows 98% on room air. BMI is 29 kg/m2. Examination reveals mucosal pallor. There is no jugular venous distension, thyromegaly, or lymphadenopathy. The lungs are clear to auscultation. No hepatosplenomegaly or peripheral edema is present. Neurological examination is unremarkable.
Laboratory results are as follows:
 Peripheral blood smear shows ovalomacrocytic red cells and reduced granulocyte segmentation. Complete blood count was normal a year ago. Colonoscopy was normal 5 years ago.
Which of the following is the most appropriate next step in management of this patient?
Peripheral blood smear shows ovalomacrocytic red cells and reduced granulocyte segmentation. Complete blood count was normal a year ago. Colonoscopy was normal 5 years ago.
Which of the following is the most appropriate next step in management of this patient? (Multiple Choice)
4.9/5 (76)
(76) A 28-year-old woman at 15 weeks gestation comes to the office for a routine follow-up appointment. A year ago the patient was diagnosed with Graves disease that subsequently was well controlled on methimazole, but she was switched to propylthiouracil when she became pregnant. The patient feels tired, has occasional palpitations, and gained no weight during the first trimester; she has no other chronic medical conditions. Her mother has hypothyroidism.
Blood pressure is 124/78 mm Hg and pulse is 90/min. The thyroid gland is diffusely enlarged and nearly twice the normal size, but there is no bruit or nodularity. No proptosis is present. The remainder of the physical examination is within normal limits.
Laboratory results are as follows:
 Which of the following is the most appropriate next step in management of this patient?
 (Multiple Choice)
5.0/5 (74)
(74) A 31-year-old woman comes to the physician due to a year-long history of gradually worsening anxiety and restlessness. The patient is a nurse and feels tense and constantly worried about the welfare of her patients and whether her coworkers like her. As a result, she feels exhausted and discouraged most days. When the patient is home with her 2 preschoolers, she constantly worries about their becoming injured while playing, where they should go to school, and if she is a good mother. Her husband is supportive but thinks she is overprotective of the children and irrational in her concerns about family finances, their marriage, and everyday matters. The patient does not experience discrete anxiety attacks or depressed mood and cites no precipitating triggers or events. She knows that her worries are often unfounded but cannot stop worrying. The patient has a history of elevated triglycerides and takes no medications. Family history is unremarkable.
Which of the following is the best pharmacotherapy for this patient's condition?
(Multiple Choice)
4.9/5 (80)
(80) A 37-year-old woman comes to the physician because of persistent nasal congestion and runny nose. She states that she developed nasal congestion, a productive cough, and myalgias 4 weeks ago. She has been self-medicating with over-the counter nasal decongestant spray and antitussive liquid for the last 2 weeks, with gradual resolution of her cough and myalgias. However, she has developed recurrent nasal congestion and runny nose that is unresponsive to treatment. Her nasal discharge is clear. She has no associated sneezing, facial pain, or ocular itching. Her overall health is good and she denies similar symptoms in the past.
On physical examination, her nasal mucosa appears edematous and red. The remainder of her physical examination is within normal limits.
Which of the following is the best next step in management?
(Multiple Choice)
4.8/5 (84)
(84) A 76-year-old woman comes to the office for follow-up. While vacationing in Florida 6 weeks ago, she had an episode of dizziness and palpitations that lasted several hours. She was seen in the local emergency department, where she was found to be in atrial fibrillation with rapid ventricular rate. The patient was then admitted to the hospital for further evaluation and treatment.
Echocardiography showed a mildly dilated left atrium, a normal left ventricle with an ejection fraction of 65%, and no significant valvular abnormalities. Discharge medications included apixaban and long-acting diltiazem. The patient has had no symptoms since hospital discharge.
Physical examination today is unremarkable. ECG performed in the office shows persistent atrial fibrillation with a ventricular rate of 68/min. The patient asks about the possibility of using medications to keep her sinus rhythm normal.
Compared to her current treatment, the use of antiarrhythmic medications in this patient will more likely result in which of the following?
(Multiple Choice)
5.0/5 (76)
(76) An 18-year-old man comes to the office for a follow-up for asthma. He is a member of his college hockey team and practices daily. He has a history of seasonal allergies that required immunotherapy during childhood. About a month ago, he had an acute asthma exacerbation during a game and was subsequently hospitalized; before the game, the patient had an upper respiratory illness with cough, rhinorrhea, and shortness of breath requiring frequent use of a rescue inhaler. In the hospital, he improved quickly with intravenous corticosteroids and nebulized albuterol. He was discharged with a 10-day tapering-dose course of oral corticosteroids, which he finished 2 weeks ago, and as-needed inhaled albuterol. The patient has been taking prophylactic albuterol prior to games and practice but continues to have wheezing and chest tightness with exercise and exposure to cold air. He often has to take more than one dose of albuterol during a prolonged practice or game and wants to know how to prevent future attacks.
On physical examination, the lungs are clear to auscultation. Spirometry reveals an FEV1 of 92% predicted and an FEV1/FVC ratio of 85%. Chest radiograph shows no hyperinflation or infiltrates.
Which of the following is the most appropriate preventive intervention for this patient?
(Multiple Choice)
4.9/5 (71)
(71) A 36-year-old woman comes to the office due to fatigue and neck discomfort. Her symptoms began several weeks ago following an upper respiratory infection. The patient's medical history is unremarkable and she takes no medications. She works as a nuclear medicine technician, has a current 20-pack-year smoking history, and does not use alcohol or illicit drugs. There is no family history of thyroid cancer, but the patient's mother has hypothyroidism treated with thyroid replacement therapy.
Vital signs are normal. On examination, the thyroid gland is low lying and difficult to palpate. There is no cervical lymphadenopathy and the remainder of the examination is unremarkable.
Laboratory results show a TSH of 12 µU/mL and free T4 of 1.1 ng/dL (normal: 0.9-2.4). Ultrasound reveals 2 nodules in the right thyroid lobe, each measuring 1.7 cm in maximal diameter, and a 1.4 cm nodule in the left lobe. All of the nodules are hypoechoic without internal vascularity or microcalcification.
Which of the following increases the risk for thyroid cancer in this patient?
(Multiple Choice)
4.8/5 (66)
(66) A 70-year-old woman comes to the office due to pain and redness of the right elbow. The patient is a freelance writer and recently began writing regularly for a local newspaper. She first noticed the symptoms 2 days ago when her arm was supported on an arm rest while she used her computer. The pain has increased and she now feels a "bump" in the area. She does not recall any trauma to her elbow. The patient has had occasional knee pain after prolonged walking but no other joint pains. Medical history is notable for type 2 diabetes mellitus, hypertension, and osteoporosis.
Temperature is 38.3 C (101 F), blood pressure is 134/84 mm Hg, and pulse is 84/min. There is a fluctuant swelling on the back of her right elbow with overlying erythema, warmth, and tenderness but passive range of motion is normal.
Leukocyte count is 9,200/mm3, blood glucose is 130 mg/dL, and serum creatinine is 0.8 mg/dL. Aspiration of the swelling yields 35 mL of clear yellowish fluid with a decrease in size of the swelling. The nucleated cell count on the fluid is 10,500/mm3. Gram stain and crystal analysis are negative.
Which of the following is the best next step in management of this patient's condition?
(Multiple Choice)
4.7/5 (81)
(81) A 60-year-old man comes to the office for presurgical evaluation before right total knee replacement. He describes pain and limited mobility due to severe knee osteoarthritis. The patient has gained 4.5 kg (10 lb) over the last 6 months due to decreased physical activity. He has a history of coronary artery disease, hypertension, and hyperlipidemia. Current medications are low-dose aspirin, prasugrel, metoprolol, valsartan, and rosuvastatin.
A year ago, the patient underwent sirolimus-eluting stent implantation into the left anterior descending artery due to angina. Two months ago, echocardiogram showed normal left ventricular systolic function and no wall motion abnormalities.
Which of the following is the best preoperative recommendation for this patient?
(Multiple Choice)
4.8/5 (79)
(79) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)