



 Chat with AI
Exam 3: Office/Health Center

Exam 1: Emergency Department218 Questions
Exam 2: In-patient Facilities128 Questions
Exam 3: Office/Health Center900 Questions
Select questions type


A 25-year-old man comes to the physician for evaluation of abnormal liver tests. Blood work performed for graduate school enrollment revealed elevated bilirubin levels. He has no complaints and feels well. He reports that he had a history of jaundice and hepatitis at the age of 5. He took azithromycin for an upper respiratory infection approximately 2 months ago. He has no other medical problems. He does not smoke or drink alcohol, and he denies any recreational drug use.
Physical examination is unremarkable.
Laboratory results are as follows:
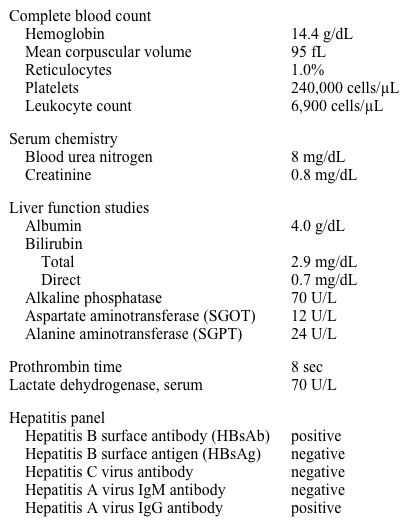 Which of the following is the best next step in management for this patient?
 (Multiple Choice)
4.9/5  (75)
(75) A 60-year-old man comes to the physician because of concerns about a lesion on his leg. It first appeared 3 months ago and rapidly grew to its current size. For the past several weeks, it has been stable with no additional growth. There is no associated pain.
The lesion is shown in the photograph below.
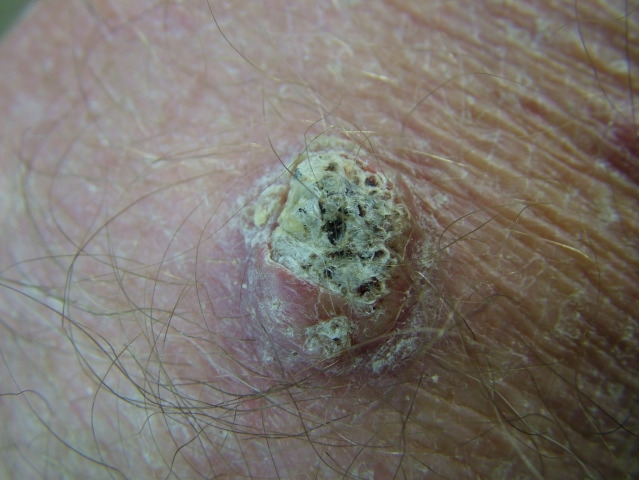 What is the most likely diagnosis?
 (Multiple Choice)
5.0/5 (71)
(71) A 52-year-old man comes to the clinic with concerns about his sexual desire. The patient's libido was previously normal but has progressively diminished over the last 6 months. The patient has also experienced fatigue and malaise without weakness or weight changes. He says, "I just do not feel like myself anymore." The patient is married and has 2 children. He reports a satisfying relationship with his wife, although his recent symptoms have been a source of tension between them. The patient's medical issues include gastroesophageal reflux, irritable bowel syndrome, and chronic low back pain from a workplace injury 2 years ago. He underwent spinal surgery after the incident but has had continuing pain, requiring opioid treatment for the last 2 years. Current medications include omeprazole, long-acting oxycodone, and as-needed acetaminophen and polyethylene glycol. He does not use alcohol, tobacco, or illicit drugs.
Vital signs are within normal limits. BMI is 26 kg/m2. Physical examination shows normal muscle bulk and body hair distribution. Auscultation of the heart and lungs is normal. Extremities are warm with palpable pulses. The testicles are small in volume with no tenderness or palpable masses. Neurological examination is normal, and visual fields are full to confrontation. Strength is normal in the extremities.
Morning serum total testosterone level is 180 ng/dL (normal 300-1200 ng/dL), which is consistent on repeat evaluation. Subsequent laboratory testing shows the following:
 Which of the following is the most likely cause of the patient's diminished sexual desire?
 (Multiple Choice)
4.9/5 (80)
(80) A 45-year-old woman comes to the physician with headache, trouble concentrating, and fatigue. She is a clerk at a high-end retail clothing store. She has had a mild, generalized headache for a week and finds it difficult to concentrate and maintain focus at work. The patient has also had progressive fatigue that is making it difficult to work and carry out daily activities. She has had heavy menses and taken iron supplements in the past. Two months ago, she got a sunburn on her face and arms while on vacation in Florida. The patient drinks 2-3 alcoholic beverages a week and has a 10-pack-year smoking history. She takes no prescribed or over-the-counter medications.
Her temperature is 36.7 C (98 F), blood pressure is 136/84 mm Hg, pulse is 90/min, and respirations are 16/min. She does not appear to be in acute distress. Her neck is supple. Cardiac, pulmonary, abdominal, and neurologic examinations are all within normal limits.
Laboratory results are as follows:
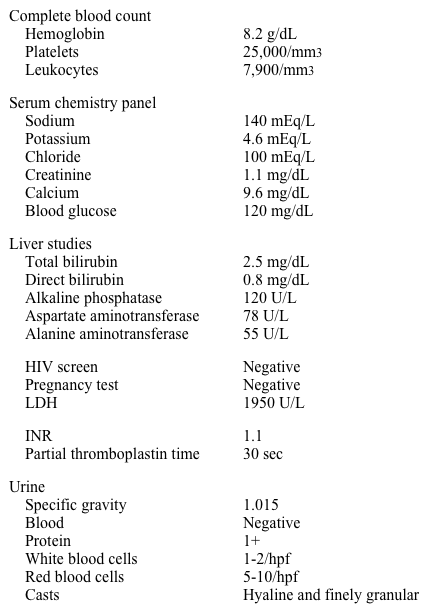 Direct Coombs test is negative and a blood smear shows hypochromic cells, few reticulocytes, and schistocytes.
Which of the following is the best next step in management of this patient?
Direct Coombs test is negative and a blood smear shows hypochromic cells, few reticulocytes, and schistocytes.
Which of the following is the best next step in management of this patient? (Multiple Choice)
4.8/5 (84)
(84) A 48-year-old woman comes to the office to discuss ongoing treatment for her recent diagnosis of right-sided, locally advanced, triple-negative (estrogen/progesterone receptor/HER2) breast cancer. The patient completed a course of chemotherapy 2 weeks ago and is scheduled for surgery in 2 weeks. She has a distant history of right leg venous thrombosis treated with 6 months of anticoagulation. The patient now feels well but is tired by the end of the day. She occasionally takes a nap around noon. She has no fever, palpitations, shortness of breath, or chest discomfort.
Blood pressure is 122/70 mm Hg and pulse is 77/min. On examination, an irregular mass is palpated in the right breast. There are no other significant examination findings.
Laboratory results are as follows:
 Serum folate and vitamin B12 levels are within normal limits.
Which of the following is the most appropriate next step in management of this patient's anemia?
Serum folate and vitamin B12 levels are within normal limits.
Which of the following is the most appropriate next step in management of this patient's anemia? (Multiple Choice)
4.9/5 (87)
(87) An 82-year-old farmer comes to the office due to easy bruising. Over the past year, he has had intermittent bruising on his arms with minimal trauma. The patient has had no bloody or dark-colored stools or other symptoms. He has a history of hypertension and osteoarthritis and had a left total hip replacement several years ago with no postoperative issues. The patient used to drink heavily but has been sober for more than 10 years. He has no family history of bleeding disorders. Vital signs are within normal limits. Physical examination shows no mucosal lesions. Cardiopulmonary auscultation is normal. The abdomen is soft and nontender. Skin findings are as follows:
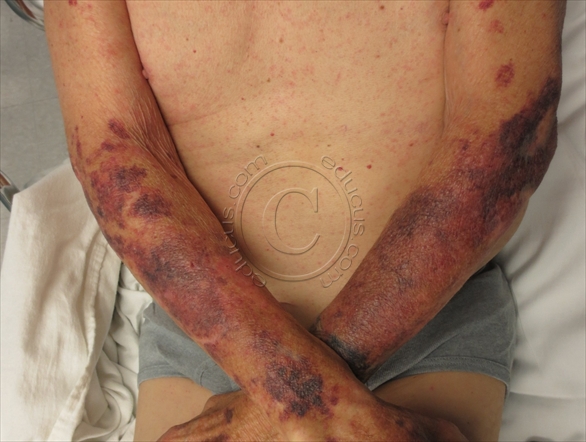 The lesions are not raised or tender, and the remainder of the skin examination is normal. Laboratory results are as follows:
 Which of the following most likely predisposed this patient to this skin condition?
The lesions are not raised or tender, and the remainder of the skin examination is normal. Laboratory results are as follows:
Which of the following most likely predisposed this patient to this skin condition? (Multiple Choice)
4.8/5 (79)
(79) A 39-year-old man comes to the physician with 3 weeks of progressive pedal edema. The edema is mild on awakening in the morning but gets worse as the day progresses. He has no shortness of breath, lower-extremity pain or warmth, or history of heart or liver disease.
His blood pressure is 155/96 mm Hg and pulse is 72/min. Jugular venous pressure is normal. Cardiopulmonary, abdominal, and neurologic examinations are within normal limits. There is soft, 2+ pitting edema of his legs below the knees.
After initial evaluation, the patient undergoes renal biopsy, which is consistent with focal segmental glomerular sclerosis.
Angiotensin-converting enzyme inhibitor therapy is most likely to delay progression of this patient's renal disease in the presence of which of the following additional findings?
(Multiple Choice)
4.9/5 (64)
(64) A 32-year-old nurse is evaluated 3 days after being exposed to a patient with active pulmonary tuberculosis. The source patient presented with cough, and a chest radiograph revealed a cavitary lung lesion. His sputum testing returned positive for acid-fast bacilli. The nurse cared for the patient for several hours without using respiratory precautions before airborne isolation precautions were implemented. She has had no symptoms and has no prior medical problems. Her only medication is an oral contraceptive. Vital signs are within normal limits, and physical examination shows no abnormalities.
Tuberculin skin test (TST) is administered and reveals a 2-mm induration at 48 hours.
Which of the following is the most appropriate next step in management of the nurse?
(Multiple Choice)
4.9/5 (87)
(87) A 60-year-old man comes to the office due to fever, shaking chills, diaphoresis, severe muscle pains, nausea, headache, and dark urine for the past 3 days. His other medical problems include chronic obstructive pulmonary disease (COPD), hypertension, and hyperlipidemia. The patient was admitted to the hospital 3 weeks ago for COPD exacerbation. His hospital course was complicated by bright red blood per rectum, for which he received 3 units of packed red blood cells. The bleeding stopped spontaneously and was attributed to diverticulosis. The patient's daily medications include hydrochlorothiazide, albuterol, and simvastatin. He just completed a 3-week corticosteroid taper. He lives in Rhode Island.
The patient's temperature is 39.8 C (103.6 F), blood pressure is 106/64 mm Hg, pulse is 108/min, and respirations are 18/min. Physical examination shows no skin rashes or joint swelling. There is no lymphadenopathy. His lungs are clear to auscultation. Heart sounds are normal. The remainder of the examination is unremarkable.
Laboratory results are as follows:
 Coagulation studies are normal. Urinalysis and microscopy are positive for urobilinogen and negative for blood and erythrocytes. Chest x-ray reveals no infiltrates.
Which of the following would be the most helpful for making the diagnosis in this patient?
Coagulation studies are normal. Urinalysis and microscopy are positive for urobilinogen and negative for blood and erythrocytes. Chest x-ray reveals no infiltrates.
Which of the following would be the most helpful for making the diagnosis in this patient? (Multiple Choice)
4.8/5 (83)
(83) A 38-year-old woman comes to the office due to an 8-month history of fatigue and difficulty performing work-related tasks. The patient works as a cashier and is unable to stand for a long time due to exhaustion and muscle aches. After unloading stock, she feels tired and has no energy for hours. The patient tries to rest at home after her shift but doesn't think this helps. She gets 7-8 hours of sleep a night but awakens feeling unrefreshed. Other than a viral infection 3 months ago, the patient has been in good health and takes no medication. She does not use tobacco, alcohol, or illicit drugs. She has no depression or anxiety. Family history is significant for hypertension in her father and depression in her mother and brother.
Vital signs and physical examination are unremarkable.
Laboratory results, including complete blood count, comprehensive metabolic panel, erythrocyte sedimentation rate, C-reactive protein, antinuclear antibody, TSH, and rheumatoid factor, are negative.
Which of the following is the most effective treatment for this patient's symptoms?
(Multiple Choice)
4.8/5 (69)
(69) A 66-year-old man comes to the office due to 3 months of scrotal discomfort. He reports heaviness and a dull ache in the left scrotal area that is worse toward the end of the day. He has no fever, dysuria, hematuria, or penile discharge. The patient has a history of hypertension and takes amlodipine. He had a vasectomy 20 years ago. He lives with his wife and has 2 grown children.
On examination, the abdomen is soft and nontender without organomegaly. Examination in the standing position shows a palpable, soft, irregular, nontender mass above the left testis that disappears in the supine position. There is no skin redness, groin bulge, or transillumination. Both testes are normal in size and without tenderness.
Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.7/5 (73)
(73) A 27-year-old woman comes to the physician for ear pain and decreased hearing. Eight days ago, she developed rhinorrhea and a mild sore throat. Three days later, she had decreased hearing and pain in her right ear. The patient went to an urgent care clinic and was prescribed amoxicillin, which she has taken since. Despite the amoxicillin, she continues to have ear pain and diminished hearing. She has no ear drainage, fever, chills, or headache. She is in good health and her only medication is birth control pills.
Vital signs are normal. There is no nystagmus. Otoscopic examination shows a cloudy, red, bulging tympanic membrane. Hearing is diminished in her right ear. A tuning fork placed in the center of her head lateralizes to the right. There is no posterior ear pain. There is no pharyngeal abnormality on examination. Her neck is supple, and gait and balance appear normal. All cranial nerves are intact.
Which of the following is the best management for this patient?
(Multiple Choice)
4.8/5 (80)
(80) A 34 year-old woman comes to the physician for nausea, vomiting, and early satiety over the last 2 weeks. The vomiting occurs mostly after eating, even though she consumes small portions. She underwent Roux-en-Y gastric bypass surgery for morbid obesity 3 months ago. Her post-operative course was uncomplicated. Prior to the surgery, she had acid reflux disease, type 2 diabetes mellitus, hypertension, and hyperlipidemia. The patient has lost 15.9 kg (35 lb) since the surgery. She currently takes omeprazole, a daily multivitamin, and calcium, iron, and vitamin B12 supplements.
Vital signs are within normal limits. Physical examination shows well-healed surgical scars on the abdomen but is otherwise unremarkable.
Laboratory results are as follows:
 Which of the following is the most likely diagnosis?
 (Multiple Choice)
4.9/5 (87)
(87) A 64-year-old man comes to the physician with a 2-week history of lightheadedness. He describes episodes of feeling woozy and a sense of heaviness in his head with squatting as he worked in his garden. He also describes occasional headaches that have recently become worse. He has no palpitations and has not lost consciousness. He has known nonischemic cardiomyopathy with a biventricular automatic implantable cardioverter defibrillator placed 2 years ago and a lead revision 1 month ago. Three weeks ago, an echocardiogram showed a left ventricular ejection fraction of 30%.
His supine blood pressure is 122/75 mm Hg, standing blood pressure is 125/78 mm Hg, and pulse is 60/min. Examination shows a plethoric face. The neck and upper chest veins are distended. No enlarged lymph nodes are palpated. A 2/6 holosystolic murmur radiating to the axilla is heard at the apex. Lungs are clear to auscultation. The liver span is 10 cm. There is trace bilateral edema of the lower extremities. Symmetrical pulses are palpated on the upper and lower extremities bilaterally.
Electrocardiogram shows atrioventricular sequential pacing.
Which of the following is the most likely diagnosis?
(Multiple Choice)
4.8/5 (81)
(81) A 48-year-old woman comes to the physician because of pain in her hands for the last 6 months. She also has joint stiffness every morning that lasts several hours. The patient has no weight loss, fever, chest pain, or back pain. Examination of her joints shows mild swelling and tenderness of several proximal interphalangeal joints, metacarpophalangeal joints, and both wrists. There are no skin rashes or mucosal lesions. No lymph nodes are palpable.
Laboratory results are as follows:
 X-ray of the hands reveals periarticular osteopenia and mild erosions of the proximal interphalangeal and metacarpophalangeal joints. She is started on naproxen and returns for follow-up 2 weeks later with marked improvement in her symptoms.
Which of the following is the best next step in the management of this patient?
X-ray of the hands reveals periarticular osteopenia and mild erosions of the proximal interphalangeal and metacarpophalangeal joints. She is started on naproxen and returns for follow-up 2 weeks later with marked improvement in her symptoms.
Which of the following is the best next step in the management of this patient? (Multiple Choice)
4.8/5 (83)
(83) A 20-year-old man comes to the physician complaining of cough, dyspnea on exertion, and nighttime awakenings with wheezing. His symptoms started 1 month ago after painting a room and using ammonia to clean the windows. He had mild shortness of breath and felt irritation and burning in his throat and nostrils afterwards. He did not seek further treatment at that time. He has a history of running marathons but is now limited to running 1 mile before he has to stop due to dyspnea and cough. He has no past medical history and does not use alcohol, tobacco, or illicit drugs.
Vital signs and physical examination are normal.
Office spirometry shows an FEV1 of 82% predicted, FVC 90% predicted, and FEV1/FVC 0.82. Chest x-ray is unremarkable.
Which of the following would be most helpful to establish the diagnosis?
(Multiple Choice)
4.7/5 (80)
(80) A 68-year-old man comes to the office with a 2-year history of increasing shortness of breath and daily cough with sputum for the past several months. The patient now becomes dyspneic walking 2 blocks or up 1 flight of stairs. He has had no fever or chest pain. The patient has not seen a physician for many years and takes no regular medication, but on several occasions, he has used his wife's albuterol inhaler, which provides some symptom relief. He has a 40-pack-year history and is trying to stop smoking.
Blood pressure is 140/80 mm Hg, pulse is 90/min, and respirations are 18/min. Pulse oximetry is 88% at rest on ambient air. Examination shows jugular venous distension, increased anteroposterior chest diameter, an accentuated S2, and a holosystolic murmur at the left sternal border, the intensity of which increases with inspiration. Lung auscultation reveals a prolonged expiration phase with decreased breath sounds throughout. There is mild bilateral pitting edema of the lower extremities.
Pulmonary function testing results are as follows:
 Chest radiograph shows hyperinflated lungs with a flattened diaphragm but no parenchymal opacities.
In addition to smoking cessation, which of the following is most likely to prolong survival in this patient?
Chest radiograph shows hyperinflated lungs with a flattened diaphragm but no parenchymal opacities.
In addition to smoking cessation, which of the following is most likely to prolong survival in this patient? (Multiple Choice)
4.8/5 (89)
(89) An 18-year-old previously healthy woman comes to the office due to redness and discharge from both eyes for the past several days. The patient also has itchiness and irritation in the eyes and has awakened with crusting in the morning. She has had a runny nose and sneezing for the last 4 days but no fever, eye pain, or photophobia. She does not wear contact lenses and her vision is unchanged. The patient is visiting her aunt, who has 2 small children; they are not ill but have a pet cat.
Eye examination reveals diffuse bilateral conjunctival erythema and edema with clear discharge. Pupils are equal and reactive bilaterally. Vision acuity is normal. No corneal opacities are present and the anterior chambers appear grossly normal.
Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (64)
(64) A 22-year-old African American man is evaluated for gross hematuria. He has had 5 days of grossly bloody urine every time he urinates. He denies associated flank or abdominal pain, back or abdominal trauma, fever, chills, or dysuria. There is no family history of either a bleeding disorder or kidney disease. He had a similar episode one year ago which lasted 5-10 days and resolved spontaneously. During that time, he had an unremarkable ultrasound of his kidneys. He has had no recent illnesses and he takes no medications. He had an uncomplicated knee surgery two years ago for a torn ligament. He had two girlfriends over the last year, and he used condoms occasionally.
He is very muscular with a BMI of 25 kg/m2. His blood pressure is 133/82 mm Hg and pulse is 89 /min. He has no costovertebral angle tenderness. Abdominal exam is unremarkable. Laboratory results are as follows:
 Which of the following is most likely to confirm this patient's diagnosis?
 (Multiple Choice)
5.0/5 (81)
(81) A 40-year-old woman comes to the office due to a red left eye. She was feeling well until 2 days ago when she awoke in the morning with sudden onset of redness and tearing of the eye. The patient has had no ocular itching or pain, but says, "I feel like there is something caught in my eye but I can't find anything." Medical history is notable for asthma, for which she uses an albuterol inhaler as needed. The patient does not use tobacco, alcohol, or illicit drugs. She works as an elementary school teacher and lives with her husband and 2 teenage children.
Vital signs are normal. Examination shows normal extraocular movements, pupillary reflexes, funduscopic findings, and visual acuity. Inspection of the eye is as shown in the exhibit.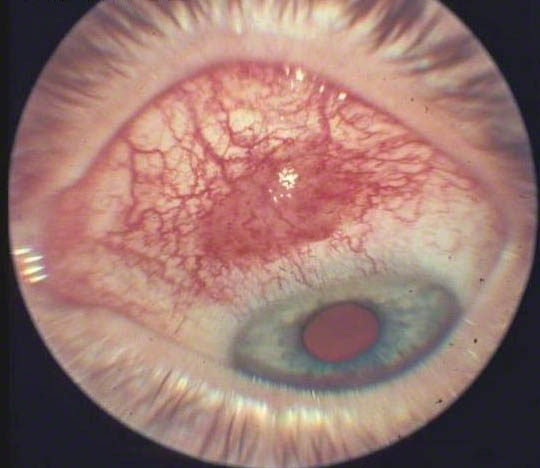 Which of the following is the most appropriate next step in management of this patient's eye condition?
 (Multiple Choice)
4.8/5 (78)
(78) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)