



 Chat with AI
Exam 3: Office/Health Center

Exam 1: Emergency Department218 Questions
Exam 2: In-patient Facilities128 Questions
Exam 3: Office/Health Center900 Questions
Select questions type


A 35-year-old man is evaluated for heartburn and a sour taste in his mouth. The patient initially presented 2 months ago due to these symptoms, and a proton pump inhibitor was begun. He has had mild relief but continues to have bothersome symptoms after his evening meal. The patient has avoided drinking coffee and eating fatty or spicy foods, and he eats his evening meal at least 2 hours before bedtime. He has had no weight loss, abdominal pain, nausea, vomiting, or black or tarry stools. The patient has no other medical issues; his only medication is lansoprazole, which he takes 30 minutes before breakfast. He works in a bank and does not use tobacco, alcohol, or illicit drugs. His father was diagnosed with colon cancer at age 67.
Vital signs are within normal limits. BMI is 28 kg/m2. Physical examination is unremarkable.
Laboratory results are as follows:
 Which of the following is the most appropriate next step in management of this patient?
 (Multiple Choice)
4.8/5  (88)
(88) A 59-year-old man with a long history of type 2 diabetes mellitus comes to the physician with complaints of progressive muscle weakness. Six months ago, he experienced clumsiness while holding onto objects or buttoning his shirt. Two weeks ago, he felt weakness in his right foot. Since then he has nearly fallen 3 times. He reports that his speech has become slurred and he also has painful muscle cramps.
His vital signs are normal. Neurologic examination reveals mild-to-moderate dysarthria with a nasal quality. Strength is 4/5 in the proximal right upper extremity and 3/5 distally, with moderate hand muscle atrophy and contracture of the third digit. Strength is 5/5 proximally and 4/5 distally in the right lower extremity. The left arm and leg have normal strength. Both tongue and muscle fasciculations are present. Sensory examination is normal. Reflexes are decreased at the biceps and brachioradialis but are increased at the knees and ankles with bilateral extensor plantar responses.
Which of the following is the most likely diagnosis?
(Multiple Choice)
4.8/5 (83)
(83) A 27-year-old man calls the office to ask for advice about fever. He has had a mild cough for the last 2 days and developed fever and chills today, with a home temperature of 38.7 C (101.7 F). Several of his coworkers have been sick recently. The patient's past medical history is significant for a motorcycle accident requiring splenectomy at age 22. All his vaccinations, including influenza and pneumococcal vaccines, are up to date. He was given a prescription for amoxicillin-clavulanate 6 months ago "just in case."
Which of the following is the best advice for the patient?
(Multiple Choice)
4.8/5 (78)
(78) A 52-year-old man comes to the office due to fatigue and muscle pain over the last several months. He has also experienced weight gain, dry skin, daytime sleepiness, and erectile dysfunction. Medical history is notable for hypertension treated with enalapril, hypercholesterolemia treated with rosuvastatin, and a nonfunctioning pituitary adenoma that was treated with trans-sphenoidal resection followed by radiation therapy 8 years ago. MRI 8 months ago showed a stable, 5-mm, residual pituitary mass. He has no headaches, vision loss, dark stools, or shortness of breath. The patient does not drink alcohol but has a 20-pack-year smoking history.
Blood pressure is 130/80 mm Hg and pulse is 58/min with no orthostatic changes. BMI is 29 kg/m2. The remainder of the physical examination (including peripheral vision, testes, and thyroid) is normal.
Laboratory results are as follows:
 Which of the following tests is most helpful in establishing this patient's diagnosis?
 (Multiple Choice)
4.9/5 (75)
(75) A 76-year-old woman comes to the physician for routine follow-up. She complains of frequent right knee pain and swelling that is relieved by daily naproxen. She was offered knee replacement surgery for her severe osteoarthritis, but she refused. She was diagnosed with stable angina five years ago and has not undergone any coronary intervention. She denies chest pain with mild exertion, but admits to occasional chest discomfort with moderate exertion.
Her other medical problems include atrial fibrillation, hypertension, hyperlipidemia, and diet-controlled type 2 diabetes mellitus. Her current medications include warfarin with target INR 2-3, low-dose aspirin, metoprolol, enalapril, and rosuvastatin. She is an ex-smoker with a 35 pack-year smoking history.
Her blood pressure is 130/69 mm Hg and pulse is 80/min and irregular. Her BMI is 42 kg/m2. A 2/6 mid-systolic murmur is heard at the left sternal border. Her lungs are clear. The right knee is mildly swollen and tender.
Laboratory results are as follows:
 Which of the following additional medications would most likely benefit the patient?
 (Multiple Choice)
4.9/5 (71)
(71) A 58-year-old woman comes to the physician because of progressive generalized weakness over the last two months. Two weeks ago, she woke up with a nosebleed that stopped after applying pressure to her nostril. She has had no other bleeding events. She was diagnosed with early stage breast cancer 6 years ago and underwent surgery and adjuvant combination chemotherapy with doxorubicin, cyclophosphamide, and paclitaxel. She underwent gastric bypass surgery two years ago. Her other medical problems include depression and gastroesophageal reflux disease. She takes paroxetine, omeprazole, and calcium and vitamin D supplements. She had smoked 1 pack of cigarettes daily for 12 years, but stopped after her diagnosis of breast cancer.
Her blood pressure is 112/70 mm Hg and pulse is 89/min. Her BMI is 30 kg/m2. Cardiopulmonary examination is normal. Breast examination shows a well-healed scar over the left breast. The abdomen is soft and non-tender and there is no organomegaly. There are no skin rashes.
Laboratory results are as follows:
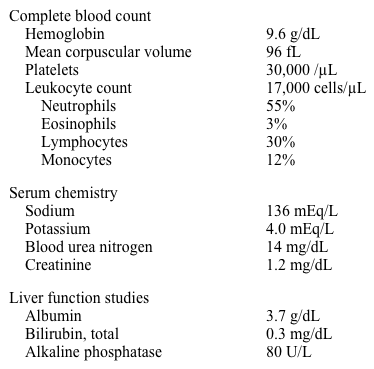 The peripheral smear reveals no platelet clumping but does show polychromasia; occasional nucleated red blood cells; metamyelocytes; and cells with large nuclei, prominent nucleoli, and scant cytoplasm. There are no schistocytes.
This patient's current condition is most likely related to which of the following?
The peripheral smear reveals no platelet clumping but does show polychromasia; occasional nucleated red blood cells; metamyelocytes; and cells with large nuclei, prominent nucleoli, and scant cytoplasm. There are no schistocytes.
This patient's current condition is most likely related to which of the following? (Multiple Choice)
4.8/5 (81)
(81) A 70-year-old man comes to the office due to trouble sleeping. He has experienced a progressively worsening urge to move his legs when he watches television at night; the urge persists when he goes to bed and often prevents him from getting to sleep. The sensation to move his legs is not present during the day and disappears when he gets up and walks. There is no associated lower extremity numbness, tingling, or weakness. Medical history is notable only for mild hypertension treated with lisinopril.
Physical examination, including neurologic examination, is unremarkable.
Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.9/5 (91)
(91) A 65-year-old man is evaluated for a 3-month history of malaise and abdominal distension with increasing abdominal girth. He has also had progressive shortness of breath and generalized weakness. Past medical problems include hypertension, hypercholesterolemia, type 2 diabetes mellitus, heart failure, and hepatitis C. The patient also has a history of prostate cancer, which was treated with radical prostatectomy and radiation therapy a year ago. He drinks 1 or 2 cans of beer a day and has smoked a pack of cigarettes daily for 20 years. He admits to using injection drugs in the past.
Vital signs are within normal limits. Chest examination reveals basilar crackles in the lungs and a grade 2 systolic murmur along the left sternal border. The abdomen is nontender and distended with ascites. There is no rebound tenderness or rigidity. The liver edge is palpable 2 cm below the right costal margin and mild splenomegaly is present. There is 2+ bilateral lower extremity pitting edema.
Laboratory results are as follows:
 Which of the following is the most likely cause of this patient's ascites?
 (Multiple Choice)
4.8/5 (75)
(75) A new nuclear stress test modality is tested in a broad range of patients with suspected coronary artery disease. The patients' pre-test probability of having the disease is determined by their Framingham score. Their post-test probability is then calculated using the results of the new test, and the following curves are constructed.
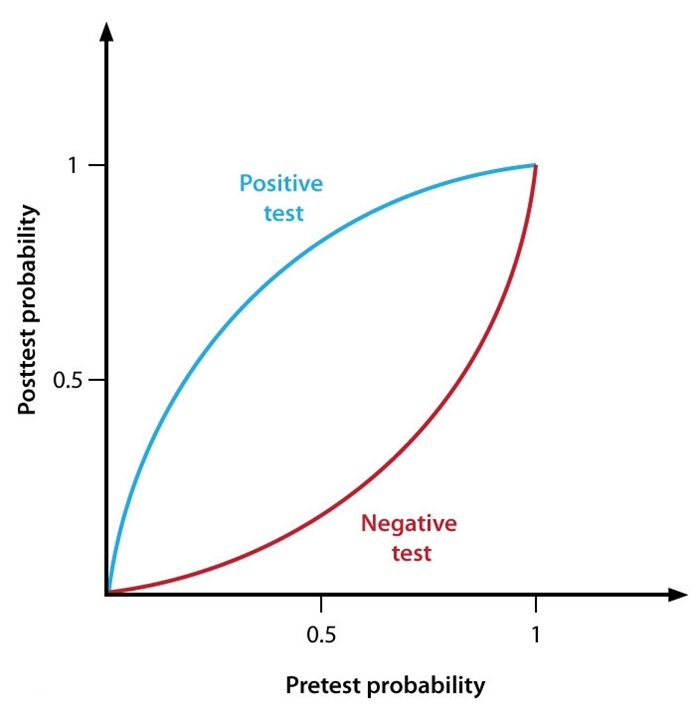 The new test is most useful for diagnosing coronary artery disease in patients with which of the following pretest probabilities?
 (Multiple Choice)
4.9/5 (84)
(84) A 25-year-old woman comes to the physician because of multiple oral ulcers that have occurred intermittently for the last two months. These ulcers are very painful and are associated with fatigue and low grade fever. She is a teacher and several of her kindergarten students have been ill with hand-foot-and-mouth disease. She has a five-year history of a clinical diagnosis of genital herpes with intermittent flares requiring oral acyclovir. Her mother has an unspecified autoimmune disease with joint pains for which she has taken intermittent steroid therapy over the last 10 years.
Physical examination reveals three vesicular lesions on her buccal and gingival mucosa and acneiform lesions on her face and back. Scars are noted on the patient's vulvar area. The remainder of the physical examination is normal.
Which of the following is the most likely diagnosis?
(Multiple Choice)
4.8/5 (91)
(91) A 32-year old woman comes to the physician because of shortness of breath while walking uphill or climbing steps for the last 3 months. She immigrated with her family to the United States from Thailand 15 years ago. She is a nurse's aide and had a recent work physical performed prior to starting a new job. The physician noted "irregular heart sounds" and performed an EKG, which showed atrial fibrillation with a ventricular rate of 85 beats per minute.
A transthoracic echocardiogram showed normal left ventricular size and function with an ejection fraction of 60%. The left atrium was severely dilated and the mitral valve leaflets were thickened with restricted motion and mild focal calcification. The mitral valve area was calculated at 1.0 cm2 (normal 4-6 cm2) with a moderate degree of mitral regurgitation. The aortic valve was trileaflet without stenosis or regurgitation. There was moderate tricuspid regurgitation with an estimated pulmonary artery systolic pressure of 72 mm Hg, consistent with severe pulmonary hypertension (normal < 30 mm Hg).
Which of the following is a contraindication to percutaneous mitral balloon valvotomy in this patient?
(Multiple Choice)
4.8/5 (88)
(88) A 77-year-old woman comes to the physician because she "passed out." She says that over the last few months she has had several episodes where she feels very lightheaded and must sit down. On one occasion, she did actually lose consciousness and hit her head against a bathroom counter. There are no clear precipitants of these episodes. She denies chest pain or pressure. She thinks that she is more short of breath while playing tennis than she used to be in the past. Her other medical problems include hypertension and mild chronic kidney disease. Her medications include amlodipine, lisinopril, simvastatin, and aspirin.
Her blood pressure is 115/70 mm Hg, pulse is 62/min, and BMI is 23 kg/m2. The patient is in no acute distress. There is a normal S1 and a soft S2. There is a III/VI mid-peaking systolic ejection murmur at the right upper sternal border that radiates to both carotid arteries. Her lungs are clear to auscultation. Her abdomen is soft and non-distended. Peripheral pulses are 2+ and symmetric.
An echocardiogram showed normal left ventricular function, mild left ventricular hypertrophy, and moderate calcific aortic stenosis with an estimated aortic valve area of 1.4 cm2 (normal 3-4 cm2).
The patient was given a 24-hour Holter monitor. The tracing below was recorded at 1:25 pm.
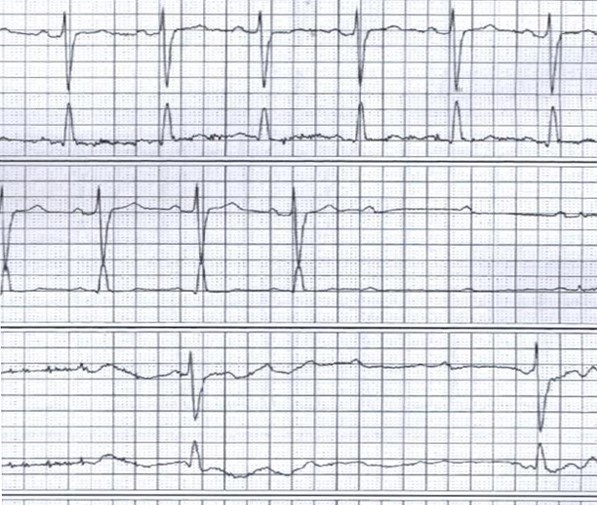 Which of the following would be the best next step in managing this patient?
 (Multiple Choice)
5.0/5 (97)
(97) A 34-year-old forest service firefighter comes to the physician with an itchy rash on both arms. The rash began as small red papules 3 days ago and subsequently developed yellow blisters. The lesions appear to be spreading to the adjacent skin. He has no fever, chills, or malaise. The patient has no significant past medical history and takes no medications. He has been sexually active with a new partner over the last 6 months and uses condoms. He rents an apartment with 2 friends and they share a bathroom.
A photograph of his arm is shown below.
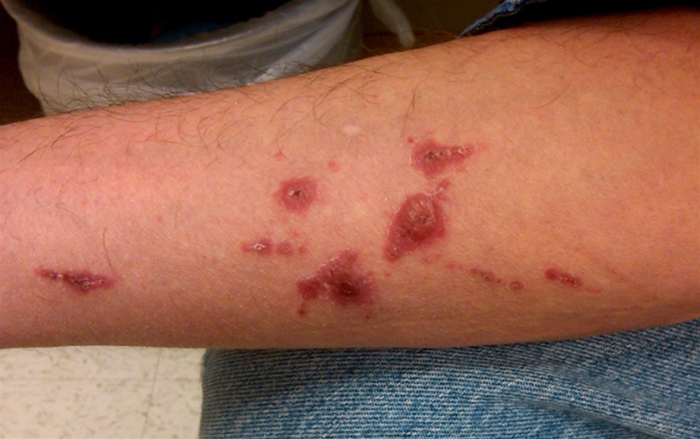 Which of the following is the best initial treatment for this patient's condition?
 (Multiple Choice)
5.0/5 (94)
(94) A 42-year-old woman comes to the office for an annual examination. The patient feels well and has regular menses with no abnormal bleeding. She has a new vaginal discharge but no vulvar pruritus or pelvic pain. The patient is sexually active and has had only women partners. Her current relationship began 6 months ago. She has no chronic medical conditions and takes no medications.
Vital signs are normal. BMI is 31 kg/m2. There is no vulvar erythema. Microscopic examination of the vaginal discharge reveals the following:
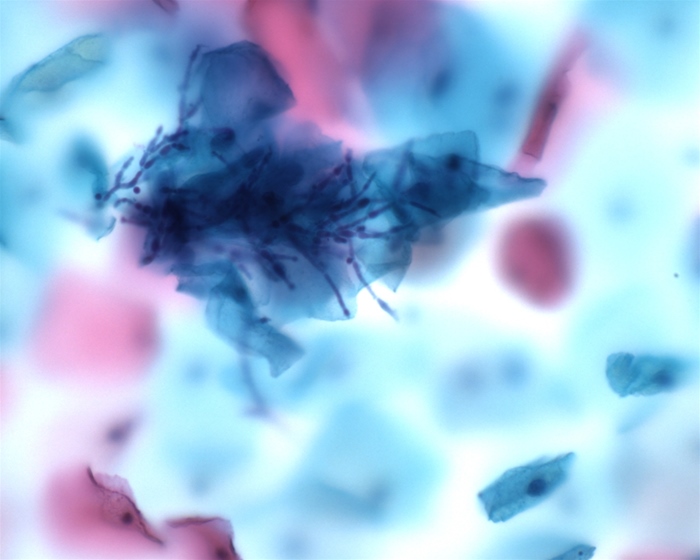 Which of the following is the most likely diagnosis in this patient?
 (Multiple Choice)
4.9/5 (89)
(89) A 54-year-old man is evaluated for worsening upper abdominal discomfort and heartburn. For the last 5 years, his occasional midepigastric pain after meals and at night was relieved by over-the-counter ranitidine. Over the last 6 months, the patient's symptoms have occurred almost daily and are not relieved by ranitidine. He has had no dysphagia, odynophagia, hematemesis, melena, or weight loss. He has a 40-pack-year smoking history.
Vital signs are within normal limits. BMI is 29 kg/m2. The abdomen is soft and nontender. Stool occult blood testing is negative.
Upper gastrointestinal endoscopy shows moderate esophagitis with red, velvety mucosa extending from the gastroesophageal junction into the distal esophagus. There is a moderate hiatal hernia but no erythema or ulcers in the stomach or duodenum. Biopsy shows Barrett esophagus with high-grade dysplasia.
In addition to daily proton pump inhibitor therapy, which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (88)
(88) A 35-year-old woman comes to the office due to fatigue and difficulty lifting heavy objects over the last several months. She has gained approximately 9.1 kg (20 lb) during the past year. The patient also reports easy bruising with minimal trauma. Medical history is unremarkable, and her only medication is a combined estrogen/progestin oral contraceptive. She does not use tobacco, alcohol, or illicit drugs. The patient lives with her boyfriend and has no children. She is employed as a secretary at a dental office.
Blood pressure is 160/100 mm Hg and pulse is 80/min. BMI is 29 kg/m2. Examination shows facial plethora and excessive fat deposition in the supraclavicular and posterior neck regions. Skin examination shows excessive terminal hair on the face and lower abdomen.
Laboratory results are as follows:
 Which of the following tests is the best next step in establishing this patient's diagnosis?
 (Multiple Choice)
4.9/5 (70)
(70) A 25-year-old previously healthy woman comes to the office after her sex partner was diagnosed with primary syphilis 2 weeks ago. She has no symptoms. The patient uses barrier contraceptives inconsistently. Her physical examination is unremarkable.
Which of the following is the most appropriate management for this patient?
(Multiple Choice)
4.9/5 (75)
(75) A 52-year-old man comes to the physician with generalized weakness and abdominal distention. He has had these symptoms for the past 5 months and says that his abdominal girth has gradually increased. He has no other complaints. His other medical problems include hepatitis C-induced cirrhosis and depression. The patient has a 24-pack-year history of cigarette smoking and drinks vodka daily. He admits to using intravenous drugs in the past.
His vital signs are within normal limits, but he has gained 6.8 kg (15 lb) since his last visit 6 months ago. Examination reveals a distended and nontender abdomen with fluid wave and shifting dullness. There is no rebound tenderness or rigidity. His cardiopulmonary examination is unremarkable. Skin examination shows a few spider nevi. He has 2+ pitting pedal edema to the mid-shin bilaterally.
Laboratory results are as follows:
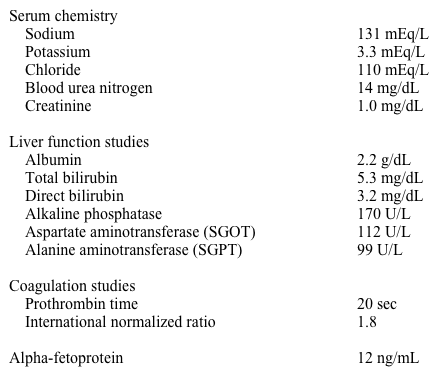 Abdominal ultrasound confirms the presence of a moderate amount of ascites, no focal liver masses, and moderate splenomegaly. A diagnostic paracentesis shows polymorphonuclear count of 88/mm3, total protein of 1.4 g/dL, and albumin of 0.9 g/dL.
Which of the following is the best next step in management of this patient?
Abdominal ultrasound confirms the presence of a moderate amount of ascites, no focal liver masses, and moderate splenomegaly. A diagnostic paracentesis shows polymorphonuclear count of 88/mm3, total protein of 1.4 g/dL, and albumin of 0.9 g/dL.
Which of the following is the best next step in management of this patient? (Multiple Choice)
4.8/5 (78)
(78) A 27-year-old woman comes to the physician because of irregular menstrual periods and failure to conceive. She was on oral contraceptive pills for 4 years for irregular menstrual periods, which she discontinued 7 months ago. She has never before tried to become pregnant. There is no history of hirsutism or abdominal striae. She has no other medical problems and takes no medications. She has a sedentary desk job at a research laboratory. She does not smoke cigarettes or drink alcohol. Her partner is in good health, and his semen analysis is normal.
Her blood pressure is 126/78 mm Hg and pulse is 72/min. Her BMI is 30 kg/m2. Physical examination, including bimanual pelvic examination, is unremarkable.
Laboratory investigations performed on the 2nd day of her menstrual cycle reveal:
 Mid-luteal phase progesterone is very low, indicating that she is not ovulating. Her fasting venous glucose level is 104 mg/dL.
Which of the following is the most appropriate initial treatment for her ovulatory dysfunction?
Mid-luteal phase progesterone is very low, indicating that she is not ovulating. Her fasting venous glucose level is 104 mg/dL.
Which of the following is the most appropriate initial treatment for her ovulatory dysfunction? (Multiple Choice)
4.7/5 (55)
(55) A 33-year-old primigravida at 32 weeks gestation comes to the office due to severe generalized itching that is most intense on her hands and feet. Her pregnancy has been uncomplicated so far. The patient has no other medical conditions and her only medication is a daily prenatal vitamin. She does not use tobacco, alcohol, or illicit drugs.
Blood pressure is 106/60 mm Hg, pulse is 56/min, and respirations are 12/min. Skin examination shows excoriations on her forearms and anterior shins. The abdomen is nontender and there is no hepatosplenomegaly. The remainder of the physical examination is within normal limits.
Laboratory results are as follows:
 Viral hepatitis panel is negative. Abdominal ultrasound reveals normal liver echogenicity and no dilated bile ducts.
Which of the following is the most appropriate next step in management of this patient?
Viral hepatitis panel is negative. Abdominal ultrasound reveals normal liver echogenicity and no dilated bile ducts.
Which of the following is the most appropriate next step in management of this patient? (Multiple Choice)
4.9/5 (73)
(73) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)