



 Chat with AI
Exam 3: Office/Health Center

Exam 1: Emergency Department218 Questions
Exam 2: In-patient Facilities128 Questions
Exam 3: Office/Health Center900 Questions
Select questions type


A 78-year-old man is evaluated for syncope. He was hospitalized a week ago after passing out in his garden and sustaining a minor head injury. He had no prodromal symptoms, chest pain, or palpitations. After the syncopal episode, he was not confused and had only a mild headache due to trauma. Four months ago, the patient had a similar episode at home but sustained no injuries. He has hypertension, for which he takes lisinopril and amlodipine. He does not use tobacco, alcohol, or illicit drugs. He walks 4 miles a day.
Blood pressure is 140/90 mm Hg supine and 138/88 mm Hg standing, and pulse is 75/min and regular. Fourth heart sound is heard on cardiac auscultation. There are no carotid bruits. Carotid sinus massage does not provoke long pauses.
Electrocardiogram shows normal sinus rhythm with tall R waves. An echocardiogram done in the hospital showed left atrial enlargement, left ventricular hypertrophy, and ejection fraction of 60%.
Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5  (80)
(80) A 38-year-old woman comes to the office with 2 weeks of mild headache and nausea. She has a history of end-stage renal disease secondary to lupus nephritis and had an allograft renal transplant a year ago. Her medications include tacrolimus, azathioprine, and prednisone. The patient has also been taking lansoprazole for indigestion for the past 3 weeks. She does not use tobacco, alcohol, or illicit drugs. To take better care of herself, she has begun eating plenty of fruits and green vegetables and drinking grapefruit juice.
The patient is afebrile. Her blood pressure was 120/70 mm Hg a month ago and is now 150/90 mm Hg. Examination shows clear lung fields, normal heart sounds, and a soft and nontender abdomen. She has mild bilateral hand tremor without muscle weakness or sensory loss. There is no lower extremity edema.
Laboratory results are as follows:
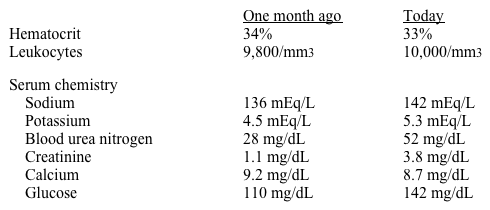 Urinalysis shows clear urine with no protein, blood, cells, or casts. Renal ultrasound shows no abnormalities of the transplanted kidney with no urinary leak or obstruction.
Which of the following is the most likely cause of this patient's renal failure?
Urinalysis shows clear urine with no protein, blood, cells, or casts. Renal ultrasound shows no abnormalities of the transplanted kidney with no urinary leak or obstruction.
Which of the following is the most likely cause of this patient's renal failure? (Multiple Choice)
4.9/5 (77)
(77) A 54-year-old woman comes to the emergency department due to persistent nonproductive cough, mild shortness of breath, and sharp, right-sided chest pain over the last week. The patient has been taking moxifloxacin prescribed by her primary care physician for the last 5 days, but her symptoms have not improved. She was diagnosed with early-stage right breast cancer 5 months ago and underwent lumpectomy and radiation therapy, which she completed 6 weeks ago. Her other medical issues include hypertension, hyperlipidemia, and gastroesophageal reflux disease. The patient has had no prior respiratory problems and is a lifelong nonsmoker.
Temperature is 38.4 C (101.1 F), blood pressure is 150/90 mm Hg, pulse is 80/min, and respirations are 15/min. Examination reveals crackles over the right lower lung with dullness on percussion. The remainder of the examination is unremarkable.
Laboratory studies reveal a leukocyte count of 13,000/mm3. Chest x-ray is shown below.
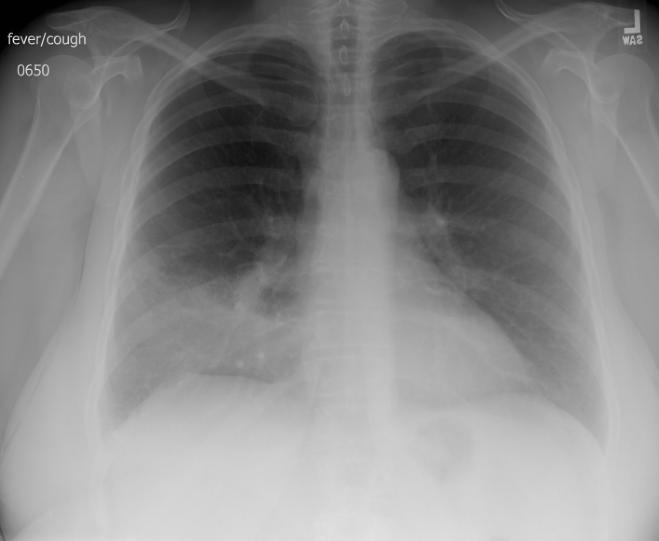 Previous chest x-ray performed at the time of the patient's breast cancer diagnosis was unremarkable, and echocardiography revealed a normal left ventricular ejection fraction, evidence of diastolic dysfunction, and no significant valvular abnormalities.
This patient would most likely respond to which of the following therapies?
Previous chest x-ray performed at the time of the patient's breast cancer diagnosis was unremarkable, and echocardiography revealed a normal left ventricular ejection fraction, evidence of diastolic dysfunction, and no significant valvular abnormalities.
This patient would most likely respond to which of the following therapies? (Multiple Choice)
4.8/5 (70)
(70) A 75-year-old man has a 3 month history of cough and weight loss. He also complains of back pain and difficulty breathing. He was initially wheelchair bound, but now he is bedbound and unable to perform any of his activities of daily living. He has a long history of cigarette smoking.
On examination, he is thin and appears tired. Vital signs are within normal limits. Breath sounds are decreased at the left lung base. A stage 2 presacral pressure ulcer is present.
CT scan of the chest demonstrates a left perihilar mass, multiple enlarged mediastinal lymph nodes, and bone metastases. A biopsy at bronchoscopy confirms a diagnosis of squamous cell cancer.
Which of the following is the best next step in the management of this patient?
(Multiple Choice)
4.9/5 (79)
(79) A 72-year-old man comes to the office 4 weeks following discharge from the hospital due to an episode of acute decompensated heart failure. The patient feels much better now but claims that he gets tired easily. He becomes short of breath after walking a few blocks on a level surface. He has a history of myocardial infarction, coronary artery bypass grafting, ischemic cardiomyopathy, hypertension, hyperlipidemia, and type 2 diabetes mellitus. The patient has had several hospital admissions for decompensated heart failure over the past 2 years. His home medications include aspirin, carvedilol, sacubitril-valsartan, atorvastatin, furosemide, and insulin.
Temperature is 37.2 C (99 F), blood pressure is 128/76 mm Hg, pulse is 76/min, and respirations are 16/min. Pulse oximetry is 94% on room air. The patient is in no apparent respiratory distress. Jugular venous pressure is measured at 8 cm H2O. Lung examination reveals clear lung fields with decreased breath sounds at the bases. Cardiac examination reveals normal S1 and S2 along with a 2/6 holosystolic murmur heard over the cardiac apex. There is minimal pitting edema around the ankles.
Laboratory results are as follows:
 ECG is shown in the exhibit.
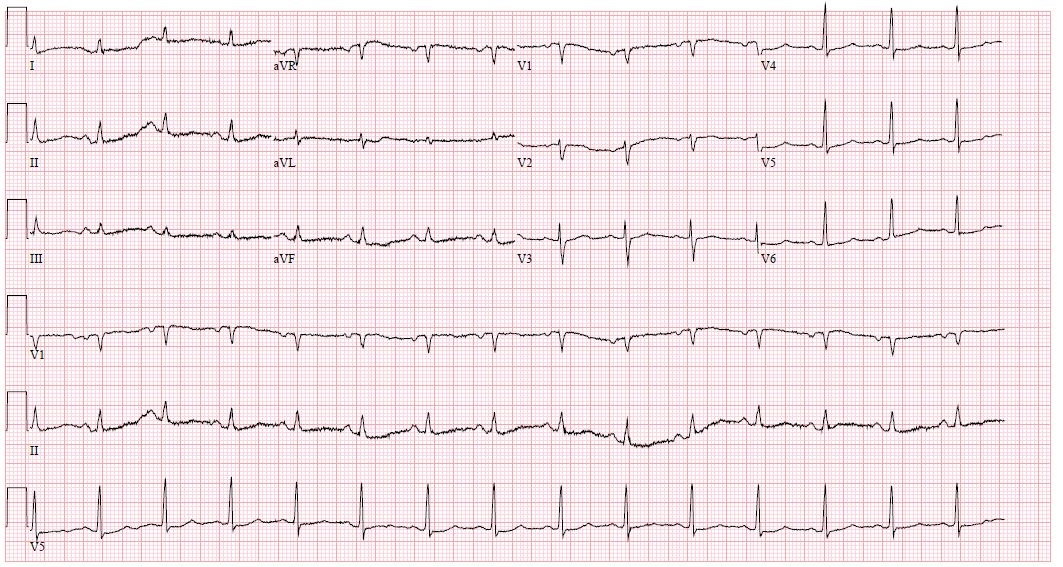 A recent echocardiogram showed a mildly dilated left ventricular cavity with akinesis of the anterior and anteroseptal walls as well as a left ventricular ejection fraction of 30%.
Which of the following additional treatments would most benefit this patient?
ECG is shown in the exhibit. A recent echocardiogram showed a mildly dilated left ventricular cavity with akinesis of the anterior and anteroseptal walls as well as a left ventricular ejection fraction of 30%.
Which of the following additional treatments would most benefit this patient? (Multiple Choice)
4.9/5 (93)
(93) A 63-year-old man comes to the office due to a month of right shoulder pain. The pain is nagging, extends down his medial right arm, and is especially bothersome at night. Over the past week, the patient has also felt a tingling numbness in his right fourth and fifth fingers. He does not know what caused the pain but recalls chopping wood a month ago. The patient also notes weight loss but cannot quantify the amount. He went to an urgent care clinic 2 weeks ago due to the shoulder pain and was prescribed naproxen, which has provided no significant relief. He believes he needs something "stronger" to cope with the pain.
Other medical problems include hypertension, chronic low back pain, and degenerative arthritis in the knees. He has a distant history of opioid abuse and completed a methadone program. The patient has a 40-pack-year smoking history and drinks 2 or 3 beers most weekends.
Vital signs are within normal limits. There is no lymphadenopathy or thyromegaly. The chest is clear to auscultation, and heart sounds are normal. Active and passive range of motion of the right shoulder is normal and elicits no pain. There is no shoulder deformity or right upper extremity muscle weakness or atrophy. Sensation to light touch is diminished in the right fourth and fifth fingers compared with the left.
Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.9/5 (75)
(75) A 28-year-old Asian woman comes to the physician to establish care. She has no specific complaints. Her past medical history is significant for menorrhagia treated successfully with medroxyprogesterone for 2 years and lactose intolerance. She was also previously advised to take iron supplements but developed constipation and abdominal cramping and stopped taking them.
Vital signs and physical examination are within normal limits.
Laboratory results are as follows:
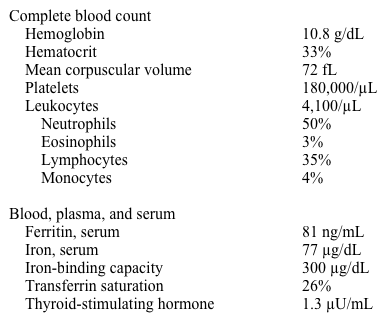 A hemoglobin electrophoresis shows hemoglobin A 98%, hemoglobin F 0%, and A2 2%.
Which of the following is the most likely diagnosis?
A hemoglobin electrophoresis shows hemoglobin A 98%, hemoglobin F 0%, and A2 2%.
Which of the following is the most likely diagnosis? (Multiple Choice)
4.9/5 (83)
(83) A 34-year-old woman comes to the physician with complaints of abdominal pain, bloating, and cramping for the past year. Her bowel movements fluctuate between constipation for several days and then 3-4 loose bowel movements in a single day. She often awakens at night with abdominal cramps followed by diarrhea and cannot fall back to sleep for hours. Her symptoms are significantly affecting her life, and she says that stress at work may be the cause. The symptoms are not exacerbated by any particular food and her appetite fluctuates. The patient does not have weight loss, blood in the stool, or a poor energy level. She has no medical problems and takes a daily multivitamin. She does not use tobacco, alcohol, or illicit drugs.
Her blood pressure is 100/52 mm Hg, pulse is 60/min, and respirations are 12/min. Her BMI is 22 kg/m2. Examination shows moist mucous membranes. The abdomen is nontender without hepatosplenomegaly. Rectal examination shows normal rectal tone and brown stool in the rectal vault that is guaiac negative.
Laboratory results are as follows:
 Which of the following is the most appropriate next step in management of this patient?
 (Multiple Choice)
4.8/5 (81)
(81) A 78-year-old woman comes to the physician accompanied by her daughter to establish primary care. The patient has just relocated to the area and moved in with her daughter. The daughter feels that her mother is no longer able to live independently and is concerned about some forgetfulness and falls that her mother has experienced. After the last fall she was seen in the local emergency department, had a normal head CT scan, and was discharged home. The patient relates a history of insomnia, depression, osteoporosis, osteoarthritis, chronic dizziness, hypertension, atrial fibrillation, "early" Alzheimer's, and urinary incontinence. She performs all her own activities of daily living but requires help with bathing. Her current medications include amitriptyline, warfarin, diphenhydramine at bedtime, meclizine, oxybutynin, calcium, vitamin D, alendronate, and lisinopril.
On examination, she is a well-dressed, pleasant, frail-looking elderly woman in no distress. Her blood pressure is 140/90 mm Hg and pulse is 84/min and irregular. Her lungs are clear on auscultation. The abdomen is soft and non-tender. Her gait is slow but normal. There are no focal defects on neurological examination. Her score on a Mini-Mental State Exam is 25/30.
She brings with her a print-out of a recent INR (2.6) performed by her previous primary care provider.
Which of the following is the best next step in managing this patient?
(Multiple Choice)
4.9/5 (71)
(71) A 56-year-old man comes to the physician with progressive shortness of breath over the past 4 months. He gets significantly short of breath after walking 2-3 blocks. He does not use tobacco.
On examination, blood pressure is 144/90 mm Hg, heart rate is 84/min, respirations are 16/min, and pulse oximetry is 91% on room air. Neck veins are flat in the sitting position. The skin of the fingers and hands appears thickened with a few ulcerations at the fingertips. Fine bibasilar crackles are heard on chest examination. There is no peripheral edema.
Chest x-ray reveals bilateral interstitial markings, most prominent at the bases.
Which of the following is most likely to be seen on pulmonary function testing?
FEV1 = Forced expiratory volume in 1 second; FVC = Forced vital capacity; DLCO = Diffusing capacity for carbon monoxide
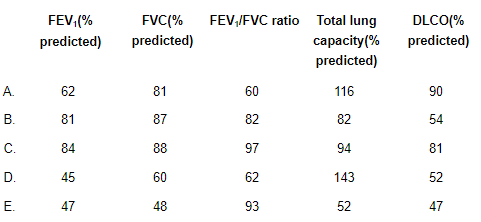
(Multiple Choice)
4.9/5 (70)
(70) A 55-year-old man comes to the office due to fatigue and inability to maintain satisfactory erections during intercourse. He has also noticed decreased early-morning erections and sexual desire. The patient has had no headaches, visual symptoms, polyuria, head injuries, or motor weakness. He has been trying to lose weight with diet and exercise. Medical history is notable for prediabetes, hypertension, and hypertriglyceridemia, and current medications include lisinopril, atorvastatin, and aspirin. The patient's father had type 2 diabetes mellitus and died of sudden cardiac arrest at age 74; his sister has hypothyroidism. He lives with his wife and 20-year-old son.
Blood pressure is 142/74 mm Hg and pulse is 78/min. BMI is 38 kg/m2. Body and facial hair distribution is normal. Visual fields are normal on confrontation. Testes are normal in size but have a soft consistency. The remainder of the physical examination is normal.
Laboratory results are as follows:
 Which of the following is the best next step in evaluation of this patient's symptoms?
 (Multiple Choice)
4.8/5 (90)
(90) A 31-year-old woman recently diagnosed with mitral valve prolapse asks about complications of the disease.
Which of the following is the most important determinant of adverse cardiovascular events in this patient?
(Multiple Choice)
4.9/5 (77)
(77) A 55-year-old businessman comes to the physician seeking medical advice before a trip to Southeast Asia. During his last trip to Jamaica 6 months ago, he developed diarrhea and had to miss several important meetings. His past medical history is significant for hyperlipidemia, for which he takes rosuvastatin. He has no other medical problems and is otherwise healthy. He requests a medication in case he develops diarrhea during this trip.
Which of the following would be the most appropriate treatment?
(Multiple Choice)
4.8/5 (65)
(65) A 35-year-old woman comes to the office due to abdominal bloating and increased flatulence over the past 2 months. She works in a bank and says her job is very stressful and the flatulence has caused her embarrassment. The patient also reports bulky, loose stools and watery diarrhea 3 or 4 times a week. She has had no abdominal pain, blood in the stool, or melena. The patient lost 45 kg (100 lb) after undergoing Roux-en-Y gastric bypass surgery 3 years ago, but her weight has been stable over the past year. Other medical issues include type 2 diabetes mellitus and chronic anxiety. Current medications include metformin, sertraline, and multivitamin and mineral supplements. The patient does not use tobacco, alcohol, or illicit drugs.
Blood pressure is 134/67 mm Hg and pulse is 72/min. BMI is 36 kg/m2. On physical examination, the abdomen is soft and nontender. Stool testing is negative for occult blood.
Laboratory results are as follows:
 Which of the following is the most likely cause of this patient's gastrointestinal symptoms?
 (Multiple Choice)
4.9/5 (85)
(85) A 66-year-old woman comes to the physician because of progressively worsening hip pain over the last several weeks. The pain is localized to the lateral aspect of her left hip over the outer thigh, but sometimes extends to her left buttock and knee. Her pain increases when she climbs stairs, gets out of the car, and stands up from sitting in a deep chair. She also notes that the pain sometimes occurs with walking or prolonged standing. On occasion, the pain awakens her from sleep when she rolls onto her left side.
She denies fever, chills, or constitutional symptoms. She cannot recall any trauma to the area and has had no falls. Her medical problems include obesity (BMI 30 kg/m2), type 2 diabetes mellitus, hypertension, hyperlipidemia, chronic low back pain, and depression.
Which of the following is the most likely cause of this patient's current complaints?
(Multiple Choice)
4.8/5 (68)
(68) A 23-year-old woman with a 4-year history of ileo-colonic Crohn's disease comes to the physician complaining of gas and a feculent vaginal discharge for the past 2 weeks. She has no fever, chills, abdominal pain, nausea, or vomiting. She has been treated with azathioprine for her Crohn's disease without any recent flares. Her medications include vitamin D and vitamin B12 supplements.
Her blood pressure is 100/60 mm Hg, pulse is 72/min, and respirations are 14/min. Examination shows a soft and nontender abdomen without hepatosplenomegaly. Rectal examination is within normal limits. Pelvic examination is unremarkable.
Laboratory results are as follows:
 Magnetic resonance imaging of the pelvis shows a fistulous tract from the rectum through the vaginal wall with surrounding wall edema.
Which of the following is the most appropriate next step in management?
Magnetic resonance imaging of the pelvis shows a fistulous tract from the rectum through the vaginal wall with surrounding wall edema.
Which of the following is the most appropriate next step in management? (Multiple Choice)
4.8/5 (80)
(80) A 42-year-old man complains of skin lesions on his legs for the last 6 weeks. He has become concerned because they are enlarging rapidly, are painful, and have started to drain pus. He has not had similar symptoms before. The patient has no trauma to the area, fevers, or night sweats. He takes analgesics for chronic low back pain and is on a lactose-free diet due to diarrhea. The patient tries to be compliant with his diet but still has crampy abdominal pain and frequent bowel movements, occasionally at night. He does not use intravenous drugs.
His vital signs are normal. Skin examination is shown in the photograph.
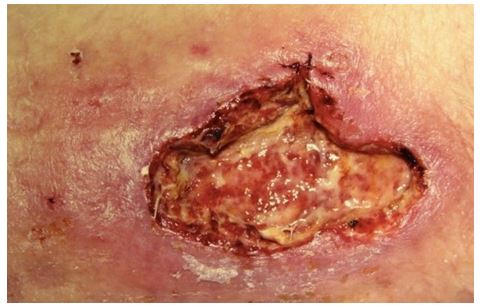 Laboratory analysis shows an elevated C-reactive protein and erythrocyte sedimentation rate. X-ray of both legs reveals no bony erosions or soft-tissue gas.
Which of the following is the most likely diagnosis?
Laboratory analysis shows an elevated C-reactive protein and erythrocyte sedimentation rate. X-ray of both legs reveals no bony erosions or soft-tissue gas.
Which of the following is the most likely diagnosis? (Multiple Choice)
4.9/5 (72)
(72) A 45-year-old man is evaluated for abnormal liver tests. The patient has had no nausea, vomiting, diarrhea, or weight loss. He has no significant medical problems, takes no medications, and has never been hospitalized or received blood transfusions. The patient consumes 1 or 2 beers during the week and, occasionally, 4 to 6 beers on the weekend. He does not smoke cigarettes or use illicit drugs. The patient works in a warehouse and is monogamous with his wife.
Vital signs are within normal limits. BMI is 30 kg/m2. There is no scleral icterus, lymphadenopathy, or rash. The abdomen is soft and nontender without hepatosplenomegaly. The remainder of the physical examination shows no abnormalities.
The most recent laboratory results are as follows:
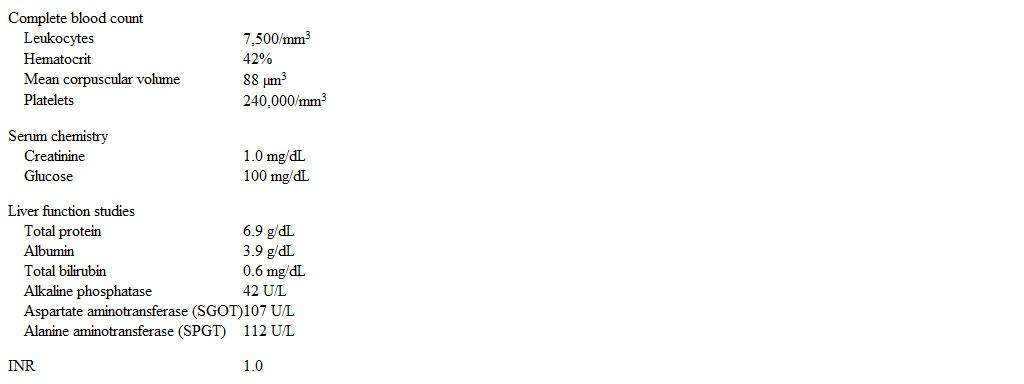 Repeat liver function testing shows similar results.
What is the most appropriate next step in management of this patient?
Repeat liver function testing shows similar results.
What is the most appropriate next step in management of this patient? (Multiple Choice)
4.9/5 (75)
(75) A 31-year-old man comes to the physician because of right testicular swelling for the past one week. He recalls trauma to the perineum and testes when he fell from a bike one month ago. He is otherwise healthy and has no other complaints. His past medical history is unremarkable. He admits to several unprotected sexual encounters in the past. He smokes marijuana occasionally but does not smoke tobacco. He denies any intravenous drug use.
On physical examination, a non-tender right testicular mass is palpated. Scrotal ultrasound shows a well-defined 2 x 1.5 cm hypoechoic lesion without cystic components in the right testis. His HIV test is negative. Serum alpha-fetoprotein and β-hCG levels are normal. CT scan of the abdomen and pelvis do not reveal any lymphadenopathy.
Which of the following is the best next step in managing this patient?
(Multiple Choice)
4.9/5 (71)
(71) A 46-year-old man is evaluated for decreased sexual performance and moderate fatigue over the last 2 years. He was diagnosed with sick sinus syndrome a year ago after an episode of syncope and received a permanent pacemaker. The patient takes no medications. He is married and has 2 children.
Vital signs and BMI are within normal limits. Physical examination shows mild testicular atrophy without gynecomastia.
Laboratory results are as follows:
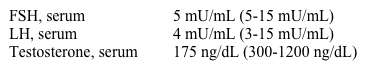 The patient should be evaluated specifically for which of the following conditions?
 (Multiple Choice)
4.8/5 (87)
(87) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)