



 Chat with AI
Exam 3: Office/Health Center

Exam 1: Emergency Department218 Questions
Exam 2: In-patient Facilities128 Questions
Exam 3: Office/Health Center900 Questions
Select questions type


A 35-year-old man comes to the office due to right knee pain over the last 2 weeks. The patient recently started running to lose weight and runs approximately 15 miles a week. He has since developed inner right knee pain, making it difficult to climb stairs. The pain is most intense at night when he is trying to fall asleep. Medical history is unremarkable, and he takes no medications. The patient does not use alcohol, tobacco, or illicit drugs.
The patient's temperature is 36.5 C (97.7 F), blood pressure is 120/70 mm Hg, and pulse is 75/min. His BMI is 31 kg/m2. There is no knee swelling. Localized tenderness is noted at the medial aspect of the right knee, 1 inch below the joint line. While stabilizing the right thigh, lateral movement of the lower right leg elicits no knee pain or medial joint space movement. His gait is normal. The remainder of the physical examination is within normal limits.
Which of the following is the most appropriate next step in management?
(Multiple Choice)
4.9/5  (87)
(87) A 22-year-old Hispanic woman comes to the office for evaluation of amenorrhea and excessive body hair. She reports a weight gain of 5.4 kg (12 lb) over the last 2 years. Menarche was at age 11, and her menstrual cycles are irregular and heavy with <6 cycles a year. The patient previously had menses following a 10-day treatment with medroxyprogesterone acetate. She has no other medical problems and takes no medications.
Blood pressure is 144/80 mm Hg and pulse is 70/min. BMI is 32 kg/m2. The patient has frontal balding with coarse terminal hair on the face, upper chest, lower abdomen, and back. There are no purple striae. Breast examination shows no galactorrhea, and the thyroid is not enlarged on palpation.
Complete blood count, TSH, FSH, prolactin, and serum chemistry tests are normal. Serum total testosterone is 105 ng/dL (normal: 20-60). Urine pregnancy test is negative.
Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (83)
(83) A 28-year-old woman is evaluated after a brief episode of syncope in the shopping mall. The patient walked into an overcrowded store where she felt hot and nauseated before passing out. She also had some palpitations. Her past medical history is significant for 2 prior episodes of syncope and a recent urinary tract infection. Electrocardiogram (ECG) is shown in this exhibit. 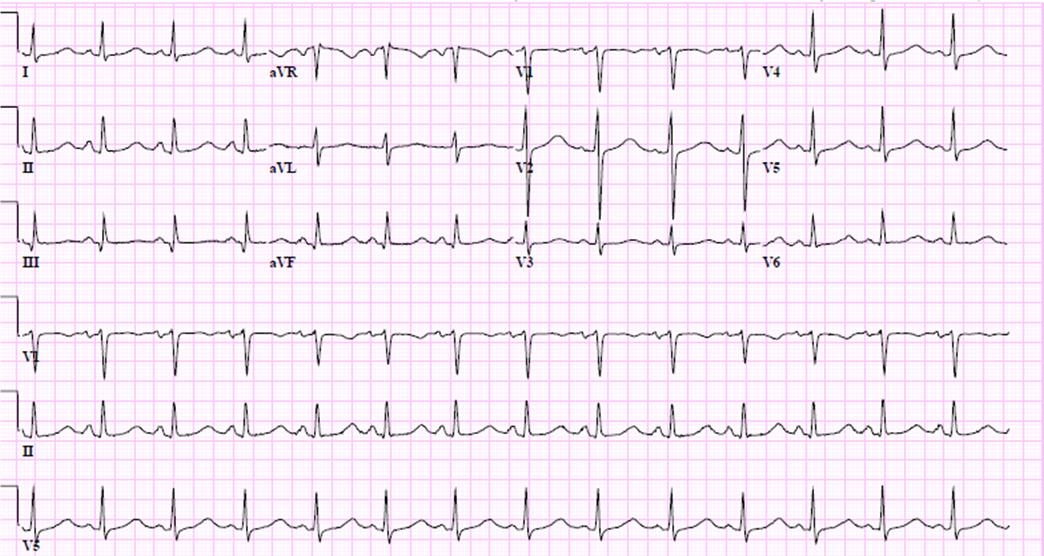 Which of the following medications should be avoided in this patient?
 (Multiple Choice)
5.0/5 (69)
(69) A 63-year-old man comes to the office for follow-up after a recent emergency department (ED) visit. The patient has had several months of mild shortness of breath and cough with clear sputum production. Ten days ago, he came to the ED due to worsening cough, shortness of breath, and wheezing. He was diagnosed with an acute exacerbation of chronic obstructive pulmonary disease and was prescribed inhaled bronchodilators, empiric antibiotics, and a 7-day course of oral prednisone. His respiratory symptoms have since improved. The patient has no other medical problems. Current medications are inhaled tiotropium and as-needed albuterol. He has smoked a pack of cigarettes daily for 34 years, but now smokes 5 or 6 cigarettes daily. The patient drinks alcohol occasionally and does not use illicit drugs.
Temperature is 36.7 C (98 F), blood pressure is 110/80 mm Hg, pulse is 78/min, and respirations are 16/min. Pulse oximetry shows 97% on room air. Examination reveals several discrete, firm, and nontender lymph nodes in cervical and axillary regions. The lungs are clear to auscultation but expiration is prolonged. Heart sounds are normal. The abdomen is soft and nontender. Liver edge is palpable 2 cm below the right costal margin, and mild splenomegaly is present.
Laboratory results are as follows:
 Leukocyte count at the time of his ED evaluation was 22,000/mm3.
Which of the following is the best next step in management of this patient's leukocytosis?
Leukocyte count at the time of his ED evaluation was 22,000/mm3.
Which of the following is the best next step in management of this patient's leukocytosis? (Multiple Choice)
4.8/5 (98)
(98) A 75-year-old woman comes to the physician for follow-up after she was started on prednisone 60 mg daily a week ago for suspected giant cell arteritis. She had headaches, blurred vision, fatigue, dry cough, and jaw pain with chewing. She had a normal complete blood count, comprehensive metabolic panel, and chest x-ray, but the erythrocyte sedimentation rate was 88 mm/hr. A biopsy of the right temporal artery was obtained due to tenderness over that area.
The patient had rapid relief on prednisone with resolution of headaches and significant improvement of her systemic symptoms. The biopsy report shows no evidence of giant cell arteritis, only atherosclerosis.
Which of the following is the best course of action?
(Multiple Choice)
4.8/5 (87)
(87) A 51-year-old woman comes to the office due to feeling "very fatigued and achy" for the past 2-3 months. She also has vague upper abdominal pain for which she has taken over-the-counter antacids without relief. The patient has no hemoptysis, chest pain, or weight loss. She has a 15-pack-year smoking history and quit 10 years ago. Her grandmother died of kidney cancer at age 65.
The patient's blood pressure is 142/90 mm Hg and pulse is 84/min. BMI is 34 kg/m2. The lungs are clear to auscultation. Neck examination is unremarkable. The abdomen is soft and nontender. Laboratory results are as follows:
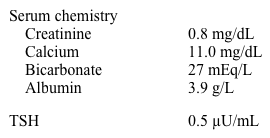 Chest x-ray is normal. Repeat serum calcium is 11.1 mg/dL. Parathyroid hormone is 85 pg/mL (10-65 pg/mL). 25-hydroxyvitamin D is 10 ng/mL (30-74 ng/mL).
Which of the following is the most likely cause of this patient's hypercalcemia?
Chest x-ray is normal. Repeat serum calcium is 11.1 mg/dL. Parathyroid hormone is 85 pg/mL (10-65 pg/mL). 25-hydroxyvitamin D is 10 ng/mL (30-74 ng/mL).
Which of the following is the most likely cause of this patient's hypercalcemia? (Multiple Choice)
4.9/5 (78)
(78) A 52-year-old woman comes to the clinic to follow up on her diabetes. She feels well, exercises 1 or 2 days a week for 20-30 minutes, and has a healthy diet. The patient's medical conditions include type 2 diabetes mellitus treated with metformin and hyperlipidemia treated with atorvastatin 20 mg daily. She has no chronic complications of diabetes. The patient drinks a glass of red wine 4 or 5 times a week to increase her "good cholesterol." Her weight has not changed in the past year. The patient has a 10-pack-year smoking history but quit when she was in her early 30s. Her father had a myocardial infarction at age 55 and died of congestive heart failure at age 64. He also had diabetes mellitus and hyperlipidemia and was a heavy smoker. Blood pressure is 116/70 mm Hg and pulse is 66/min. BMI is 26 kg/m2. The remainder of the physical examination is unremarkable.
Laboratory results are as follows:
 The patient's baseline LDL prior to starting atorvastatin therapy was 145 mg/dL, and her estimated 10-year risk of atherosclerotic cardiovascular disease is 3.1%. Which of the following is the most appropriate next step to address this patient's lipid abnormalities?
 (Multiple Choice)
4.8/5 (74)
(74) A 75-year-old man comes to the physician because of bilateral groin pain that is worse on the right side than the left. The pain is aggravated by any type of prolonged weight bearing. He feels particularly stiff in the hips in the mornings and after sitting in one place for a few hours. He was prescribed physical therapy and tramadol 4 months ago. After some temporary relief, he now feels more pain throughout the day, which limits his daily activities. He also received physical therapy last year, which provided only temporary relief. He denies any pain or swelling in his other joints or systemic symptoms. His daughter who accompanies him states that he had recently complained of dizziness.
His other medical problems include type 2 diabetes mellitus, hypercholesterolemia, peripheral vascular disease, and benign prostatic hyperplasia. The patient lives at home by himself. His medications include aspirin, metformin, glipizide, hydrochlorothiazide, lisinopril, acetaminophen, and tramadol.
His vital signs are within normal limits. Range of motion of the spine is normal and without pain. There is no scoliosis or excessive kyphosis. There is significant reduction in internal and external rotation at the hip joints accompanied by pain.
Complete blood count and basic metabolic panel are unremarkable. ESR is 15 mm/hr.
A radiograph of the right hip joint is shown here.
Which of the following is the most appropriate next step in this patient's management?
(Multiple Choice)
4.8/5 (82)
(82) A 65-year-old woman comes to the physician for mild pain, tingling, and numbness in her right hand. The symptoms started 2 weeks ago and are worse at night. She experiences neck pain occasionally but has no shooting or radiating pain. The patient has not had any recent head/neck trauma, headache, muscle weakness, or bowel/bladder incontinence. Her past medical history includes hypertension, hyperlipidemia, and cervical degenerative disk disease. The patient has a 30-pack-year smoking history. She is retired and knits frequently as a hobby.
Her blood pressure is 150/90 mm Hg and pulse is 88/min. Examination of the right hand reveals decreased sensation to pain and temperature along the ventral aspect of the first 3 digits and the radial half of the fourth digit. Sensation over the thenar eminence is preserved. There is no muscle weakness or atrophy.
Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.8/5 (85)
(85) A 47-year-old man comes to the office due to recurrent kidney stones. He passed his first stone 7 years ago and has subsequently passed 2 additional stones since then. Analysis of one of the stones revealed a stone content of 85% calcium oxalate and 15% calcium phosphate. His father and brother have both had kidney stones. His medical history is significant for gastroesophageal reflux disease, mild intermittent asthma, and psoriasis. He takes esomeprazole several times per week and uses an albuterol inhaler as needed for shortness of breath. He is allergic to sulfa medications. His blood pressure is 122/78 mm Hg and his pulse is 76/min. BMI is 27kg/m2.
The patient's blood work from 6 months ago is shown below.
 The patient's current laboratory studies reveal:
 Which of the following is the most appropriate recommendation for this patient?
The patient's current laboratory studies reveal:
Which of the following is the most appropriate recommendation for this patient? (Multiple Choice)
4.7/5 (84)
(84) A 68-year-old woman comes to the emergency room because of worsening dyspnea. The patient has severe chronic obstructive pulmonary disease, hypertension, and ischemic cardiomyopathy (left ventricular ejection fraction 35%).
Physical examination shows a thin woman in respiratory distress. Lung examination is notable for bronchial breath sounds at the left lung base. There is also dullness to percussion at the left lung base, with increased tactile fremitus. Bronchophony is present. Bilateral ankle edema is present.
Chest x-ray in this patient would most likely show?
(Multiple Choice)
4.9/5 (86)
(86) A 67-year-old man comes to the office for evaluation of bilateral leg swelling. The patient has had 3 months of swelling of the feet and ankles, which has progressively worsened to involve the legs, arms, and lower back. He also noticed shortness of breath 3 months ago while walking a few blocks, and his dyspnea now occurs after walking only a single block. Past medical history is significant for type 2 diabetes mellitus, mild peripheral neuropathy, and hypertension. His medications include metformin, lisinopril, and hydrochlorothiazide.
Blood pressure is 130/90 mm Hg, pulse is 72/min, and respirations are 14/min. There is no retinopathy. The patient has distended jugular neck veins to the angle of the jaw. Cardiac examination shows an S4 without murmurs. Pulmonary examination reveals bibasilar crackles but otherwise is clear to auscultation. Abdominal examination shows hepatomegaly without splenomegaly. He has 4+ pitting edema to the mid-thigh bilaterally.
Laboratory and ECG results are as follows:
 Which of the following is the most likely diagnosis?
 (Multiple Choice)
4.7/5 (81)
(81) A 50-year-old man comes to the physician with complaints of low-grade fever, malaise, and intermittent diarrhea. He experiences a burning sensation in his chest when he swallows food. He received a living related-donor kidney transplant 5 months ago. The donor and recipient were both cytomegalovirus immunoglobulin G antibody positive and Epstein-Barr virus antibody positive. Valganciclovir prophylaxis was given for 100 days. The patient experienced an acute cellular rejection 3 weeks ago that was diagnosed after kidney biopsy. He was treated with pulse methylprednisolone and a change from cyclosporine to tacrolimus. His rejection was successfully treated and his kidney function stabilized.
On examination, the patient is in no distress. His temperature is 38.1 C (100.5 F), blood pressure is 120/70 mm Hg, pulse is 90/min, and respirations are 16/min. Pulse oximetry is 97% on room air. Ocular fundi show no exudates or papilledema. The remainder of his physical examination is within normal limits.
Laboratory results are as follows:
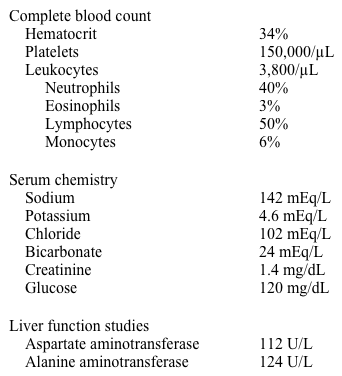 A chest x-ray is normal and unchanged from a pre-transplant film.
Which of the following is the most likely explanation for this patient's illness?
A chest x-ray is normal and unchanged from a pre-transplant film.
Which of the following is the most likely explanation for this patient's illness? (Multiple Choice)
4.9/5 (85)
(85) A 58-year-old man comes to the office due to progressive generalized weakness, leg swelling, and abdominal distension for the past several months. The patient also notes that his previously small umbilical hernia has recently enlarged, and he would like it repaired. He has no abdominal pain, hematemesis, or melena. His other medical conditions include type 2 diabetes mellitus, hypercholesterolemia, hypertension, obesity, and nonalcoholic steatohepatitis. He does not use tobacco, alcohol, or illicit drugs.
Blood pressure is 102/76 mm Hg, pulse is 74/min, and respirations are 16/min. The abdomen is moderately distended with fluid wave but nontender. There is a large, reducible, umbilical hernia with expansile cough impulse. There are no dilated superficial veins on the abdominal wall. Rectal examination reveals a normal-sized, nontender prostate gland and occult blood-negative brown stool. There is 2+ bilateral lower extremity pitting edema.
Laboratory results are as follows:
 Ultrasonography of the abdomen shows moderate ascites, splenomegaly, and a shrunken liver with no focal masses. Ascitic fluid analysis reveals a leukocyte count of 440/mm3 with 20% neutrophils, protein of 1.8 g/dL, and albumin of 1.2 g/dL. Ascitic fluid culture is pending.
In addition to dietary salt restriction and diuretic therapy, which of the following is the most appropriate next step in management of this patient?
Ultrasonography of the abdomen shows moderate ascites, splenomegaly, and a shrunken liver with no focal masses. Ascitic fluid analysis reveals a leukocyte count of 440/mm3 with 20% neutrophils, protein of 1.8 g/dL, and albumin of 1.2 g/dL. Ascitic fluid culture is pending.
In addition to dietary salt restriction and diuretic therapy, which of the following is the most appropriate next step in management of this patient? (Multiple Choice)
4.7/5 (76)
(76) A 34-year-old immigrant from Brazil comes to the physician with 2 months of palpitations accompanied by lightheadedness. He also complains of mild shortness of breath. The patient suffers from moderate, persistent asthma and takes daily inhaled glucocorticoid and salmeterol. He received "most of the childhood immunizations." He has no family history of heart disease or sudden cardiac death.
The patient's blood pressure is 122/70 mm Hg and pulse is 82/min. Estimated jugular venous pressure is normal. The apical impulse is displaced to the left. A soft 2/6 holosystolic murmur is heard at the apex. Lungs are clear on auscultation. There is no organomegaly, skin rash, or peripheral edema.
Electrocardiogram shows normal sinus rhythm with right bundle branch block. Echocardiogram shows a left ventricular apical aneurysm and left ventricular ejection fraction of 35%. Cardiac catheterization shows normal coronary arteries.
Which of the following is most likely responsible for this patient's condition?
(Multiple Choice)
4.8/5 (89)
(89) A 38-year-old woman comes to the office for chronic aching pain and stiffness all over her body for the last 6 months. Her symptoms are worse with exercise. She also has experienced fatigue, headaches, and insomnia. The patient tried water aerobic exercise 3 times a week but had no symptom improvement. She has a history of irritable bowel syndrome.
/_
/_Vital signs are within normal limits. Examination shows multiple tender spots over bony prominences. Her muscle strength is 5/5 in all extremities and deep-tendon reflexes are normal throughout. No sensory abnormalities are noted. There is no joint redness or swelling.
/_
/_Laboratory results are as follows:
 Which of the following is the most appropriate therapy for this patient?
 (Multiple Choice)
4.8/5 (73)
(73) A 40-year-old man seeks evaluation for edema. Two days ago, he had sudden onset of swelling in his legs. There was no associated warmth, redness, or tenderness. The patient had a mild cold a week ago and was taking over-the-counter cold remedies. He thought the swelling was an allergic reaction that would go away, but it has not. His past medical history is unremarkable. The patient does not use tobacco, alcohol, or illicit drugs. He takes no prescription or over-the-counter medications. There is no family history of kidney disease.
The patient's temperature is 36.7 C (98.1 F), blood pressure is 120/70 mm Hg, and pulse is 78/min. He has 3+ pitting edema to the mid-thigh bilaterally. Otherwise, his physical examination is unremarkable.
Laboratory results are as follows:
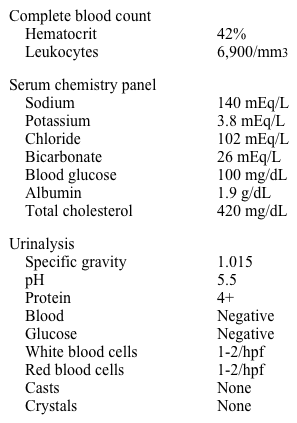 Which of the following diagnoses is most likely to be made with renal biopsy?
 (Multiple Choice)
4.8/5 (65)
(65) A 65-year-old man on chronic peritoneal dialysis (PD) for two years complains of 1 day of diffuse abdominal pain. He has not noticed any changes in his catheter exit site, changes in bowel movements, fever, or chills.
His temperature is 37.2 C (99.0 F), blood pressure is 140/90 mm Hg, and pulse is 90/min. Bowel sounds are normal. There is mild, diffuse abdominal tenderness without definite rebound tenderness. The catheter exit site looks normal.
Analysis of peritoneal fluid reveals a white blood cell count of 110 cells/µL. Gram stain of the peritoneal fluid is negative.
Laboratory results are as follows:
 Which of the following would be the most appropriate next step in management?
 (Multiple Choice)
4.9/5 (84)
(84) A 48-year-old woman comes to the clinic with her husband due to snoring. Her husband mentions that she snores sometimes and gets up to urinate 2 or 3 times during the night. The patient reports no daytime sleepiness, morning headaches, lack of concentration, or fatigue. She drinks a glass of wine every evening and does not smoke cigarettes. The patient works as a railroad operator, controlling the traffic of passenger trains through a large city. She last saw a physician 3 years ago and has no chronic medical conditions.
Blood pressure is 158/95 mm Hg, pulse is 76/min, and respirations are 14/min. BMI is 31 kg/m2. The nasal septum is midline. Examination shows a neck circumference of 17 inches. The lungs are clear to auscultation. There is no peripheral edema.
Complete blood count, serum chemistries, and TSH are within normal limits. ECG shows left ventricular hypertrophy.
The patient agrees to take antihypertensive medication. Which of the following is the most appropriate recommendation for addressing this patient's snoring?
(Multiple Choice)
4.9/5 (92)
(92) A 68-year-old African American man is evaluated for several weeks of progressive fatigue. His other complaints include abdominal discomfort, lower extremity edema, and chronic dry cough. He has not experienced fever, chills, or weight loss. He has a history of type 2 diabetes mellitus diagnosed 5 years ago, hypertension, and hyperlipidemia. Current medications include amlodipine, lisinopril, metformin, glyburide, and rosuvastatin.
His temperature is 37.1 C (98.8 F), blood pressure is 165/92 mm Hg, pulse is 84/min, and respirations are 16/min. Examination shows a 2/6 systolic ejection murmur along the left sternal border without radiation and 2+ pretibial edema bilaterally.
Laboratory results are as follows:
 Chest X-ray shows mild cardiomegaly and small bilateral pleural effusions.
Which of the following is the most likely diagnosis?
Chest X-ray shows mild cardiomegaly and small bilateral pleural effusions.
Which of the following is the most likely diagnosis? (Multiple Choice)
4.9/5 (92)
(92) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)