



 Chat with AI
Exam 3: Office/Health Center

Exam 1: Emergency Department218 Questions
Exam 2: In-patient Facilities128 Questions
Exam 3: Office/Health Center900 Questions
Select questions type


A 36-year-old man who just returned from a vacation in the Caribbean complains of an intensely pruritic skin rash. He spent a lot of time outdoors on the beach and applied sunscreen daily. He initially thought the rash was an allergic reaction, but it began expanding. The affected area is shown in the photograph.
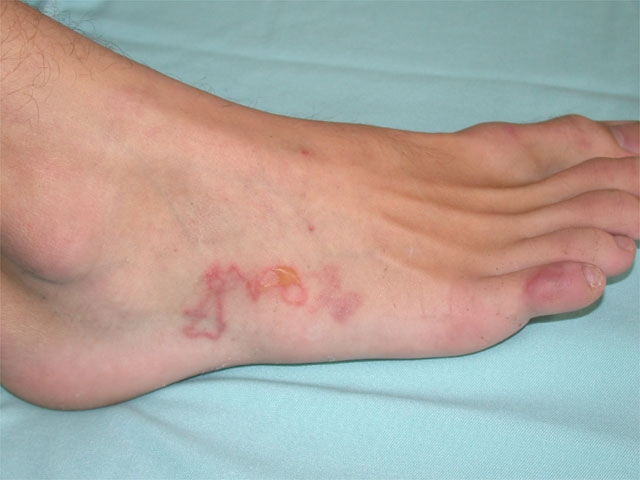 Which of the following is the most likely diagnosis?
A)Cutaneous leishmaniasis
B)Larva migrans
C)Mycetoma
D)Swimmer's itch
Which of the following is the most likely diagnosis?
A)Cutaneous leishmaniasis
B)Larva migrans
C)Mycetoma
D)Swimmer's itch (Not Answered)
This question doesn't have any answer yet
A 33-year-old man comes to the office due to persistent anal pain. Two months ago, the patient experienced severe anal pain associated with bowel movements. Evaluation revealed an anal fissure and external hemorrhoids for which he was treated with stool softeners and topical nitroglycerine. His symptoms have persisted despite adherence with the medical therapy and high-fiber diet. He reports no history of anal trauma or anal intercourse.
Vital signs are within normal limits. Rectal examination is painful and reveals a posterior midline anal fissure, large skin tag, and external hemorrhoids with no thrombosis. The remainder of the physical examination shows no abnormalities.
Blood cell counts and serum chemistry studies are within normal limits. Which of the following is the most appropriate next step in management of this patient's disorder?
(Multiple Choice)
4.9/5  (85)
(85) A 29-year-old man comes to the office due to a 2-month history of a worsening nonpruritic skin rash. The patient also has had pain and stiffness of his hands for the past several days. He has no known medical issues and takes no medications.
Vital signs are within normal limits. Mild swelling and tenderness are present in several digits of both hands. Skin examination shows extensive scaly and erythematous plaques on the scalp, hands, arms, torso, and legs, as shown in the images.
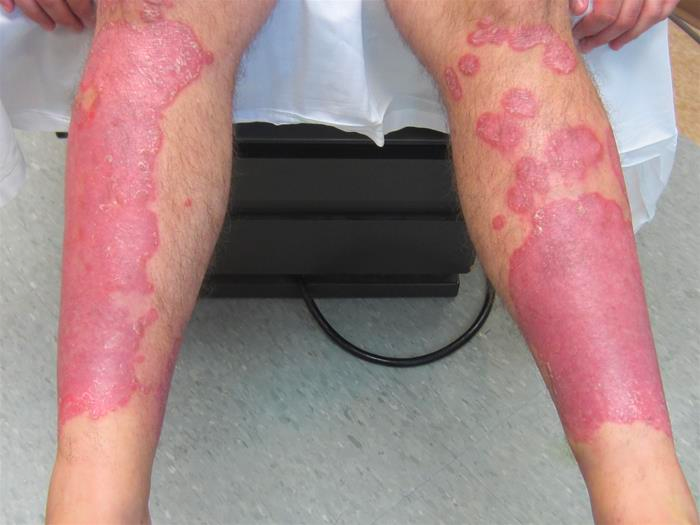
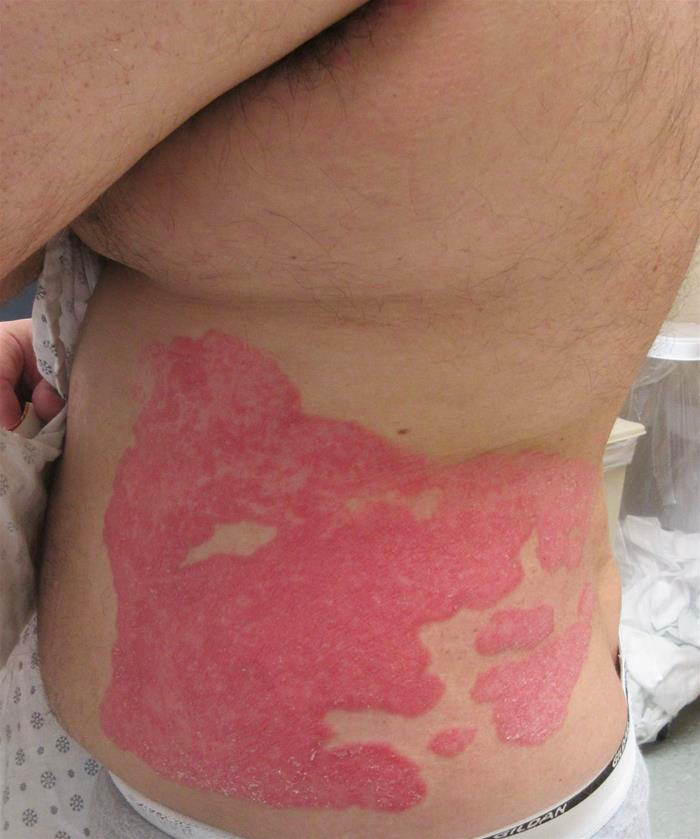 Which of the following diagnostic studies is most appropriate in evaluation of this patient?
 (Multiple Choice)
4.9/5 (89)
(89) An 84-year-old woman comes to the office to follow up on multiple chronic medical conditions. She has intermittent dizziness and has recently fallen twice, although she was not injured. During the most recent episode, the patient was standing in the living room when she felt lightheaded and slipped backward onto a chair. She did not lose consciousness or experience involuntary movements. Medical history is notable for hypertension, type 2 diabetes mellitus, severe osteoporosis, coronary artery disease, and chronic renal disease. Current medications include hydrochlorothiazide, low-dose metformin, vitamin D, and metoprolol, and she has taken alendronate for the past 4 years.
Supine blood pressure is 129/75 mm Hg, pulse is 66/min, and respirations are 16/min. Physical examination shows a grade 2/6 midsystolic murmur at the right second intercostal area, moderately severe thoracic kyphosis, and decreased pulses bilaterally in the feet. The remainder of the examination is normal.
Laboratory results are as follows:
 Complete blood count is within normal limits.
Which of the following is the most appropriate next step in management of this patient?
Complete blood count is within normal limits.
Which of the following is the most appropriate next step in management of this patient? (Multiple Choice)
4.8/5 (86)
(86) A 41-year-old man comes to the office for follow-up after a recent upper gastrointestinal endoscopy and small-bowel biopsy for suspected celiac disease. He initially presented 6 weeks ago with diarrhea and weight loss. The patient has followed a gluten-free diet since then and has noticed significant improvement in his bowel symptoms. He has no other medical problems and has started taking a multivitamin daily. The patient does not use tobacco, alcohol, or illicit drugs.
Vital signs are normal, and examination shows no abnormalities.
Laboratory results today show hemoglobin of 12.8 g/dL (11.0 g/dL 6 weeks ago) and mean corpuscular volume of 88 µm3. Small-bowel biopsy results are consistent with celiac disease.
Which of the following additional interventions is needed at this time?
(Multiple Choice)
4.9/5 (71)
(71) A 68-year-old man comes to the physician because of increased urinary frequency and nocturia. He has not increased his daily oral fluid intake. He has no dysuria, hematuria, penile discharge, or difficulty urinating. His other medical problems include recently diagnosed hypertension and osteoarthritis of his knees.
His temperature is 36.7 C (98 F), blood pressure is 130/82 mm Hg, and pulse is 80/min. Cardiopulmonary examination is normal. There is no jugular venous distention or peripheral edema. The abdomen is soft and without suprapubic tenderness. The prostate gland is normal in size, has no distinct nodules, and is nontender.
Which of the following is the most appropriate next step in management?
(Multiple Choice)
4.8/5 (85)
(85) A 67-year-old woman comes to the office after a recent hospitalization. She had abrupt onset of right arm weakness and difficulty speaking a week ago while playing cards with friends. The patient's friends called 911, but her symptoms had resolved completely by the time she arrived at the hospital.
MRI of the brain showed no acute abnormalities. A carotid ultrasound showed 60% stenosis in the left internal carotid artery and 50% stenosis in the right internal carotid artery. ECG showed normal sinus rhythm with occasional atrial premature beats, and 48 hours of telemetry monitoring was unrevealing. Echocardiogram showed mild left atrial enlargement, mild left ventricular hypertrophy, and normal left ventricular systolic function.
Since discharge, the patient has had no recurrence of symptoms and has been able to resume her normal daily activities. Her other medical problems include hypertension and hyperlipidemia. She has no history of angina or coronary artery disease. Medications include lisinopril, metoprolol, amlodipine, and aspirin.
Temperature is 36.7 C (98 F), blood pressure is 125/70 mm Hg, and pulse is 78/min; BMI is 26 kg/m2. Estimated jugular venous pressure is 8 cm H2O. There is normal S1 and S2 with a 2/6 ejection-type murmur at the right upper sternal border. Peripheral pulses are 2+ and no edema is present. The cranial nerves are intact and deep-tendon reflexes are normal. Muscle strength is symmetrically intact.
Laboratory results are as follows:
 Which of the following would be the most appropriate next step to prevent future neurovascular events in this patient?
 (Multiple Choice)
4.7/5 (82)
(82) A 60-year-old man with long-standing type 2 diabetes mellitus comes to the physician due to progressive weakness. Six months ago he started experiencing tingling and numbness in his feet. A few weeks later he experienced similar symptoms in his hands. Over the last 2 months he has been having increasing difficulty rising from a chair, going up stairs, and lifting objects. He does not have slurred speech, difficulty breathing, changes in vision, bowel or bladder dysfunction, or back pain.
His neurological examination reveals symmetric, proximal and distal, and upper and lower extremity muscle weakness associated with atrophy. He has reduced vibration, proprioception, and pinprick sensation that is worse in the legs compared to his arms. His reflexes are diminished in the upper extremities and absent in the lower extremities. Plantar responses are flexor bilaterally.
Which of the following is the most likely diagnosis?
(Multiple Choice)
4.8/5 (77)
(77) A 26-year-old man comes to the office due to back pain. He hurt his back while lifting a heavy box and now has discomfort while working on his computer. He proceeds to give an overly detailed analysis of the mechanics of his chair in relation to the height of his desk and computer screen. The patient has no medical problems and takes no medication. He lives alone and has a computer data entry job that allows him to work remotely. He prefers working from home because he does not enjoy socializing. The patient says, "I don't really get people's sense of humor, and I think they might be laughing at me. I also prefer to eat at home so I can follow my routines and keep the food separated on my plate." The patient does not use alcohol, tobacco, or illicit drugs. He has no psychiatric history but recalls that his mother once had him evaluated in grade school due to concern about his development.
Physical examination is unremarkable. On mental status examination, the patient makes poor eye contact and appears anxious and uncomfortable. He declines to put on a paper gown because he dislikes the feel of the paper against his skin. He answers questions appropriately in a stilted and monotone voice. He does not feel sad and has no hallucinations or delusions.
Which of the following is the most likely explanation for the patient's behavior?
(Multiple Choice)
5.0/5 (83)
(83) A 72-year-old woman with moderate dementia is brought to the physician by her son for weight loss and poor appetite over the last 4-5 months. She eats small amounts and often refuses to eat due to abdominal cramping and back pain after meals. She has no vomiting but does have constipation. The patient has lost 7 kg (15 lb) during this period. Computed tomography scan of the abdomen 1 month ago showed no masses. Her past medical history is also significant for coronary artery disease requiring bypass graft 10 years ago, congestive heart failure, lacunar stroke, and hypertension. Her medications include metoprolol, lisinopril, aspirin, simvastatin, and donepezil. She is an ex-smoker with a 40-pack-year history. She needs assistance with most activities of daily living.
The patient's blood pressure is 114/62 mm Hg, pulse is 68/min, and respirations are 14/min. She appears well groomed and answers questions appropriately. Cardiac examination shows a right carotid bruit. Lungs are clear to auscultation bilaterally. The abdomen is soft with mild diffuse tenderness to palpation. Rectal examination shows guaiac-negative brown stool. There is trace bilateral pedal edema. The remainder of the examination is within normal limits.
Laboratory results are as follows:
 Upper gastrointestinal endoscopy and colonoscopy show mild esophagitis and sigmoid diverticulosis.
Which of the following is the most appropriate next step in management of this patient?
Upper gastrointestinal endoscopy and colonoscopy show mild esophagitis and sigmoid diverticulosis.
Which of the following is the most appropriate next step in management of this patient? (Multiple Choice)
4.9/5 (74)
(74) A 67-year-old man with known coronary artery disease complains of exertional chest pain that limits his daily activities. He has long-standing angina symptoms. The patient reports that over the last month his exercise tolerance has decreased significantly and he has chest pain after walking only half a block. He takes sublingual nitroglycerin 6-7 times a day. Seven years ago he had coronary artery bypass surgery due to severe multivessel coronary artery disease with 3 venous grafts and left internal mammary artery graft to the left anterior descending artery.
Since then, he has had 2 cardiac catheterizations; the last showed occlusion of venous grafts and progressive native coronary artery disease not amenable to revascularization. His last left ventricular ejection fraction was 45%. The patient's medications include aspirin, lisinopril, atorvastatin, amlodipine, metoprolol, and nitroglycerin as needed. Two months ago, he was started on isosorbide dinitrate that he currently takes 4 times daily.
His blood pressure is 122/70 mm Hg and pulse is 55/min. No murmurs are heard on cardiac auscultation. Peripheral pulses are 2+ bilaterally. The remainder of the examination is within normal limits.
Which of the following most likely contributes to this patient's current symptoms?
(Multiple Choice)
4.8/5 (63)
(63) A 64-year-old man comes to the office due to frequent urination. He has a history of benign prostatic hyperplasia with mild hesitancy and occasional nocturia. During the past 8 weeks, he has been bothered by 2 or 3 episodes of nocturia each night and increased urinary urgency. The patient has no dysuria or hematuria and says that his daytime urinary frequency is unchanged. He also has shortness of breath with exertion. His medical history includes hypertension, hypercholesterolemia, and non-ischemic cardiomyopathy with a left ventricular ejection fraction of 40% on an echocardiogram a year ago. The patient's medications include furosemide, carvedilol, lisinopril, spironolactone, and atorvastatin.
Blood pressure is 140/80 mm Hg, pulse is 76/min, and respirations are 16/min. Pulmonary examination reveals bilateral basal crackles. Rectal examination shows a diffusely enlarged prostate. He has 2+ pitting edema of the bilateral lower extremities.
Serum sodium is 133 mEq/L, potassium is 3.9 mEq/L, and creatinine is 1.1 mg/dL. Urinalysis is normal.
Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.9/5 (84)
(84) A 40-year-old man with end-stage renal disease comes to the office for routine follow-up. He has been on chronic hemodialysis for the last 3 years. The patient's parathyroid hormone and alkaline phosphatase levels have increased progressively despite efforts to maintain normal serum phosphorus with phosphate binders and oral vitamin D.
Laboratory results are as follows:
 Adding cinacalcet to this patient's regimen would most likely contribute to which of the following?
 (Multiple Choice)
4.9/5 (80)
(80) A 48-year-old man comes to the office to discuss weight loss. For the past 6 months, he and his wife have been following a low-fat diet and exercising regularly. However, the patient has not achieved satisfactory weight loss. Medical history is unremarkable, but family history is notable for cardiovascular disease in both parents. The patient quit smoking 13 years ago and has a 10-pack-year history; he drinks alcohol only on social occasions.
Blood pressure is 133/86 mm Hg and pulse is 78/min. BMI is 29 kg/m2. The patient appears moderately overweight but comfortable. Physical examination is otherwise normal.
Laboratory results show fasting blood glucose 105 mg/dL, total cholesterol 210 mg/dL, HDL cholesterol 40 mg/dL, and triglycerides 185 mg/dL.
The patient indicates that he and his wife intend to start a very low-carbohydrate diet. Compared to his current program, which of the following is this patient most likely to experience after changing his diet?
(Multiple Choice)
4.7/5 (85)
(85) An 86-year-old woman is evaluated in the office for a 2-month history of lightheadedness with episodes of near-syncope and imbalance that last for seconds. She has had no syncope or falls. The patient lives in a personal care home and performs most of her daily activities with some assistance. Her medical problems include mild Alzheimer dementia, hypertension, coronary artery disease with coronary artery bypass grafting, and mitral valve repair 10 years ago. Her medications include aspirin, quinapril, amlodipine, simvastatin, and donepezil.
Her blood pressure is 162/82 mm Hg supine and 155/85 mm Hg standing. Her pulse is 50/min. Pulse oximetry is 96% on room air. She is alert and oriented to time and place. Cardiac examination shows a II/VI holosystolic murmur present at the apex. There are no carotid bruits. Lungs are clear to auscultation.
ECG shows sinus bradycardia and QRS complex duration of 98 msec.
Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (73)
(73) A 34-year-old man comes to the physician with lesions on his face, scalp, and neck. He has had the lesions for 1 year and they are slowly growing in size and number. There is mild pruritus that worsens with exposure to sunlight. The patient has no fever, arthralgias, or myalgias. He has no other medical problems and takes no medications.
The neck lesion is shown in the photograph below.
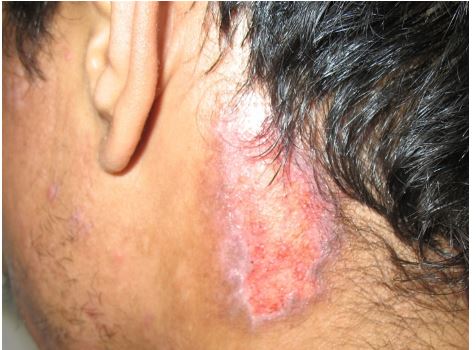 Lesions on the face and scalp have a similar appearance. The scalp lesion has hair loss.
Which of the following is the most likely diagnosis?
Lesions on the face and scalp have a similar appearance. The scalp lesion has hair loss.
Which of the following is the most likely diagnosis? (Multiple Choice)
4.9/5 (67)
(67) A 32-year-old man comes to the office due to malaise and fatigue over the last 3 months. The patient also reports mild generalized abdominal discomfort and nausea. He has lost approximately 2.3 kg (5 lb) in the last month. The patient has had no fever, vomiting, diarrhea, back pain, or urinary symptoms. He has no medical issues and takes no medication. The patient is a lifetime nonsmoker. Family history is notable for liver cancer in his father.
Physical examination shows right upper quadrant tenderness. The liver edge is soft and palpable 2 cm below the right costal margin. Rectal examination shows no abnormalities, and a stool occult blood test is negative.
Laboratory results are as follows:
 A hepatitis panel shows immunity against the hepatitis B virus. Ultrasonography shows no gallstones and no common bile duct dilation. Liver biopsy reveals intrahepatic ductal obliteration with moderate lymphocytic infiltration and periductal "onion skin" fibrosis.
Which of the following is the best next step in management of this patient?
A hepatitis panel shows immunity against the hepatitis B virus. Ultrasonography shows no gallstones and no common bile duct dilation. Liver biopsy reveals intrahepatic ductal obliteration with moderate lymphocytic infiltration and periductal "onion skin" fibrosis.
Which of the following is the best next step in management of this patient? (Multiple Choice)
4.9/5 (78)
(78) A 66-year-old man comes to the office due to shortness of breath and cough. Three years ago, he was diagnosed with chronic obstructive pulmonary disease and as needed inhaled albuterol was started. Over the past few months, he has been having worsening shortness of breath and has been using his inhaler more frequently. The patient is an avid golfer and says he has had to stop to catch his breath when walking on the golf course. He has had no chest pain, orthopnea, or leg swelling. The patient has never required urgent medical care for his breathing. His other medical problems include hypertension and hyperlipidemia. The patient has smoked for 50 years and says he has now cut down to 5 cigarettes daily.
Blood pressure is 140/83 mm Hg, pulse is 77/min, and respirations are 16/min. Oxygen saturation on room air is 95% at rest and 90% after walking for several minutes. Lung auscultation reveals good air entry with occasional expiratory wheezes.
Pulmonary function testing shows FEV1 is 54% of predicted, FVC is 68% of predicted, and FEV1/FVC is 61%. Chest radiography reveals no lung infiltrates or masses.
In addition to recommending complete smoking cessation, which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.7/5 (78)
(78) An 80-year-old woman comes to the physician accompanied by her daughter, who is concerned because her mother no longer participates in group activities. The patient has lived in an apartment within an assisted-living facility for 12 months. She now no longer attends communal movie nights or bingo games, eats all her meals in her apartment, rarely watches her favorite television shows, and does not call her family and friends. She feels well and has not been depressed or fatigued. She says that she sometimes "forgets stuff" but is still able to function independently. She has not fallen in the past year.
The patient has osteoporosis, hypertension, osteoarthritis of her hips and knees, diet-controlled type 2 diabetes mellitus, and cataracts. Current medications include hydrochlorothiazide, alendronate, and calcium with vitamin D.
Her temperature is 37.0 C (98.6 F), blood pressure is 150/80 mm Hg, pulse is 84/min, and respirations are 16/min. BMI is 22 kg/m2. The patient is alert, attentive, pleasant, well-dressed, and well-groomed. Chest and abdominal examinations are unremarkable. There is no muscle weakness, her deep-tendon reflexes are normal, and her gait is steady. She scores 27/30 on a Mini-Mental State Examination. A geriatric depression scale screening test is negative.
Laboratory results are as follows:
 Which of the following is the most appropriate next step in management of this patient?
 (Multiple Choice)
4.9/5 (82)
(82) A 25-year-old immigrant from the Ukraine comes to the office because of exertional shortness of breath. He was an avid soccer player five years ago, but now describes fatigue and shortness of breath after brisk walking for 5-6 blocks. He denies any chest pain, palpitations, syncope, or lower extremity swelling. His weight has been stable. He takes no medications and has no allergies. He smokes 1 pack of cigarettes daily and drinks alcohol over the weekend. His grandfather died suddenly at the age of 34 years, but both his parents are in good health.
His blood pressure is 105/70 mm Hg in the right arm and 107/72 mm Hg in the left arm, and his pulse is 76/min. Cardiovascular examination reveals a normal apical impulse. There is a normal S1 with a fixed and wide split S2. There is no S3. He has a 2/6 mid-systolic murmur along the left upper sternal border. Femoral pulses are 2+ bilaterally and symmetrical. There is no peripheral edema.
The EKG shows normal sinus rhythm, right axis deviation, and incomplete right bundle branch block.
Which of the following is the most likely finding on transthoracic echocardiography?
(Multiple Choice)
4.8/5 (106)
(106) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)