



 Chat with AI
Exam 3: Office/Health Center

Exam 1: Emergency Department218 Questions
Exam 2: In-patient Facilities128 Questions
Exam 3: Office/Health Center900 Questions
Select questions type


A 46-year-old woman was instructed to follow up with her primary care physician after a recent emergency department visit for self-limited nausea and vomiting. The patient currently has no issues. Her medical history is notable for obesity, ulcerative colitis, essential hypertension, and gastroesophageal reflux disease. The patient's last ulcerative colitis flare was 5 years ago and was treated with a short course of corticosteroids. Colonoscopy with biopsy performed a year ago revealed mild inflammation with no dysplasia. Her medications include mesalamine, omeprazole, and lisinopril.
Blood pressure is 140/88 mm Hg, pulse is 84/min, and respirations are 14/min. BMI is 32 kg/m2. Cardiopulmonary examination is normal. The abdomen is soft and nontender. There is no hepatomegaly or splenomegaly.
Laboratory results from the patient's recent emergency department visit are as follows:
 Repeat testing shows similar results.
Which of the following would be the most helpful for establishing the diagnosis in this patient?
Repeat testing shows similar results.
Which of the following would be the most helpful for establishing the diagnosis in this patient? (Multiple Choice)
4.8/5  (79)
(79) A 22-year-old man comes to the office due to 6 months of exertional shortness of breath. He describes himself as nonathletic and has never engaged in competitive sports. The patient has recently experienced dyspnea on moderate exertion. He also describes a pounding sensation in his head at night. He does not use tobacco, alcohol, or illicit drugs.
Blood pressure is 150/65 mm Hg and pulse is 90/min. No jugular venous distension is present. There is no digital clubbing or cyanosis. The apical impulse is brisk and displaced to the left. A 2/6 continuous murmur is heard below the left clavicle. Upper and lower extremity pulses are prominent and equal. The lungs are clear on auscultation.
If untreated, this patient's risk for which of the following is most increased?
(Multiple Choice)
4.9/5 (87)
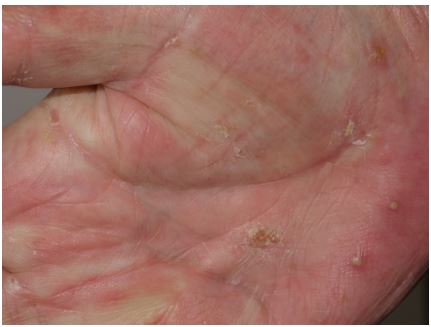
(87) A 25-year-old man comes to the physician with intense itching of his hands and wrists that prevents him from sleeping. The itching started about 1 week after he returned from a month-long stay in Europe. He had sexual contact with 2 paid sex workers while there. His itching involves predominantly the webs of his fingers and the flexor surfaces of his wrists. He has no other medical problems and takes no medications.
Vital signs are within normal limits. Examination of the skin shows the following:
 Rapid HIV and syphilis testing return negative.
What would be the most effective treatment for his current condition?
Rapid HIV and syphilis testing return negative.
What would be the most effective treatment for his current condition? (Multiple Choice)
4.9/5 (77)
(77) A 63-year-old woman comes to the office due to several months of bilateral leg pain, predominantly in her calves and thighs when she walks. After a block or two, she experiences numbness in both calves and thighs that progresses to pain and weakness with continued walking. The patient's symptoms worsen when she walks downhill, and the pain and numbness quickly subside with rest. Her symptoms often occur at the grocery store, but are relieved when she leans over a cart. She also has lower back pain. The patient has no bladder and/or bowel symptoms, chest pain, chest pressure, dyspnea, or edema.
The patient's medical problems include hypertension, gastroesophageal reflux disease, hyperlipidemia, and degenerative joint disease. She also has a history of coronary artery disease with stent placement in her right coronary artery 2 years ago. Her medications include atorvastatin, metoprolol, aspirin, clopidogrel, lisinopril, and omeprazole.
The patient's blood pressure is 130/80 mm Hg and pulse is 72/min. A bruit is heard over the right carotid artery. There are no abdominal or femoral bruits. Her femoral, popliteal, and dorsalis pedal pulses are normal and symmetric. There are no trophic changes of the skin or nails in the feet. Straight leg raising test is negative. The patient can walk on her heels and toes. There are no lower extremity sensory deficits. Lower extremity deep-tendon reflexes are 2+ and symmetric. Perineal sensation is normal.
Which of the following would establish the correct diagnosis?
(Multiple Choice)
4.9/5 (76)
(76) A 72-year-old man with a seven-year history of type 2 diabetes mellitus comes to the physician because of pain in his feet. He has had numbness and tingling in his feet up to his ankles for two years. He recently began experiencing burning pain in both feet that extends to the mid-calf. This discomfort keeps him awake at night. He has no associated weakness. He has tried capsaicin ointment without relief.
On examination, there is decreased sensation to light touch and pinprick involving both feet. Ankle jerk reflex is absent bilaterally. Muscle strength in both lower extremities is normal with normal pulses. The remainder of the examination is within normal limits.
Laboratory data reveals a normal complete blood count, TSH, protein electrophoresis, and vitamin B12 levels. His HbA1c is 7.5%.
Which of the following would be the best initial therapeutic option for this patient?
(Multiple Choice)
4.7/5 (91)
(91) A 58-year-old woman comes to the office for an annual health examination. She has a history of hypothyroidism, hypercholesterolemia, and depression. Medications include levothyroxine, simvastatin, and escitalopram. The patient reports feeling "tired and worn out" due to difficulty falling asleep and also awakening several times a night over the past several months. She reports no change in appetite, bowel habits, interest in activities, or concentration. The patient limits her caffeine intake to mornings and does not drink alcohol. She quit her job last year in order to care full-time for her mother, who has Alzheimer disease and lives with her. The patient says, "It's been difficult to see my mother decline, and I worry because she is increasingly confused and wanders at night. I feel badly, because I get irritable when I am tired and lose patience with her. I would like to keep Mom at home as long as possible, but it is difficult."
Vital signs and physical examination are unremarkable. TSH is within normal limits.
Which of the following is the most appropriate intervention for this patient?
(Multiple Choice)
4.9/5 (71)
(71) A 48-year-old woman comes to the office for a well-woman examination and a discussion about menopausal symptoms. She has experienced unpredictable and progressively worsening episodes of flushing, sweating, and anxiety that interfere with her occupational performance during the day and wake her from sleep at night. The patient has attempted to manage her symptoms by turning on the air conditioner in the winter and dressing in layers. Her menstrual cycles have become irregular, occurring every 28-50 days. The patient had a tubal ligation at age 40, and her postoperative course was complicated by lower extremity deep vein thrombosis. She does not use tobacco and does not have a personal history of breast cancer.
Blood pressure is 122/78 mm Hg, pulse is 72/min, and respirations are 17/min. The well-woman physical examination is unremarkable.
Which of the following is the most appropriate next step in management to reduce this patient's symptoms?
(Multiple Choice)
4.9/5 (82)
(82) A 42-year-old man comes to the physician with 4-6 weeks of occasional subjective fever, mild shortness of breath on exertion, intermittent cough, and right-sided chest pain. The patient was started on chlorthalidone for hypertension 4 months ago. He has smoked 2 packs of cigarettes daily for 15 years. The patient emigrated 14 years ago from Russia, where he used to work in construction and building demolition and did not wear a respirator mask at work. He has lived in Chicago since his arrival to the United States.
The patient's temperature is 37.3 C (99.1 F). Lung examination is significant for decreased breath sounds at the right base.
Chest x-ray reveals a small right-sided effusion with mild pleural thickening. A thoracentesis is performed.
 What is the most likely cause of the effusion?
 (Multiple Choice)
4.7/5 (84)
(84) A 47-year-old man comes to the physician complaining of fatigue. He reports low energy and has resorted to energy-boosting drinks to keep him going at work. His sex drive is not "as good as it used to be" when he was in his 30s. He is uncertain whether he gets early-morning spontaneous erections. He also has dull, bilateral, nonthrobbing headaches 3-4 times per month that he describes as a constriction band around his head. The patient denies peripheral vision loss, decreased shaving frequency, or testicular injury. He lives with his girlfriend and has a daughter from a previous relationship.
His other medical problems include hypertension and hyperlipidemia. His current medications are enalapril and atorvastatin. He does not use tobacco, alcohol, or illicit drugs.
His blood pressure is 130/70 mm Hg and pulse is 68/min. His BMI is 25 kg/m2. There is no gynecomastia, and body hair distribution is normal for his age. Digital rectal examination reveals normal prostate. Testes have a volume of 20 mL. The remainder of the physical examination is unremarkable.
Complete blood count, serum chemistries, and TSH levels are normal. Serum testosterone measured at 4 PM is 256 ng/dL (normal, 300-800 ng/dL).
Which of the following is the most appropriate next step in evaluating his low testosterone level?
(Multiple Choice)
4.8/5 (88)
(88) A 30-year-old woman comes to the physician for a follow-up evaluation after a recent hospitalization. She was admitted to the hospital two weeks ago with abdominal pain and bloody diarrhea, and she improved markedly with antibiotics and intravenous hydration. She was told to follow-up with her physician regarding abnormal laboratory results obtained during her hospitalization. She currently has no symptoms and denies prior chronic medical problems. She does not smoke or drink alcohol.
Examination shows no abnormalities.
Today's laboratory results are as follows:
 The laboratory studies at the time of hospital discharge showed similar results.
Which of the following is the most appropriate next step in management?
The laboratory studies at the time of hospital discharge showed similar results.
Which of the following is the most appropriate next step in management? (Multiple Choice)
4.8/5 (90)
(90) A 27-year-old woman comes to the physician because of poor sleep, hand tremors, and heat intolerance for the last 2-3 weeks. She denies fever or neck pain and she has no previous medical problems. She does not use tobacco or alcohol. She takes a multivitamin in addition to dietary supplements and she exercises daily. Her mother had Graves' disease and was treated with radioiodine. Her sister has hypothyroidism.
Her blood pressure is 150/80 mm Hg, pulse is 120/min, and respirations are 20/min. Her BMI is 23 kg/m2. Neck examination shows mild, diffuse thyroid enlargement without any palpable nodule, tenderness, or bruit. She has lid lag without exophthalmos. Her hands are warm and sweaty with fine tremors. The remainder of the examination is unremarkable.
Laboratory results are as follows:
 Electrocardiogram shows sinus tachycardia with a heart rate of 120/min with non-specific ST-T changes. Radioactive iodine uptake at 24 hours is 2% (normal 10-30%). Urine pregnancy test is negative.
Which of the following is the best next step in management?
Electrocardiogram shows sinus tachycardia with a heart rate of 120/min with non-specific ST-T changes. Radioactive iodine uptake at 24 hours is 2% (normal 10-30%). Urine pregnancy test is negative.
Which of the following is the best next step in management? (Multiple Choice)
4.9/5 (88)
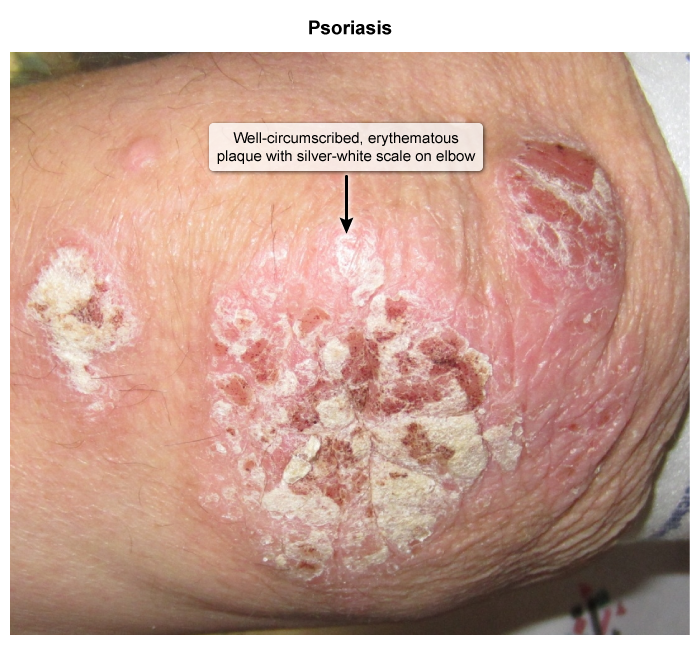
(88) A 57-year-old man comes to the physician for evaluation of a rash on his elbows and knees. He initially had the rash 3 years ago, and it reoccurs every 3-4 months in the same regions. The patient has no pruritus or discharge during the episodes but notices an occasional silvery scale.
Vital signs are within normal limits. Skin examination of the left elbow is shown below. There is no drainage from the lesions or tenderness to palpation.
 Which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.8/5 (87)
(87) A 24-year-old woman is being evaluated for positive reactive plasma reagin (RPR) testing for syphilis as part of a routine prenatal workup. The current titer is 1:8. She feels well and has no complaints. Six months ago, she went to the hospital with fever and a diffuse rash following sexual activity with a new male partner. There she underwent testing that showed an RPR titer of 1:256. The Treponema pallidum particle agglutination assay was positive at that time. HIV testing was negative. The patient was treated for secondary syphilis with intramuscular penicillin G. Her symptoms resolved over the next week. Her partner also was treated appropriately for syphilis at that time; she has had no new sexual partners.
Complete examination, including genital and neurologic examination, is normal. Repeat HIV antibody testing is negative.
What is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (86)
(86) A 52-year-old woman comes to the office due to "feeling hot all the time." She reports the sensation of heat starting in her upper body and spreading all over. She has had these symptoms for the past 10 months and is exhausted as they keep her awake most nights. Her last menstrual period was 8 months ago. The patient's other medical problems include hypothyroidism and gastroesophageal reflux disease, and her medications include levothyroxine and omeprazole. A mammogram performed last year was normal. She has had no surgeries; her family history is unremarkable. The patient does not use tobacco, alcohol, or illicit drugs.
Physical examination, including pelvic examination, is within normal limits. Laboratory findings, including TSH, are within normal limits.
Which of the following is the best therapy to relieve this patient's symptoms?
(Multiple Choice)
5.0/5 (72)
(72) A 43-year-old man comes to the office for follow-up 12 weeks after starting sertraline for major depressive disorder. The patient was initially started on sertraline 50 mg and started to improve when his dose was increased to 100 mg. He now feels that he is back to baseline and reports significant improvement in mood, sleep, appetite, and energy over the past several weeks. He is painting again and feels more optimistic. Despite these improvements, the patient is troubled by a 2-month history of erectile dysfunction that started shortly after sertraline was titrated up to 100 mg. He still sometimes wakes up with an erection. He is distressed by this sexual dysfunction and says that it is straining his relationship with his wife. The patient has no previous history of sexual dysfunction. Medical history includes hypertension, for which he takes lisinopril.
Blood pressure is 130/80 mm Hg and pulse is 72/min. Physical examination shows clear lung fields, normal S1 and S2, and intact bilateral dorsalis pedis pulses.
Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.8/5 (90)
(90) A 19-year-old college student comes to the physician with generalized weakness and diarrhea for the last year. She describes 8-10 watery bowel movements daily, including at night. She has abdominal cramps but no vomiting or blood or mucus in the stool. She drinks 8 cups of coffee daily but does not use tobacco, alcohol, or illicit drugs. She is currently applying for a merit scholarship and must be at the top of her class to qualify.
Her blood pressure is 92/54 mm Hg, pulse is 94/min, and respirations are 12/min. Her body mass index is 17 kg/m2. Examination shows no abnormalities.
Stool study results are as follows:
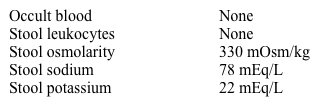 An esophagogastroduodenoscopy is unremarkable with normal duodenal biopsies.
Which of the following is the most likely diagnosis?
An esophagogastroduodenoscopy is unremarkable with normal duodenal biopsies.
Which of the following is the most likely diagnosis? (Multiple Choice)
4.8/5 (73)
(73) A 46-year-old man comes to the emergency department after awakening with dyspnea and diaphoresis this morning. He has had 6 weeks of fever, increased weakness, and fatigue. The patient underwent a root canal procedure 4 months ago but reports that he has been otherwise healthy. He has no history of cardiovascular disease, pulmonary disease, or cardiac surgery.
Temperature is 38.4 C (101.1 F), blood pressure is 144/76 mm Hg, pulse is 106/min, and respirations are 28/min. The patient is diaphoretic and appears uncomfortable. There are no skin rashes. The pupils are equal, round, and reactive without conjunctival lesions or suffusion. There is no neck stiffness or meningeal signs. A short, early diastolic murmur is heard at the left sternal border. Coarse inspiratory crackles are heard bilaterally halfway up the lung fields. The spleen is not palpable. His speech is abnormal.
Chest x-ray reveals pulmonary congestion. Transthoracic echocardiogram shows a 7-mm, mobile echodensity on the aortic valve with high-grade aortic regurgitation. MRI of the brain reveals a small area of acute infarction in the left frontal lobe.
Blood cultures are obtained and empiric antibiotics are initiated. Noninvasive positive-pressure ventilation is started with some improvement in respiratory distress.
Which of the following is an indication for cardiac valve surgery in this patient?
(Multiple Choice)
4.8/5 (80)
(80) A 66-year-old man comes to the hospital due to 2 days of fever, chills, fatigue, and malaise. He has had no chest pain, cough, diarrhea, or dysuria. The patient has a history of lymphoma and underwent a splenectomy 6 years ago. Prior to the splenectomy, he received vaccinations against Neisseria meningitidis and Streptococcus pneumoniae. Six months ago, the patient returned from a 2-week trip to India during which he did not take antimalarial prophylaxis. He has no known ill contacts. The patient lives in Massachusetts and is a professor at a local college.
Temperature is 38.6 C (101.5 F), blood pressure is 122/70 mm Hg, and pulse is 110/min and regular. The patient has mild respiratory distress. The oropharynx is dry without lesions. Lung examination reveals bilateral coarse crackles. The abdomen is soft and mildly tender throughout. He has no skin rash.
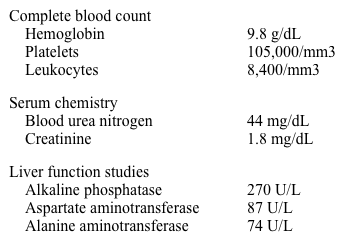
Laboratory results are as follows:
 A chest x-ray reveals diffuse bilateral infiltrates. A peripheral blood smear shows intraerythrocytic inclusions (see exhibit).
Which of the following is the most likely organism causing this patient's illness?
A chest x-ray reveals diffuse bilateral infiltrates. A peripheral blood smear shows intraerythrocytic inclusions (see exhibit).
Which of the following is the most likely organism causing this patient's illness? (Multiple Choice)
4.8/5 (90)
(90) An 84-year-old woman comes to the office for evaluation of bleeding. The patient first noticed small amounts of blood on her underwear 2 weeks ago. She has been wearing pads that require changing once or twice a day with only a small amount of blood accumulating between changes. Her last Pap test at age 64 was normal. A small, hyperplastic rectal polyp was removed at age 80. Vital signs are normal. BMI is 38 kg/m2. The speculum is difficult to insert; on examination there is mucosal pallor throughout the vagina with epithelial thinning and dryness. No mass or prolapse is visualized. Fecal occult blood test is negative.
Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (91)
(91) A 63-year-old woman comes to the office due to pain during sexual intercourse. The patient had been abstinent since the death of her husband 10 years ago and attempted intercourse recently with a new partner. Although she uses lubrication, the patient has been unable to have intercourse due to severe pain on penetration. She also had several days of post-coital spotting and mild vaginal pruritus that have resolved.
Menopause was at age 57. Since then, the patient occasionally has had small amounts of thin, malodorous vaginal discharge. She does not use scented soaps, deodorants, or douches. She is worried that her inability to have intercourse might interfere with her relationship. The patient has a history of mild hypertension and takes lisinopril.
Blood pressure is 138/84 mm Hg and pulse is 82/min. Examination of the external genitalia shows scant pubic hair; pale, thin skin; and recession of the labia minora. The introitus is narrow, small, and barely permits 2 fingers to be inserted; the vaginal mucosa is pale, smooth, dry, and slightly friable.
Vaginal pH is 6. Wet mount microscopy shows a few inflammatory cells, no clue cells, and no trichomonads.
Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (82)
(82) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)