



 Chat with AI
Exam 3: Office/Health Center

Exam 1: Emergency Department218 Questions
Exam 2: In-patient Facilities128 Questions
Exam 3: Office/Health Center900 Questions
Select questions type


A 62-year-old woman undergoing chemotherapy through a subcutaneous port for locally advanced breast cancer comes to the physician with fever and malaise. She has no other symptoms.
There are no skin lesions on physical examination and cardiac examination is normal. The patient's abdomen is soft and nontender to palpation. She has a subcutaneous port in the left chest and there is no erythema, warmth, tenderness, or drainage at the catheter exit site.
Blood cultures grow yeast within 36 hours that is later identified as Candida albicans. Antifungal therapy is initiated, her port is removed, and blood cultures 48 hours later are negative.
Which of the following must be included in the initial diagnostic workup?
(Multiple Choice)
4.9/5  (80)
(80) A 50-year-old man comes to the physician for evaluation of an itchy rash on his extremities for the last several weeks. He was diagnosed with hepatitis C infection 6 months ago but refused further workup and treatment. His vital signs are normal. Skin findings are shown in the image below. The remainder of the examination is within normal limits.
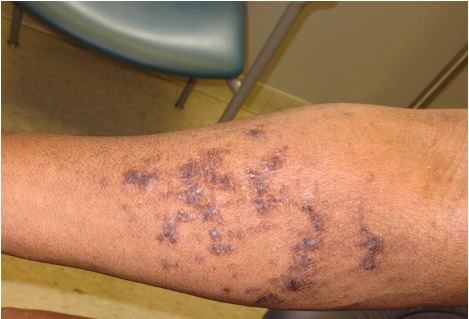 Which of the following is the most appropriate treatment for this patient's current condition?
 (Multiple Choice)
4.8/5 (64)
(64) A 60-year-old man comes to the office due to occasional episodes of dizziness, usually when he tries to get up quickly. He had sustained an anterior wall myocardial infarction 4 months ago, and had emergent percutaneous revascularization of his proximal left anterior descending artery with placement of a stent. He has no chest pain, shortness of breath, palpitations, or syncope. He has been able to resume walking about 3 miles every day.
His home medications include aspirin, clopidogrel, rosuvastatin, carvedilol, sacubitril-valsartan, and spironolactone. Echocardiography performed 1 week ago showed a large area of dyskinesia in the anterior and anterolateral myocardial segments, with an ejection fraction of 25%. There was also mild mitral and tricuspid regurgitation present. These findings are similar to the earlier echocardiogram performed at the time of myocardial infarction.
His blood pressure is 112/62 mm Hg and pulse is 68/min. A soft, 2/6 holosystolic murmur is heard at the cardiac apex in the left lateral position. Lungs are clear to auscultation.
His ECG in the office shows sinus rhythm and Q waves in precordial leads.
Which of the following is the most appropriate next step in management?
(Multiple Choice)
4.9/5 (64)
(64) A 72-year-old woman comes to the office for follow-up of shortness of breath. For the last year, the patient has had increasing dyspnea on exertion and can now walk only 2-3 blocks at a slow pace. She has had no associated chest pain or lightheadedness. The patient was seen at an urgent care facility a month ago and was found to have bibasilar crackles and 1+ bilateral pedal edema. She was started on daily furosemide, with significant improvement in her symptoms, and was instructed to see her regular physician for further evaluation. Medical history is notable for hypertension treated with amlodipine and spironolactone, and the patient has no history of myocardial infarction or stroke. She is a lifetime nonsmoker and does not use alcohol.
Blood pressure is 125/70 mm Hg and pulse is 75/min and regular. Oxygen saturation is 98% on room air. BMI is 24 kg/m2. Cardiac auscultation shows an S4 and no murmurs. Lung sounds are normal. There is no peripheral edema.
ECG shows normal sinus rhythm with left ventricular hypertrophy. Complete blood count and basic metabolic panel are unremarkable. Transthoracic echocardiogram shows left atrial enlargement, left ventricular hypertrophy, left ventricular ejection fraction of 65%, and pulmonary artery systolic pressure of 50 mm Hg.
Which of the following is most likely to improve quality of life in this patient?
(Multiple Choice)
4.9/5 (71)
(71) A 35-year-old man comes to the urgent care center with 2 days of pain in the intergluteal area made worse with sitting. For the last several years, he has had staining of the underwear in that area with clear fluid. The patient has no other symptoms or medical conditions. His temperature is 37 C (98.6 F). Physical examination shows mild swelling and tenderness at the midline immediately below the coccyx with a small sinus opening.
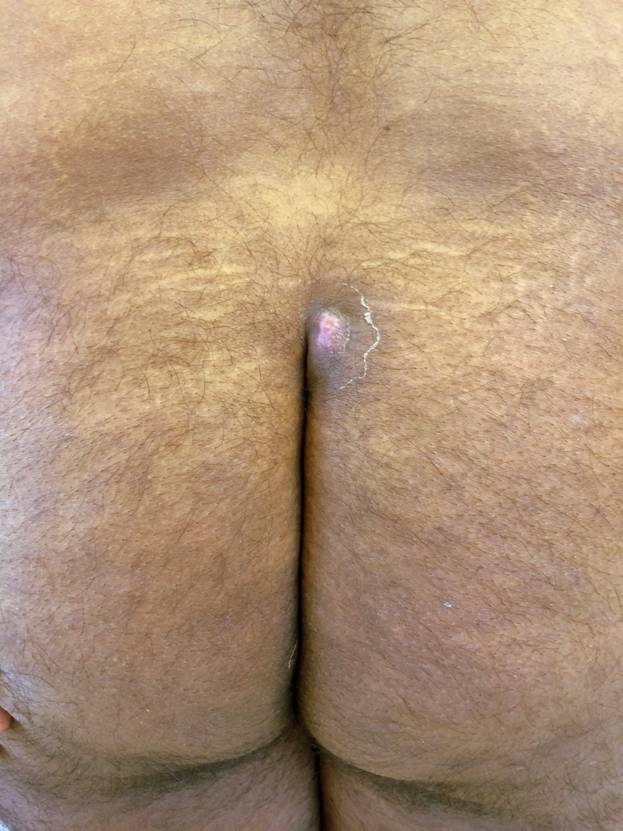 Which of the following is the most likely diagnosis?
 (Multiple Choice)
5.0/5 (73)
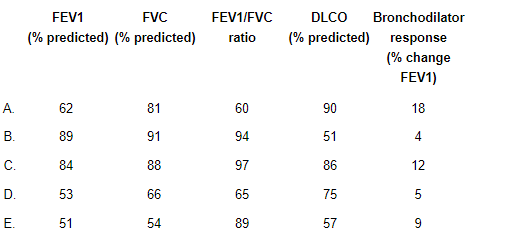
(73) A 70-year-old man comes to the office with a 2-year history of progressive shortness of breath and productive cough. The patient describes frequent episodes of bronchitis treated with oral antibiotics. He has smoked a pack of cigarettes a day for the past 40 years. Breath sounds are decreased throughout the lung fields bilaterally.
Which of the following results is likely to be seen on pulmonary function testing?
FEV1 = forced expiratory volume in 1 second; FVC = forced vital capacity; DLCO = diffusing capacity for carbon monoxide.
(Multiple Choice)
4.9/5 (80)
(80) A 62-year-old man complains of right-sided leg and thigh pain while walking. The pain improves with rest and is described as a heaviness or cramping sensation. His sexual performance has decreased over the past year. The patient's other medical problems include chronic kidney disease, type 2 diabetes mellitus, hypertension, hyperlipidemia, and gastroesophageal reflux disease. He has a 38-pack-year smoking history.
The patient's blood pressure is 144/72 mm Hg, pulse is 67/min, and body mass index is 29 kg/m2. A bruit is heard over the right carotid artery. Peripheral pulses are palpable bilaterally. There is a small ulcer at the tip of the right big toe. No extremity edema is present.
The ankle-brachial index is 1.45 on the right and 1.40 on the left (normal 1.0-1.3). The serum creatinine is 2.2 mg/dL and HbA1c is 7.5%.
Which of the following is the most likely cause of this patient's leg pain?
(Multiple Choice)
4.8/5 (68)
(68) A 57-year-old man comes to the physician with 3 months of cough, night sweats, and subjective fevers. He has been feeling "run down." The patient emigrated from India 26 years ago and has not travelled recently. He had a negative tuberculin skin test 6 months ago performed at work.
Lung examination is significant for reduced breath sounds with dullness to percussion on the left.
Chest imaging reveals a moderate left-sided pleural effusion with bulky mediastinal lymphadenopathy. A thoracentesis shows turbid white fluid. Laboratory results are as follows:
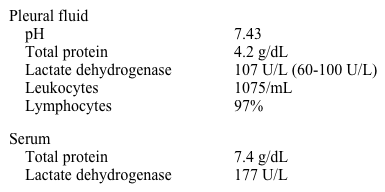 Which of the following tests performed on pleural fluid would help identify the cause of the effusion?
 (Multiple Choice)
5.0/5 (84)
(84) A 54-year-old woman with end-stage renal disease secondary to diabetic nephropathy and hypertension comes to the office due to easy fatigability and tiredness. The patient experienced similar symptoms 6 months ago, but they improved after starting erythropoietin therapy for anemia. Over the past several weeks, the symptoms have recurred but she has had no chest pain, dyspnea, palpitations, syncope, melena, or hematochezia. The patient receives 3-4 hours of maintenance hemodialysis 3 times a week. She has no drug allergies.
Blood pressure is 130/78 mm Hg and pulse is 70/min with no orthostatic changes. She weighs 68 kg (150 lbs), which is her 'dry weight'. There are no heart murmurs. Abdominal examination shows no organomegaly and stool occult blood testing is negative.
Laboratory studies are as follows:
 Hemoglobin was 8.2 g/dL and 10.1 g/dL 6 months and 4 months ago, respectively.
Which of the following is the most appropriate next step in management of this patient's anemia?
Hemoglobin was 8.2 g/dL and 10.1 g/dL 6 months and 4 months ago, respectively.
Which of the following is the most appropriate next step in management of this patient's anemia? (Multiple Choice)
4.8/5 (77)
(77) A 72-year-old man with a history of heart failure and reduced ejection fraction comes to the office for follow-up. The patient reports no change in his chronic dyspnea on exertion but says he has had a persistent, nonproductive cough for the past 4 weeks. The cough occurs during the day and night, and he has not been able to get restful sleep. The patient has had no fever, chills, night sweats, or loss of appetite. In the past year, he has had several hospitalizations due to decompensated heart failure, and 6 months ago he was treated with coronary stenting for an episode of non-ST elevation myocardial infarction. A recent echocardiogram revealed a left ventricular ejection fraction of 30%. The patient's other medical problems include hypertension, hyperlipidemia, and osteoarthritis. He takes aspirin, ticagrelor, atorvastatin, furosemide, carvedilol, sacubitril-valsartan, and spironolactone. He smoked a half pack of cigarettes daily for 10 years, but quit at age 40. The patient does not use alcohol or illicit drugs.
Temperature is 36.6 C (98 F), blood pressure is 106/60 mm Hg, pulse is 72/min and regular, and respirations are 16/min. Pulse oximetry shows 96% on ambient air. Weight is 75 kg (165.3 lb), unchanged from previous visits. Physical examination reveals normal nasal and oropharyngeal mucous membranes, poor dentition, normal jugular venous pressure, clear lungs, and a grade 2/6 systolic murmur at the left sternal border. The abdomen is soft and nontender with no hepatosplenomegaly. Trace bilateral lower extremity pitting edema is present.
Chest x-ray reveals no parenchymal opacities.
Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.7/5 (79)
(79) A 74-year-old man comes to the physician because of daily productive cough with yellowish sputum and dyspnea on exertion. His past medical history includes chronic obstructive pulmonary disease, type 2 diabetes mellitus, hypertension, and hyperlipidemia. Over the last 6 months, he has had 2 hospital admissions for respiratory distress. The most recent admission was 2 months ago, when he was treated with IV corticosteroids and bronchodilators via nebulizer. His medications include formoterol and tiotropium. The patient's dyspnea has improved since discharge but he is short of breath with exertion. He has lost 10 lb (4.5 kg) over the last 6 months. He stopped smoking 7 years ago but has a 60-pack-year history.
Pulse oximetry is 93% on room air. He is notably dyspneic after walking down the hall. Physical examination shows a thin man with bitemporal wasting. His chest is barrel shaped. There is mild diffuse expiratory wheezing on lung examination.
Pulmonary function testing is significant for FEV1 35% of predicted, FVC 55% of predicted, FEV1/FVC 63%, and lung diffusion capacity testing 43% of predicted. Chest x-ray reveals hyperinflation.
Inhaled corticosteroids are added to his regimen during this clinic visit.
Which of the following do inhaled corticosteroids increase?
(Multiple Choice)
5.0/5 (88)
(88) A 40-year-old woman comes to the clinic due to fatigue and generalized weakness for the last 3 months. She has vague, intermittent right upper quadrant abdominal discomfort without pain, nausea, vomiting, or diaphoresis. The patient also reports low back pain and bilateral knee pain. She has had no weight loss or stool changes. Her other medical problems include polycystic ovarian disease, type 2 diabetes, and hyperlipidemia. The patient's menstruations are regular, and she does not use any hormonal contraception. Her medications include glyburide and metformin. She stopped taking a statin due to muscle cramps. The patient drinks 1 or 2 beers (350 mL each) every weekend. Her father was diagnosed with gallbladder carcinoma at age 65. Her mother has hypothyroidism and vitiligo.
Blood pressure is 142/78 mm Hg and pulse is 92/min. BMI is 36 kg/m2. Examination reveals an obese and nontender abdomen. The right knee has mild crepitus. Pinprick sensitivity is decreased below the knees, and the ankle reflex is absent bilaterally.
Laboratory results are as follows:
 Ultrasonogram shows gallstones and a hyperechoic, enlarged liver with a 16-cm span. There is no gallbladder wall thickening or pericholecystic fluid.
Which of the following would most likely improve this patient's liver condition?
Ultrasonogram shows gallstones and a hyperechoic, enlarged liver with a 16-cm span. There is no gallbladder wall thickening or pericholecystic fluid.
Which of the following would most likely improve this patient's liver condition? (Multiple Choice)
4.8/5 (77)
(77) A 27-year-old woman comes to the office due to hair loss. For the last week, small clumps of hair have come out when she showers or brushes her hair. There is no associated pain or itching in the scalp. The patient had an uncomplicated vaginal delivery of her second child 3 months ago, and her medical history is otherwise unremarkable. She is breastfeeding and continues to take a prenatal vitamin. She does not use tobacco, alcohol, or illicit drugs.
Vital signs are normal. Skin examination shows diffuse hair loss across the scalp with no other abnormalities. Complete blood count and serum chemistries are normal. Serum TSH is 4.0 µU/mL and free T4 is 1.2 ng/dL (normal: 0.9-2.4).
Which of the following is the most appropriate next step in management of this patient's hair loss?
(Multiple Choice)
4.8/5 (74)
(74) A 56-year-old woman comes to the physician for follow-up of uncontrolled type 2 diabetes mellitus. Her other medical problems include hypertension and hyperlipidemia. Despite optimal lifestyle and compliance with medications, her fasting blood glucose levels on home glucose monitoring range from 140-160 mg/dL. Her last hemoglobin A1c performed 4 weeks ago was 8.2%. Her current medications include metformin, sitagliptin, amlodipine, hydrochlorothiazide, and simvastatin.
Blood pressure is 102/70 mm Hg, pulse is 89/min, and BMI is 34 kg/m2. The rest of the physical examination is unremarkable.
The patient does not want to go on insulin or any other injectable medications. Adding canagliflozin to her current anti-diabetic medication is considered.
Which of the following medications will most likely need dose adjustment or discontinuation if canagliflozin is added?
(Multiple Choice)
4.9/5 (81)
(81) A 23-year-old man comes to the physician saying that his eyes often have a yellowish hue. He considers himself healthy, eats well, and exercises regularly. He does not use tobacco, alcohol, or illicit drugs. The patient was adopted at a young age and does not know his biological family history.
Vital signs are within normal limits. The tip of the spleen is palpable on inspiration. The remainder of the physical examination is unremarkable.
Laboratory values are as follows:
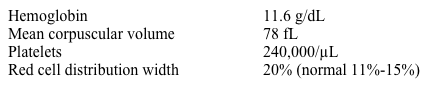 Blood smear shows 3-5 spherocytes per high-power field.
Which of the following is the best next step in the evaluation of this patient?
Blood smear shows 3-5 spherocytes per high-power field.
Which of the following is the best next step in the evaluation of this patient? (Multiple Choice)
4.8/5 (69)
(69) An 86-year-old woman comes to the clinic due to mouth dryness that has led to oral soreness and difficulty tasting, swallowing, and speaking. The patient has a history of locally advanced squamous cell carcinoma of the mouth and recently underwent radiation therapy. Medical history also includes hypertension, diabetes, and depression. She currently takes lisinopril, oxycodone, long-acting morphine, citalopram, and insulin.
Vital signs are normal with no orthostasis. The patient's lips and oral mucosa appear dry. Oral hygiene is poor, and diffuse dental caries are present. The saliva appears stringy. The affected region of her face shows changes consistent with localized radiation therapy. The remainder of the physical examination is normal.
Which of the following is the best next step in management of this patient's symptoms?
(Multiple Choice)
4.8/5 (75)
(75) A 24-year-old woman comes to the office due to a painful lesion in her mouth. She has had similar lesions once or twice a year over the last several years that caused significant discomfort with chewing and lasted 6-7 days. She has no associated rashes, joint pains or swelling, or genital lesions. She does not have any significant past medical history and does not use tobacco or alcohol. The patient is HIV-negative. Her mother has rheumatoid arthritis. Physical examination findings are shown in the image below.
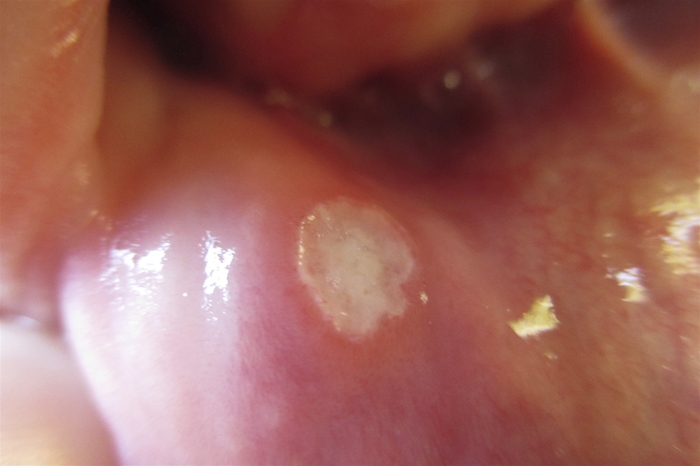 Complete blood count and comprehensive metabolic panel are within normal limits. Erythrocyte sedimentation rate is 12 mm/hr.
Which of the following is the best next step in management of this patient?
Complete blood count and comprehensive metabolic panel are within normal limits. Erythrocyte sedimentation rate is 12 mm/hr.
Which of the following is the best next step in management of this patient? (Multiple Choice)
4.8/5 (89)
(89) A 35-year-old right-handed woman comes to the physician because of a 2-month history of right wrist pain that radiates into her forearm. She also describes a sensation of pins and needles as well as numbness in her right thumb and index finger. She states that her symptoms are worse at night, causing her to wake up in the middle of the night. She has also been inadvertently dropping objects from her right hand. She denies any recent trauma to her right upper extremity, or weakness or numbness involving any of her other limbs. She also denies neck pain. She has no other medical problems. She works as a medical transcriptionist.
Examination shows some atrophy over the right thenar eminence. The sensory examination reveals reduced pinprick sensation along the first, second, and lateral half of the third digit with sparing of the thenar eminence.
An outpatient EMG study is consistent with median neuropathy at the wrist with axonal loss and prolonged motor and sensory latencies.
Which of the following is the next best step in this patient's management?
(Multiple Choice)
4.8/5 (76)
(76) A 60-year-old man comes to the physician with a growth in his left ear. It has been present for a while and never bothered him, but his wife insisted that it be "checked out." His past medical history is significant for hypertension treated with amlodipine and losartan. He has no family history of cancer. He had a colonoscopy 2 years ago and 2 small adenomatous polyps were excised. The skin examination findings are shown in the photograph below.
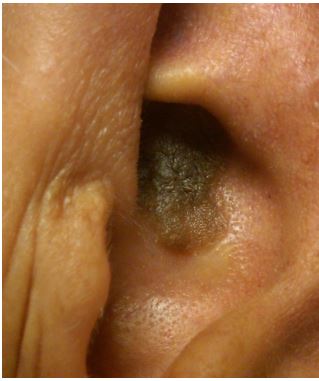 Which of the following is the most likely diagnosis?
 (Multiple Choice)
4.8/5 (78)
(78) A 79-year-old man comes to your office accompanied by his daughter, who is concerned that the patient has become more remote and less interested in participating in his usual activities over the past 6 months. He voices no complaints, but does note some difficulties getting to and maintaining sleep and feeling more short of breath with exertion than usual. He denies chest pain/pressure, orthopnea, and paroxysmal nocturnal dyspnea. His wife died eight months ago from breast cancer. He lives independently and performs all of his activities of daily living.
On examination, he is in no acute distress. He has some difficulty in rising from a chair and stepping up to the examination table. His temperature is 37.1 C (98.8 F), pulse is 114/min and irregular, blood pressure is 148/76 mm Hg, and respirations are 16/min. BMI is 19 kg/m2. Jugular venous pressure is normal. Cardiac examination reveals an irregularly irregular rhythm with a 2/6 systolic ejection murmur along his upper left sternal border. Lungs are clear to auscultation. Abdominal and extremity examinations are within normal limits. There are no focal neurologic findings. He has 4/5 proximal muscle strength in his lower extremities. Results of the five item Geriatric Depression Screen are 1/5. Complete blood count, serum chemistries, liver function panel, and chest x-ray reveal no abnormalities. EKG shows atrial fibrillation.
Which of the following is the most reasonable next step in managing this patient?
(Multiple Choice)
4.8/5 (82)
(82) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)