



 Chat with AI
Exam 3: Office/Health Center

Exam 1: Emergency Department218 Questions
Exam 2: In-patient Facilities128 Questions
Exam 3: Office/Health Center900 Questions
Select questions type


A 63-year-old man, who was diagnosed with type 2 diabetes mellitus 8 years ago, comes to the office for a follow-up appointment. Over the last 2 weeks, he has noticed mild swelling in his legs, as well as fatigue. He has had no shortness of breath, orthopnea, nausea, vomiting, or diarrhea. Over the past year, the patient was found to have albuminuria on 2 separate visits. Three months ago, blood pressure was 122/78 mm Hg, serum creatinine was 1.2 mg/dL, urine albumin-to-creatinine ratio was 250 mg/g, and hemoglobin A1c was 7.2%. Lisinopril was initiated a year ago and the dose was increased 3 months ago. The patient has had no recent viral illnesses or taken any new medications. Current medications include low-dose aspirin, atorvastatin, lisinopril, and glargine insulin. The patient does not use tobacco, alcohol, or illicit drugs.
Blood pressure is 155/95 mm Hg and pulse is 85/min. Auscultation of the heart and lungs shows no abnormalities. The abdomen is nontender and no costovertebral angle tenderness. The patient has 2+ pitting edema of the bilateral lower extremities.
Laboratory results are as follows:
 Hemoglobin A1c is 7.5%. A renal ultrasonogram shows symmetric, normal-sized kidneys with no evidence of hydronephrosis. Which of the following is the next most appropriate step in management of this patient?
 (Multiple Choice)
4.9/5  (95)
(95) An 80-year-old hospitalized woman is evaluated for chest pressure and dyspnea. The patient has advanced stage lung cancer and was admitted 3 days ago for chemotherapy. Her hospital course was complicated by severe nausea and vomiting and an episode of supraventricular tachycardia. On the third day of hospitalization, she complains of chest pressure, epigastric pain, and difficulty breathing. Her other medical problems include type 2 diabetes mellitus, hypertension, and mild diastolic dysfunction.
Her temperature is 38.9 C (102 F), blood pressure is 92/40 mm Hg, pulse is 112 /min, and respirations are 24 /min. The patient's pulse oximetry shows 89% on a nonrebreathing mask. Examination reveals scattered bilateral rhonchi and dullness to percussion over the left base. Her abdomen is soft but tender.
Her laboratory results are as follows:
 Portable chest X-ray shows a moderate left-sided pleural effusion and a retrocardiac air shadow, both of which are new findings compared to the study done one day prior.
Which of the following is most helpful in diagnosing her current condition?
Portable chest X-ray shows a moderate left-sided pleural effusion and a retrocardiac air shadow, both of which are new findings compared to the study done one day prior.
Which of the following is most helpful in diagnosing her current condition? (Multiple Choice)
4.8/5 (73)
(73) A 44-year-old man comes to the physician because of a productive cough consisting of tenacious sputum for the last 2 weeks. He denies fever, chills, wheezes, shortness of breath, and chest pain. He reports getting "bronchitis" and "sinus infections" almost every year for the past five years that subside with antibiotic therapy. He attributes his infections to his smoking, which he has cut down to a half-pack per day over the past year. He was admitted to the hospital for pneumonia one year ago and was treated with intravenous antibiotics. He reports that he was "a healthy child" and received all of his childhood immunizations. There is no family history of lung disease.
His blood pressure is 122/70 mm Hg and his pulse is 89/min and regular. Oxygen saturation is 95% on room air. Examination reveals scattered rhonchi at the right lung base. There is no sinus tenderness. The nasal turbinates look normal. There is no finger or toe clubbing.
Complete blood count with differential is within normal limits. Chest x-ray shows linear atelectasis at the right lung base. Multi-slice CT scan of the chest shows dilation and wall thickening of the right lower lobe bronchi with adjacent areas of fibrosis and possible parenchymal consolidation.
Two sputum cultures from different samples grow Haemophilus influenzae, and acid-fast staining is negative. PPD skin testing shows 3 mm induration after 48 hours.
After three days of antibiotic therapy, the patient reports marked improvement of his symptoms.
Which of the following is the most appropriate next step in management?
(Multiple Choice)
4.8/5 (81)
(81) A 50-year-old woman comes to the physician for a routine screening mammogram. An asymmetric 1.5-cm mass with calcifications is found in the upper outer quadrant of her left breast. She has no weight loss, headaches, or bone pain. She has no other medical problems and takes no medications. There is no family history of ovarian or breast cancer.
The patient's vital signs are normal. BMI is 24 kg/m2. Examination reveals a palpable mass in the left upper quadrant of the left breast. She has no nipple or skin abnormalities.
A core needle biopsy of the mass confirms invasive ductal carcinoma with focal necrosis. Staining for hormone receptors (estrogen/progesterone) and HER2 is negative. She undergoes a wide-margin lumpectomy with surgical axillary lymph node staging. The tumor is 1.8 cm in diameter. She has 4 positive lymph nodes in the axilla. Imaging reveals no evidence of other metastatic disease.
Which of the following is the most appropriate next step in managing this patient?
(Multiple Choice)
4.7/5 (89)
(89) A 36-year-old woman comes to a new primary care provider due to diffuse abdominal pain and poor appetite. The patient has worked as an administrative assistant but recently quit her job "because I always felt uncomfortable. I couldn't get my work done because the pain was bothering me so much." She has difficulty describing the pain in detail and cannot identify any precipitants. Nothing appears to bring relief, although she has felt a little better since leaving her job.
The patient does not use tobacco or alcohol. Family history is noncontributory. Over the past several years, the patient has seen 3 different physicians and had several hospitalizations for similar symptoms; previous workups, including endoscopic studies and an exploratory laparotomy, have revealed no etiology for the pain.
Recent abdominal CT scan and abdominal ultrasound were normal. Physical examination and laboratory tests, including comprehensive metabolic panel, complete blood count, and urinalysis, are within normal limits.
In addition to explaining that serious illness has been ruled out, which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.8/5 (86)
(86) A 65-year-old man comes to the physician to discuss chronic obstructive pulmonary disease. His medications include budesonide/formoterol, tiotropium, and as-needed albuterol. He has dyspnea on exertion after walking 100 yards or up a flight of stairs. The patient has never had an exacerbation requiring hospitalization. He quit smoking 7 years ago and has a 45-pack-year history. SaO2 is 88% on room air at rest. He has a barrel chest, and the lung examination shows decreased air entry bilaterally but is otherwise clear to auscultation. Heart examination is significant for a holosystolic murmur at the left lower sternal border and a loud P2. There is 1+ bilateral pretibial edema. Pulmonary function results are as follows:
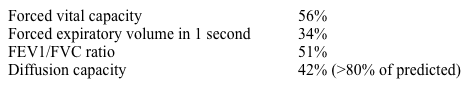 An echocardiogram demonstrates normal left ventricular function, normal right ventricular size and function, and moderate tricuspid regurgitation. Estimated pulmonary artery systolic pressure is 50 mm Hg, and mean pulmonary artery pressure is 29 mm Hg.
In addition to starting home oxygen, which of the following would be recommended in this patient?
An echocardiogram demonstrates normal left ventricular function, normal right ventricular size and function, and moderate tricuspid regurgitation. Estimated pulmonary artery systolic pressure is 50 mm Hg, and mean pulmonary artery pressure is 29 mm Hg.
In addition to starting home oxygen, which of the following would be recommended in this patient? (Multiple Choice)
5.0/5 (75)
(75) A 44-year-old otherwise healthy woman comes to the office due to a cough that has lasted 3 weeks. She had rhinorrhea with clear discharge, sore throat, and mild myalgias for 2-3 days before the cough started. Initially, she coughed up thick, yellow sputum in small amounts, but now she is coughing up small amounts of whitish grey sputum. The cough is worse when she exercises, and it often awakens her from sleep between 1:00 AM and 3:00 AM. The patient has no fevers, chills, vomiting, or chest pain. She takes no medications and does not use tobacco. Her immunizations are up to date. There is no family history of asthma.
Vital signs are within normal limits. Pulse oximetry shows an oxygen saturation of 97% on room air. The nasal mucosa is not congested and there is no evidence of post-nasal drip. Scattered wheezes and rhonchi are present at both lung bases; rhonchi clear when the patient coughs. The remainder of the physical examination is within normal limits.
Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.9/5 (73)
(73) A 37-year-old man comes to the office for evaluation of insomnia and daytime fatigue for the past 6 months. The patient describes frequent nighttime awakenings. He has no snoring or gasping for air, but he awakens suddenly with a feeling of panic. During the day, he feels tired at work and has made several errors in his paperwork due to poor concentration. The patient does not feel sad or depressed but admits that he has been more irritable and uncharacteristically loses his temper with his wife and 2 young children. He has a history of hypertension. Two years ago, he required extensive orthopedic surgery following an injury sustained when he was deployed to a combat zone. He has one alcoholic drink daily and recently has started having a second drink at bedtime to help him relax and fall asleep.
Blood pressure is 130/80 mm Hg, pulse is 72/min, and respirations are 14/min. BMI is 27 kg/m2. Physical examination is unremarkable apart from well-healed surgical scars.
Which of the following is the most appropriate next step in management of this patient?
A)Obtain a polysomnogram
B)Perform a brief intervention for unhealthy alcohol use
C)Prescribe a selective serotonin reuptake inhibitor
D)Prescribe short-term zolpidem and follow up in 2 weeks
E)Screen the patient for post-traumatic stress disorder
(Essay)
4.8/5 (85)
(85) A 30-year-old man comes to the office for worsening headaches. He has had episodic, unilateral, throbbing headaches associated with nausea and occasional vomiting for the past several years. Over the last 6 months, the headaches have become progressively worse and now occur twice a week. The patient usually takes abortive therapy at the onset of a headache, but recently he went to the emergency department 3 times due to uncontrolled pain. Other medical conditions include asthma and gastroesophageal reflux. He was hospitalized twice over the last year for asthma exacerbations but has never required endotracheal intubation. He does not use tobacco, alcohol, or illicit drugs.
Vital signs are within normal limits. BMI is 32 kg/m2. Examination shows no abnormalities. Recent brain MRI was normal.
Which of the following is the best approach for long-term management of this patient's headaches?
(Multiple Choice)
4.9/5 (94)
(94) A 42-year-old man comes to the physician with muscle aches and joint pain. He reports fatigue, headaches, diffuse muscle aches, and occasional spine stiffness for the past 4-6 weeks. He has no fevers, chills, night sweats, dizziness, or vision changes. The patient was diagnosed with Lyme disease 2 months ago after a skin rash and was treated with doxycycline for 21 days. He denies non-compliance with doxycycline. He takes no other medications and does not use tobacco, alcohol, or illicit drugs.
His temperature is 36.7 C (98 F), blood pressure is 134/82 mm Hg, and pulse is 80/min and regular. There are no skin rashes. The neck is supple without lymphadenopathy. Cardiac examination shows no murmurs. There is no joint swelling or peripheral edema. Range of motion is normal. The remainder of the physical examination is unremarkable.
Laboratory results are as follows:
 Which of the following is the next best step in managing this patient?
 (Multiple Choice)
4.9/5 (94)
(94) A 55-year-old man with a history of gout comes to the physician because of progressively worsening pain and swelling in his right knee that started overnight. The patient took two over-the-counter ibuprofen tablets earlier in the day, which were ineffective. He was diagnosed with gout six months ago when he had an ankle effusion, and he was started on allopurinol at that time. His other medical problems include recurrent renal stones, hypertension, and chronic rotator cuff tendinitis. His home medications include benazepril and allopurinol 100 mg daily.
On examination, the right knee appears swollen and tender.
Laboratory studies show a white blood cell count of 12,200 cells/µL, serum creatinine of 1.1 mg/dL, uric acid level of 9 mg/dL (11 mg/dL 6 months ago), and normal liver function tests. Knee aspiration reveals monosodium urate crystals.
Which of the following is the best next step in managing this patient?
(Multiple Choice)
4.8/5 (89)
(89) A 64-year-old woman comes to the office for follow-up. She was diagnosed with chronic obstructive pulmonary disease (COPD) 4 years ago. She initially used albuterol as needed but was started on daily tiotropium a year ago. The patient reports a mild cough and shortness of breath with exertion, which somewhat limits her daily activities. She has no dyspnea or chest pain at rest. She had 3 COPD exacerbations last year but has never been hospitalized, and she has never undergone endotracheal intubation. The patient quit smoking when she was diagnosed with COPD. She received both pneumococcal and annual influenza vaccinations. Her other medical problems include osteoarthritis of the knees and hypertension.
Vital signs are normal. Oxygen saturation at rest is 95% on room air but 90% on room air after a 6-minute walk. BMI is 29 kg/m2. Examination reveals decreased breath sounds bilaterally with no wheezing or crackles. There is no jugular venous distension or peripheral edema.
Pulmonary function testing reveals an FEV1/FVC ratio of 62% and an FEV1 55% of predicted. Chest x-ray shows mild hyperinflation but no infiltrates.
Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.7/5 (82)
(82) A 49-year-old woman comes to the clinic due to night sweats, palpitations, and heat intolerance for the last 4 weeks. She used to exercise regularly to stay "in good shape," but her energy level has been too low for exercise over the last 2 weeks. The patient has no past medical problems and takes no medications, including over-the-counter drugs. Her mother underwent a thyroidectomy 15 years ago.
Blood pressure is 140/70 mm Hg and pulse is 104/min. BMI is 22 kg/m2. The patient has mild lid lag but no proptosis. She has fine tremors involving her hands. Thyroid examination reveals a palpable nodule in the left thyroid lobe. The remainder of the examination is unremarkable.
Her TSH is <0.01 µU/mL. T3 and free T4 are elevated. Urine pregnancy test is negative.
Which of the following tests will be most helpful in identifying the cause of this patient's current condition?
(Multiple Choice)
4.7/5 (90)
(90) A 54-year-old woman with a history of depression, migraine headaches, and fibromyalgia is evaluated at the office at the request of her husband. The couple was returning home from an extended weekend vacation when the patient began behaving strangely. Her husband says she could remember details about herself and their family, but continually asked where they were going even after being told several times. She was anxious and was able to talk and answer questions appropriately. However, she could not remember any new information that she was told during this roughly 8-hour episode. Throughout the event, her husband saw no changes in the patient's ability to walk, write, or speak. He said that the following day she seemed to be back to normal although she did not recall what had happened. The patient has no dizziness, visual difficulties, chest pain, or other concerns.
The patient underwent endoscopy the previous week and was diagnosed with gastroesophageal reflux disease. She is now receiving treatment with a proton pump inhibitor but otherwise has had no recent changes to her medications, which include sertraline and ibuprofen.
Physical examination is unremarkable.
This patient's presentation is most likely a result of which of the following?
(Multiple Choice)
4.9/5 (87)
(87) The fall risk in elderly patients taking a hypnotic medication is being evaluated in a retrospective case-control study. The investigators report the following association between medication consumption and fall incidence over the subsequent week:
Unadjusted odds ratio: 1.40 (95% confidence interval: 1.2-1.6)
Odds ratio adjusted for age and gender: 1.34 (95% confidence interval: 1.1-1.5)
Odds ratio adjusted for age, gender, and handgrip strength: 1.12 (95% confidence interval: 0.8-1.4)
Which of the following is the best interpretation of the study results?
(Multiple Choice)
4.8/5 (71)
(71) A 70-year-old man comes to the office due to weakness and clumsiness of his left leg. The patient's family noticed him dragging the left foot over the past several days, and he fell when his toes caught on a step. He has had no fever, headache, numbness, or visual disturbances. The patient has a history of lacunar infarction causing left-sided hemiparesis several years ago, which improved with physical therapy. His other medical problems include hypertension, type 2 diabetes mellitus, osteoarthritis, and chronic back pain attributed to osteoarthritis. The patient has lived alone since the death of his wife 4 years ago.
Temperature is 36.7 C (98.1 F), blood pressure is 136/88 mm Hg, pulse is 80/min, and respirations are 16/min. Examination shows moist mucous membranes, normal jugular venous pressure, clear lung fields, and normal heart sounds. The abdomen is soft and nontender. Cranial nerve examination is normal. Motor power is 5/5 in both upper and right lower extremities. There is reduced strength of left leg abduction, left foot inversion and eversion, and toe extension. Bilateral upper and lower extremity deep tendon reflexes are normal. While walking, the patient flexes his left thigh higher and his left foot slaps the floor.
Which of the following is most appropriate next step in evaluation of this patient's current symptoms?
(Multiple Choice)
4.8/5 (63)
(63) A 43-year-old construction worker comes to the physician with intermittent fever, cough, and shortness of breath over the last 4 months. He also complains of night sweats and reports a 4.5-kg (10-lb) weight loss. He has no hemoptysis. The patient has no medical problems and does not use tobacco, alcohol, or illicit drugs.
Bilateral scattered wheezes are heard on physical examination. There are no cardiac murmurs. The spleen is not palpable, and there are no skin rashes or lymphadenopathy.
Rapid HIV test is negative. Chest x-ray reveals bilateral pleural-based dense infiltrates involving upper and lower lobes. The infiltrates spare the central and perihilar lung regions.
Which of the following is the most likely diagnosis?
(Multiple Choice)
4.9/5 (80)
(80) A 55-year-old man comes to the physician complaining of an episode of rectal bleeding. His past medical history includes chronic constipation for which he takes over-the-counter laxatives. He also has a history of intravenous drug use and an episode of tricuspid and mitral valve infective endocarditis 15 years ago. Since that episode, he has stopped using illicit drugs. The patient has a 20-pack-year smoking history and drinks 1-2 cans of beer daily. Family history is not significant. He is allergic to penicillin.
His vital signs are within normal limits. Physical examination shows no abnormalities. Stool is positive for occult blood.
The patient is scheduled for a colonoscopy.
Which of the following is the most appropriate next step in management?
(Multiple Choice)
4.9/5 (85)
(85) A 64-year-old man comes to the physician with a 2-month history of increasing cough. He has had a "smoker's cough" for years that has worsened. He has no fever, chills, chest pain, or hemoptysis but has lost 10 lb (4.53 kg) weight. The patient has a 45-pack-year smoking history. He emigrated from Bangladesh 20 years ago.
His vital signs are normal. Pulse oximetry is 96% on room air. Examination shows decreased breath sounds at the right lung base and normal first and second heart sounds. No peripheral lymphadenopathy is present.
Chest x-ray reveals a moderate, right-sided pleural effusion. CT scan of the chest demonstrates a 2.5-cm, spiculated lesion in the right middle lobe 2 cm from the pleural surface and confirms the right pleural effusion. There are no other lesions noted on CT scan, and no mediastinal lymphadenopathy is seen. The patient undergoes thoracentesis with removal of 250 mL of fluid, which shows an exudative effusion. Pleural cytology is negative for malignancy. Gram and acid-fast bacteria stains are negative. Culture shows no growth after 48 hours.
Which of the following is the best next step in managing this patient?
(Multiple Choice)
4.8/5 (79)
(79) A 57-year-old man comes to the physician because of fatigue, abdominal discomfort, and poor appetite. He denies changes in his bowel function or urinary habits. He has lost approximately 10 lbs (4.5 kg) in the past month. Family history is not significant.
His blood pressure is 133/70 mm Hg and pulse is 76/min. Examination shows intact skin on the extremities. Breath sounds are normal. His liver is palpable 3 cm below the costal margin. There is moderate splenomegaly. There is no lymphadenopathy.
Laboratory results are as follows:
 The peripheral smear shows predominantly myelocytes and polymorphonuclear neutrophils. A bone marrow biopsy shows a hypercellular marrow with 7% blasts.
This patient is most likely to benefit from which of the following?
The peripheral smear shows predominantly myelocytes and polymorphonuclear neutrophils. A bone marrow biopsy shows a hypercellular marrow with 7% blasts.
This patient is most likely to benefit from which of the following? (Multiple Choice)
4.8/5 (69)
(69) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)