



 Chat with AI
Exam 3: Office/Health Center

Exam 1: Emergency Department218 Questions
Exam 2: In-patient Facilities128 Questions
Exam 3: Office/Health Center900 Questions
Select questions type


A 29-year-old woman comes to the physician because of recurrent headaches for the past 3 weeks. She describes her headaches as bifrontal and throbbing. She denies decreased vision, vomiting, fever, or head injury. Her stress level has increased over the past few weeks after she was laid off from her job. She has a history of migraine headaches as a teenager. She does not use tobacco or drink alcohol. She takes no medications. She stopped having menstrual periods after a progesterone-containing intra-uterine device was placed 18 months ago.
Examination, including neurologic examination, shows no abnormalities.
Complete blood count, chemistry profile, thyrotropin (TSH), and liver function tests are all within normal limits.
MRI of the brain shows a 7 mm hypointense mass in the pituitary without stalk deviation.
Which of the following is the most appropriate next step?
(Multiple Choice)
4.9/5  (95)
(95) A 64-year-old man comes to the physician with malaise and decreased exercise tolerance for the last 2-3 months. He has no abdominal pain, melena, or hematochezia. His weight and appetite have been stable. The patient's past medical history is significant for hypertension, type 2 diabetes mellitus, hypercholesterolemia, and osteoarthritis. His medications include lisinopril, metformin, pravastatin, and naproxen as needed for knee pain. He does not use tobacco, alcohol, or illicit drugs.
The patient's vital signs are stable. Physical examination shows mild pallor and a systolic murmur at the right upper sternal border. Digital rectal examination reveals brown stool that tests positive for occult blood.
Laboratory results are as follows:
 Upper gastrointestinal endoscopy shows a small hiatal hernia. Antral and duodenal biopsies are unremarkable. Colonoscopy performed up to the last 5 cm of the terminal ileum shows small sigmoid diverticula but is otherwise unremarkable.
Which of the following is the most appropriate next step in management of this patient?
Upper gastrointestinal endoscopy shows a small hiatal hernia. Antral and duodenal biopsies are unremarkable. Colonoscopy performed up to the last 5 cm of the terminal ileum shows small sigmoid diverticula but is otherwise unremarkable.
Which of the following is the most appropriate next step in management of this patient? (Multiple Choice)
4.9/5 (91)
(91) A 45-year-old woman comes to the physician with imbalance and repeated falls over the last 3 months. She has fallen twice in the last week and reports that the imbalance is worse in the dark. She also has numbness of her toes and weakness of both lower extremities. The patient is unable to climb stairs without support. She denies headache, diplopia, blurry vision, back pain, upper extremity symptoms, urinary incontinence, or trauma.
She had Roux-en-Y gastric bypass 3 years ago for morbid obesity. Her medical problems include hypertension and hyperlipidemia. Her current medications are ramipril, fenofibrate, nasal cyanocobalamin (B12), calcium carbonate, iron sulfate, multivitamins, and vitamin D. She began taking over-the-counter zinc supplements 4 months ago. She does not use tobacco, alcohol, or illicit drugs.
Her blood pressure is 120/80 mm Hg without orthostatic changes, and pulse is 68/min. Her BMI is 32 kg/m2. Neurological examination reveals mild bilateral weakness of the ankle extensors and flexors. There is loss of proprioception and touch sensation in her feet up to her ankles. The ankle reflexes are absent but the knee reflexes are brisk. There is bilateral extensor plantar response. She is unstable in Romberg position with her eyes closed. The remainder of the physical examination is unremarkable.
Laboratory results are as follows:
 Which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.9/5 (84)
(84) A 30-year-old woman without significant past medical history comes to the physician with a palpable lump in her neck. She has no associated symptoms and no family history of thyroid or other endocrine disorders. Her TSH level is 1.3 µU/mL (normal 0.5-5.0 µU/mL). Thyroid ultrasound shows a 16-mm round, hypoechoic nodule in the right lobe of the thyroid. There is no lymph node enlargement.
Which of the following is the most appropriate course of action?
(Multiple Choice)
4.8/5 (88)
(88) A 38-year-old woman comes to the office for follow-up 6 weeks after completing triple-drug therapy for Helicobacter pylori infection. Eight weeks ago, she had an esophagogastroduodenoscopy showing a non-bleeding duodenal ulcer with a positive antral biopsy for H pylori. The patient reports improvement of her epigastric discomfort but still feels bloated. She has had no melena or vomiting. The patient is taking daily over-the-counter esomeprazole. She does not use tobacco, alcohol, or illicit drugs.
Her vital signs are stable. The abdomen is soft and nontender. Rectal examination shows guaiac-negative brown stool.
Urea breath test for H pylori is positive.
Which of the following is the best next step in managing this patient?
(Multiple Choice)
5.0/5 (77)
(77) A 39-year-old man seeks care for his third episode of gross hematuria. His first episode occurred shortly after onset of an upper respiratory infection 2 years ago. His most recent episode started about 5 days ago. Both episodes lasted 5-10 days and were not associated with either flank or abdominal pain. The episodes had accompanying mild dysuria. There were no blood clots passed. He has no other medical problems. He takes no medication. There is no family history of kidney disease.
His blood pressure is 132/90 mm Hg, pulse is 72/min, and respirations are 12/min. Physical examination shows no significant abnormalities.
The patient's laboratory studies show:
 Using phase-contrast microscopy, the pathologist finds several dysmorphic red blood cells in the urine. Which of the following is the most appropriate next step in management?
 (Multiple Choice)
5.0/5 (75)
(75) A 36-year-old woman with a history of recurrent major depressive episodes comes to the office due to a 1-month history of severely depressed mood, social isolation, decreased libido, low energy, sleeping 14 hours a day, and weight gain. The patient works as a real estate agent but recently took a leave of absence as she has no motivation and is unable to concentrate. She has had 4 prior episodes of severe depression, starting in her mid-20s after the birth of her first child. The patient's first episode responded to sertraline within several days. She also responded well to venlafaxine, but her husband recalls that she was instructed to stop the medication after 2 weeks due to severe insomnia. The patient has no significant medical history. She has a family history of opioid use disorder. She drinks 1 or 2 glasses of wine a day and does not use illicit drugs.
Temperature is 36 C (96.8 F), blood pressure is 118/75 mm Hg, and pulse is 68/min. Physical examination is normal.
Which of the following would be most important to obtain prior to initiating antidepressant treatment?
(Multiple Choice)
4.7/5 (96)
(96) A 65-year-old woman comes to the physician with a pruritic rash. This is the second year the rash has appeared, both times during the onset of winter. She has intensely pruritic areas on her lower extremities along the shins and above the right lateral malleolus. The patient sometimes experiences pruritus on her lower back and the extensor surfaces of the forearms. One area usually predominates. There is no visible rash initially, but the involved areas can become rough and scaly after a few weeks of frequent scratching. Her only other medical problem is perennial rhinitis. Her medications include cetirizine, calcium plus vitamin D supplements, and a multivitamin.
Skin examination findings are shown in the photograph.
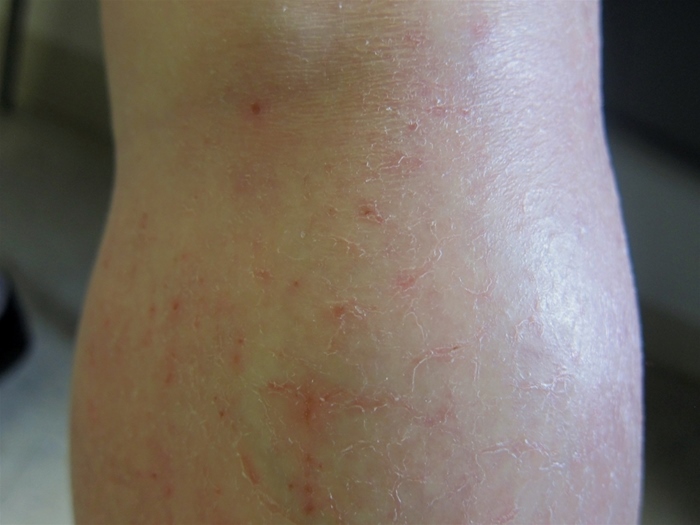 Which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.8/5 (85)
(85) A 56-year-old woman who is post-operative day #1 after a laparoscopic cholecystectomy complains of chest discomfort. The patient reports that in the early hours of the morning, she was awakened from sleep with nausea, one episode of vomiting, and persistent burning in her chest. Her only medical history includes hypertension, which has been well-controlled with medication. Her other current medications include ondansetron, acetaminophen, and hydrocodone.
Her temperature is 37.9 C (100.2 F), blood pressure is 92/60 mm Hg, heart rate is 90 /min, and respirations are 18 /min. Her BMI is 31 kg/m2. She is in moderate distress and appears anxious. There is no murmur on cardiac examination and bilateral fine crackles are heard at the lung bases. Her abdomen is distended and non-tender with an incision that is clean and intact. Bowel sounds are diminished. There is no rebound tenderness or rigidity. There is no peripheral edema.
A 12 lead EKG is performed and displayed below:
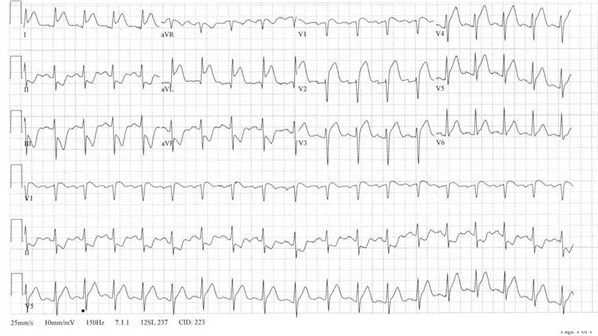 Which of the following would be the most appropriate next step in managing this patient?
 (Multiple Choice)
4.7/5 (75)
(75) A 63-year-old woman comes to the office for her annual checkup. Her medical problems include intermittent insomnia and chronic headaches and stomach pains for several years. She reports no significant change in the frequency and intensity of her headaches or any change in bowel habits. The patient has a history of major depressive disorder treated with citalopram 20 mg. She reports that her mood is "okay" and her appetite is good. She does not use tobacco or alcohol but confides, "I'm worried about my husband because he has been under a lot of stress lately and his drinking is getting worse. We have been arguing and he promises that he will cut down his drinking, but it has been difficult."
Vital signs are within normal limits. Physical examination shows normal heart and lungs; a soft, nontender abdomen with normal bowel sounds; and some mild bruising on her arms that the patient says she sustained while moving heavy furniture. She is tearful when discussing her husband but denies depression or suicidal thoughts.
Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.8/5 (83)
(83) A 67-year-old man comes to the office due to decreased vision in his left eye. While driving 2 weeks ago, he noticed things appeared distorted or were "missing." He has also had difficulty reading despite changing his reading glasses multiple times over the last several months. The patient has had no headaches, eye pain, or double vision. He has a long-standing history of hypertension and is an ex-smoker with a 40-pack-year history.
Funduscopic findings are shown in the image below.
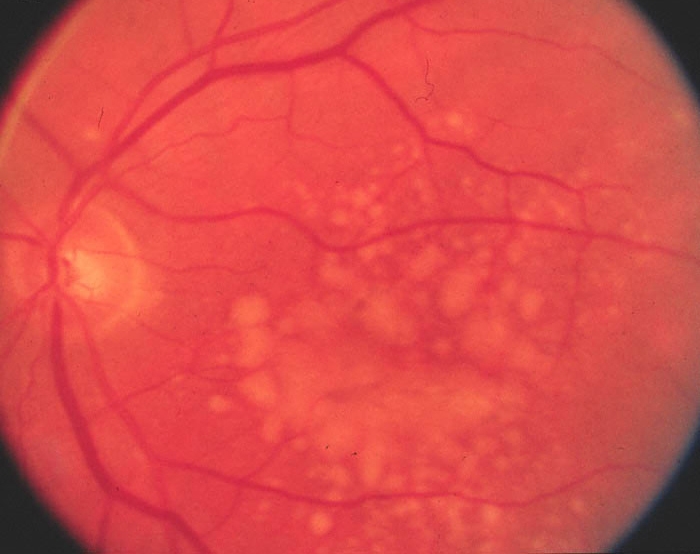 Which of the following is the most likely diagnosis?
 (Multiple Choice)
4.9/5 (74)
(74) A 69-year-old man comes to the office due to severe pain in his left knee for the past 48 hours. The pain began in the middle of the night. He has not had trauma, fever, or chills. He had an episode of pain in his right great toe 3 years ago that he was told was gout. He was given treatment to prevent a recurrence but has been noncompliant. Medical history is significant for hypertension, stage 3 chronic kidney disease, and gastroesophageal reflux disease (GERD). His current medications are atenolol, fosinopril, and lansoprazole.
He appears to be in mild distress and has difficulty with ambulation. Temperature is 36.7 C (98 F), blood pressure is 136/94 mm Hg, pulse is 84/min, and respirations are 14/min. Cardiovascular, pulmonary, and abdominal exams are unremarkable. His left knee is tender, warm, and erythematous with a small effusion. There is decreased range of motion in all aspects. There are no abnormalities of any other joints.
Laboratory results are as follows:
 Plain films of the knee are remarkable only for evidence of degenerative joint disease.
On arthrocentesis of the left knee, a small amount of fluid was obtained with a negative gram stain and 13,000/mm3 white blood cells (50% polymorphonuclear cells). Needle-shaped, negatively birefringent crystals are present on polarized microscopy.
Which of the following is the best treatment option for this patient?
Plain films of the knee are remarkable only for evidence of degenerative joint disease.
On arthrocentesis of the left knee, a small amount of fluid was obtained with a negative gram stain and 13,000/mm3 white blood cells (50% polymorphonuclear cells). Needle-shaped, negatively birefringent crystals are present on polarized microscopy.
Which of the following is the best treatment option for this patient? (Multiple Choice)
4.8/5 (87)
(87) An 18-year-old woman comes to the office due to 6 months of painful menstrual periods. The patient's menstrual period began yesterday, and she has severe lower abdominal pain and cramping that has caused her to stay home from school. She has associated headaches, nausea, fatigue, and dizziness. Acetaminophen has not relieved any of these symptoms. Menarche was at age 13, followed by irregular menstrual periods for the first year. Her menstrual periods are now monthly and consist of 4 days of moderate bleeding. The patient is sexually active with her boyfriend. She has no other medical problems. The patient does not use tobacco, alcohol, or illicit drugs.
BMI is 30 kg/m2. Pelvic examination and the remainder of the physical examination are within normal limits. Pregnancy test is negative.
Which of the following is the best next step in management of this patient?
(Multiple Choice)
5.0/5 (82)
(82) A 71-year-old woman comes to the physician for constipation. She has had 1-2 bowel movements a week associated with straining and the sensation of incomplete evacuation for the past 5 years. She has no rectal bleeding, abdominal pain, weight loss, pain with defecation, change in stool caliber, or diarrhea. The patient has increased her exercise and fluid intake without improvement in symptoms. She had a colonoscopy 3 years ago in which only 1 small hyperplastic polyp was found. Her past medical history includes hypertension, for which she takes chlorthalidone.
Vital signs are normal and her body mass index is 29 kg/m2. Physical examination and rectal examination, which shows normal sphincter tone and no palpable masses, are unremarkable.
Laboratory tests, including electrolytes, renal function, and thyroid studies, are within normal limits. A radio marker study is performed and demonstrates delayed motility in the proximal colon.
Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (76)
(76) A 76-year-old man comes to the office because of lightheadedness. It occurs occasionally while he does yard work and is sometimes accompanied by chest pressure. He denies any syncope, shortness of breath, or palpitations. He has a history of hypertension, hyperlipidemia, gout, and osteoarthritis. He is an ex-smoker.
His blood pressure is 148/78 mm Hg, pulse is 78 /min, and respirations are 16 /min. The patient's pulse oximetry showed 97% on room air. His BMI is 28 kg/m2. Cardiac examination reveals a soft S2. There is a 3/6 late peaking systolic ejection murmur at the right upper sternal border. The carotid, radial, and femoral pulses are 2+ and are not delayed. There is 1+ edema in the lower extremities.
Echocardiogram shows normal left ventricular size and function with moderate concentric left ventricular hypertrophy. The aortic valve is calcified with restricted opening, and the mean gradient across the aortic valve is 50 mm Hg.
Which of the following would be the role of heart catheterization in this patient?
(Multiple Choice)
4.8/5 (73)
(73) A 78-year-old woman comes to the physician following discharge from the hospital. One week ago, she had gone to the emergency department for palpitations, which she had experienced several times before, and she was diagnosed with atrial fibrillation with rapid ventricular response. The arrhythmia resolved spontaneously overnight, and the patient was discharged the following day. She has no chest pain or shortness of breath and has never had syncope.
Past medical history includes hypertension and hyperlipidemia. The patient's medications include aspirin, diltiazem, atorvastatin, and ramipril. She exercises most days of the week on a stationary bicycle for 20-30 minutes without any difficulty. The patient volunteers at a senior center and helps care for her husband with Alzheimer's dementia.
Blood pressure is 135/75 mm Hg, pulse is 75 and regular, and BMI is 25 kg/m2. Cardiac auscultation shows no murmurs. Her lungs are clear. Distal pulses are normal and symmetric. There is no edema.
Electrocardiogram (ECG) shows normal sinus rhythm with no significant repolarization abnormalities. Transthoracic echocardiogram shows a mildly dilated left atrium, left ventricular ejection fraction of 55%, and mild mitral and tricuspid regurgitation.
Laboratory studies show a TSH of 2.9 µU/mL.
Which of the following is the most appropriate next step in management?
(Multiple Choice)
5.0/5 (63)
(63) A 57-year-old man comes to the office after a recent hospitalization. Two weeks ago, he went to the emergency department due to chest pressure and was diagnosed with an acute ST elevation myocardial infarction. Emergency coronary angiography revealed an occluded left anterior descending artery, which was opened with a stent. The patient did well after the procedure and remained in the hospital for 2 days.
Since leaving the hospital, he has had no further chest discomfort. The patient notes dyspnea on exertion, and his current exercise tolerance is limited to walking 2 blocks on a flat surface. Other medical issues include hypertension, hyperlipidemia, and type 2 diabetes mellitus. Current medications include carvedilol, sacubitril-valsartan, aspirin, ticagrelor, atorvastatin, dapagliflozin, and furosemide.
Temperature is 36.7 C (98 F), blood pressure is 125/70 mm Hg, and pulse is 88/min. BMI is 33 kg/m2. The patient is in no acute distress. Estimated jugular venous pressure is 12 cm H2O. There is a 2/6 holosystolic apical murmur that radiates to the axilla. Crackles are heard at the right lung base that clear with deep inspiration. There is 1+ pitting lower extremity edema bilaterally to the mid-shin.
Laboratory results are as follows:
 ECG shows normal sinus rhythm. There are Q waves in the anterior precordial leads with a QRS complex duration of 80 msec. Echocardiography performed prior to discharge showed hypokinesis of the anterior and anterolateral walls, moderate mitral regurgitation, and a left ventricular ejection fraction of 30%.
Which of the following would be the most appropriate next step in the management of this patient?
ECG shows normal sinus rhythm. There are Q waves in the anterior precordial leads with a QRS complex duration of 80 msec. Echocardiography performed prior to discharge showed hypokinesis of the anterior and anterolateral walls, moderate mitral regurgitation, and a left ventricular ejection fraction of 30%.
Which of the following would be the most appropriate next step in the management of this patient? (Multiple Choice)
4.9/5 (90)
(90) A 20-year-old man with known cystic fibrosis is evaluated for productive cough, dyspnea, and malaise that have progressively worsened over the last 3 months. He describes daily brownish sputum production and episodes of wheezing/chest tightness partially relieved by albuterol inhaler. One month ago, he was hospitalized and treated with intravenous antibiotics. He received saline nebulizer, azithromycin, inhaled tobramycin, and chest physiotherapy. The patient has no other medical problems. His medications include dornase alfa, pancrelipase, hypertonic saline therapy, and a short-acting albuterol inhaler as needed.
His temperature is 36.6° C (98° F) and BMI is 20 kg/m2. Examination shows pale conjunctivae. There are bilateral scattered rhonchi and wheezes with prolonged expiration on auscultation.
Laboratory results are as follows:
 Chest x-ray shows new bilateral patchy upper-lobe infiltrates compared to prior x-rays.
Which of the following is the most likely diagnosis?
Chest x-ray shows new bilateral patchy upper-lobe infiltrates compared to prior x-rays.
Which of the following is the most likely diagnosis? (Multiple Choice)
4.9/5 (73)
(73) A 66-year-old man comes to the physician with watery diarrhea for the past 2 days. The diarrhea is nonbloody and occurs about 3 times during the day and once or twice at night. He has no fever or abdominal pain. The patient is currently on day 6 of amoxicillin/clavulanate that his primary care physician prescribed for maxillary sinusitis.
His blood pressure is 110/64 mm Hg, pulse is 84/min, and respirations are 20/min. He appears in no acute distress. Cardiopulmonary examination is within normal limits. The abdomen is soft without tenderness. Rectal examination shows normal tone without stool in the vault.
 Stool samples are negative for Clostridium difficile using polymerase chain reaction.
Which of the following is the best next step in management of this patient?
Stool samples are negative for Clostridium difficile using polymerase chain reaction.
Which of the following is the best next step in management of this patient? (Multiple Choice)
4.9/5 (66)
(66) A 42-year-old man comes to the physician because of a tingling sensation and pain in both hands. He believes that his hands are 'swollen.' He reports bilateral tingling and electric shock-like pain on the lateral aspect of his palms and first three digits. He is a software engineer and has difficulty typing because of bilateral hand pain. He also complains of fatigue and excessive malodorous sweat. His other medical problems include obstructive sleep apnea and hypertension and he uses CPAP at night. His medications include enalapril, amlodipine, chlorthalidone, and aspirin. He does not smoke cigarettes or drink alcohol.
His blood pressure is 146/88 mm Hg, pulse is 88/min, and BMI is 34 kg/m2. Skin examination reveals oily skin with skin tags over the nape of his neck. Tinel's sign is positive bilaterally.
Laboratory results are as follows:
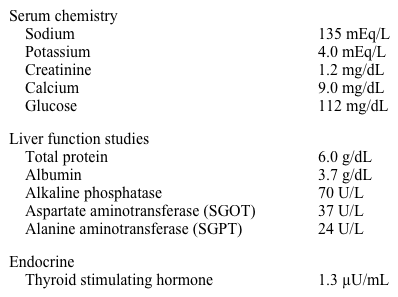 Which of the following is the best next step in managing this patient?
 (Multiple Choice)
4.8/5 (70)
(70) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)