



 Chat with AI
Exam 3: Office/Health Center

Exam 1: Emergency Department218 Questions
Exam 2: In-patient Facilities128 Questions
Exam 3: Office/Health Center900 Questions
Select questions type


A 24-year-old man comes to an urgent care center because of a 2 week history of watery diarrhea. The patient's stools are pale, voluminous, foul smelling, and non-bloody. He has lost 5 pounds (2.3 kg) over the past week despite eating normally. He denies fever or abdominal pain, but does admit to bloating and flatulence. He is an avid hiker, but denies recent travel.
His vital signs are within normal limits. His abdomen is soft and non-tender with normal bowel sounds. The remainder of his examination shows no abnormalities.
Laboratory results are as follows:
 Which of the following is the most appropriate next step in management?
 (Multiple Choice)
4.9/5  (74)
(74) A 40-year-old man comes to the physician with pain, swelling, warmth, and redness of his distal right lower extremity for the past 3 days. No recent trauma has occurred to the area. He had a similar episode 1 year ago in his right leg and was hospitalized for cellulitis, which responded quickly to antibiotics. He has no previous history of lower-extremity edema or recurrent infections. The patient exercises at a gym 3 times a week. He does not use tobacco or illicit drugs and works as an accountant.
Vital signs are within normal limits. BMI is 32 kg/m2. Examination shows swelling, warmth, and erythema of his right lower extremity starting from his foot up to the mid-calf region. There is also erythema in the 1st and 2nd toe web spaces with chronic-appearing skin erosions. There is no purulent drainage or ulcers. Pulses are 2+ in the bilateral lower extremities.
In addition to treatment of his cellulitis, which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (80)
(80) A 64-year-old man seeks treatment for erectile dysfunction. He has been in a stable, monogamous relationship for many years. Over the last 3 years, he has had progressive difficulty attaining and maintaining an erection sufficient for successful intercourse. He relates that his sexual desire is unchanged, but he no longer has spontaneous morning erections. His medical problems include type 2 diabetes mellitus, hypertension, hyperlipidemia, and coronary artery disease.
He underwent successful angioplasty of the proximal left anterior descending artery for non-ST elevation myocardial infarction 2 years ago with a drug-eluting stent. He can walk up 4 flights of stairs and about 6 blocks at a modest pace before he has to stop due to fatigue. He has occasional episodes of angina while walking at a fast pace or in cold weather. His current medications include metformin, rosuvastatin, losartan, metoprolol succinate, clopidogrel, low-dose aspirin, and isosorbide mononitrate.
His blood pressure is 124/74 mm Hg, pulse is 64/min, and respirations are 14/min. His BMI is 31 kg/m2. Cardiopulmonary and abdominal examinations are within normal limits. Femoral and peripheral pulses are 2+ and symmetric. Testes are normal size. Both feet have decreased sensation to pinprick.
Echocardiogram shows ejection fraction of 42%. He is able to walk on a treadmill to 84% of predicted maximum without chest pain or ECG changes. His systolic blood pressure does not decrease with treadmill exercise.
Laboratory testing shows normal complete blood count and a morning total serum testosterone of 340 ng/dL.
Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (86)
(86) A 51-year-old woman comes to the office due to 2 days of progressive left leg pain and swelling. She has had no trauma, fever, chills, chest pain, or shortness of breath. The patient has a history of invasive ductal breast carcinoma treated with surgery and chemotherapy 2 years ago and was recently found to have brain metastases after a new-onset seizure. She is undergoing brain radiation treatment and hormonal therapy for the cancer.
Temperature is 37.2 C (99 F), blood pressure is 120/60 mm Hg, pulse is 84/min and regular, and respirations are 20/min. Pulse oximetry shows 98% on room air. Cardiopulmonary examination reveals no abnormalities. There is left leg pitting edema and calf tenderness, but the right lower-extremity examination is normal.
Compression ultrasonography reveals an occluding thrombus in the left femoral vein. Platelet count and coagulation studies are within normal limits. Stool guaiac is negative. MRI of the brain 2 weeks ago showed several 1- to 3-cm metastatic lesions in the right frontal and parietal lobes.
Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.9/5 (95)
(95) A 34-year-old woman with a history of migraine headaches comes to the office due to insomnia. She has difficulties with sleep initiation/maintenance that started 5 years ago when she became the caretaker for her mother, who had Alzheimer dementia. She slept poorly as she had to be alert in case her mother called for her during the night. Although her mother passed away 3 years ago, the patient still has insomnia.
The patient takes >1 hour to fall asleep. She wakes up twice in the middle of the night and may take up to 45 minutes to fall back asleep. When she can't sleep, she stays in bed thinking about her career, lack of social life, and "ticking biological clock." She is exhausted the next day. The patient has no snoring or awakenings with gasping. She does not feel depressed. There is no history of tobacco, alcohol, or illegal drug use.
Vital signs are within normal limits. The patient is thin and in no acute distress. Physical examination is unremarkable.
Which of the following is the most appropriate treatment for this patient's insomnia?
(Multiple Choice)
4.9/5 (71)
(71) A 78-year-old retired professor comes to the physician because of occasional headaches that have gradually worsened over the last six months. The headaches are right-sided and involve the corner of the right eye. He also gets pains in his jaw while chewing food. He has hyperlipidemia and he takes atorvastatin daily. He asks if the medication might be causing his symptoms.
His other medical problems include coronary artery disease for which he had a stent placed in his left anterior descending artery five years ago. He has no history of strokes, vision problems, or peripheral artery disease. He is a lifetime non-smoker.
Physical examination reveals a right-sided carotid bruit. Heart sounds are normal. The remainder of the physical examination is within normal limits.
Laboratory results are as follows:
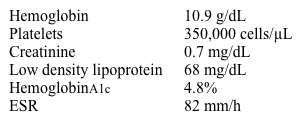 Which of the following should be part of the long-term management for this patient?
 (Multiple Choice)
4.9/5 (74)
(74) A 65-year-old man with moderate chronic obstructive pulmonary disease comes to the physician complaining of a dry cough over the past week. He has no fever, chills, night sweats, or weight loss, but the cough has kept him awake at night. The patient has been using his rescue albuterol 3 times a day. Pulmonary function testing a month ago showed a forced expiratory volume in 1 second of 53% of predicted, a forced vital capacity of 64% of predicted, and FEV1/FVC ratio of 0.56. His past medical history also includes hypertension and hyperlipidemia. His other medications include budesonide/formoterol, tiotropium, long-acting nifedipine, and simvastatin.
His temperature is 37 C (98.6 F), blood pressure is 120/80 mm Hg, pulse is 89/min, and respirations are 18/min. Pulse oximetry is 97% on room air. Examination shows a thin, elderly man in no significant respiratory distress but with frequent cough. There is good air entry with diffuse bilateral wheezes in all lung fields and scattered coarse breath sounds that clear with cough.
Posteroanterior and lateral chest x-rays reveal no infiltrates. His white blood cell count is 6,700/µL with normal differential.
Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (82)
(82) A 31-year-old woman is assessed for difficulty sleeping and feeling exhausted nearly every day for the past 6 months. When the patient pushes herself to perform basic household tasks, she has no energy for the next 1 or 2 days and says, "My muscles ache for hours afterward." She gets 6-7 broken hours of sleep a night and does not feel rested on awakening. The patient also has intermittent headaches and difficulty concentrating. Other than an episode of influenza 8 months ago, she has been in good health.
The patient describes feeling "down in the dumps" as she cannot go to the gym or socialize with friends as she once did. She works as a counselor but has recently missed at least a day of work a week due to worsening exhaustion and body aches. She enjoys her job and is anxious that the frequent absences will result in her termination; she asks the physician for a doctor's note. The patient does not use tobacco, alcohol, or illicit drugs.
Vital signs and physical examination are unremarkable.
Laboratory results are as follows:
 Which of the following is the most likely diagnosis in this patient?
 (Multiple Choice)
4.8/5 (89)
(89) A 68-year-old woman comes to the office and inquires about screening mammography. The patient has had normal biennial mammographies in the past and reports no breast symptoms. Medical conditions include hypertension, type 2 diabetes mellitus treated with insulin, hypercholesterolemia, end-stage renal disease on hemodialysis, ischemic stroke with residual deficits, and congestive heart failure with an ejection fraction of 15%. The patient has been hospitalized 3 times in the past year due to decompensated heart failure. She has a 50-pack-year smoking history. The patient has no personal or family history of breast or ovarian malignancies. She ambulates using a walker.
Which of the following is the most appropriate recommendation regarding breast cancer screening for this patient?
(Multiple Choice)
4.8/5 (92)
(92) A 45-year-old man comes to the office due to difficulty hearing in the right ear. The patient first noticed that he could not hear in his right ear when he awoke this morning. He has had no ringing in the ear, earache, or drainage, and no recent upper respiratory illness. There is also no associated vertigo, tinnitus, or imbalance. He has a history of seasonal allergy but has had no recent symptoms. The patient takes no medications, drinks alcohol occasionally, and does not use tobacco or illicit drugs.
Vital signs are within normal limits. Otoscopic examination shows a normal external auditory canal, and the tympanic membrane is gray with a normal light reflex. The patient is unable to hear a whisper in the right ear. Sound from a tuning fork placed in the middle of the forehead lateralizes to the left ear. The tuning fork is heard better when held in front of either ear compared to when placed on the ipsilateral mastoid. No nystagmus is present. The remainder of the examination is within normal limits.
Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.7/5 (72)
(72) A 56-year-old woman is evaluated for persistent fatigue. A year ago, she developed panhypopituitarism following resection of a large nonfunctional pituitary tumor. Current treatment includes hydrocortisone and levothyroxine, with her most recent dose adjustment a few months ago. The patient has had no associated headaches, excessive urination, visual disturbances, or weight change. Vital signs are normal. BMI is 26 kg/m2 with no change in weight over the last 6 months. Physical examination is unremarkable.
Laboratory results are as follows:
 An MRI of the pituitary 6 months ago showed no residual pituitary tumor. Which of the following is the most appropriate next step in management of this patient's disorder?
 (Multiple Choice)
4.8/5 (76)
(76) A 68-year-old woman is seen in the clinic for a 5-day history of diarrhea. The patient's stools are small, watery, and contain no blood or mucus. She has had no fever, dizziness, nausea, vomiting, or abdominal pain. Her other medical problems include hypertension, osteoporosis, gastroesophageal reflux, and stress incontinence. Several years ago, the patient had aortic valve replacement with a mechanical valve due to stenosis from a bicuspid aortic valve. Current medications include aspirin, amlodipine, alendronate, warfarin, and calcium and vitamin D supplements. The patient has not traveled recently or eaten anything unusual.
She is afebrile; blood pressure is 132/70 mm Hg and pulse is 78/min with no orthostatic changes. The remainder of the examination is within normal limits.
Laboratory results are as follows:
 In addition to careful follow-up of INR, which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.9/5 (80)
(80) A 58-year-old woman comes to the office due to leakage of urine. The patient has had increased urinary frequency over the last 3 months, often voiding 1 or 2 times every hour and multiple times each night. She has difficulty initiating urination and voids a small volume of urine. The patient now has continued leakage of urine, requiring her to wear an incontinence pad. She has no dysuria or hematuria.
The patient has a history of depression and switched from sertraline to amitriptyline 4 months ago. She underwent a total abdominal hysterectomy 2 years ago for endometrial hyperplasia. She does not use tobacco, alcohol, or illicit drugs.
BMI is 30 kg/m2. Vital signs are normal. Abdominal examination reveals a lower abdominal mass. Pelvic examination reveals continuous leakage of urine from the urethra; no pooling is seen in the vaginal vault. A small amount of urine is leaked with cough-stress test; postvoid residual volume is 500 mL.
Which of the following is the most likely diagnosis in this patient?
(Multiple Choice)
4.9/5 (80)
(80) A 38-year-old Puerto Rican woman comes to the physician because of fever and fatigue for the last two weeks. Over the past few days, she has developed bilateral pedal edema, ankle pain with walking, and painful bruises on her shins without any trauma. She denies diarrhea, vaginal discharge, or lower abdominal pain. Her weight has been stable. She has no travel history within the past year. She denies tobacco, alcohol, or illicit drug use. She is in a monogamous relationship with her long-standing, live-in boyfriend and uses oral contraceptives.
Her temperature is 38.1 C (100.5 F), blood pressure is 122/70 mm Hg, and pulse is 86/min. Chest examination is unremarkable. The liver span is 11 cm and the tip of the spleen is not palpable. There are several violaceous, tender, raised lesions over both pretibial areas and 1+ pretibial edema. Both ankles are warm to the touch with some discomfort on passive movement.
Complete blood count, comprehensive metabolic panel, and urinalysis are all within normal limits.
Which of the following would be most useful in establishing the diagnosis in this patient?
(Multiple Choice)
4.9/5 (86)
(86) A 44-year-old woman comes to the office due to fatigue. Medical history is notable for hypertension, obesity, and hypothyroidism; current medications include hydrochlorothiazide, amlodipine, and levothyroxine. The patient does not use tobacco but drinks 1 or 2 glasses of wine on weekends. She stopped using recreational drugs approximately 10 years ago.
Examination shows multiple skin xanthelasmas, a few scattered hyperpigmented spots, and tenderness in the right upper quadrant of the abdomen. The liver is palpable 3 cm below the costal margin and mild splenomegaly is present.
Laboratory results are as follows:
 Which of the following is this patient at the highest risk of developing?
 (Multiple Choice)
4.9/5 (80)
(80) A 47-year-old man comes to the physician with a scaly rash on his face. Two weeks ago, he went to an urgent care clinic and was treated with a topical corticosteroid and antifungal agent. Despite consistent use of these agents, the rash has not improved. He also has new areas on his arms and legs. He reports that he feels constantly embarrassed by his condition.
The skin examination findings are shown in the photograph below.
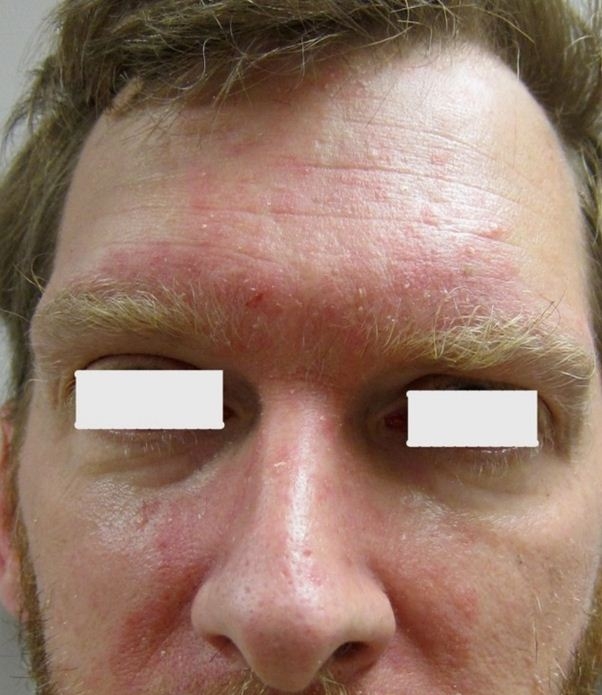 Which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.9/5 (83)
(83) An outbreak of influenza A occurs in the community, and a case has just been confirmed at a nursing home. Three additional residents with a flulike illness are identified in the same facility. The nursing home plans to institute measures to prevent further spread of the infection.
Which of the following measures is most likely to have the highest impact in reducing the number of new influenza cases at the facility during this outbreak?
(Multiple Choice)
4.9/5 (79)
(79) A 40-year-old man comes to the office due to sleep difficulties over the past 2 years. He regularly goes to bed at 11:00 PM but is unable to fall asleep until 12:30 AM. As bedtime approaches, he typically becomes tense, watches the clock, and worries about the prospect of another sleepless night. The patient eventually falls asleep and awakens by alarm at 6 AM in order to arrive at his office by 8 AM. During the day he feels fatigued and is concerned that his insomnia is negatively affecting his work performance. The patient does not take naps during the day. His wife has not noticed any snoring or unusual limb movements during sleep. His general health has been good and he takes no medication. He would like to exercise but feels too tired.
Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.8/5 (72)
(72) A 32-year-old primigravid woman at 36 weeks gestation comes to the office for consultation regarding abnormal test results. The tests were part of an evaluation for an episode of burning epigastric pain that radiated to the chest and has since resolved without treatment. The patient has fatigue and malaise but attributes these symptoms to pregnancy. She has no chronic medical conditions and has had no surgeries. The patient takes a prenatal vitamin daily and acetaminophen as needed for lower back pain. She does not use tobacco, alcohol, or illicit drugs. The patient's father died of alcoholic cirrhosis, and her mother underwent a cholecystectomy for gallstone cholecystitis.
Blood pressure is 120/70 mm Hg and pulse is 82/min. Examination reveals a nontender gravid uterus appropriate for gestational age and 1+ bilateral pedal edema. The remainder of the physical examination is unremarkable.
Laboratory results are as follows:
 Abdominal ultrasound shows normal liver echogenicity, a liver span of 12 cm, a normal-sized spleen, a gallbladder with multiple stones, and a common bile duct size of 4 mm. There is no pericholecystic fluid.
Which of the following is the best next step in management of this patient?
Abdominal ultrasound shows normal liver echogenicity, a liver span of 12 cm, a normal-sized spleen, a gallbladder with multiple stones, and a common bile duct size of 4 mm. There is no pericholecystic fluid.
Which of the following is the best next step in management of this patient? (Multiple Choice)
4.7/5 (77)
(77) Which of the following patients would require a Pap test as part of a routine health maintenance examination?
(Multiple Choice)
4.9/5 (77)
(77) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)