



 Chat with AI
Exam 2: Pediatric

Exam 1: Medicine2 k Questions
Exam 2: Pediatric723 Questions
Exam 3: Psychiatry336 Questions
Exam 4: Surgery563 Questions
Exam 5: Obstetrics & Gynecology469 Questions
Select questions type


A 3-year-old girl is brought to the urgent care clinic due to chronic cough. The cough began 5 weeks ago and is nonproductive. Three weeks ago, the patient was seen for left lower lobar pneumonia; she completed 10 days of amoxicillin, but the cough has not improved. The patient has mild eczema but is otherwise healthy; her immunizations are up to date. The family had been living in a shelter the previous 2 months but recently moved in with the patient's aunt and her young children. Temperature is 37.1 C (98.8 F). Lung auscultation shows decreased breath sounds on the left with expiratory wheezing. Chest x-ray reveals a left lower lobe infiltrate and hilar adenopathy. Which of the following is the most likely cause of this child's symptoms?
(Multiple Choice)
4.9/5  (73)
(73) A 5-year-old girl is brought to the clinic with joint pain and rash. Last week, the patient developed pain in her knees. The pain resolved after a few days, but now her ankles and wrists are tender. She has also developed a nonpruritic, pink rash on her back. The patient had previously been healthy except for a sore throat a few weeks ago that resolved on its own. Temperature is 38.3 C (101 F), pulse is 85/min, and respirations are 20/min. Cardiac examination is normal. The lungs are clear to auscultation. The wrists and ankles are stiff and tender to manipulation. Multiple large, well-demarcated, erythematous, nonpruritic patches with a slightly raised outline are present on the trunk and proximal limbs. Laboratory results are as follows:  Which of the following is the most likely diagnosis in this patient?
 (Multiple Choice)
4.9/5 (78)
(78) The parents of a 16-year-old boy come to the pediatrician's office to discuss concerns about their son's behavior. The mother reports that he has been more distant and his grades have dropped over the past 2 months. The patient has no significant medical history and takes no medication. The parents ask if the physician can order a urine drug test without their son's knowledge. The father says, "We just want to get him help if he needs it." Which of the following is the most appropriate response to the parents?
(Multiple Choice)
4.8/5 (82)
(82) A 3-week-old girl is brought to the emergency department due to apnea and cyanosis. Her mother reports multiple episodes over the last 48 hours of gagging and gasping for air. During the last event, the patient started coughing harshly during a feed and then stopped breathing. She became cyanotic for approximately 12 seconds, then quickly returned to normal. The patient has a 1-week history of clear rhinorrhea and increasing cough with episodes of emesis. Temperature is 37.2 C (99 F), blood pressure is 85/52 mm Hg, pulse is 110/min, and respirations are 45/min. She is well developed and active. There is nasal congestion and clear rhinorrhea. Lung sounds are clear except for referred upper airway congestion. Cardiac and abdominal examinations are normal. Which of the following is the most appropriate empiric pharmacotherapy for this patient's condition?
(Multiple Choice)
4.9/5 (86)
(86) A 6-month-old boy is brought to the office for evaluation of a progressive facial rash that started 3 weeks ago near his eyebrows and spread to areas of the face and scalp. The rash does not appear to be painful or pruritic. The mother recently started using a mild, unscented shampoo that slightly improved the scalp rash. Physical examination of the scalp is shown in the exhibit. 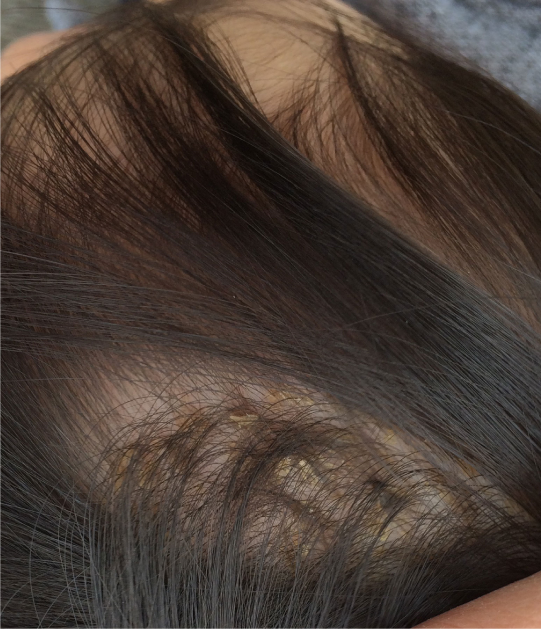 In addition, erythematous, scaly plaques are on the eyebrows, nasolabial folds, and behind the ears. Which of the following is the most likely diagnosis?
 (Multiple Choice)
4.9/5 (71)
(71) A 6-year-old boy is brought to the office with a 10-day history of thick and persistent nasal discharge, nasal congestion, and cough. He has had no associated vomiting, headache, or earache. The patient has mild, persistent asthma for which he uses an inhaled corticosteroid. Temperature is 37.2 C (98.9 F), pulse is 90/min, and respirations are 15/min. Physical examination reveals yellow mucus dripping in the posterior nasopharynx. Tympanic membranes are clear bilaterally. Nasal turbinates are red and swollen. Maxillary sinuses are tender to palpation. Heart sounds are normal and the lungs are clear to auscultation bilaterally. Skin examination shows no rashes. Which of the following organisms is the most likely cause of this patient's condition?
(Multiple Choice)
4.8/5 (95)
(95) A 1-day-old boy is admitted to the neonatal intensive care unit due to microcephaly. Microcephaly and ventriculomegaly were first seen during an antenatal sonogram at 20 weeks gestation. Follow-up ultrasounds revealed progressive fetal growth restriction for which a cesarean delivery was performed at 35 weeks gestation. The mother is a 28-year-old woman, gravida 3 para 3, who is healthy and took prenatal vitamins. The infant's 2 siblings, age 18 months and 4 years, are healthy. Weight and length are at the 5th percentile, and head circumference is <3rd percentile. Temperature is 37.2 C (99 F), and the remaining vital signs are normal. Physical examination shows a jaundiced infant who is small for gestational age. The lungs are clear to auscultation, and no murmurs are audible. The liver edge is palpable at the level of the umbilicus. Platelet count is 25,000/mm3. CT scan of the head is shown below. 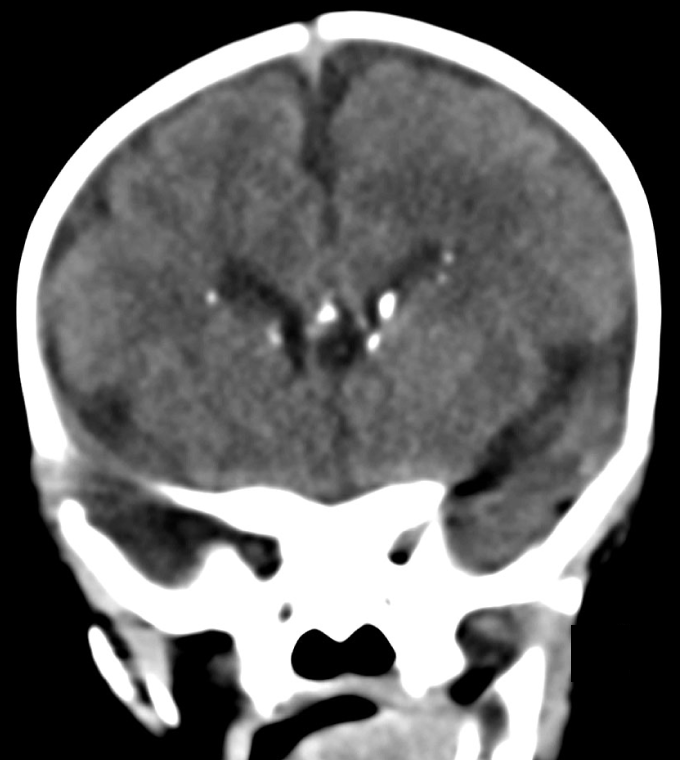 The most likely source of congenital infection is maternal exposure to which of the following?
 (Multiple Choice)
4.9/5 (67)
(67) A 4-year-old boy is brought to the clinic due to sore throat. He first became ill 2 days ago with fever and rhinorrhea. This morning, he developed a severe sore throat and refused to eat his midmorning snack. The patient has type 1 diabetes mellitus and has been hospitalized twice in the last year for diabetic ketoacidosis. He has had no childhood vaccinations. His mother is a smoker and often smokes cigarettes inside the house. The patient is at the 50th percentile for height and 99th percentile for weight. Temperature is 39.4 C (103 F). While sitting on the examination table, the patient appears distressed and leans forward with his chin thrust forward. Tympanic membranes are clear. Oropharyngeal examination shows multiple dental caries. The tonsils are mildly erythematous and 1+ bilaterally. The submandibular space and neck are soft. Lung examination reveals no wheezes or crackles. Which of the following is the most likely risk factor for this patient's current condition?
(Multiple Choice)
4.7/5 (74)
(74) A 67-year-old man is brought to the emergency department due to right-sided weakness, numbness, and slurred speech. The patient was in his usual state of health last night but awoke this morning with these symptoms. He has a history of hypertension, hyperlipidemia, type 2 diabetes mellitus, and peripheral arterial disease. The patient does not drink alcohol regularly but has a 45-pack-year history. Physical examination shows an awake and alert patient with right-sided weakness, hemisensory loss, homonymous hemianopsia, and aphasia. CT scan of the head reveals a large left hemispheric infarction due to an occluded middle cerebral artery. The patient is hospitalized but is not treated with fibrinolytic therapy or mechanical thrombectomy due to ineligibility. Forty-eight hours later, he becomes obtunded. Temperature is 38.3 C (100.9 F), blood pressure is 154/86 mm Hg, and pulse is 64/min. Physical examination now shows complete right hemiplegia and deviation of the eyes to the left. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (77)
(77) A 4-year-old boy is brought to the office due to a rash. Four days ago, the patient developed a localized rash consisting of a few small, round spots on his left foot. Over the next 2 days, some of the spots developed into pustules, and the affected area appeared slightly moist. The rash is mildly itchy and painful. His sister, with whom he shares a room, has also developed a few small, round spots on her hands. The patient has atopic dermatitis and intermittent asthma, for which he uses over-the-counter emollients and albuterol as needed, respectively. Vital signs are normal. Physical examination shows 5-7 small papules and pustules on the left dorsal foot. Some lesions are covered with a transparent, yellow crusting. There is no induration or streaking erythema. The rest of the examination is normal. Which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.8/5 (83)
(83) An 8-year-old boy is brought to the office for evaluation of heel pain. The patient has had increasing pain in the back of his heels for the past 2 months during basketball season. The pain was tolerable until a recent 3-day basketball tournament, which exacerbated his heel pain. He has no pain in other joints and does not recall a specific injury. The patient has no chronic medical conditions and takes no daily medications. Temperature is 36.7 C (98 F). He is at the 98th percentile for height and the 55th percentile for weight. The patient has a normal gait but is unable to stand directly on his heels without pain. Bilateral heels have mild swelling, and the bases of both are tender to palpation. Dorsiflexion of the ankle elicits pain. The Achilles tendon is nontender. Which of the following is the most likely cause of this patient's heel pain?
(Multiple Choice)
4.9/5 (88)
(88) An 8-year-old boy is brought to the emergency department due to worsening abdominal pain for a day. He has vomited twice but has had neither fever nor diarrhea. The patient has had no previous abdominal pain or trauma. Vital signs are unremarkable. Examination shows scleral icterus and epigastric tenderness. An abdominal mass is palpable in the right upper quadrant. Laboratory results are as follows:  Ultrasonography reveals an extrahepatic cystic mass and a normal gallbladder. Which of the following is the most likely underlying cause of this patient's presentation?
 (Multiple Choice)
4.8/5 (81)
(81) A 5-year-old girl is brought to the office for evaluation of pubic hair. Her mother noticed dark hair under the girl's arms and in her pubic area several days ago when helping her bathe. The patient has no headaches, visual changes, abdominal pain, or behavioral changes. She is obese and currently on a diet and exercise program. Several maternal relatives have type 2 diabetes mellitus. The patient's height has been tracking along the 50th percentile and weight at the 97th percentile. Physical examination shows a cooperative girl with mild facial acne. No breast buds are palpable. She has dark, coarse hair across the pubis and under both axillae. External genitalia appear normal. Bone age is normal. Which of the following is the most likely diagnosis for this patient?
(Multiple Choice)
4.8/5 (76)
(76) A 5-year-old girl with chronic renal insufficiency is brought to the physician for a follow-up visit. Since birth, she has had multiple episodes of urinary tract infections, for which she takes trimethoprim-sulfamethoxazole daily for prophylaxis. She has a history of poor growth and mild hypertension but is otherwise developmentally normal. Her mother lost custody of the girl 3 years ago due to failure to comply with recommended treatment and prophylaxis of her infections. The girl has since lived with her grandmother. Examination shows mild bilateral lower-extremity edema but no other abnormalities. Urinalysis shows mild proteinuria but no white blood cells or bacteria. Renal scintigraphy with dimercaptosuccinic acid shows bilateral focal parenchymal scarring and blunted calyces. Which of the following is the most likely predisposing factor for this patient's recurrent infections?
(Multiple Choice)
4.9/5 (70)
(70) An 8-year-old boy is brought to the office by his mother due to difficulties at school. The patient was adopted at age 2 from an orphanage. Medical history is significant for a heart murmur that resolved when he was an infant. His mother says, "His handwriting is illegible and the school wants to keep him back a grade. He has always struggled to sit still and focus; he is clumsy and breaks things without meaning to. He gets upset easily and throws things or hits his brothers when they don't do what he wants." The patient's teacher has reported that he doesn't listen, talks back, and distracts other children. Psychoeducational testing revealed an IQ score of 85. In the office, the boy is playing with a toy. When his mother takes it away, he hits her, starts crying, and becomes difficult to console. Vital signs are within normal limits. Weight and height are tracking at the 30th percentile, but head circumference is below the 10th percentile. Physical examination shows a thin upper lip and short palpebral fissures. Which of the following is the most likely diagnosis?
(Multiple Choice)
4.9/5 (78)
(78) A 10-day-old boy is brought to the emergency department by his mother due to persistent bilious vomiting for 10 hours. The patient has also been more irritable and has refused to feed. His last bowel movement was 24 hours ago. The patient was born at term via vaginal delivery with no prenatal or neonatal complications. Apgar scores were 8 and 9 at 1 and 5 minutes, respectively. Temperature is 37.9 C (100.2 F), blood pressure is 68/36 mm Hg, and pulse is 176/min. The patient appears lethargic. The fontanelles are open and flat. The neck is supple. The abdomen is firm and distended with hypoactive bowel sounds and tenderness to palpation. Rectal tone is normal, and there is a small amount of stool in the rectal vault. Stool testing is positive for occult blood. Plain abdominal x-ray is shown in the exhibit. 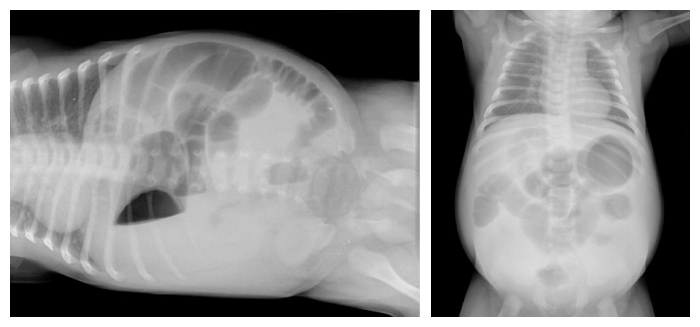 Which of the following is the best next step in management of this patient?
 (Multiple Choice)
4.9/5 (91)
(91) An 18-year-old man is evaluated due to worsening headaches. For the last several months, the patient has had intermittent, dull, occipital headaches, which are often brought on by physical activity, cough, or straining. The pain is usually accompanied by nausea and dizziness, and the symptoms spontaneously resolve after several minutes. There is no history of fever, chills, photophobia, vision disturbances, or focal weakness or numbness. He has no prior medical conditions and takes no medications. Vital signs are normal. Physical examination, including neurologic examination, shows no abnormalities. MRI of the head is shown in the image below: 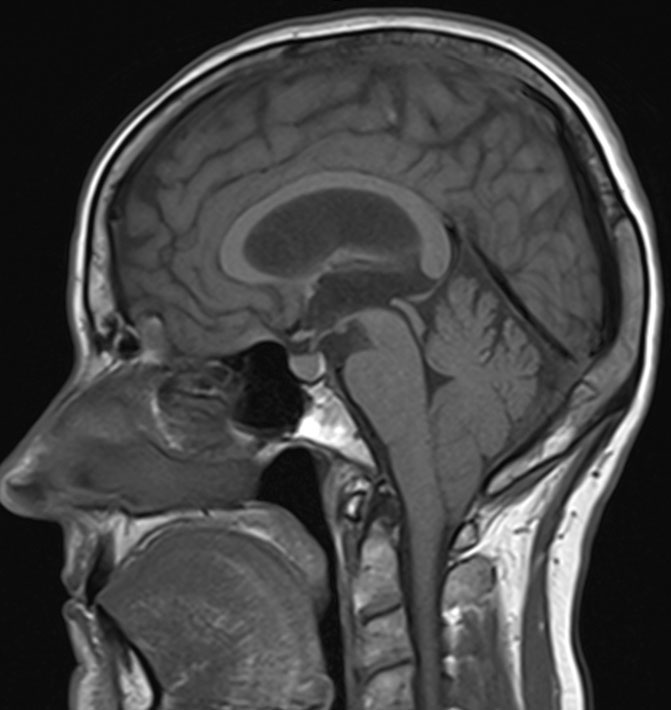 This patient is at greatest risk for which of the following in association with his current condition?
 (Multiple Choice)
4.9/5 (90)
(90) A 29-year-old woman with a history of epilepsy is brought to the emergency department 30 minutes after a seizure. The patient was at a party where she had consumed alcohol when she experienced a generalized tonic-clonic seizure. She had another brief seizure in the ambulance. On arrival, the patient is stuporous and not following instructions and withdraws all extremities from painful stimuli. While being evaluated, she has another seizure that terminates after a dose of intravenous lorazepam is administered. Serum chemistry panel is normal, CT scan of the head reveals no abnormalities, and blood alcohol level is 0.06%. Serum levetiracetam level, which she takes at home, is subtherapeutic, and an additional dose is administered. The patient has no further seizure activity but remains unresponsive an hour after treatment. In addition to continued supportive care, which of the following is the most appropriate next step in management of this patient?
(Multiple Choice)
4.7/5 (85)
(85) A 12-month-old baby girl is brought to the office because of vomiting and diarrhea. She became ill 3 days ago when she developed a low-grade fever and diarrhea. She refuses to eat, but was drinking some liquids until yesterday when she began vomiting. In the last 24 hours, she has had 1 wet diaper. Temperature is 38 C (100.4 F), blood pressure is 90/50 mm Hg, pulse is 110/min, and respirations are 25/min. On examination, she is lethargic with sunken eyes. Her mucous membranes are dry and her capillary refill is 3-4 seconds. Which of the following is the next best step in the management of this patient?
(Multiple Choice)
4.8/5 (77)
(77) An 18-month-old boy is brought to the office by his mother for a checkup. The patient was born at full term without complications. Growth has been consistently along the 80th percentile for height and weight. The mother reports, "He is healthy and seems happy just playing by himself, but I am concerned about him not talking." She says that he makes some sounds that are unintelligible, has a 1-word vocabulary of "no," and does not yet say "mama," "dada," or "bye-bye." The patient is able to walk and is starting to run. He can scribble and with help can use a spoon to feed himself. On examination, he does not make eye contact, respond to his name, or follow the doctor's gaze when toys are pointed out to him. Hearing testing is normal. Which of the following is the most likely explanation for the patient's behavior?
(Multiple Choice)
4.8/5 (79)
(79) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)