



 Chat with AI
Exam 2: Pediatric

Exam 1: Medicine2 k Questions
Exam 2: Pediatric723 Questions
Exam 3: Psychiatry336 Questions
Exam 4: Surgery563 Questions
Exam 5: Obstetrics & Gynecology469 Questions
Select questions type


An 18-month-old boy is brought to the emergency department due to fatigue. Yesterday, his mother noticed that he was less active, and this morning, he did not want to get out of bed. The patient was born in Uganda, and the family recently moved to the United States. Temperature is 37 C (98.6 F), blood pressure is 74/40 mm Hg, pulse is 190/min, and respirations are 30/min. The patient appears tired. Eye examination shows equal and reactive pupils with bilateral scleral icterus. The oropharynx is clear, and the oral mucosa is pale. The neck is supple, and there are several 1-cm, anterior cervical lymph nodes. The lungs are clear bilaterally, and cardiac examination reveals a 2/6 systolic ejection murmur. Abdominal examination reveals tenderness on the left side. The spleen is palpable at the level of the umbilicus; the liver is not palpable. Bilateral distal pulses are weak. Which of the following would most likely establish this patient's diagnosis?
(Multiple Choice)
4.8/5  (76)
(76) A 6-year-old boy is brought to the office by his mother due to fever, pruritic rash, and joint pain. The rash began 2 days ago and has spread to his trunk and arms. The patient has also had pain in the wrists and ankles. He was diagnosed with streptococcal pharyngitis 9 days ago and is on his second to last day of oral penicillin. Temperature is 38.8 C (101.8 F). Physical examination shows an uncomfortable-appearing boy with a diffuse rash on the arms and back. There are palpable lymph nodes in the cervical, axillary, and inguinal regions. The wrists and ankles are tender to palpation but are not swollen or erythematous. The remainder of the physical examination is normal. Which of the following is the most likely diagnosis?
(Multiple Choice)
4.9/5 (74)
(74) A 14-year-old boy is brought to the office due to right groin pain. Three months ago, the patient developed intermittent right groin pain while playing soccer. Despite stretching exercises, the pain worsened. In the past 4 weeks, he developed a limp and has had difficulty climbing stairs at home. The patient has had no fever, night sweats, or weight loss; there has been no trauma. Vital signs are normal. Height and weight have been tracking along the 75th and 10th percentiles, respectively. On examination, mild atrophy of the right quadriceps and gluteal muscles is present. When the patient stands with the feet together, the right foot points outward and the left foot points straight ahead. When he stands on the right leg, the left half of the pelvis drops downward. When he stands on the left leg, the pelvis remains level. Knees have full range of active motion. Strength on knee extension is 5/5 on the left and 4/5 on the right. Sensation in both legs is intact. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.7/5 (68)
(68) A 5-month-old girl is brought to the physician for a weight check. The patient has been evaluated several times for poor weight gain. She takes 6 ounces of regular formula every 4 hours. Increasing the caloric density of her formula has not improved her growth. The patient has no diarrhea or vomiting. There is a family history of nephrolithiasis. She was born full term without complications. The patient's birth weight was 3.6 kg (8 lb, 50th percentile). Current weight is <5th percentile; length and head circumference have been tracking along the 25th percentile. The infant appears thin, but the remainder of the physical examination is unremarkable. Newborn screening results were normal. Laboratory results are as follows:  Which of the following is the most likely cause of this patient's failure to thrive?
 (Multiple Choice)
4.9/5 (81)
(81) A 74-year-old woman is brought to the emergency department due to worsening weakness and gait unsteadiness. The patient has a history of ischemic stroke causing right-sided weakness and uses a cane to ambulate. Over the past several days, she has been feeling weak and unsteady, and this morning she fell while getting out of bed. She did not lose consciousness and has had no headache, vomiting, or vision loss. The patient recently has had dysuria and urinary urgency, which have improved after taking trimethoprim-sulfamethoxazole. Other medical conditions include hypertension, type 2 diabetes mellitus, and seizure disorder controlled with phenytoin. Temperature is 37.1 C (98.8 F), blood pressure is 140/86 mm Hg, and pulse is 84/min. Pupils are equal and briskly reactive, and extraocular movements are intact. There is bilateral nystagmus on lateral gaze. Muscle strength is diffusely decreased but more pronounced in the right extremities. Deep tendon reflexes are increased throughout. Dysmetria is present on finger-nose testing, and the gait is wide-based. Which of the following is the most likely cause of this patient's current condition?
(Multiple Choice)
4.8/5 (83)
(83) An 18-month-old girl is brought to the emergency department after having a seizure in day care. The staff reports that "she suddenly fell down and started shaking," but they also note that the patient has seemed quieter and has repeatedly pulled at her hair over the past month. The patient's mother says, "My daughter used to say 'mama' and 'papa' and babble away but has begun to talk less in the past few months. She's also become more needy, wanting me to feed her rather than using a spoon herself." Medical history is significant for 3 ear infections in the past year and another seizure thought to have been febrile in origin. Family history is significant for early-onset Alzheimer disease in the patient's paternal grandfather and retinoblastoma in a paternal cousin. The patient is afebrile, and other vital signs are normal. On physical examination, the patient makes eye contact with the physician but speaks no words. She is noted to have a lurching gait. Which of the following would most likely establish a diagnosis in this patient?
(Multiple Choice)
4.8/5 (86)
(86) A 1-month-old girl is brought to the office for a routine well-child visit. The patient has no symptoms and is feeding well. Weight and length are stable at the 45th percentile. Pulse is 120/min, and respirations are 35/min. Oxygen saturation is 97% on room air. She is breathing comfortably without retractions or grunting. There is no cyanosis. Jugular venous pressure is not elevated. The lungs are clear to auscultation. A grade 3/6 holosystolic murmur and a systolic thrill are present at the left lower sternal border. Blood pressure is 80/40 mm Hg in her right arm and 78/38 mm Hg in her right leg. A chest x-ray reveals an enlarged left heart contour. What is the most likely cause of this patient's x-ray findings?
(Multiple Choice)
5.0/5 (85)
(85) A 2-week-old girl in the neonatal intensive care unit for prematurity is evaluated for increasing episodes of apnea and bradycardia over the past 3 hours. The patient was born at 29 weeks gestation via vaginal delivery; birth weight was 1.02 kg (2 lb 4 oz). She has been receiving enteral feeds via nasogastric tube with premature formula. Temperature is 36.1 C (97 F), blood pressure is 76/42 mm Hg, pulse is 150/min, and respirations are 44/min. Pulse oximetry is 96% on room air. The patient appears lethargic. There is no cyanosis, stridor, or intercostal retractions. The lungs are clear to auscultation bilaterally. Heart sounds are normal with no gallops or heart murmur. There is mild abdominal distension. The extremities are well perfused. Laboratory results are as follows:  Which of the following is the best next step in management?
 (Multiple Choice)
4.9/5 (73)
(73) A 45-year-old woman comes to the office due to tremor in her hands. She has had an on-and-off tremor for several years, especially when she becomes stressed; however, over the past 6 weeks, the tremor has persisted and become more severe. The patient has no other symptoms. Medical history is significant for generalized anxiety disorder, for which she has been taking sertraline for 2 months. The patient does not drink alcohol. There is no family history of tremor or neurologic conditions. Temperature is 36.8 C (98.2 F), blood pressure is 130/84 mm Hg, pulse is 82/min, and respirations are 16/min. Physical examination shows a high-frequency tremor of both hands that is prominent with finger-to-nose testing. The tremor is not relieved with distraction. The remainder of the examination is normal. Complete blood count, serum chemistry profile, and serum TSH are normal. What is the most likely diagnosis?
(Multiple Choice)
4.8/5 (78)
(78) An 18-month-old boy is brought to the office due to developmental concerns. His parents have noticed that he does not walk independently, which worries them because his older brother began walking at age 12 months. The patient holds on to furniture while standing and steps sideways to move around. He can speak in 2- to 3-word sentences and follow simple commands. The patient can also build a tower of 6 cubes, drink from a straw, and feed himself table foods. Height, weight, and head circumference track at the 20th percentile, similar to prior visits. During physical examination, he uses his hands to push on his legs while getting up and seems to have pain when doing so. Which of the following is the best next step in evaluation of this patient?
(Multiple Choice)
4.9/5 (64)
(64) A 15-year-old boy with cystic fibrosis is brought to the emergency department for epistaxis. He first noticed intermittent nose bleeds a few days ago after a week of nasal congestion with low-grade fever. The bleeding worsened today and has been difficult to control. The patient has also had easy bruising for the past 2 months. He has not been taking his prescribed medications. Temperature is 37 C (98.6 F), blood pressure is 108/72 mm Hg, pulse is 90/min, and respirations are 18/min. The patient is alert and cooperative. There is active bleeding from the left naris. The pupils are equal and reactive. Breath sounds are coarse bilaterally, and cardiac examination is unremarkable. The abdomen is soft and nontender with no organomegaly. Strength and sensations are 5/5. Reflexes are equal bilaterally, and gait appears normal. Skin examination shows diffuse bruises along the extremities. Which of the following is the most likely cause of this patient's symptoms?
(Multiple Choice)
4.7/5 (83)
(83) A 20-year-old college student comes to the office due to worsening abnormal movements. The symptoms initially started in middle school when he would repeatedly blink and then shrug his shoulders. The patient worked with a counselor who taught him techniques to suppress movements for periods of time, although these did not completely resolve them. Over the past few years, the symptoms have gradually worsened. Episodes now occur multiple times daily, particularly around highly stressful times at school. His grades have declined, and he is embarrassed during class presentations. The patient has no history of serious illness and takes no medications. He occasionally smokes marijuana on weekends. Family history is notable for the death of his father at age 50 from a stroke. Vital signs are normal. During the examination, the patient is visibly anxious. He repeatedly blinks, clears his throat, and shrugs his shoulders. The remainder of the physical examination shows no abnormalities. Which of the following is the most appropriate treatment for this patient?
(Multiple Choice)
4.7/5 (78)
(78) A 4-month-old boy is brought to the office by his mother for a routine examination. This is the patient's first visit as the mother recently moved to the area. Review of medical records shows that the only parental concerns at age 2 months were excessive gassiness and spitting up, both of which have resolved. The patient was born full term and has no chronic medical conditions. Vaccinations are up to date. His parents recently divorced, and he now lives with his mother and 9-year-old sister. The sister has attention-deficit hyperactivity disorder and anxiety. The patient's height and weight are at the 50th and 75th percentiles, respectively. On physical examination, he is smiling and reaching for the examiner's stethoscope. He holds his bottle for a few seconds and then drops it on the ground. The patient can sit with support and roll from front to back. Flat, nonblanching, nontender patches over his sacrum and buttocks are shown in the image below. 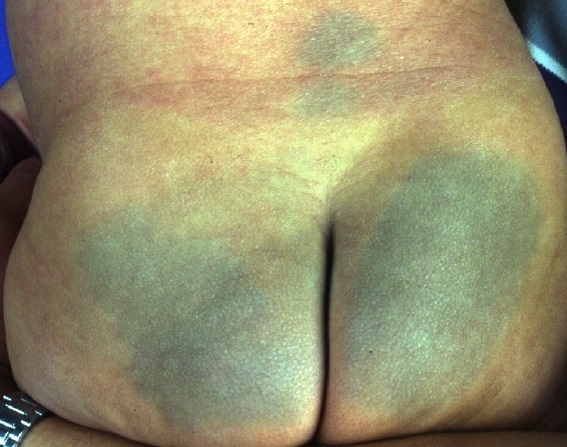 Which of the following is the most appropriate next step in management of this patient?
 (Multiple Choice)
4.8/5 (72)
(72) A 4-year-old boy with sickle cell disease is brought to the emergency department by his parents due to a progressive headache and drowsiness. While coming down the stairs, the patient slipped and fell from a height of 1.5 m (5 ft), hitting his head on the tile floor. He lay on the ground for several seconds but got up and continued walking and talking normally. The patient initially had only mild pain at the injury site. A few minutes later, he developed a progressive headache and vomiting before becoming somnolent. The patient has been hospitalized multiples times for vasoocclusive crises. He takes hydroxyurea and penicillin daily. Blood pressure is 140/86 mm Hg and pulse is 66/min. The patient is sleepy and requires painful stimuli to remain awake. On neurologic examination, the left pupil is 3 mm with normal pupillary reflex, but the right pupil is 8 mm and unreactive to light. Which of the following is the most likely cause of this patient's acute decompensation?
(Multiple Choice)
4.7/5 (87)
(87) A 5-month-old boy is brought to the clinic due to fever and irritability. Over the past 48 hours, the patient has been less interested in drinking formula, although he still produces an adequate number of wet diapers each day. He woke up crying several times last night and developed a fever this morning. The patient was born at term following an uncomplicated pregnancy and has met all developmental milestones. Temperature is 38.3 C (100.9 F), blood pressure is 89/50 mm Hg, pulse is 135/min, and respiratory rate is 28/min. On examination, the patient is fussy but consolable in his parent's arms. Heart and lung examinations are unremarkable. There is clear rhinorrhea from the nares bilaterally. Otoscopic examination shows erythematous, bulging tympanic membranes bilaterally. Which of the following pieces of additional history is most relevant to this patient's condition?
(Multiple Choice)
4.9/5 (73)
(73) A 3-year-old girl with a history of asthma is brought to the clinic for follow-up. Five days ago, the patient had a choking episode during a meal. She subsequently developed persistent cough and wheezing and was taken to the emergency department the same day. The wheezing improved with 3 treatments of nebulized albuterol, and chest radiograph was unremarkable. The patient was discharged with instructions to continue the albuterol and begin oral corticosteroids. She finished her corticosteroid course this morning, but the cough has persisted despite albuterol use. The patient has had no fever, congestion, or rhinorrhea. Vital signs are normal. The oropharynx is clear. Lung examination shows symmetric chest expansion, with diminished breath sounds and a faint wheeze in the right middle lobe. There are no crackles. The left lung is clear. Cardiac examination is unremarkable. Pulses are 2+ bilaterally. The abdomen is soft and nontender. Skin examination shows no rashes. Repeat chest radiograph is unchanged. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.8/5 (91)
(91) A 15-year-old boy is brought to the office by his parents due to worsening articulation and gait instability. His parents say that his speech has been increasingly difficult to understand over the last 2 months, but he has had no difficulty with comprehension. The patient has also had progressive gait instability over the last month. He is falling more frequently and had to quit his basketball team. He has no chronic medical problems or allergies. The patient takes no medications and does not use alcohol or illicit drugs. Blood pressure is 120/70 mm Hg and pulse is 80/min. Musculoskeletal examination shows scoliosis. Neurologic examination reveals dysarthria and a wide-based, unstable gait. There are absent deep tendon reflexes of the bilateral lower extremities. MRI of the brain and spinal cord shows marked atrophy of the medulla and dorsal columns of the spinal cord. This patient is at greatest risk of mortality from which of the following conditions?
(Multiple Choice)
4.9/5 (81)
(81) A 15-year-old girl is brought to the office by her mother due to hair loss. The patient was cast in the lead role of the school play a month ago and has been wearing hats and wigs to stay in character. A few days ago, her mother noticed several bald spots on the patient's scalp. The patient does well in school and enjoys rehearsals. She does not use alcohol or illicit drugs. Menarche was at age 13; menstruation occurs every 4-6 weeks and typically lasts 5-7 days. Vital signs are normal. BMI is 22 kg/m2. Physical examination shows a 3 × 5 cm area of patchy hair loss in the right parietal region surrounded by several areas of uneven hair growth. Eyebrows are sparse. Scalp and skin examination shows no scaling or erythema. Physical examination is otherwise unremarkable. Which of the following is the most likely diagnosis in this patient?
(Multiple Choice)
4.8/5 (87)
(87) A 1-year-old boy is brought to the clinic due to poor weight gain. The patient's mother is concerned that he is smaller than children of the same age. He drinks 600 mL (20 oz) of whole milk daily and eats table food such as meats, fruits, and grains 3 times a day. Since the introduction of solid foods, the child has had an increase in bulky bowel movements, occurring 5-6 times daily. The patient also has frequent coughing episodes. He has not had any previous surgeries. The family lives in a rural area. Temperature is 37.1 C (98.8 F), pulse is 120/min, and respirations are 24/min. Physical examination shows a thin but active child. The oropharynx is clear, and there is no cervical lymphadenopathy. Pulmonary examination reveals a wet cough with bilateral rhonchi. The abdomen is soft with no organomegaly. Growth chart shows: 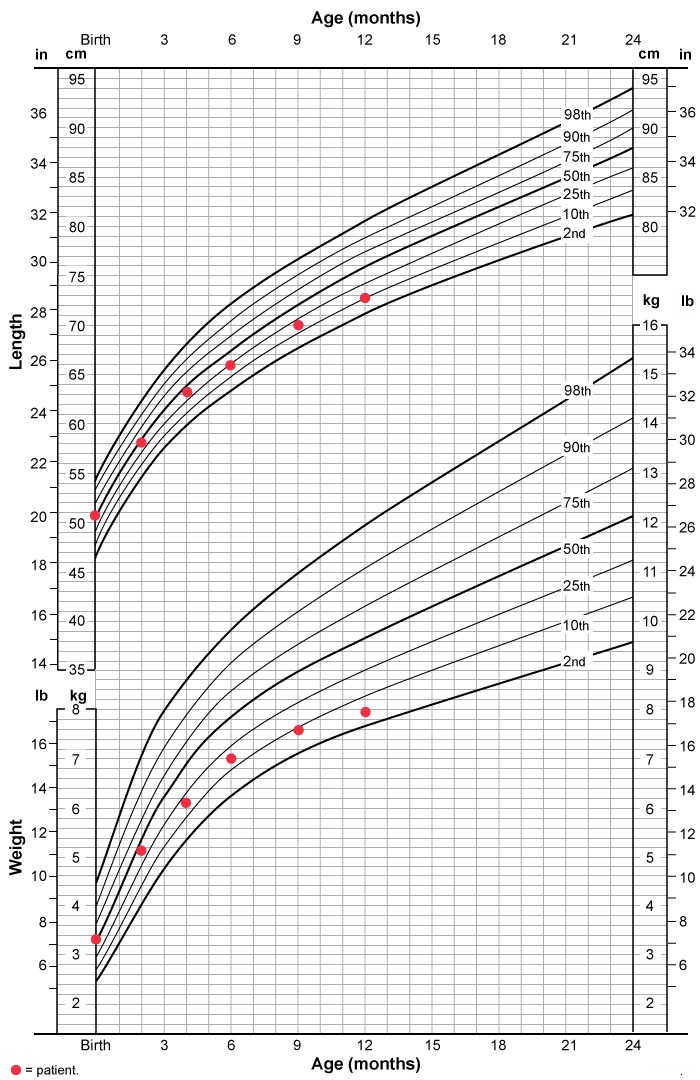 Which of the following is the most likely cause of this patient's symptoms?
 (Multiple Choice)
4.8/5 (70)
(70) A newborn girl born at 37 weeks gestation after an uncomplicated vaginal delivery is evaluated due to poor tone of the lower extremities. She is not moving her legs and does not respond to heel prick. Deep tendon reflexes are 1+ in the lower extremities. Cervical spine range of motion and upper extremity examination are normal. A hemangioma is present over the midline lumbosacral area. Apgar scores were 7 and 9 at 1 and 5 minutes, respectively. Which of the following is the most likely diagnosis?
(Multiple Choice)
5.0/5 (87)
(87) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)