



 Chat with AI
Exam 2: Foundations of Independent Practice

Exam 1: Advanced Clinical Medicine1 k+ Questions
Exam 2: Foundations of Independent Practice597 Questions
Select questions type


A 30-year-old nulliparous woman comes to the office due to amenorrhea. Shortly after menarche at age 15, the patient began taking combined estrogen/progestin oral contraceptives for irregular menstrual cycles. While she was using contraception, her menstrual periods occurred every 28 days and consisted of 3-4 days of light bleeding. The patient stopped using contraception a year ago to conceive, and since then has not had a menstrual period. She has hot flashes several times a day and often awakens at night with profuse sweating. The patient has no chronic medical conditions and has had no previous surgeries. She takes a daily multivitamin and acetaminophen occasionally for headaches. Her sister (age 40) has 2 children and has regular monthly menses. Blood pressure is 110/70 mm Hg, weight is 65 kg (143.3 lb), and height is 152.5 cm (5 ft). Laboratory results are as follows:  Pelvic ultrasound shows a normal uterus with a thin endometrial stripe and small ovaries bilaterally. Which of the following is the best next step in diagnosis of this patient's condition?
 (Multiple Choice)
4.7/5  (96)
(96) A 74-year-old man is brought to the emergency department after being involved in a major motor vehicle collision. According to the report from paramedics, he was a restrained passenger. The patient has superficial injuries to the lower extremities and blunt chest trauma. He has pain "all over" but is answering all questions appropriately. Initial blood pressure is 98/65 mm Hg, pulse is 105/min, and respirations are 18/min. Oxygen saturation is 100% on 40% oxygen via face mask. Examination shows some bruises over the anterior chest, clear lungs, and no murmurs or abnormal heart sounds. The abdomen is soft and nontender. Which of the following is the most appropriate next step in evaluation of this patient?
(Multiple Choice)
4.9/5 (77)
(77) A 28-year-old woman comes to the emergency department due to the abrupt onset of palpitations that started while she was watching television. She says, "I suddenly started to feel like my heart was racing." The patient describes mild lightheadedness but no chest pain, shortness of breath, or syncope. In the past, she has experienced similar episodes of palpitations that were nonsustained and terminated abruptly. The patient has never sought medical care for these episodes and cannot identify any provoking factor. She saw a physician for anxiety when she was a teenager but does not remember if she received any therapy. The patient has no other medical problems and takes no medications. She does not use tobacco, alcohol, or illicit drugs. She jogs 2-3 miles a day. The patient has no family history of coronary artery disease, cardiomyopathy, blood clots, or sudden cardiac death. She appears mildly uncomfortable but not in any respiratory distress. Temperature is 36.7 C (98 F), blood pressure is 100/60 mm Hg, pulse is 172/min, and respirations are 20/min. Urine pregnancy test is negative. ECG is shown in the exhibit. The patient receives antiarrhythmic therapy, and her pulse immediately decreases from 172/min to 68/min. The palpitations resolve, and she states that she feels "normal now." Cardiac examination reveals no murmurs or additional sounds. A 12-lead ECG is performed and is shown in the exhibit. 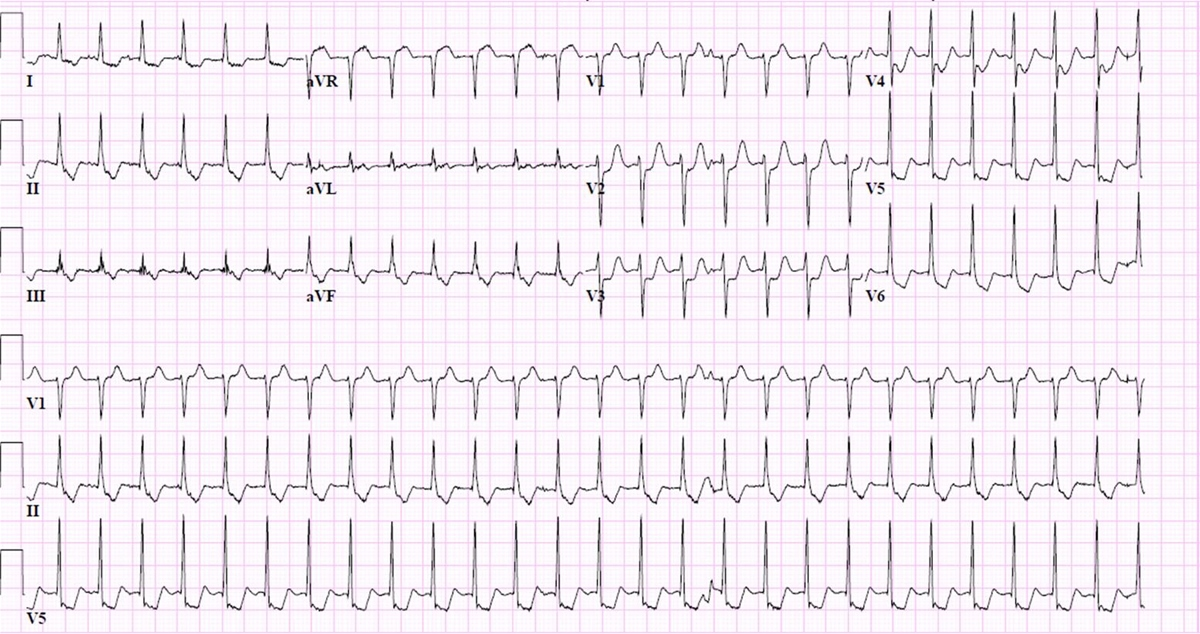 Which of the following is the most likely diagnosis?
 (Multiple Choice)
4.9/5 (73)
(73) A study examines the relationship between urine sodium excretion and systolic blood pressure in a large cohort of patients from several countries. The following results are reported for change in systolic blood pressure for every 1-g increase in urine sodium excretion: Which of the following best describes the study results?
(Multiple Choice)
4.9/5 (62)
(62) A 62-year-old man comes to the office due to a 2-month history of progressive exertional dyspnea and fatigue. The patient says, "I feel tired all the time and take frequent naps during the day." He consumes a balanced diet and does not use tobacco, alcohol, or illicit drugs. Physical examination shows mucosal pallor. Stool testing for occult blood is positive. Laboratory results are as follows:  Colonoscopy reveals several small, flat, cherry-red lesions in the right colon but is otherwise normal. Esophagogastroduodenoscopy and capsule endoscopy are normal. The likely cause of this patient's anemia is most strongly associated with which of the following?
 (Multiple Choice)
4.8/5 (76)
(76) A 35-year-old woman comes to the office for evaluation. Her medical problems include migraine headaches, chronic back pain, asthma, and depression. The patient has had extensive diagnostic workup of her back pain, including several imaging studies, that was unrevealing. At today's visit, she is seen by another physician in the same group, as her primary physician is currently on personal leave. The patient is mildly depressed and reports continued headaches and back pain. During the course of the appointment, the patient discloses that her primary physician asks her to undress at every visit so he can examine her breasts. She also mentions that they were in a consensual sexual relationship that she stopped because the physician was not willing to divorce his wife to be with her. The treating physician contacts the patient's primary physician to discuss concerns about the patient's report. The primary physician admits to a brief sexual relationship over a year ago when he first began treating her as a patient. However, he denies there has ever been any inappropriate behavior in the office, stating, "She is a psych patient and is always upset; you can't trust what she is saying." Which of the following is the best next course of action?
(Multiple Choice)
4.8/5 (84)
(84) A 72-year-old Caucasian man is brought to the emergency department (ED) due to a sudden onset of severe difficulty in breathing. He has chronic obstructive pulmonary disease, and is on 2 liters of oxygen at all times. While in the ED, he develops progressive hypoxic respiratory failure, and is intubated by the ED physician. His son comes to the hospital an hour later, and gets very upset. He pulls you to one side of the room and says, "Please remove the tube. He never wanted to live like this." The patient does not have any advance directives for his health care. He regains consciousness for a few seconds while you were having a discussion with his son, but he was unable to state his wishes regarding life-sustaining treatment.
The patient's whole family shows up in the hospital two hours later. He has two sons and three daughters who appear extremely concerned by the recent events. They all live in the same town and are very close to their parents. The patient lives alone. After prolonged discussions, the two sons agree and wish to proceed with the withdrawal of mechanical ventilation. The daughters are adamant about continuing life-sustaining treatment. The daughters tell you, "Our dad never said that he didn't want to live". Which of the following is the most appropriate next step in the management of this patient?
(Multiple Choice)
4.9/5 (81)
(81) A 63-year-old woman, gravida 3 para 3, comes to the office for urinary incontinence. The patient has been experiencing involuntary leakage of urine that occurs after a strong sensation "that I really have to go." After the sensation occurs, "I can never get to the bathroom in time." The patient reports that her symptoms started over 2 years ago. The leakage was initially occasional but now occurs 2 or 3 times a day and soaks an entire pad. The patient's symptoms occur randomly and she now avoids leaving the house. She has hypertension controlled on an ACE inhibitor. She has had no surgery. The patient's deliveries were all vaginal; her Pap tests have been normal. She drinks 8 ounces of water 3 or 4 times a day but limits water intake in the evening; on weekends she drinks a cup of caffeinated coffee with breakfast. The patient does not use tobacco, alcohol, or illicit drugs. Blood pressure is 130/80 mm Hg and pulse is 72/min. BMI is 23 kg/m2. Speculum examination shows a pale vagina without rugae. Bimanual examination reveals a small, mobile uterus and no adnexal masses. No leakage of urine occurs when the patient coughs with a full bladder. After voiding, the patient is catheterized and 30 mL of urine are drained from the bladder. Urinalysis is within normal limits. The patient returns to the office 10 weeks later for follow-up. She reports no response to the initial therapy. Repeat urinalysis is normal. Which of the following is the best next step in management of this patient?
(Multiple Choice)
4.9/5 (87)
(87) A 16-year-old boy is brought to the emergency department by his mother after a single episode of generalized tonic-clonic seizure. The patient has been staying up late studying for midterm exams and has been feeling "more tired than usual" for the last few days. For the last 6 months, he has had occasional jerking arm movements in the morning but was not medically evaluated as they were brief and he otherwise "felt fine." The patient has had no recent fevers, vomiting, or headaches. He does not use alcohol or illicit drugs. His mother describes him as "anxious," but he has no chronic medical conditions and takes no medications. Temperature is 37.2 C (99 F), blood pressure is 120/60 mm Hg, and pulse is 72/min. On physical examination, the patient is drowsy but responsive to commands and oriented to person, place, and time. Cardiac examination reveals a regular rate and rhythm without murmurs. Cranial nerves II-XII are intact; there are no focal deficits. Deep tendon reflexes are normal in the upper and lower extremities, and plantar responses are flexor. There are no rashes or petechiae. Electroencephalogram shows bilateral polyspike and slow wave discharges.
Which of the following is the best next step in management of this patient's condition?
(Multiple Choice)
5.0/5 (73)
(73) A 53-year-old man comes to the office due to progressive pain and stiffness in his hands for the past several months. The patient's symptoms are worse in the morning, and he has difficulty shaving or holding a coffee cup. The stiffness lasts for about 15 minutes and the pain gradually improves through the course of the day, but he often has to take acetaminophen for complete relief. For the past 3 weeks, he has experienced pain in the left knee, especially after prolonged rest. The patient has also had progressive fatigue over the past year. Medical history is notable for type 2 diabetes mellitus, which was diagnosed 6 months ago and is treated with metformin. He works as a sales representative and does not use tobacco, alcohol, or illicit drugs. Family history is remarkable for diabetes mellitus in his father. Temperature is 37.1 C (98.8 F), blood pressure is 126/78 mm Hg, and pulse is 82/min. Physical examination shows normal jugular venous pressure, clear lung fields, and normal heart sounds. The abdomen is nondistended, soft, and nontender. The liver is palpable 1 cm below the right costal margin. There is moderate swelling, warmth, and mild tenderness and decreased range of motion of the second and third metacarpophalangeal joints in both hands. A small effusion and tenderness of the left knee is present without any redness. Radiography of the hand reveals narrowing of the joint space, particularly of the second and third metacarpophalangeal joints, along with subchondral sclerosis, curved osteophytes, subchondral cysts, and osteopenia. An arthrocentesis of the knee is performed, and the synovial fluid analysis shows a leukocyte count of 20,000 cells/mm3 with 80% neutrophils. Gram stain shows no organisms, and polarization microscopy reveals positively birefringent rhomboid-shaped crystals. Additional studies are performed and the diagnosis is established. If this patient's current condition remains untreated, he is at greatest risk for which of the following?
(Multiple Choice)
4.8/5 (82)
(82) A 53-year-old man comes to the office due to progressive pain and stiffness in his hands for the past several months. The patient's symptoms are worse in the morning, and he has difficulty shaving or holding a coffee cup. The stiffness lasts for about 15 minutes and the pain gradually improves through the course of the day, but he often has to take acetaminophen for complete relief. For the past 3 weeks, he has experienced pain in the left knee, especially after prolonged rest. The patient has also had progressive fatigue over the past year. Medical history is notable for type 2 diabetes mellitus, which was diagnosed 6 months ago and is treated with metformin. He works as a sales representative and does not use tobacco, alcohol, or illicit drugs. Family history is remarkable for diabetes mellitus in his father. Temperature is 37.1 C (98.8 F), blood pressure is 126/78 mm Hg, and pulse is 82/min. Physical examination shows normal jugular venous pressure, clear lung fields, and normal heart sounds. The abdomen is nondistended, soft, and nontender. The liver is palpable 1 cm below the right costal margin. There is moderate swelling, warmth, and mild tenderness and decreased range of motion of the second and third metacarpophalangeal joints in both hands. A small effusion and tenderness of the left knee is present without any redness. Radiography of the hand reveals narrowing of the joint space, particularly of the second and third metacarpophalangeal joints, along with subchondral sclerosis, curved osteophytes, subchondral cysts, and osteopenia. An arthrocentesis of the knee is performed, and the synovial fluid analysis shows a leukocyte count of 20,000 cells/mm3 with 80% neutrophils. Gram stain shows no organisms, and polarization microscopy reveals positively birefringent rhomboid-shaped crystals.
Which of the following is the most likely cause of this patient's joint pain?
(Multiple Choice)
4.8/5 (93)
(93) A 32-year-old unemployed woman with type I diabetes mellitus comes to the physician at a free clinic serving patients of low socioeconomic status. Despite compliance with her insulin regimen, she continues to have difficulty controlling her diabetes. Her recent HgbA1C was 9% and her home glucose log shows several readings >200 mg/dL and many as low as 50 mg/dL. The patient is very concerned about the possible complications of uncontrolled diabetes. She has been told several times that an insulin pump would help stabilize her glucose levels, but she cannot afford it. Her physician has recently begun enrolling patients in a clinical trial for type I diabetes in which an insulin pump is paid for by the drug company sponsoring the study. The company also provides a small stipend for participating in the trial. Considering the patient's low socioeconomic status and the fact that she cannot afford an insulin pump, what would be appropriate to tell her about the clinical trial?
(Multiple Choice)
4.9/5 (75)
(75) A 34-year-old woman comes to the office after a recent hospitalization. Over the past several months, the patient has had worsening weakness, anorexia, nausea, and abdominal discomfort. Two weeks ago, she had a syncopal episode; evaluation found a low serum cortisol level and subnormal response to ACTH stimulation. The patient was treated in the hospital and was discharged on oral hydrocortisone therapy. Since discharge, she has had intermittent episodes of light-headedness and nausea but reports improvement in other symptoms. Her husband adds that the patient consumes excessive amounts of salty foods. Temperature is 36.9 C (98.4 F), blood pressure is 108/66 mm Hg supine and 98/60 mm Hg upright, and pulse is 88/min supine and 102/min upright. Physical examination reveals hyperpigmentation of the oral mucosa and palmar creases. Cardiopulmonary and abdominal examination shows no abnormalities. Laboratory results are as follows:  Which of the following is the most appropriate next step in management of this patient?
 (Multiple Choice)
4.8/5 (87)
(87) A 52-year-old woman comes to the office for follow-up of long-standing primary hypothyroidism, which has been treated for the past 6 years with a stable dose of levothyroxine 0.125 mg. The patient is very compliant and takes her medication an hour before breakfast every day. Recently, however, she has had increasing weight gain, dry skin, cold intolerance, and lethargy. The patient otherwise feels well and experienced menopause 6 months ago. Laboratory results at that time showed a low serum 25-hydroxyvitamin D level, which improved with oral vitamin D supplementation. She is currently taking over-the-counter calcium and vitamin D supplements every morning with breakfast. Medical history is unremarkable, and family history is positive for osteoporosis in her mother. The patient has a 35-pack-year history of smoking but quit 3 months ago with bupropion as she heard that "smoking increases the risk of bone fractures." She does not use alcohol or illicit drugs. Vital signs and physical examination are normal. Serum TSH is 9 μU/mL; it was 2.3 μU/mL a year ago. Complete blood count and basic chemistry profile are normal. Which of the following is the most appropriate advice for this patient?
(Multiple Choice)
4.9/5 (85)
(85) A 76-year-old woman is brought to the physician by her son. He is concerned that his mother, who was previously outgoing, does not want to leave her home. She lives alone and works as a part-time volunteer at a local library. Although she continues to work shelving books, she has stopped attending her weekly meetings at a senior center where she socialized with friends. The patient also seems quieter and more difficult to engage in conversation when he calls her on the telephone. One week ago, he found her sitting on a chair pulled up close to the television. She did not notice his presence immediately but then smiled and nodded as if following the conversation. He became concerned when she asked about her grandchild's upcoming birthday party even though he had just told her the details. Her past medical history is significant for hypertension. The patient reports that her sleep and appetite are fine. She does not use tobacco, alcohol, or illicit drugs. Her medications include valsartan and hydrochlorothiazide. Which of the following is the most likely diagnosis?
(Multiple Choice)
4.9/5 (71)
(71) A 32-year-old man sustains a midshaft fracture of his left tibia during a motor vehicle accident. The fracture was surgically fixed and stabilized in a plaster cast soon after the patient arrived in the emergency department. Continuous morphine by patient-controlled anesthesia pump was provided for analgesic effect. Sixteen hours after the surgery, the patient complains of significant pain in his left calf. He appears very uncomfortable, is sweating and shifting restlessly in bed, and pleads for better analgesia. He has no other medical problems. His last tetanus toxoid booster shot was 2 years ago. Which of the following is most likely to be present on physical examination?
(Multiple Choice)
4.8/5 (81)
(81) A study is conducted to assess myocardial perfusion imaging performance using a new pharmacologic agent for stress testing. The test is performed on inpatients and outpatients with chest pain. Patients with positive stress test results underwent cardiac catheterization to diagnose flow-limiting coronary artery disease (CAD). Physicians interpreting the catheterization radiographs were blinded to inpatient/outpatient status. The following results are obtained: Inpatients:
Number of patients with positive stress test: 122
Flow-limiting CAD on cardiac catheterization: 102/122 (84%)
Outpatients:
Number of patients with positive stress test: 115
Flow-limiting CAD on cardiac catheterization: 67/115 (58%)
Which of the following best explains the difference in the rate of flow-limiting CAD between the groups in this study?
(Multiple Choice)
4.8/5 (77)
(77) A 4-year-old girl is in the hospital with pyelonephritis. Urine culture shows >100,000 colonies of Klebsiella oxytoca, which is susceptible to all tested antibiotics. After 36 hours of intravenous antibiotics, the patient's temperature decreases from 39.4 C (103 F) to 37.8 C (100 F). She no longer has flank pain or dysuria and is eating and drinking normally. The patient is prescribed oral antibiotics and prepared for discharge home. The mother has contacted an herbalist who recommends treating the infection with motherwort. The mother says, "I know doctors don't believe in herbalism but I tried it for my skin condition and it worked, so I'm going to use it for my daughter no matter what you say." A literature search shows no adverse associations with motherwort. Which of the following is the most appropriate response?
(Multiple Choice)
4.9/5 (90)
(90) A 62-year-old woman is brought to the physician by her son due to progressive forgetfulness over the last year. She has been less active than normal and is having some difficulty walking. The patient has no urinary incontinence. Her past medical history is significant for exertional angina and hypertension. She has recently been depending on her son to manage her medications, which include metoprolol, amlodipine, and aspirin. She does not smoke or consume alcohol. Her father had hypertension and stroke, and her mother had Alzheimer disease. The patient is oriented to person and place, but not time. She has difficulty with 3-word recall. Her gait is slightly unstable and she has problems balancing when she closes her eyes. Examination of the lower extremities show decreased vibratory sensation, spastic paresis, and hyperreflexia bilaterally.
Further evaluation of the patient shows a mild indirect hyperbilirubinemia. Which of the following is the most likely explanation of this finding?
(Multiple Choice)
4.9/5 (71)
(71) A 16-year-old boy is brought to the emergency department by his mother after a single episode of generalized tonic-clonic seizure. The patient has been staying up late studying for midterm exams and has been feeling "more tired than usual" for the last few days. For the last 6 months, he has had occasional jerking arm movements in the morning but was not medically evaluated as they were brief and he otherwise "felt fine." The patient has had no recent fevers, vomiting, or headaches. He does not use alcohol or illicit drugs. His mother describes him as "anxious," but he has no chronic medical conditions and takes no medications. Temperature is 37.2 C (99 F), blood pressure is 120/60 mm Hg, and pulse is 72/min. On physical examination, the patient is drowsy but responsive to commands and oriented to person, place, and time. Cardiac examination reveals a regular rate and rhythm without murmurs. Cranial nerves II-XII are intact; there are no focal deficits. Deep tendon reflexes are normal in the upper and lower extremities, and plantar responses are flexor. There are no rashes or petechiae. Electroencephalogram shows bilateral polyspike and slow wave discharges. The patient receives appropriate treatment. He will require long-term monitoring for which of the following medication side effects?
(Multiple Choice)
4.8/5 (67)
(67) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)