



 Chat with AI
Exam 1: Behavioral Sciences

Exam 1: Behavioral Sciences343 Questions
Exam 2: Biochemistry307 Questions
Exam 3: Biology319 Questions
Exam 4: Critical Analysis & Reasoning Skills358 Questions
Exam 5: General Chemistry317 Questions
Exam 6: Organic Chemistry191 Questions
Exam 7: Physics200 Questions
Select questions type


Passage
Although the terms sex, sex category, and gender are commonly used interchangeably by most people, sociologists distinguish between them. Sex refers to the biological distinction between bodies (eg, male, female). Sex category (eg, male, female) is based on the visible secondary sex characteristics people use to attribute sex to others. Gender (eg, masculine, feminine) specifically refers to the behaviors and behavioral expectations people attribute to others on the basis of the individual's perceived sex category. Sex category and gender have recently been conceptualized as continua, with male and female as the extremes for sex category perception and masculine and feminine as the extremes for gender. Despite this, sex category and gender are usually perceived by humans categorically instead of continuously.Researchers conducted a study to assess how sex category interpretation is related to implicit bias and cortical activity. For the first phase, researchers tested sex category interpretation using 12 highly realistic computer-generated "facial morphs" varying along a continuum of apparent sex category from extremely male (1) to extremely female (12). The sexually dimorphic content of the faces was manipulated, but all other aspects were unchanged. For example, eyes and noses remained constant, but brow lines and eyebrows were thickened for male faces. Participants viewed the 12 faces in random order, rating each face on a scale of 1 (extremely male) to 10 (extremely female). Despite the uniform increments in the sexually dimorphic content of the facial morphs, responses demonstrated dichotomous sex category classification, as expected.For the second phase, which assessed the relationship between sex category interpretation and implicit bias, participants completed an implicit association test (IAT), in which they were shown the facial morphs with a pair of word attributes, one positive and one negative (eg, hard-working, lazy), and were asked to quickly pick the word they most associated with the face. Participants demonstrated shorter response times for facial morphs at the end points of the sex category continuum.For the third phase, researchers assessed the relationship between face-sensitive regions in the occipitotemporal cortex, particularly the fusiform face area (FFA), and sex category interpretation. Participants were injected with a glucose analog containing a radioactive tracer an hour before brain activity was measured while participants viewed the facial morphs. Results suggest that FFA activity was strongest when the faces were at the end points of the sex category continuum, regardless of whether a face was perceived as male or female.
-On the IAT, faster response times when pairing negative traits with less sex categorized faces most plausibly reflect:
(Multiple Choice)
4.9/5  (81)
(81) Passage
Prominent theories of emotion have long held that alterations in one's internal physiological state are necessary for the experience of emotion. Interoception involves both the unconscious and conscious perception of one's internal physiological state. The insula (or insular cortex), located deep within the lateral fissure on both sides of the brain, appears to be largely responsible for interoception. Studies suggest that the posterior insula (PI) is involved with processing homeostatic afferent information such as pain, temperature, hunger, thirst, and the impulse to breathe. In contrast, the anterior insula (AI) appears to process information regarding emotional awareness, the conscious experience of emotion.A recent study evaluated AI activity using functional magnetic resonance imaging (fMRI). Using fMRI, the participants' brain activity was monitored during two different tasks: an emotion-eliciting task and an interoceptive task.Task 1Participants watched 10 short videos of people recalling personal events that were either negative (eg, surviving a mass shooting attack) or positive (eg, seeing a loved one after a year apart). After each video, participants rated their reactions on a Likert scale from 1 (no emotional reaction) to 10 (extreme emotional reaction).Task 2Participants were instructed to monitor their own heart rate and press a button each time they felt their heartbeat. Participants' heart rates were externally monitored to gauge the accuracy of their responses.ResultsNeuroimaging results suggested that both tasks elicited activity in the AI. Furthermore, there was a high degree of overlap in the activity of the right AI and surrounding limbic and paralimbic brain regions at both the individual and group levels.
J. Zaki, J. I. Davis, and K. N. Ochsner ©2012 by Elsevier, B. V., and A. D. Craig ©2003 by Elsevier, B. V.
-If subjects from around the world were shown photographs of participants' faces during Task 1 and asked to identify the participants' facial expressions, on which of the following facial expressions would the subjects most likely agree?
(Multiple Choice)
4.8/5 (78)
(78) Passage
Major depression is a mood disorder that affects nearly 7% of the American population and is the most common cause of disability worldwide. Standard treatment typically involves antidepressant medication alone, although a combination of antidepressant medication and psychological treatment, such as psychotherapy or cognitive-behavioral therapy, is often more effective. However, because depression has genetic, environmental, and psychological contributing factors, treatment can be challenging. Approximately 10% of those suffering from depression have treatment-resistant depression (TRD) that does not respond to standard treatment.A number of treatment options for those with TRD target the functioning of the nervous system. Deep-brain stimulation (DBS), which is used to treat Parkinson disease, has also been investigated as a treatment for TRD. DBS involves implanting a device in the brain that sends electrical impulses to a specific area. Although the mechanism by which DBS alleviates depressive symptoms is unclear, neurostimulation provided by DBS is thought to disrupt dysfunctional patterns of electrical activity in local areas and connected brain regions.A meta-analysis reviewed the data from several studies that used different brain regions as DBS targets in the treatment of TRD. Table 1 shows the percentage of TRD patients who underwent DBS and showed clinical responsiveness and remission of depression. Clinical response was defined as a 50% reduction in scores on a measure of depression. Various scales were used in the studies, including different versions of the Hamilton Depression Rating Scale (HDRS) and Montgomery-Asberg Depression Rating Scale (MADRS). Remission of depression was defined as a score that fell below a predetermined threshold.Table 1 Percentage of TRD Patients Who Showed Clinical Response and Remission With DBS Treatment
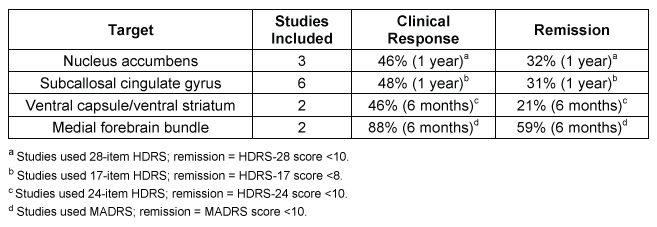 -According to the monoamine hypothesis:
 (Multiple Choice)
4.7/5 (76)
(76) Passage
Both institutional and interpersonal factors contribute to persistent disparities in health outcomes for minorities in the U.S. In Study 1, researchers sought to categorize the major factors contributing to the disparity by surveying 2,000 African American and 3,000 Hispanic residents in a major metropolitan city. Of those surveyed, 64% met federal guidelines for living at or below the poverty threshold even though 90% of those surveyed were employed. When asked, "What prevents you from going to the doctor?" the most common responses were financial considerations (92%), inability to get time off from work for appointments (85%), lack of transportation (52%), difficulty communicating with the health care provider (51%), and fear/distrust of the health care system (48%).Interpersonally, patients tend to fare better when their physician is of their same racial or ethnic background. Study 2 observed all Hispanic patients (n = 110) who visited a clinic in an urban lower-income community over one week. Patients met with either a Hispanic physician (n = 43) or a white, non-Hispanic physician (n = 67). The Hispanic physician saw the patients who visited the clinic on Monday or Tuesday, and the white, non-Hispanic physician saw the patients who visited the clinic on Wednesday, Thursday, or Friday. Both physicians were men who spoke Spanish fluently, had been working at the clinic for 8-10 years, and were unaware of the study's purpose beforehand. This study collected data on the duration of the face-to-face appointment time with the physician, medication adherence one month after the appointment, and the number of symptoms disclosed to the physician by the patient. Ninety-eight of the patients were already on medication or were prescribed new medication at the time of their appointment, and patients were contacted one month later for assessment of adherence. The results of this study are shown in Figure 1.
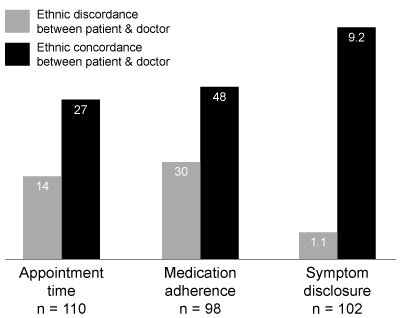 Figure 1 Average appointment time (minutes), medication adherence (percent), and number of symptoms disclosed according to patient-physician ethnic discordance vs. concordance
Adapted from W. Yost, (C)2007 Academic Press.
-Racial or ethnic discordance between patient and physician may result in increased distrust by the patient because the physician is a member of:
Figure 1 Average appointment time (minutes), medication adherence (percent), and number of symptoms disclosed according to patient-physician ethnic discordance vs. concordance
Adapted from W. Yost, (C)2007 Academic Press.
-Racial or ethnic discordance between patient and physician may result in increased distrust by the patient because the physician is a member of: (Multiple Choice)
4.7/5 (82)
(82) Passage
The highly addictive nature of cigarettes can be partly explained by how nicotine, the primary addictive ingredient, is administered. The fastest route of administration for most drugs is through inhalation; cigarette smoking results in the transmission of nicotine to the brain in about 15 seconds. In the brain, nicotine activates the nicotinic acetylcholine receptors, which stimulate the brain's reward pathway and produce mild feelings of euphoria. Those who quit smoking often relapse due to stress, weight gain, and withdrawal symptoms such as cravings and irritability. Of those who attempt to quit without formal treatment, only 3%-5% remain abstinent after a year.Research suggests that mindfulness meditation-based programs can be an effective strategy to quit smoking. Mindfulness is an aspect of meditation that involves cultivating a nonjudgmental awareness of the thoughts, emotions, and sensations arising in the present moment.For one study, researchers randomly assigned 88 smokers to either Mindfulness Training (MT) or the Freedom From Smoking (FFS) intervention developed by the American Lung Association. Both groups participated in 90-minute group training sessions twice a week for four weeks. The FFS intervention educated participants on the negative health consequences of smoking, coping strategies for cravings, and the development of healthy lifestyle habits. The MT intervention taught mindfulness meditation techniques as a way of gaining awareness and acceptance of the cognitive, emotional, and physical components of cravings. The number of cigarettes smoked per day and self-reported abstinence, as verified by exhaled carbon monoxide, were measured at the end of treatment and at a 17-week follow-up for participants in each group (Figure 1).
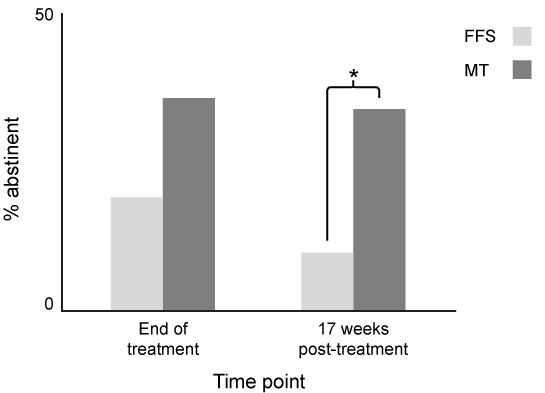 Figure 1 Percentage of participants in each group abstinent at the end of treatment and at 17-week follow-up (* indicates p < 0.05)
-The data in Figure 1 suggest which of the following relationships is statistically significant?
Figure 1 Percentage of participants in each group abstinent at the end of treatment and at 17-week follow-up (* indicates p < 0.05)
-The data in Figure 1 suggest which of the following relationships is statistically significant? (Multiple Choice)
4.8/5 (82)
(82) Passage
Korsakoff syndrome (KS) is caused by a thiamin (vitamin B1) deficiency that often results from chronic alcohol consumption. If KS is diagnosed during its earliest stages, its course may be reversed with thiamin supplements; otherwise, it progresses into a permanent type of dementia that includes severe cognitive dysfunction and memory loss. Alzheimer disease (AD) is associated with a different type of dementia that worsens over time, eventually causing memory loss, cognitive dysfunction, and severe brain atrophy.In one study, KS and AD subjects were assessed using the Corsi block-tapping task, which measures nonverbal memory. The experiment consisted of 10 KS subjects, 10 AD subjects, and 10 healthy control subjects. The control group was matched by age, gender, and premorbid IQ (intelligence quotient preceding the occurrence of symptoms) to the KS and AD groups.
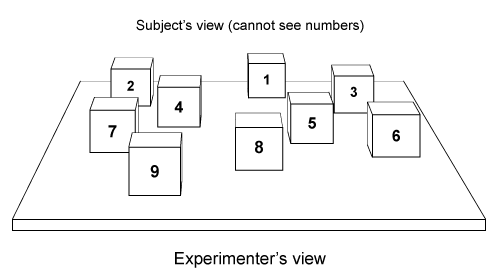 Figure 1 Corsi block-tapping taskThe Corsi block-tapping task consists of nine wooden blocks placed randomly on a board (Figure 1). To assess subjects' nonverbal memory, the experimenter touched four numbered blocks (numbers were visible only to the experimenter) in a specific pattern. Each subject was then asked to touch the same four blocks in the same sequence, either immediately or after a delay of 5-25 seconds. Subjects were required to perform a distractor task during the delay period. For the distractor task, subjects were asked to watch and reproduce a finger-tapping sequence first demonstrated by the experimenter. Experimenters would touch a finger on their right hand to a finger on their left hand according to a specific sequence (eg, index finger to ring finger, then pinky finger to middle finger) and the subjects would try to do the same.Results indicated that compared to controls, subjects with AD and KS were significantly impaired on the delayed memory task, although all subjects showed a significantly greater number of errors with increases in the delay interval.
-Which of the following cognitive abilities is critical to the Corsi block-tapping task and would be MOST affected by a lesion to the right hemisphere?
Figure 1 Corsi block-tapping taskThe Corsi block-tapping task consists of nine wooden blocks placed randomly on a board (Figure 1). To assess subjects' nonverbal memory, the experimenter touched four numbered blocks (numbers were visible only to the experimenter) in a specific pattern. Each subject was then asked to touch the same four blocks in the same sequence, either immediately or after a delay of 5-25 seconds. Subjects were required to perform a distractor task during the delay period. For the distractor task, subjects were asked to watch and reproduce a finger-tapping sequence first demonstrated by the experimenter. Experimenters would touch a finger on their right hand to a finger on their left hand according to a specific sequence (eg, index finger to ring finger, then pinky finger to middle finger) and the subjects would try to do the same.Results indicated that compared to controls, subjects with AD and KS were significantly impaired on the delayed memory task, although all subjects showed a significantly greater number of errors with increases in the delay interval.
-Which of the following cognitive abilities is critical to the Corsi block-tapping task and would be MOST affected by a lesion to the right hemisphere? (Multiple Choice)
4.9/5 (79)
(79) Passage
On the way home from a routine visit to the pediatrician, Sarah stops with her infant son at the local convenience store. As she is waiting in line, a man squeezes in closely behind them and sneezes. As Sarah walks home, she finds that her heart is racing, she feels nauseous, and she is terrified that her child will become severely ill.Soon after, she becomes obsessed with disease and contamination. She begins to take extensive measures to "decontaminate" herself and her home, including washing her hands dozens of times daily. These cleaning rituals have the immediate effect of lessening Sarah's anxiety, so she soon spends most of her day performing them. She seeks treatment from a therapist, who instructs her to gradually expose herself to "contamination" but refrain from her cleaning rituals. The therapist also teaches Sarah how to recognize and modify her maladaptive thoughts about illness prevention. Within several weeks, Sarah finds that she can manage her thoughts about disease and contamination without resorting to ritualistic cleaning.A researcher hypothesized that individuals with obsessive-compulsive disorder (OCD), such as Sarah, would show a more generalized fear response to safe stimuli compared to controls. Generalized conditioned fear responses occur when individuals react with fear to stimuli that resemble the original conditioned stimulus (eg, someone injured in an accident with a red truck fears all red vehicles). The researcher conditioned 100 individuals (50 with OCD and 50 controls) to associate a shock with a visual stimulus. In phase 1, participants viewed a computer screen that alternated between images of a small ring (1 cm) and a large ring (20 cm). The small ring and large ring were displayed for 1 second each, with a blank screen in between for 5 seconds. A mild electric shock was paired with the large ring, and no shock was paired with the small ring. This was repeated for 10 trials. In phase 2, shocks were discontinued, and three intermediate-sized rings were added to the series and presented in increasing size (ie, 1 cm, 5 cm, 10 cm, 15 cm, 20 cm) while the participants' startle response to each ring was measured. This was repeated for 10 trials.
ncbi.nlm.nih.gov/pmc/articles/PMC3932061/
-Which hypothetical result would provide support for the researcher's hypothesis?
(Multiple Choice)
5.0/5 (82)
(82) Standardized protocols, patient checklists, and clinical guidelines are meant to increase efficiency, calculability, predictability, and control in the clinical setting. However, critics of standardizing medicine suggest that these sorts of practices may lead to:
(Multiple Choice)
4.9/5 (65)
(65) A social psychologist employs a confederate to pretend to have a heart attack in a crowded train station, then measures how long it takes for the confederate to receive help. The study procedure is repeated over multiple trials throughout the day. This experiment is most likely evaluating which phenomenon and with what independent variable, respectively?
(Multiple Choice)
4.9/5 (69)
(69) Passage
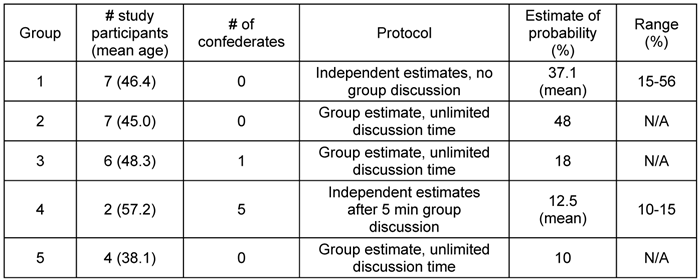
Twenty-two adults (mean age 49.5) were recruited to participate in a study they were told was to assess beliefs about cancer risk. All participants were in good health; neither they nor any first-degree relatives had been diagnosed with cancer.In the first phase of the study, participants viewed a brief video about the epidemiology and prevalence of cancer in the United States, and then were randomly assigned to one of four groups and asked to estimate the probability that they would develop cancer in their lifetimes. Group 1 consisted of seven study participants who each arrived at their estimates independently and without discussion. Group 2 consisted of seven study participants who were asked to agree on a group estimate after discussion (with unlimited time). Group 3 contained seven members who were also asked to arrive at a consensus estimate after discussion (with unlimited time): Six were study participants and the seventh was a confederate who suggested a very low estimate. Group 4 likewise contained seven members: Two were study participants and the other five were confederates who each suggested low estimates. Group 4 members were limited to 5 minutes of discussion and then asked to arrive at individual estimates.For the second phase of the study, four members of Group 1 who arrived at independent estimates of 20% or lower were put into a new group (Group 5), then were given unlimited time to discuss their initial estimates and arrive at a group estimate (Table 1).Table 1 Group Composition, Protocol, and Estimate of Developing Cancer in One's Lifetime
 S. E. Asch ©1956 American Psychological Association.
-This study appears to have been actually assessing which of the following?
S. E. Asch ©1956 American Psychological Association.
-This study appears to have been actually assessing which of the following? (Multiple Choice)
4.9/5 (87)
(87) A researcher is testing a patient's neurological function. When a word is flashed briefly in the patient's right visual field, he can correctly vocalize what he saw. When a word is flashed briefly in the patient's left visual field, he is unable to say what he saw but can correctly draw it. Which of the following is most likely damaged in this patient?
(Multiple Choice)
5.0/5 (74)
(74) Passage
Health psychologists interested in studying the influence of positive and negative thinking on weight loss conducted a study on 120 obese adults attempting to lose weight. Participants indicated on a scale of 1 to 7 how successful they thought they would be at losing weight (1 = "not successful" and 7 = "very successful") and how much control they believed they had over their success (1 = "no control" and 7 = "complete control"), recorded as expectation of success scores and control of success scores, respectively.Participants were then randomly divided into three groups and asked to complete a 15-minute guided mental exercise twice a day for three weeks. Participants in the fantasy/reality contrast condition were instructed to reflect on two positive aspects of a fantasized weight loss, such as attaining better health and more energy, and two negative aspects of reality that impede weight loss, such as lack of discipline and desire to eat unhealthy foods. Participants in the positive fantasy condition were asked to reflect on four positive aspects of weight loss, and participants in the negative reality condition were asked to reflect on four factors that impede weight loss.At the end of this three-week period, participants began a three-month diet and exercise regimen involving caloric restriction to 1,500 calories per day as well as regular participation in aerobic exercise and weight training. Researchers recorded weekly weights of participants and surveyed participants regarding adherence to proactive weight loss strategies. The results are shown by group in Figures 1 and 2.
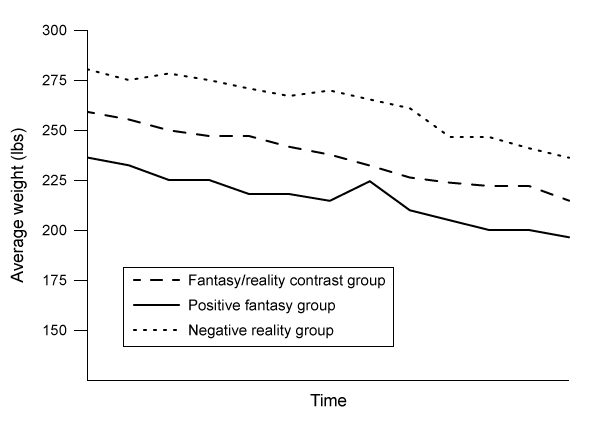 Figure 1 Average weight recorded for each group during three-month follow-up
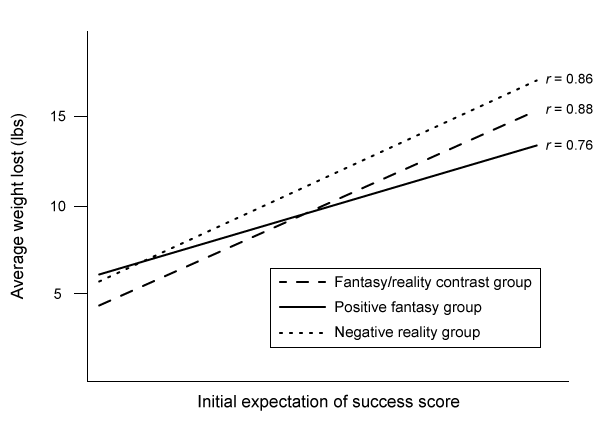 Figure 2 Initial expectation of success score versus average weight loss
-Which of the following participants are most likely to experience learned helplessness?
Figure 1 Average weight recorded for each group during three-month follow-up
Figure 2 Initial expectation of success score versus average weight loss
-Which of the following participants are most likely to experience learned helplessness? (Multiple Choice)
4.8/5 (90)
(90) Passage
Studies suggest that health outcomes for preventable diseases are impacted by delayed treatment and lack of compliance. People often postpone seeking medical care because they fear hearing bad news from their physician. Paradoxically, when they finally do see a doctor, they may find out that their disease is indeed serious, but only because treatment was so delayed.Refusal to comply with a physician's instructions is another major issue. Although there are many reasons for this, one possible explanation is that patients are responding with psychological reactance. Reactance theory suggests that when an individual perceives that free choice is threatened or limited, he or she may respond by wanting to perform the threatened behavior even more, as if to preserve original freedoms. For example, if a physician tells a patient to quit smoking, the smoker might respond by smoking even more in an effort to preserve the freedom to smoke.Researchers hypothesize that psychological reactance may be reduced or avoided when physicians communicate with their patients through a process known as deliberation. In the following example, the physician has already explained to the patient that her weight could be having a negative impact on her diabetes. The physician, using deliberation, then initiates a dialogue about how the patient would like to address the situation:Physician: "You are already taking pretty strong medications, so your options are either to change your eating habits or increase your level of exercise. It's your choice."Patient: "I think I could exercise more by joining a gym. I could stop eating dessert, but I would hate to give up chocolate."Physician: "Okay. Let's negotiate. Why don't you try going to the gym and giving up sweets-except chocolate-for the next month. Then come back to see me, and we'll see where we are."
Adapted from S. Bigi ©2016 Frontiers.
-The process of deliberation, as described in the passage, is most consistent with which of the following major sociological theories?
(Multiple Choice)
4.9/5 (69)
(69) Passage
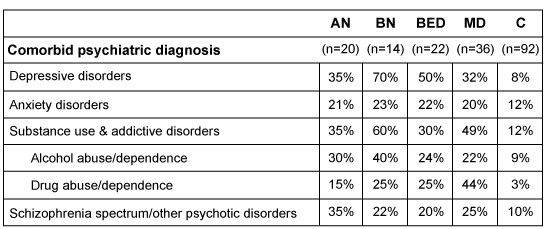
A common misconception in medicine is that eating disorders present similarly in males and females. Research suggests that this is untrue: males meeting diagnostic criteria for eating disorders are more likely than females to have another psychiatric illness, demonstrate a later age of onset, and engage in excessive exercise. They are less likely to engage in purging behaviors, be diagnosed by clinicians, or seek treatment. When males do enter treatment, they are generally further along in the course of the illness.The classification of eating disorders in males according to the Diagnostic and Statistical Manual of Mental Disorders, Fifth Edition (DSM-5) has recently been debated. Research suggests that one very common manifestation of eating disorder etiology in males, called muscle dysmorphia (MD), includes an obsession with a larger and more muscular body, which contrasts with the thin, idealized body for females with eating disorders. Characterized as a subset of body dysmorphic disorder, MD is more recently conceptualized as part of a spectrum of eating disorders; however, it is still classified under the obsessive-compulsive and related disorders umbrella in the DSM-5.One study applied the latest DSM-5 diagnostic criteria for anorexia nervosa (AN), bulimia nervosa (BN), binge eating disorder (BED), and MD to the medical records of male veterans treated in Veterans Administration (VA) hospitals across the United States from 2000 to 2015. The study (Table 1) found a significant increase in psychiatric comorbidity compared to controls (C).Table 1 Prevalence of Psychiatric Disorders for Eating Disorder and MD Cases and Controls in a National Sample of Male Veterans Treated at VA Hospitals from 2000 to 2015
 -A physician suspects that a young woman seen in the clinic displays symptoms of an eating disorder. Which of the following responses best demonstrates the ego defense mechanism of rationalization in the patient?
 (Multiple Choice)
4.8/5 (94)
(94) Passage
Almost 70% of Americans today are either overweight or obese, but only 34% think they weigh too much. This is in contrast to 1990, when 54% of Americans were overweight or obese and 46% reported being at least somewhat overweight. In other words, the gap between what we weigh and what we think we weigh is getting bigger.Epidemiologists argue that this discrepancy can be partly explained by the widespread resetting of norms regarding "normal weight" and "obesity." As close friends, coworkers, and family members gain weight, one's concept of what a body of acceptable weight looks like becomes modified. What was once considered overweight is now considered the norm, if only because it is so common (Figure 1).
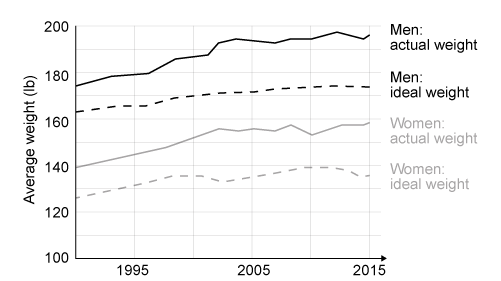 Figure 1 Actual vs. ideal weight (in pounds) for Americans, 1990-2015This sheds new light on recent efforts to stop the obesity epidemic in America. Experts have long contended that awareness efforts don't work because overweight individuals are already aware that they are overweight and that obesity causes health problems. These latest data suggest that many overweight Americans don't even realize that they are overweight. Epidemiologists are now suggesting that a more successful strategy to get Americans to lose weight might be to first succeed at convincing them that being overweight is not normal.
-The second paragraph describes:
Figure 1 Actual vs. ideal weight (in pounds) for Americans, 1990-2015This sheds new light on recent efforts to stop the obesity epidemic in America. Experts have long contended that awareness efforts don't work because overweight individuals are already aware that they are overweight and that obesity causes health problems. These latest data suggest that many overweight Americans don't even realize that they are overweight. Epidemiologists are now suggesting that a more successful strategy to get Americans to lose weight might be to first succeed at convincing them that being overweight is not normal.
-The second paragraph describes: (Multiple Choice)
4.8/5 (93)
(93) Passage
The term "health disparities" describes a systematic incidence of poorer health outcomes for groups that have traditionally experienced social disadvantage (eg, racial and ethnic minorities, lower-income individuals, women) as compared to more advantaged groups (eg, whites, higher-income individuals, men). These health disparities are driven by unequal access to health care services and health insurance due to prejudice and discrimination on the part of health care providers and the overall system, and extensive research has focused on these issues.Recent research suggests that another factor might explain health disparities: stereotype threat on the part of the patient. Stereotype threat can be evoked by verbal or nonverbal cues from health care professionals, such as a physician's use of confusing medical jargon (the standardized language medical personnel use to communicate among themselves) or a nurse's body language while discussing the risks of obesity and alcohol use. Once triggered, stereotype threat may result in behaviors that compromise one's own health. For example, a patient may withhold information or feel compelled to describe health-related behaviors in a positive light. Similarly, if the interaction arouses anxiety, a patient may be less likely to remember the physician's instructions or might dismiss a physician's advice as biased.Stereotype threat can be reduced through training programs that improve employees' communication skills. Some hospitals in large urban areas have implemented the use of cultural liaisons, individuals who are able to bridge the gap between a minority patient's cultural beliefs and Western medicine. Cultural liaisons are often present during the nonsensitive portions of the doctor's appointment, and studies suggest they may help to reduce stereotype threat in patients.
Adapted from J. Aronson, D. Burgess, S. M. Phelan, and L. Juarez (C)2013 American Public Health Association
-Which of the following concepts is LEAST relevant to the processes described in the second paragraph?
(Multiple Choice)
4.8/5 (90)
(90) Passage
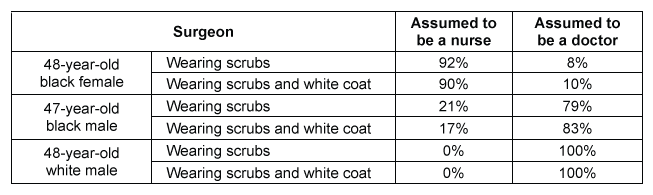
Numerous studies suggest that physicians make both conscious and unconscious assumptions about their patients, and these assumptions often impact patient care and outcomes. However, little research has focused on the assumptions patients make about their physicians.Researchers designed an observational study to investigate assumptions made by patients in health care settings. For this study, three different surgeons were asked to interact with pre-surgery patients whom they had never met using a standardized script. Each surgeon participated in 30 total interactions over the course of two weeks. The purpose of the study was to assess how the patient's assumptions regarding the surgeon's status were impacted by the surgeon's race, gender, and attire.According to the script, the surgeon did not introduce him- or herself upon entering the room. All three surgeons were in their late 40s; one surgeon was a black woman, one was a black man, and one was a white man. The surgeons wore either surgical scrubs alone or a white coat over their surgical scrubs. Researchers analyzed how patients addressed or referred to the surgeon to assess assumptions about the surgeon's role as a doctor or a nurse. The results are presented in Table 1.Table 1 Percentage of Patients Who Assumed the Surgeon Was a Doctor or a Nurse
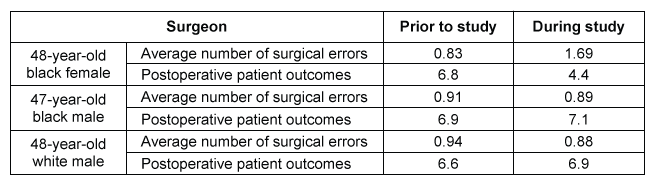
 The researchers also retrospectively analyzed minor (non-life-threatening) surgical errors and postoperative patient outcomes for one month prior to the study and during the study timeframe for each surgeon. The number of minor errors was averaged per surgery, and postoperative patient outcomes were quantified using a multifactor (eg, pain, infection, bleeding, other complications) assessment scale of 1 (worst outcome) to 12 (best outcome).Table 2 Average Number of Minor Surgical Errors (Per Surgery) and Aggregated Postoperative Patient Outcome Scores
 -Which of the following is best supported by the data in Table 1 and Table 2?
The researchers also retrospectively analyzed minor (non-life-threatening) surgical errors and postoperative patient outcomes for one month prior to the study and during the study timeframe for each surgeon. The number of minor errors was averaged per surgery, and postoperative patient outcomes were quantified using a multifactor (eg, pain, infection, bleeding, other complications) assessment scale of 1 (worst outcome) to 12 (best outcome).Table 2 Average Number of Minor Surgical Errors (Per Surgery) and Aggregated Postoperative Patient Outcome Scores
-Which of the following is best supported by the data in Table 1 and Table 2? (Multiple Choice)
4.9/5 (74)
(74) Passage
Research suggests that cognitive changes occur with age. Though dementia is common, occurring in about 14% of individuals age 71 and older and in almost 34% of individuals 90 and older, a majority of older adults exhibit some degree of "normal" cognitive decline. The following studies were conducted on 605 older adults (mean age = 78.2) who did not show any signs of dementia and 590 younger adult participants (mean age = 28.8).Cognition studiesParticipants were asked to solve five puzzles designed to test their ability to apply new information, reason inductively and deductively, and use logic. Participants were also asked to complete a 20-item vocabulary and grammar test. The older adults performed significantly worse than the younger adults on the puzzles, but there was no significant difference between the groups on the vocabulary/grammar test.Focus studiesWhen asked to read a short story and then answer a series of questions assessing comprehension (focused condition), older adults performed equally well as the younger adults. However, when asked to read a similar story while wearing headphones playing another story that was to be ignored (distraction condition), older adults performed worse than younger adults when answering questions assessing comprehension of the story they read.Memory studiesWhen asked to memorize 30 neutral items (eg, a key, a pencil, a book), the images of which were presented serially, younger adults performed significantly better when asked to list the items immediately after seeing them and when asked to list the items after performing a distraction task. In a second trial, both groups were serially presented with 30 pictures of faces showing positive, negative, or neutral expressions. The groups were later asked to identify these faces among a set of 100. Results are shown in Figure 1.
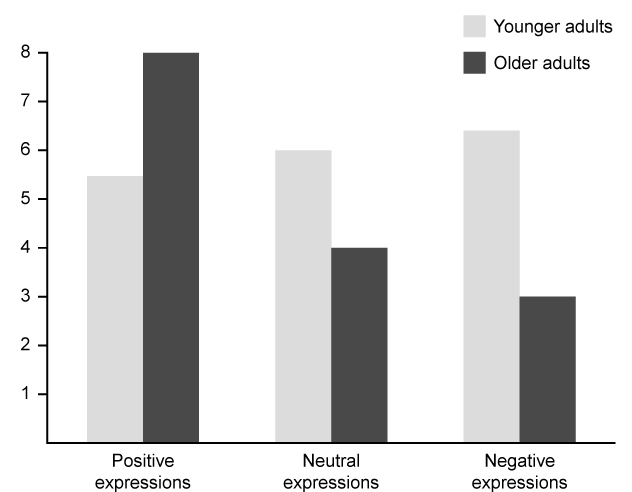 Figure 1 Average number of correctly identified faces for older and younger adult groups
-Which of the following conflicts corresponds to the stage of psychosocial development most appropriate for the age of the older adult study participants?
Figure 1 Average number of correctly identified faces for older and younger adult groups
-Which of the following conflicts corresponds to the stage of psychosocial development most appropriate for the age of the older adult study participants? (Multiple Choice)
4.9/5 (74)
(74) Passage
Trait theorists believe that all people have certain traits, or characteristic ways of thinking and behaving, that largely account for personality. Psychobehavioral researchers conducted a pair of studies to determine whether individuals could intentionally alter one of their respective personality traits.In Study 1, participants were asked to select one personality trait they wished to increase from among the following: openness to experience, conscientiousness, extraversion, agreeableness, or emotional stability. Participants first completed a short survey that measured baseline personality trait expression scores (pretest). Participants in the experimental group (n = 125) then developed their own intervention plan intended to increase the selected personality trait whereas the control group (n = 125) did not implement any changes to daily activities. At the end of the study, all participants completed the same self-report survey to reassess their personality trait expression scores (posttest). Results were calculated by subtracting pretest from posttest scores for each person (change score), and then comparing the mean change scores for the experimental and control groups. Results showed significantly greater change scores for experimental group participants who elected to increase their emotional stability, relative to control subjects who selected this trait. The change scores did not differ significantly between the experimental and control groups that selected any of the other four traits (ie, openness to experience, conscientiousness, extraversion, or agreeableness).In Study 2, the same basic methodology was used on a new cohort with several adjustments to the Study 1 design. Instead of asking participants in the experimental condition to formulate their own intervention plans, licensed therapists trained participants in practices to redirect thought processes, emotional responses, and behaviors associated with the selected personality trait. The experimental group participants carried out these practices for the course of the study whereas the control group participants implemented no changes. In contrast to the self-reports used in Study 1, personality trait expression scores (both pre and post) were determined by assessments made by researchers. Results from Study 2 showed significantly greater increases in all five personality trait expression scores for experimental versus control participants.
-A trait theorist would most likely challenge the study findings described in the passage by asserting that researchers failed to assess:
(Multiple Choice)
4.9/5 (88)
(88) Which of the following population pyramids depicts the population that is most likely to decrease in size in the near future?
(Multiple Choice)
4.7/5 (86)
(86) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)