



 Chat with AI
Exam 1: Behavioral Sciences

Exam 1: Behavioral Sciences343 Questions
Exam 2: Biochemistry307 Questions
Exam 3: Biology319 Questions
Exam 4: Critical Analysis & Reasoning Skills358 Questions
Exam 5: General Chemistry317 Questions
Exam 6: Organic Chemistry191 Questions
Exam 7: Physics200 Questions
Select questions type


Passage
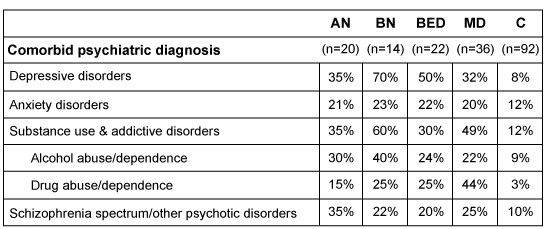
A common misconception in medicine is that eating disorders present similarly in males and females. Research suggests that this is untrue: males meeting diagnostic criteria for eating disorders are more likely than females to have another psychiatric illness, demonstrate a later age of onset, and engage in excessive exercise. They are less likely to engage in purging behaviors, be diagnosed by clinicians, or seek treatment. When males do enter treatment, they are generally further along in the course of the illness.The classification of eating disorders in males according to the Diagnostic and Statistical Manual of Mental Disorders, Fifth Edition (DSM-5) has recently been debated. Research suggests that one very common manifestation of eating disorder etiology in males, called muscle dysmorphia (MD), includes an obsession with a larger and more muscular body, which contrasts with the thin, idealized body for females with eating disorders. Characterized as a subset of body dysmorphic disorder, MD is more recently conceptualized as part of a spectrum of eating disorders; however, it is still classified under the obsessive-compulsive and related disorders umbrella in the DSM-5.One study applied the latest DSM-5 diagnostic criteria for anorexia nervosa (AN), bulimia nervosa (BN), binge eating disorder (BED), and MD to the medical records of male veterans treated in Veterans Administration (VA) hospitals across the United States from 2000 to 2015. The study (Table 1) found a significant increase in psychiatric comorbidity compared to controls (C).Table 1 Prevalence of Psychiatric Disorders for Eating Disorder and MD Cases and Controls in a National Sample of Male Veterans Treated at VA Hospitals from 2000 to 2015
 -The DSM-5 describes AN as characterized by a distorted body image and excessive food restriction leading to severe weight loss. How would a behaviorist explain the behavior of an individual diagnosed with AN?
 (Multiple Choice)
4.7/5  (64)
(64) Passage
Religion establishes the beliefs and rituals surrounding the sacred and provides meaning and significance to individuals' lives. The tenets of any given religion can have a far-reaching impact on the individuals within its faith community. For example, certain religions promote faith-based lifestyle directives (FBLDs), which urge believers to follow specific guidelines regarding their own behavior (eg, restrictions on diet and substance use) and their treatment of others (eg, mission work). Because these practices typically reflect the religious group's values, FBLDs are often an important expression of faith for the deeply religious.One religious group with health-related FBLDs is the Seventh Day Adventist Church, which formed in the 1860s after early leaders broke away from established Protestant churches. Since its formal establishment, Seventh Day Adventist Church membership has grown from 3,500 to over 20 million worldwide. The Seventh Day Adventist Church advocates conservative religious teachings and a holistic approach to health and wellness; members are encouraged to pursue vegetarianism, exercise regularly, and avoid alcohol and tobacco.Although FBLDs impact believers' personal choices and behaviors, they are also often meant to have an impact on others through the creation of social institutions such as schools and hospitals. For example, early Adventist leaders developed a health care system to serve the needs of the larger community, and members of the modern Adventist Church have continued to try to reduce health disparities worldwide by creating hospitals, clinics, and universities that provide health care and education services to underserved and developing communities.Researchers from a variety of fields have examined health-related religious values and FBLDs. Epidemiological research has shown that believers from different religions who follow certain FBLDs (eg, abstaining from smoking and alcohol) experience lower rates of chronic illnesses (eg, heart disease and many types of cancer) than the general population. Sociologists have suggested that as a society increasingly relies on medical professionals, rather than clergy, as legitimate sources of guidance on lifestyle behaviors, membership in religious groups with values that are compatible with medicalization will continue to rise. Some hypothesize that this phenomenon accounts for the seemingly contradictory increase in membership in certain conservative religious groups with strict FBLDs, despite mainstream society becoming less religious.
-Which prediction is compatible with the sociologists' assertion in the fourth paragraph? The increase of medicalization in society will result in medical professionals having:
(Multiple Choice)
4.9/5 (95)
(95) Passage
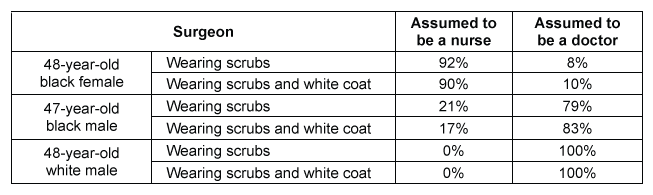
Numerous studies suggest that physicians make both conscious and unconscious assumptions about their patients, and these assumptions often impact patient care and outcomes. However, little research has focused on the assumptions patients make about their physicians.Researchers designed an observational study to investigate assumptions made by patients in health care settings. For this study, three different surgeons were asked to interact with pre-surgery patients whom they had never met using a standardized script. Each surgeon participated in 30 total interactions over the course of two weeks. The purpose of the study was to assess how the patient's assumptions regarding the surgeon's status were impacted by the surgeon's race, gender, and attire.According to the script, the surgeon did not introduce him- or herself upon entering the room. All three surgeons were in their late 40s; one surgeon was a black woman, one was a black man, and one was a white man. The surgeons wore either surgical scrubs alone or a white coat over their surgical scrubs. Researchers analyzed how patients addressed or referred to the surgeon to assess assumptions about the surgeon's role as a doctor or a nurse. The results are presented in Table 1.Table 1 Percentage of Patients Who Assumed the Surgeon Was a Doctor or a Nurse
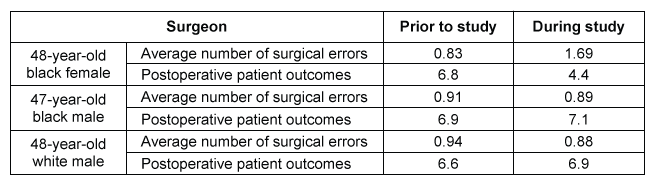
 The researchers also retrospectively analyzed minor (non-life-threatening) surgical errors and postoperative patient outcomes for one month prior to the study and during the study timeframe for each surgeon. The number of minor errors was averaged per surgery, and postoperative patient outcomes were quantified using a multifactor (eg, pain, infection, bleeding, other complications) assessment scale of 1 (worst outcome) to 12 (best outcome).Table 2 Average Number of Minor Surgical Errors (Per Surgery) and Aggregated Postoperative Patient Outcome Scores
 -Table 1 suggests that the patients' assumptions may have been influenced by which of the following?
The researchers also retrospectively analyzed minor (non-life-threatening) surgical errors and postoperative patient outcomes for one month prior to the study and during the study timeframe for each surgeon. The number of minor errors was averaged per surgery, and postoperative patient outcomes were quantified using a multifactor (eg, pain, infection, bleeding, other complications) assessment scale of 1 (worst outcome) to 12 (best outcome).Table 2 Average Number of Minor Surgical Errors (Per Surgery) and Aggregated Postoperative Patient Outcome Scores
-Table 1 suggests that the patients' assumptions may have been influenced by which of the following? (Multiple Choice)
4.8/5 (89)
(89) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)