



 Chat with AI
Exam 3: Biology

Exam 1: Behavioral Sciences343 Questions
Exam 2: Biochemistry307 Questions
Exam 3: Biology319 Questions
Exam 4: Critical Analysis & Reasoning Skills358 Questions
Exam 5: General Chemistry317 Questions
Exam 6: Organic Chemistry191 Questions
Exam 7: Physics200 Questions
Select questions type


Passage
Hematological anomalies have been observed in patients with prolonged liver damage. For example, patients with chronic cirrhosis (scarring of the liver) often develop anemia and other blood disorders. Hemoglobin is the metalloprotein within red blood cells that is responsible for the oxygen-carrying capacity of blood, and its function may be affected by liver damage. The poor prognosis of patients with cirrhosis and anemia has stimulated further study of hemoglobin function and oxygen saturation.Blood samples from both cirrhotic patients and healthy individuals at rest and after exercise were exposed to varying partial pressures of oxygen. Measurement of oxyhemoglobin dissociation curves (ODCs [Figure 1]) from the blood samples revealed significant functional differences in the hemoglobin from cirrhotic patients relative to control subjects.
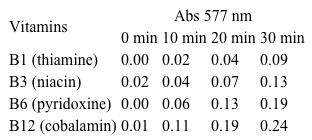
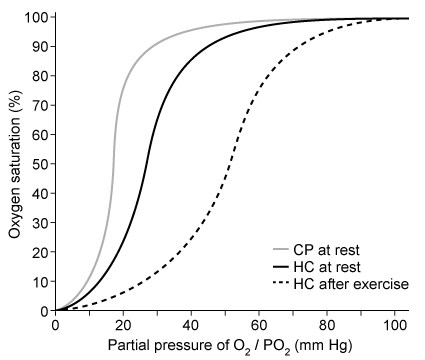 Figure 1 Oxyhemoglobin dissociation curve for cirrhotic patients (CP) at rest and for healthy controls (HC) at rest and after 20 minutes of exerciseVitamins are considered nontoxic supplements and are frequently provided to anemic patients to increase red blood cell production. They may therefore have therapeutic benefits for cirrhotic patients. However, some studies indicate that excessive vitamin consumption may lead to oxidative stress that could induce anemia through hemolysis (red blood cell rupturing). Hemoglobin strongly absorbs light at 577 nm, and researchers conducted hemolysis assays by spinning down red blood cells and measuring absorbance (Abs) of the supernatant at 577 nm to determine how much hemoglobin was released. The assay was carried out in the presence of four vitamins to determine their potential as oxidizing agents, and results are shown in Table 1.Table 1 Hemolysis of Red Blood Cells from Healthy Donors Treated With Vitamins [2 mM] for 30 Minutes, Measured by Absorbance at 577 nm
 Adapted from Clerbaux T, Detry B, Geubel A, et al. The oxyhemoglobin dissociation curve in liver cirrhosis. Chest. 2006;129(2):438-45.
-A patient treated for cirrhosis was given vitamin B6 to stimulate red blood cell production. To counteract the potential negative side effects of this treatment, extract of ginkgo biloba was also administered. What is the most likely role of ginkgo biloba extract in this scenario?
Figure 1 Oxyhemoglobin dissociation curve for cirrhotic patients (CP) at rest and for healthy controls (HC) at rest and after 20 minutes of exerciseVitamins are considered nontoxic supplements and are frequently provided to anemic patients to increase red blood cell production. They may therefore have therapeutic benefits for cirrhotic patients. However, some studies indicate that excessive vitamin consumption may lead to oxidative stress that could induce anemia through hemolysis (red blood cell rupturing). Hemoglobin strongly absorbs light at 577 nm, and researchers conducted hemolysis assays by spinning down red blood cells and measuring absorbance (Abs) of the supernatant at 577 nm to determine how much hemoglobin was released. The assay was carried out in the presence of four vitamins to determine their potential as oxidizing agents, and results are shown in Table 1.Table 1 Hemolysis of Red Blood Cells from Healthy Donors Treated With Vitamins [2 mM] for 30 Minutes, Measured by Absorbance at 577 nm
Adapted from Clerbaux T, Detry B, Geubel A, et al. The oxyhemoglobin dissociation curve in liver cirrhosis. Chest. 2006;129(2):438-45.
-A patient treated for cirrhosis was given vitamin B6 to stimulate red blood cell production. To counteract the potential negative side effects of this treatment, extract of ginkgo biloba was also administered. What is the most likely role of ginkgo biloba extract in this scenario? (Multiple Choice)
4.9/5  (81)
(81) Passage
Skin grafting is a procedure in which healthy skin from a different region of the body is transplanted onto an area of absent or damaged skin. Skin grafts are used for partial-thickness burns, which damage the epidermis and dermis, and for full-thickness burns, which damage the epidermis, dermis, and hypodermis. Superficial burns injure only epidermal tissue and heal without skin grafts. Skin grafting has greatly improved the long-term survival of burn victims. However, because grafted skin cannot effectively dissipate heat, burn survivors are at an increased risk of hyperthermia (abnormally high body temperature), a condition that can lead to heat-related medical emergencies such as heat stroke. The greater the grafted body surface area (BSA), the greater the risk for complications related to thermoregulation.Heat acclimation (HA) is the process by which the body increases heat tolerance through adaptive changes in the sympathetic control of skin heat dissipation. It can be induced in healthy individuals by repeated exercise at elevated ambient temperature and humidity. A group of researchers tested whether skin graft recipients could also undergo HA. Skin graft recipients who were otherwise healthy and had at least 15% grafted BSA were recruited for the study, as were controls with no history of receiving grafts. The skin graft recipients were split into two groups, those with 15%-40% grafted BSA and those with >40% grafted BSA. For a period of seven days, subjects participated daily in 90 min of exercise at 50% maximal oxygen consumption in a room where the temperature was maintained at 40°C. Exercise modality, fluid intake, and frequency and duration of rest were strictly monitored.On the days immediately preceding and following the HA regimen, the heat tolerance of participants was tested with a 90-min exercise regimen at a fixed heat production rate (Figure 1). Tolerance testing was halted before 90 min for subjects whose internal body temperature exceeded 40°C. The change in internal temperature of participants was calculated by subtracting their internal temperature before exercise from their internal temperature at exercise cessation (either once temperature reached 40°C or at the 90-min endpoint).
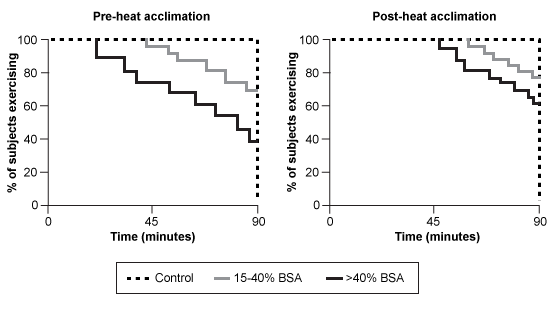 Figure 1 HA in controls and in skin graft recipients
Adapted from Schlader ZJ, Ganio MS, Pearson J, et al. J Appl Physiol. 2015;119(1):69-76.
-A skin graft candidate with full-thickness burns on approximately 50% of the total BSA is at risk for all of the following EXCEPT:
Figure 1 HA in controls and in skin graft recipients
Adapted from Schlader ZJ, Ganio MS, Pearson J, et al. J Appl Physiol. 2015;119(1):69-76.
-A skin graft candidate with full-thickness burns on approximately 50% of the total BSA is at risk for all of the following EXCEPT: (Multiple Choice)
4.9/5 (80)
(80) Passage
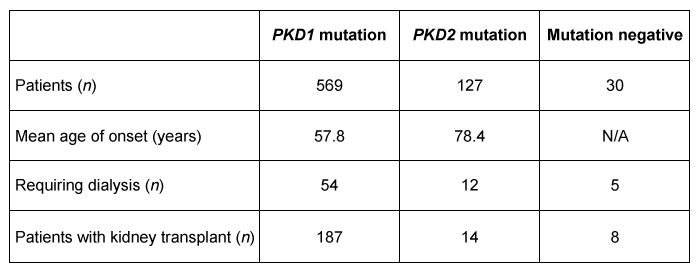
Autosomal dominant polycystic kidney disease (ADPKD) is one of the most common heterogeneous disorders, with a reported incidence of 1 in 1,000 people. The primary pathology is the development of numerous fluid-filled renal cysts that ultimately expand and severely impair kidney function. By age 60, approximately 50% of patients with ADPKD progress to end-stage renal disease (ESRD) and kidney failure. Clinical complications include high blood pressure, urinary tract infections, and cysts in other organs such as the liver and pancreas.Approximately 85% of ADPKD cases are caused by mutations in the PKD1 gene, which codes for the protein polycystin-1 (PC1). The remaining 15% of cases are caused by mutations in the PKD2 gene, which codes for the protein polycystin-2 (PC2). The PC2 protein functions as a mechanically activated calcium (Ca2+) channel in ciliated renal epithelial cells. PC1 and PC2 interact via their C-terminal cytoplasmic tails to form a heteromer that modulates intracellular calcium homeostasis. Disruption of calcium signaling as a result of mutations in either PKD1 or PKD2 is associated with increased cell growth and cyst formation in ADPKD patients.To identify individuals with mutations in PKD1 and PKD2, researchers analyzed phenotypic and genetic data from patients with established renal disease, as shown in Table 1.Table 1 Comparison of Renal Disease Onset and Symptom Severity in Various Patient Groups
 Next, researchers examined how phenotypic disease severity was affected by both the position of the mutations in PKD1 (5′ or 3′ end) and the type of mutation in PKD1 or PKD2. In Figure 1, disease severity is given as the cumulative probability of renal survival as a function of age.
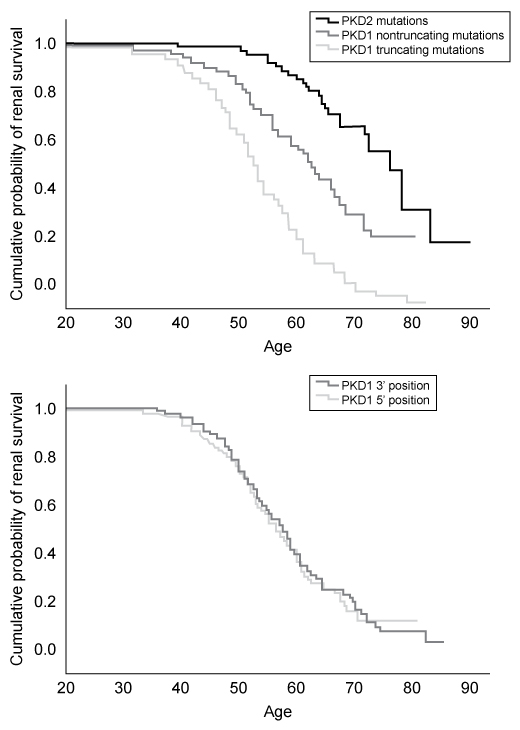 Figure 1 Probability of maintaining healthy kidney physiology as a function of age, analyzed by mutation type and position
Adapted from Cornec-le gall E, Audrézet MP, Chen JM, et al. J Am Soc Nephrol. 2013;24(6):1006-13.
-Based on the passage, is the mutated PKD1 allele likely to be eradicated from the gene pool by natural selection?
Next, researchers examined how phenotypic disease severity was affected by both the position of the mutations in PKD1 (5′ or 3′ end) and the type of mutation in PKD1 or PKD2. In Figure 1, disease severity is given as the cumulative probability of renal survival as a function of age.
Figure 1 Probability of maintaining healthy kidney physiology as a function of age, analyzed by mutation type and position
Adapted from Cornec-le gall E, Audrézet MP, Chen JM, et al. J Am Soc Nephrol. 2013;24(6):1006-13.
-Based on the passage, is the mutated PKD1 allele likely to be eradicated from the gene pool by natural selection? (Multiple Choice)
4.8/5 (88)
(88) Passage
Each time a eukaryotic cell replicates its DNA, the telomeres at the ends of each chromosome become slightly shorter. When telomeres reach a critically short length, the cells enter the senescent state, in which cell division ceases (Figure 1). In humans, conditions such as hypertension, liver disease, and Alzheimer disease have been associated with the decreased telomere length and resulting senescence that occur as part of the normal aging process.
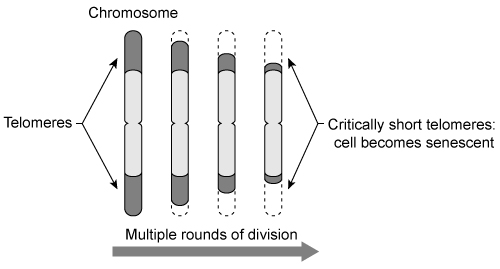 Figure 1Cells that must be able to divide indefinitely (stem cells and germ cells) express an enzyme known as telomerase. Functional telomerase consists of a protein subunit called telomerase reverse transcriptase (TERT) and a noncoding RNA subunit called telomerase RNA (TR). Using a portion of TR as a template, telomerase extends telomeres by continuously adding the sequence 5′-TTAGGG-3′ to the ends of chromosomes. The complement strand is then filled in by DNA polymerase. Telomere extension allows these cells to avoid senescence.In healthy somatic cells, however, TERT transcription is generally downregulated by the absence of the oncogene c-Myc and the presence of the tumor suppressor protein WT1. When telomerase is suppressed, the resulting critical telomere shortening has been hypothesized to prevent uncontrolled cell proliferation in adult tissues. In cancerous somatic cells, on the other hand, increased telomerase activity is often associated with tumorigenesis. WT1 is frequently absent and c-Myc is frequently overexpressed in these cells, leading to increased TERT expression.In addition to transcriptional control, TERT can be regulated at the post-transcriptional level. The TERT gene consists of 16 exons and 15 introns that can be spliced into more than 20 different isoforms in humans. Only one isoform (the active isoform) is known to extend telomeres. However, the i2 isoform, in which intron 2 is partially included in the mature mRNA (Figure 2), has been hypothesized to downregulate residual TERT activity in somatic cells.
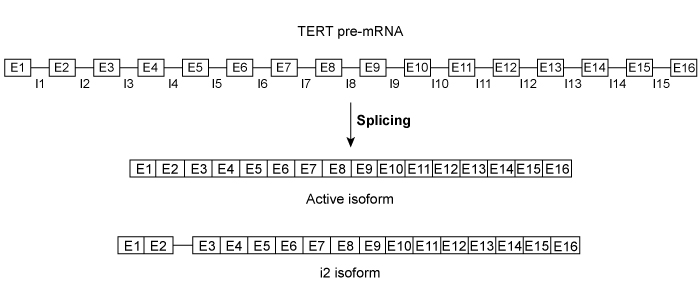 Figure 2
Adapted from Cifuentes-rojas C, Shippen DE. Telomerase regulation. Mutat Res. 2012;730(1-2):20-7.
-If the role of the i2 isoform of the TERT gene proposed in the passage is correct, individuals who express the i2 isoform in somatic cells would be expected to have a decreased risk of:
Figure 1Cells that must be able to divide indefinitely (stem cells and germ cells) express an enzyme known as telomerase. Functional telomerase consists of a protein subunit called telomerase reverse transcriptase (TERT) and a noncoding RNA subunit called telomerase RNA (TR). Using a portion of TR as a template, telomerase extends telomeres by continuously adding the sequence 5′-TTAGGG-3′ to the ends of chromosomes. The complement strand is then filled in by DNA polymerase. Telomere extension allows these cells to avoid senescence.In healthy somatic cells, however, TERT transcription is generally downregulated by the absence of the oncogene c-Myc and the presence of the tumor suppressor protein WT1. When telomerase is suppressed, the resulting critical telomere shortening has been hypothesized to prevent uncontrolled cell proliferation in adult tissues. In cancerous somatic cells, on the other hand, increased telomerase activity is often associated with tumorigenesis. WT1 is frequently absent and c-Myc is frequently overexpressed in these cells, leading to increased TERT expression.In addition to transcriptional control, TERT can be regulated at the post-transcriptional level. The TERT gene consists of 16 exons and 15 introns that can be spliced into more than 20 different isoforms in humans. Only one isoform (the active isoform) is known to extend telomeres. However, the i2 isoform, in which intron 2 is partially included in the mature mRNA (Figure 2), has been hypothesized to downregulate residual TERT activity in somatic cells.
Figure 2
Adapted from Cifuentes-rojas C, Shippen DE. Telomerase regulation. Mutat Res. 2012;730(1-2):20-7.
-If the role of the i2 isoform of the TERT gene proposed in the passage is correct, individuals who express the i2 isoform in somatic cells would be expected to have a decreased risk of: (Multiple Choice)
4.7/5 (83)
(83) Passage
Obstructive respiratory illnesses are characterized by an increased difficulty exhaling much of the air in the lungs. Asthma and chronic obstructive pulmonary disease (COPD) are two of the most common obstructive respiratory illnesses. Asthma is due to allergen hypersensitivity and can be identified by temporary airway inflammation, which causes the bronchioles to narrow. The decreased airway diameter increases the resistance to airflow. Subsequently, air becomes "trapped" in the lungs, restricting the amount of air that can be moved in each breath.COPD refers to a spectrum of disorders and can be a result of emphysema, the irreversible destruction of pulmonary tissue. The breakdown of elastic proteins in the lungs results in a loss of pulmonary resiliency and chronic lung hyperinflation. Because the walls between individual alveoli are broken down, the alveolar sacs that remain are larger.Lung diseases can be diagnosed and monitored using spirometry. A spirometer measures the flow rate and volume of inhaled and exhaled air. In one pulmonary test, a patient is asked to exhale forcibly and completely into a spirometer after maximum inhalation. This test is done to measure the patient's forced expiratory volume in one second (FEV1) and forced vital capacity (FVC), the total amount of air exhaled in a single breath.
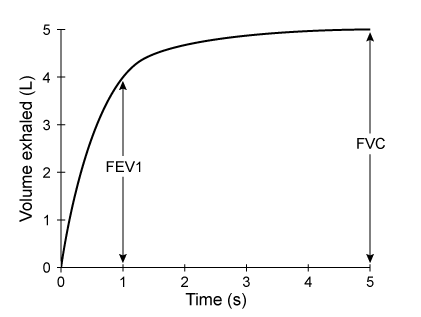 Figure 1 Forced expiratory spirogram of a healthy individual
Adapted from T. Barreiro, "An Approach to Interpreting Spirometry." American Family Physician. ©2004 AAFP.
-According to the passage, which of the following changes would be expected in a patient with signs of emphysema?
Figure 1 Forced expiratory spirogram of a healthy individual
Adapted from T. Barreiro, "An Approach to Interpreting Spirometry." American Family Physician. ©2004 AAFP.
-According to the passage, which of the following changes would be expected in a patient with signs of emphysema? (Multiple Choice)
4.8/5 (77)
(77) Passage
Saliva, a secreted fluid with multiple physiologic functions, is composed of water (~99%), proteins, and electrolytes. Together, these components facilitate nutrient consumption, respiration, and communication. For example, saliva aids in digestion by serving as a lubricant during mastication and by initiating carbohydrate and fat metabolism. In addition, the calcium and phosphate present in saliva promote tooth remineralization, and antimicrobial and chemical buffering agents give saliva protective properties.The gustatory-salivary reflex, the secretion of saliva from the salivary glands in response to gustation (taste), is primarily mediated by the parasympathetic division of the nervous system. In general, parasympathetic pathways originate from the brain stem or the sacral spinal cord. Fibers originating from nuclei in these regions synapse onto ganglia that lie in close proximity to the target organ. Both preganglionic neurons (those originating from the nuclei) and postganglionic neurons (those originating from the ganglia) release acetylcholine (ACh).In the gustatory-salivary reflex, activation of taste receptors in the tongue sends impulses to the superior and inferior salivatory nuclei in the brainstem. Local processing within these nuclei activates the parasympathetic pathways that innervate the salivary glands. Ultimately, ACh released from postganglionic neurons acts on the muscarinic acetylcholine receptors (mAChRs) on the secretory cells of the salivary gland to stimulate salivation (Figure 1).
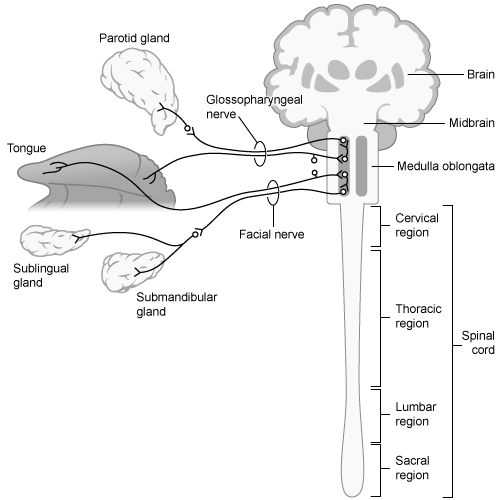 Figure 1 Parasympathetic regulation of salivary secretionSympathetic stimulation of the salivary glands also promotes salivation but to a lesser degree than parasympathetic stimulation. This may contribute to what is often perceived to be decreased salivation when the sympathetic division is more active than its counterpart. Unlike parasympathetic pathways, sympathetic pathways originate in the thoracic and lumbar spinal segments, and the ganglia lie in close proximity to the spinal cord. Although preganglionic neurons of the sympathetic nervous system release ACh, the postganglionic neurons often release norepinephrine.
-During periods of stress, many individuals experience dry mouth caused by decreased salivation. Which of the following functions would also be expected to decrease during periods of stress?
Figure 1 Parasympathetic regulation of salivary secretionSympathetic stimulation of the salivary glands also promotes salivation but to a lesser degree than parasympathetic stimulation. This may contribute to what is often perceived to be decreased salivation when the sympathetic division is more active than its counterpart. Unlike parasympathetic pathways, sympathetic pathways originate in the thoracic and lumbar spinal segments, and the ganglia lie in close proximity to the spinal cord. Although preganglionic neurons of the sympathetic nervous system release ACh, the postganglionic neurons often release norepinephrine.
-During periods of stress, many individuals experience dry mouth caused by decreased salivation. Which of the following functions would also be expected to decrease during periods of stress? (Multiple Choice)
4.9/5 (72)
(72) Passage
At the blood-brain barrier, the cerebral spinal fluid (CSF) is separated from lymphatic circulation by epithelial cells bound by tight junctions. Within the central nervous system (CNS), CSF surrounds and protects the brain and spinal cord and is believed to function in waste clearance for the CNS analogous to the role of the lymphatic system within the body.This waste clearance system has been dubbed the "glymphatic system." Although the mechanism of clearance is largely unknown, specialized glial cells known as astrocytes appear to modify the interstitial volume between neurons. This increase in interstitial volume allows for greater CSF flow, which increases the efficiency of neurotoxic clearance. Waste products removed from the brain include metabolic products such as ammonia and harmful compounds such as amyloid proteins.Recent advances in imaging technology suggest that interstitial clearance may be modified during sleep. To test this hypothesis, researchers indirectly studied changes in interstitial volume by measuring the percentage of CSF coverage in animal models during the first hour of sleep and again during the first hour of wakefulness (Figure 1).
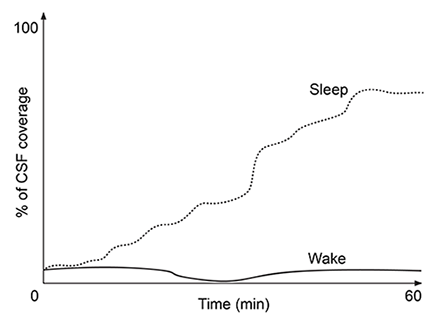 Figure 1. Percentage of CSF coverage of interstitial space during sleep and wakefulness
-Which of the following is true regarding the function of neuroglia in the central and peripheral nervous systems?
Figure 1. Percentage of CSF coverage of interstitial space during sleep and wakefulness
-Which of the following is true regarding the function of neuroglia in the central and peripheral nervous systems? (Multiple Choice)
4.7/5 (86)
(86) Passage
Endometriosis is a chronic, treatable disease of the female reproductive tract associated with infertility and pelvic pain in women of reproductive age. The endometrium, a layer of epithelial tissue that grows and sheds during the menstrual cycle, normally makes up the interior lining of the uterus. In individuals with endometriosis, endometrial tissue is also found ectopically (outside the uterine cavity).The mechanism by which endometrial tissue successfully implants outside the uterine cavity is thought to be dependent on signaling molecules that promote the formation of blood vessels locally. One of these signaling molecules is vascular endothelial growth factor (VEGF), a protein that is normally synthesized and secreted by various tissues in response to reduced oxygen levels. Because VEGF is thought to be implicated in ectopic endometrial tissue growth, researchers hypothesize that the abdominal and pelvic structures of women with endometriosis would contain higher levels of VEGF compared to women without endometriosis.In an experiment, women ages 25-40 were divided into groups based on endometriosis disease status. Individuals on any type of medication were excluded from the study. Using minimally invasive surgery, samples of peritoneal fluid were taken from healthy subjects (n = 19) and from subjects diagnosed with endometriosis (n = 30). An enzyme-linked immunosorbent assay (ELISA) was used to characterize the concentration of VEGF protein present within these samples.In a separate procedure that took place five days after peritoneal fluid collection, uterine endometrial samples were obtained from all subjects and visualized under a microscope to determine the menstrual cycle phase of each participant. Figure 1 shows the level of VEGF in the abdominal fluid categorized by disease status and menstrual cycle phase.
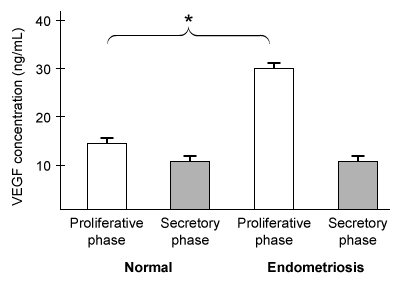 Figure 1 VEGF concentration in sampled peritoneal fluid (Note: * = p < 0.05; Proliferative phase = stage immediately preceding ovulation; Secretory phase = stage immediately following ovulation)
-VEGF signaling also leads to the dilation of existing blood vessels. One function of vasodilation is to:
Figure 1 VEGF concentration in sampled peritoneal fluid (Note: * = p < 0.05; Proliferative phase = stage immediately preceding ovulation; Secretory phase = stage immediately following ovulation)
-VEGF signaling also leads to the dilation of existing blood vessels. One function of vasodilation is to: (Multiple Choice)
4.8/5 (66)
(66) Which of the following would most likely cause an embryo to implant in a location other than the uterine lining?
(Multiple Choice)
4.8/5 (77)
(77) Protein coding genes are composed of multiple codons, sequences of three nucleotides that each code for a specific amino acid. Given that multiple codons may encode a single amino acid, which of the following nucleotide substitutions in a codon would be LEAST likely to affect protein structure?
(Multiple Choice)
4.8/5 (70)
(70) Passage
Hematological anomalies have been observed in patients with prolonged liver damage. For example, patients with chronic cirrhosis (scarring of the liver) often develop anemia and other blood disorders. Hemoglobin is the metalloprotein within red blood cells that is responsible for the oxygen-carrying capacity of blood, and its function may be affected by liver damage. The poor prognosis of patients with cirrhosis and anemia has stimulated further study of hemoglobin function and oxygen saturation.Blood samples from both cirrhotic patients and healthy individuals at rest and after exercise were exposed to varying partial pressures of oxygen. Measurement of oxyhemoglobin dissociation curves (ODCs [Figure 1]) from the blood samples revealed significant functional differences in the hemoglobin from cirrhotic patients relative to control subjects.
Figure 1 Oxyhemoglobin dissociation curve for cirrhotic patients (CP) at rest and for healthy controls (HC) at rest and after 20 minutes of exerciseVitamins are considered nontoxic supplements and are frequently provided to anemic patients to increase red blood cell production. They may therefore have therapeutic benefits for cirrhotic patients. However, some studies indicate that excessive vitamin consumption may lead to oxidative stress that could induce anemia through hemolysis (red blood cell rupturing). Hemoglobin strongly absorbs light at 577 nm, and researchers conducted hemolysis assays by spinning down red blood cells and measuring absorbance (Abs) of the supernatant at 577 nm to determine how much hemoglobin was released. The assay was carried out in the presence of four vitamins to determine their potential as oxidizing agents, and results are shown in Table 1.Table 1 Hemolysis of Red Blood Cells from Healthy Donors Treated With Vitamins [2 mM] for 30 Minutes, Measured by Absorbance at 577 nm
Adapted from Clerbaux T, Detry B, Geubel A, et al. The oxyhemoglobin dissociation curve in liver cirrhosis. Chest. 2006;129(2):438-45.
-Hyperventilation leads to oxygen dissociation curves similar to those seen in patients with cirrhosis when at rest. Based on this information, what physiological change in cirrhotic patients most likely decreases the level of oxygen delivery to tissues?
Figure 1 Oxyhemoglobin dissociation curve for cirrhotic patients (CP) at rest and for healthy controls (HC) at rest and after 20 minutes of exerciseVitamins are considered nontoxic supplements and are frequently provided to anemic patients to increase red blood cell production. They may therefore have therapeutic benefits for cirrhotic patients. However, some studies indicate that excessive vitamin consumption may lead to oxidative stress that could induce anemia through hemolysis (red blood cell rupturing). Hemoglobin strongly absorbs light at 577 nm, and researchers conducted hemolysis assays by spinning down red blood cells and measuring absorbance (Abs) of the supernatant at 577 nm to determine how much hemoglobin was released. The assay was carried out in the presence of four vitamins to determine their potential as oxidizing agents, and results are shown in Table 1.Table 1 Hemolysis of Red Blood Cells from Healthy Donors Treated With Vitamins [2 mM] for 30 Minutes, Measured by Absorbance at 577 nm
Adapted from Clerbaux T, Detry B, Geubel A, et al. The oxyhemoglobin dissociation curve in liver cirrhosis. Chest. 2006;129(2):438-45.
-Hyperventilation leads to oxygen dissociation curves similar to those seen in patients with cirrhosis when at rest. Based on this information, what physiological change in cirrhotic patients most likely decreases the level of oxygen delivery to tissues? (Multiple Choice)
4.9/5 (75)
(75) Passage
Renal reabsorption of glucose is facilitated by sodium-glucose linked transporters (SGLTs), which are secondary active transport proteins located in the apical membrane of the proximal tubular cells in the kidney. SGLT activity determines the transport maximum of glucose Tm, the maximum rate at which the kidneys can reabsorb glucose.Excretion of glucose in the urine (glycosuria) occurs when the glomerular filtration rate (GFR) of glucose exceeds the Tm. Glycosuria is a symptom of diabetes mellitus, a disease marked by hyperglycemia (elevated serum glucose). Uncontrolled hyperglycemia can damage the nerves that innervate urinary tract musculature, resulting in urinary retention (inability to fully empty the bladder) or incontinence (involuntary urine leakage).Canagliflozin is a SGLT inhibitor used for the treatment for diabetes. The effect of canagliflozin on renal glucose reabsorption was tested in a glucose infusion experiment in patients with type 2 diabetes mellitus (T2DM). First, researchers measured the participants' fasting serum glucose levels (average ~80 mg/dL) and then began a continuous intravenous infusion of a glucose solution. The rate of glucose infusion was adjusted such that blood glucose concentration steadily rose to 300 mg/dL. Blood and urine glucose concentrations were measured at 30-minute intervals. The experiment was later repeated in the same patients following canagliflozin administration (100 mg, once a day for seven days). The results of both trials are shown in Figure 1.
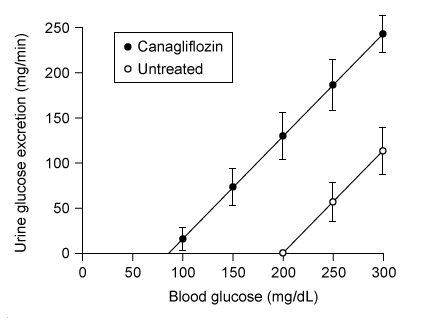 Figure 1 Mean urine glucose excretion versus blood glucose concentration in patients with T2DM, with and without canagliflozin treatmentResearchers then estimated the new Tm of glucose following canagliflozin treatment (Figure 2). Canagliflozin was found to also lower fasting blood glucose in individuals with T2DM. Side effects included weight loss, increased urinary frequency, excessive thirst, and blood pressure reduction.
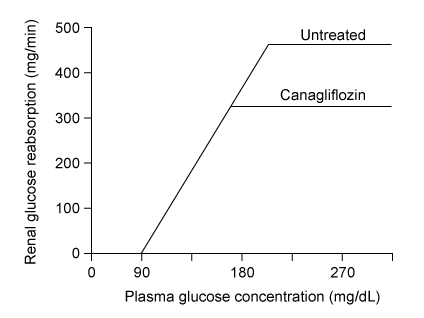 Figure 2 Mean rate of renal glucose reabsorption versus plasma glucose concentration in patients with T2DM, with and without canagliflozin treatment
-Urinary retention in patients with poorly controlled diabetes mellitus is most likely the result of nerve damage impairing smooth muscle contraction in which of the following structures?
Figure 1 Mean urine glucose excretion versus blood glucose concentration in patients with T2DM, with and without canagliflozin treatmentResearchers then estimated the new Tm of glucose following canagliflozin treatment (Figure 2). Canagliflozin was found to also lower fasting blood glucose in individuals with T2DM. Side effects included weight loss, increased urinary frequency, excessive thirst, and blood pressure reduction.
Figure 2 Mean rate of renal glucose reabsorption versus plasma glucose concentration in patients with T2DM, with and without canagliflozin treatment
-Urinary retention in patients with poorly controlled diabetes mellitus is most likely the result of nerve damage impairing smooth muscle contraction in which of the following structures? (Multiple Choice)
4.9/5 (80)
(80) Passage
The Namibian cheetah (Acinonyx jubatus jubatus), the world's fastest land-dwelling animal, hunts across the African grasslands using high-speed sprints. Cheetahs possess unique anatomical features specialized for speed, including an aerodynamic skull, elongated legs, and an enlarged heart. These physiological adaptations have occurred over time and allow cheetahs to achieve speeds greater than 100 km/h. However, due to their small body and slender limbs, cheetahs (50-64 kg) are limited with regard to the size of the animals they can successfully hunt and therefore typically prey on slightly smaller species that inhabit open grasslands.It is believed that around 12,000 years ago, Namibian cheetahs experienced an environmental catastrophe that drastically reduced their population. The small number of surviving cheetahs began mating with one another, which led to severe inbreeding depression. Over time, the offspring of subsequent generations exhibited decreased fitness, reduced fecundity (number of offspring), and sustained a loss of major histocompatibility complex (MHC) allele diversity. To study if low MHC diversity correlates with low fitness in cheetahs, scientists analyzed the genetic diversity and disease prevalence in a group of free-ranging and captive male cheetahs.Experiment 1MHC allele genotyping and analysis was performed in wild (free-ranging) and captive male cheetahs (Figure 1). Because MHC diversity is strongly correlated with genetic diversity, MHC diversity is used as a marker for an organism's overall genetic variability.
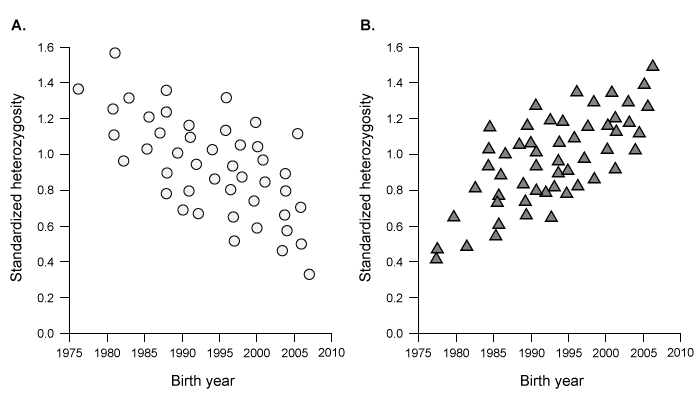 Figure 1 Evaluation of heterozygosity in (A) wild and (B) captive male cheetahs born between 1976 and 2007 (Note: Each data point represents a single male cheetah.)Experiment 2Disease prevalence was evaluated in wild and captive male cheetahs by quantitative analysis of symptoms relating gastrointestinal, liver, and kidney disease. The percentages of cheetahs affected by each disease are shown in Figure 2.
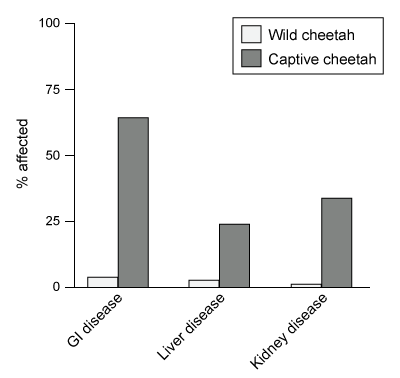 Figure 2 Evaluation of disease prevalence in wild and captive male cheetahsExperiment 3Fecal cortisol levels were noninvasively evaluated in wild and captive cheetahs over a period of 6 months (Figure 3).
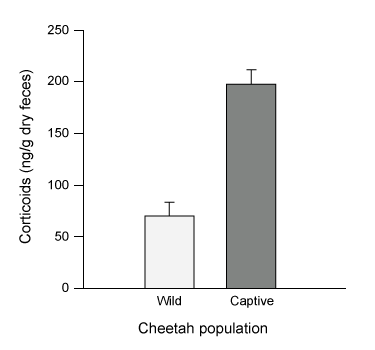 Figure 3 Average fecal cortisol concentrations of wild and captive male cheetahs
Adapted from Castro-prieto A, Wachter B, Sommer S. Cheetah paradigm revisited: MHC diversity in the world's largest free-ranging population. Mol Biol Evol. 2011;28(4):1455-68.
-Researchers concluded that captive cheetahs have reduced fitness because of their increased susceptibility to diseases. What can best explain the decreased fitness of captive cheetahs?
Figure 1 Evaluation of heterozygosity in (A) wild and (B) captive male cheetahs born between 1976 and 2007 (Note: Each data point represents a single male cheetah.)Experiment 2Disease prevalence was evaluated in wild and captive male cheetahs by quantitative analysis of symptoms relating gastrointestinal, liver, and kidney disease. The percentages of cheetahs affected by each disease are shown in Figure 2.
Figure 2 Evaluation of disease prevalence in wild and captive male cheetahsExperiment 3Fecal cortisol levels were noninvasively evaluated in wild and captive cheetahs over a period of 6 months (Figure 3).
Figure 3 Average fecal cortisol concentrations of wild and captive male cheetahs
Adapted from Castro-prieto A, Wachter B, Sommer S. Cheetah paradigm revisited: MHC diversity in the world's largest free-ranging population. Mol Biol Evol. 2011;28(4):1455-68.
-Researchers concluded that captive cheetahs have reduced fitness because of their increased susceptibility to diseases. What can best explain the decreased fitness of captive cheetahs? (Multiple Choice)
4.7/5 (93)
(93) Compared with blood in the pulmonary veins, blood in the pulmonary arteries has higher concentrations of:O2H+CO2
(Multiple Choice)
4.9/5 (82)
(82) Passage
Beta-thalassemia is a blood disorder caused by reduced production of the β-globin subunit of hemoglobin. The erythrocytes in patients with beta-thalassemia are abnormally small, lack sufficient functional hemoglobin, and are decreased in number. These individuals require lifelong blood transfusions to correct their erythrocyte shortage. Each unit of blood transfused contains many milligrams of iron and, consequently, blood iron levels increase due to repeated transfusions. The excess iron is then continuously deposited in the organs, leading to organ damage.Transferrin (Tf) is a protein that binds free iron in the blood and plays a key role in erythropoiesis, which requires uptake of iron from the blood in a process facilitated by Tf and its cell surface receptor (TfR). Iron-bound Tf, known as holotransferrin (holoTf), binds TfR to form a complex that is brought into the developing erythrocyte in an endosome. Acidification of the endosome triggers a conformational change in holoTf, which allows the release of free iron into the cell and the recycling of the remaining complex components to the cell surface. Non-iron-bound Tf is referred to as apotransferrin (apoTf), and due to its iron-binding capability, researchers believe that apoTf injections may help prevent deposition of excess iron in the organs of patients with beta-thalassemia.To investigate the effect of apoTf administration in a mouse model of beta-thalassemia, mice homozygous for an inactivating deletion in the murine β-globin gene (Hbbth−3/Hbbth−3) were given blood transfusions followed by apoTf injection. Measurements of non-transferrin-bound iron in the blood (NTBI), plasma holoTf, and urinary holoTf were taken immediately and at 15 days post-injection. Results revealed that NTBI decreased over the tested period. Experimenters hypothesized that apoTf mediated certain regulatory changes that reduced NTBI in Hbbth−3/Hbbth−3 mice by increasing urinary holoTf excretion.
-ApoTf and TfR were analyzed by SDS-PAGE under nonreducing and reducing conditions. Based on the gels shown, which conclusion is LEAST likely to be true? 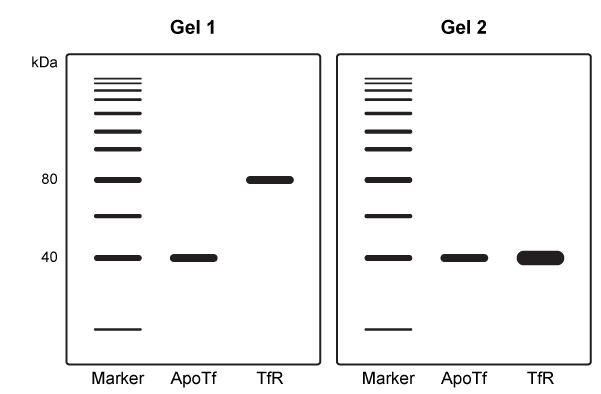
(Multiple Choice)
4.9/5 (76)
(76) Passage
Renal reabsorption of glucose is facilitated by sodium-glucose linked transporters (SGLTs), which are secondary active transport proteins located in the apical membrane of the proximal tubular cells in the kidney. SGLT activity determines the transport maximum of glucose Tm, the maximum rate at which the kidneys can reabsorb glucose.Excretion of glucose in the urine (glycosuria) occurs when the glomerular filtration rate (GFR) of glucose exceeds the Tm. Glycosuria is a symptom of diabetes mellitus, a disease marked by hyperglycemia (elevated serum glucose). Uncontrolled hyperglycemia can damage the nerves that innervate urinary tract musculature, resulting in urinary retention (inability to fully empty the bladder) or incontinence (involuntary urine leakage).Canagliflozin is a SGLT inhibitor used for the treatment for diabetes. The effect of canagliflozin on renal glucose reabsorption was tested in a glucose infusion experiment in patients with type 2 diabetes mellitus (T2DM). First, researchers measured the participants' fasting serum glucose levels (average ~80 mg/dL) and then began a continuous intravenous infusion of a glucose solution. The rate of glucose infusion was adjusted such that blood glucose concentration steadily rose to 300 mg/dL. Blood and urine glucose concentrations were measured at 30-minute intervals. The experiment was later repeated in the same patients following canagliflozin administration (100 mg, once a day for seven days). The results of both trials are shown in Figure 1.
Figure 1 Mean urine glucose excretion versus blood glucose concentration in patients with T2DM, with and without canagliflozin treatmentResearchers then estimated the new Tm of glucose following canagliflozin treatment (Figure 2). Canagliflozin was found to also lower fasting blood glucose in individuals with T2DM. Side effects included weight loss, increased urinary frequency, excessive thirst, and blood pressure reduction.
Figure 2 Mean rate of renal glucose reabsorption versus plasma glucose concentration in patients with T2DM, with and without canagliflozin treatment
-The critical concentration of plasma glucose necessary to induce glycosuria is termed the renal threshold of glucose. Compared to untreated T2DM patients, the renal threshold of glucose in T2DM patients treated with canagliflozin is:
Figure 1 Mean urine glucose excretion versus blood glucose concentration in patients with T2DM, with and without canagliflozin treatmentResearchers then estimated the new Tm of glucose following canagliflozin treatment (Figure 2). Canagliflozin was found to also lower fasting blood glucose in individuals with T2DM. Side effects included weight loss, increased urinary frequency, excessive thirst, and blood pressure reduction.
Figure 2 Mean rate of renal glucose reabsorption versus plasma glucose concentration in patients with T2DM, with and without canagliflozin treatment
-The critical concentration of plasma glucose necessary to induce glycosuria is termed the renal threshold of glucose. Compared to untreated T2DM patients, the renal threshold of glucose in T2DM patients treated with canagliflozin is: (Multiple Choice)
4.8/5 (62)
(62) A male patient was born with an abnormal opening in the muscular wall separating the two ventricles of the heart. The opening allows blood to flow from the left to the right ventricle. If left untreated, this cardiac defect may cause any of the following in the patient EXCEPT:
(Multiple Choice)
4.9/5 (73)
(73) Passage
Rheumatoid arthritis (RA) is an autoimmune disease that causes chronic synovial (joint) inflammation. RA immunopathogenesis involves LFA-1, a surface receptor found on leukocytes that is composed of an α-chain (CD11a) and a β-chain (CD18). The binding of LFA-1 to ICAM-1, an adhesion protein on the surface of B cells and endothelial cells, stimulates the migration of leukocytes to specific areas of inflammation. After successful LFA-1/ICAM-1 binding, CD18 is released into the plasma and synovial fluid (SF), where it exists in soluble form (sCD18). The levels of sCD18 in SF can be used as a marker for inflammation in RA.CD18 release has been shown to increase in response to tumor necrosis factor (TNF), a pro-inflammatory cytokine involved in the inflammatory response of RA. In patients with newly diagnosed and untreated RA (eRA), leukocytes produce adequate quantities of LFA-1 and plasma sCD18 levels are unchanged. However, over time there is dysregulation of LFA-1 synthesis and an increase in competition for ICAM-1 by other ligands, leading to a reduction in CD18 shedding. As a result, sCD18 is decreased in patients with chronic RA (cRA).Experiment 1An immunofluorescence assay was used to measure plasma sCD18 levels in patients with eRA and cRA, and in age- and gender-matched healthy controls (HC).
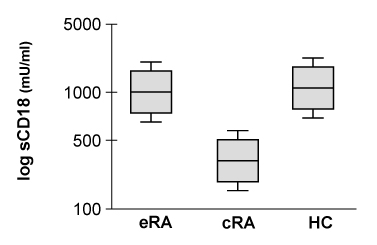 Figure 1 Baseline sCD18 measurements (Note: 50% of data points are below the median value; median = line inside the box.)Experiment 2Clinical assessments were performed in eRA patients to establish a baseline disease status. eRA patients were assigned DAS28CRP scores measured by RA-specific laboratory values. This was followed by treatment with anti-inflammatory drugs. DAS28CRP scores were calculated at 3-month intervals for 12 months, with lower scores indicating decreased RA severity (Figure 2).
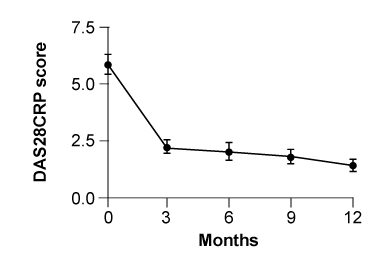 Figure 2 DAS28CRP scores in eRA patientsExperiment 3Heterogeneous populations of mononuclear cells were cultured from the synovial fluid (SFMC) and peripheral blood (PBMC) of eRA patients during an acute exacerbation of their symptoms. sCD18 levels were measured in SFMCs and PBMCs that were untreated, treated with TNF, or treated with monoclonal antibodies targeting TNF (anti-TNF).
Adapted from Kragstrup TW, Jalilian B, Keller KK, et al. Changes in Soluble CD18 in Murine Autoimmune Arthritis and Rheumatoid Arthritis Reflect Disease Establishment and Treatment Response. PLoS ONE. 2016;11(2):e0148486.
-A self-directed antibody known as rheumatoid factor (RF) has been found to be involved in RA-mediated inflammation. RF is an antibody that targets a patient's own IgG antibodies, which results in the formation of immune complexes that induce an inflammatory response. High concentrations of self-antibodies such as RF are NOT typically found in the human body because:
Figure 1 Baseline sCD18 measurements (Note: 50% of data points are below the median value; median = line inside the box.)Experiment 2Clinical assessments were performed in eRA patients to establish a baseline disease status. eRA patients were assigned DAS28CRP scores measured by RA-specific laboratory values. This was followed by treatment with anti-inflammatory drugs. DAS28CRP scores were calculated at 3-month intervals for 12 months, with lower scores indicating decreased RA severity (Figure 2).
Figure 2 DAS28CRP scores in eRA patientsExperiment 3Heterogeneous populations of mononuclear cells were cultured from the synovial fluid (SFMC) and peripheral blood (PBMC) of eRA patients during an acute exacerbation of their symptoms. sCD18 levels were measured in SFMCs and PBMCs that were untreated, treated with TNF, or treated with monoclonal antibodies targeting TNF (anti-TNF).
Adapted from Kragstrup TW, Jalilian B, Keller KK, et al. Changes in Soluble CD18 in Murine Autoimmune Arthritis and Rheumatoid Arthritis Reflect Disease Establishment and Treatment Response. PLoS ONE. 2016;11(2):e0148486.
-A self-directed antibody known as rheumatoid factor (RF) has been found to be involved in RA-mediated inflammation. RF is an antibody that targets a patient's own IgG antibodies, which results in the formation of immune complexes that induce an inflammatory response. High concentrations of self-antibodies such as RF are NOT typically found in the human body because: (Multiple Choice)
4.9/5 (81)
(81) Passage
Obstructive respiratory illnesses are characterized by an increased difficulty exhaling much of the air in the lungs. Asthma and chronic obstructive pulmonary disease (COPD) are two of the most common obstructive respiratory illnesses. Asthma is due to allergen hypersensitivity and can be identified by temporary airway inflammation, which causes the bronchioles to narrow. The decreased airway diameter increases the resistance to airflow. Subsequently, air becomes "trapped" in the lungs, restricting the amount of air that can be moved in each breath.COPD refers to a spectrum of disorders and can be a result of emphysema, the irreversible destruction of pulmonary tissue. The breakdown of elastic proteins in the lungs results in a loss of pulmonary resiliency and chronic lung hyperinflation. Because the walls between individual alveoli are broken down, the alveolar sacs that remain are larger.Lung diseases can be diagnosed and monitored using spirometry. A spirometer measures the flow rate and volume of inhaled and exhaled air. In one pulmonary test, a patient is asked to exhale forcibly and completely into a spirometer after maximum inhalation. This test is done to measure the patient's forced expiratory volume in one second (FEV1) and forced vital capacity (FVC), the total amount of air exhaled in a single breath.
Figure 1 Forced expiratory spirogram of a healthy individual
Adapted from T. Barreiro, "An Approach to Interpreting Spirometry." American Family Physician. ©2004 AAFP.
-The regulation of respiratory rate is normally most sensitive to:
Figure 1 Forced expiratory spirogram of a healthy individual
Adapted from T. Barreiro, "An Approach to Interpreting Spirometry." American Family Physician. ©2004 AAFP.
-The regulation of respiratory rate is normally most sensitive to: (Multiple Choice)
4.8/5 (85)
(85) A physician determines that a patient has injured a connective tissue structure connecting two bones within the knee joint. Given this finding, the likely basis of the injury is damage to:
(Multiple Choice)
4.8/5 (72)
(72) 
Filters
- Essay(0)
- Multiple Choice(0)
- Short Answer(0)
- True False(0)
- Matching(0)