Exam 2: STEP 2 CS - Practice Cases

arrow
  • Select Tags
search iconSearch Question
  • Select Tags

Doorway information about patient The patient is a 65-year-old woman who comes to the emergency department due to arm and leg weakness. Vital signs Temperature: 36.7 C (98.1 F) Blood pressure: 160/90 mm Hg Pulse: 78/min Respirations: 22/min Basic differential diagnosis Neurologic Stroke Transient ischemic attack (TIA) Subarachnoid hemorrhage Subdural hematoma Intracranial mass Guillain-Barré syndrome Spinal cord lesion Complex migraine Metabolic Hypoglycemia Hypothyroidism Adrenal insufficiency Electrolyte disorders Musculoskeletal Myopathy Miscellaneous Conversion disorder Heat-related illness

Free
(Essay)
4.9/5
(87)
Correct Answer:
Verified

Instructions:
If the doctor asks you about anything other than these, just say "no," or provide an answer that a normal patient might give.
You are a 65-year-old woman who comes to the emergency department with 1 hour of right arm and leg weakness.
History of present illness
The symptoms started an hour ago with weakness in the right arm and leg
Gradually increasing numbness
Moderate (5/10 in severity) headache that is felt "all over" the head
Nausea but no vomiting
No slurred speech or difficulty swallowing
No blurred or double vision
No recent falls or loss of consciousness
No symptoms like this in the past
Review of systems
No fever
No chest pain or palpitations
No diarrhea or constipation
No urinary symptoms
No seizures
Past medical/family/social history
High blood pressure for 25 years
High cholesterol
Heart attack 6 years ago; heart bypass surgery at that time
Medications:  Simvastatin 20 mg daily, aspirin 81 mg daily, atenolol 50 mg daily
Medication allergies:  None
Both parents had hypertension and died in their 60s of heart attacks
Widow (husband died 8 years ago); lives alone
Brought to the hospital by neighbor ("Steve") who is closest contact and is "like a son to me"
Tobacco:  2 packs of cigarettes a day for 35 years and quit 6 years ago
Alcohol:  1-2 drinks, once a month
Recreational drugs:  None
Physical examination
Neurological:
Weaker on the right side of the body
Unable to lift right leg or arm without assistance
Unable to stand
Cranial nerves are normal
Reflexes are slightly exaggerated on the right
Babinski:  Upgoing on right and downgoing on left
Sensation is normal on both sides of body
The rest of the examination is normal.
Ask this question:  If the examinee does not discuss the possibility of a stroke, ask, "Doctor, is it a stroke?"
Checklist:
Following the encounter, check which of the following items were performed by the examinee.
History of present illness/review of systems
Asked about the onset of weakness
Asked where the weakness is felt
Asked if the weakness is changing over time
Asked how you felt prior to onset of the weakness
Asked about associated symptoms Sensory changes or numbness
Loss of consciousness
Seizures/jerky movements
Fever
Nausea/vomiting
Chest pain, palpitations
Problems with speech or swallowing
Visual changes (eg, blurred vision, double vision)
Incontinence/bowel or bladder dysfunction
Asked about a history of frequent falls/spells
Asked about any history of recent head trauma
Past/family/social history
Asked about similar symptoms in the past
Asked about past/other medical issues (especially hypertension, diabetes mellitus, hypercholesterolemia, myocardial infarction, strokes, migraine headaches)
Asked about previous hospitalizations and surgeries
Asked about current medications
Asked about medication allergies
Asked about any family history of strokes, heart attacks, or aneurysms
Asked about smoking
Asked about alcohol intake
Asked about living situation
Examination
Examinee washed hands before examination
Examined without gown, not through gown
Checked cranial nerves II-XII
Tested muscle power bilaterally
Checked deep-tendon reflexes in both the upper/lower extremities
Checked for sensory modalities proximally and distally
Checked cerebellar function (eg, Romberg test)
Checked coordination and gait
Listened for carotid bruit
Checked for neck stiffness
Auscultated heart
Counseling
Explained the physical findings and possible diagnosis
Explained further workup
Communication skills and professional conduct
Knocked before entering the room
Introduced self and greeted you warmly
Used your name to address you
Paid attention to what you said and maintained good eye contact
Asked open-ended questions
Asked non-leading questions
Asked one question at a time
Listened to what you said without interrupting
Used plain English rather than technical jargon
Used appropriate transition sentences
Used appropriate draping techniques
Expressed empathy and made appropriate reassurances
Asked whether you had any concerns/questions
Differential diagnosis
Stroke
Transient ischemic attack (TIA)
Subarachnoid hemorrhage
Diagnostic study/studies
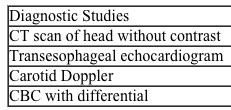
CBC with differential
Basic metabolic panel (or glucose and electrolytes)
CT scan of the head without contrast
Doppler ultrasound of the carotid arteries
ECG
Transesophageal echocardiogram
Case 3 Patient Note
The following represents a typical note for this patient encounter. The details may vary depending on the information given by the simulated patient.
History:  Describe the history you just obtained from this patient.  Include only information (pertinent positives and negatives) relevant to this patient's problem(s).
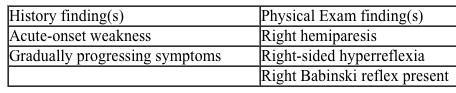
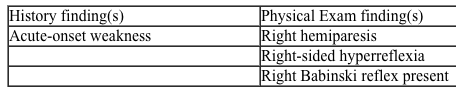
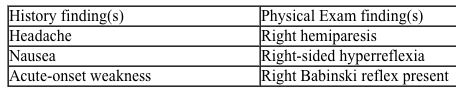
65-yo female with an hour of acute-onset, right-sided weakness and headache.
Gradually progressing symptoms over the past hour.
Nausea without vomiting.
No history of fall or syncope.
ROS:  No fever, chest pain, shortness of breath, vision changes, dysarthria, seizures
PMHx:  HTN, hypercholesterolemia, CAD
PSHx:  CABG 6 years ago
Meds:  Aspirin, simvastatin, atenolol
Allergies: None
FHx:  Mother and father had HTN and died of MI, brother has HTN and hypercholesterolemia
SHx:  Smoked 2 PPD for 35 years but quit 6 years ago
Physical examination:  Describe any positive and negative findings relevant to this patient's problem(s).  Be careful to include only those parts of the examination performed in this encounter.
Vital signs:  Temperature, 36.8 C (98.2 F); blood pressure, 160/90 mm Hg; pulse, 78/min; and respirations, 16/min
Lungs:  CTA bilaterally
Heart:  RRR without M/G/R
Neurological:  A&O ×3, CN 2-12 intact, motor 5/5 on LUE and LLE but 3/5 in RUE and RLE, sensory grossly intact, DTR 2+ on left but 3+ in RUE and RLE, upgoing toes on right and downgoing on left, gait unable to be assessed
Data interpretation:  Based on what you have learned from the history and physical examination, list up to 3 diagnoses that might explain this patient's complaint(s).  List your diagnoses from most to least likely.  For some cases, fewer than 3 diagnoses will be appropriate.  Then, enter the positive or negative findings from the history and the physical examination (if present) that support each diagnosis.  Lastly, list initial diagnostic studies (if any) you would order for each listed diagnosis (e.g., restricted physical examination maneuvers, laboratory tests, imaging, ECG, etc.).
Diagnosis #1:  Evolving stroke
Instructions:  <strong>If the doctor asks you about anything other than these, just say no, or provide an answer that a normal patient might give.</strong> You are a 65-year-old woman who comes to the emergency department with 1 hour of right arm and leg weakness. <strong>History of present illness</strong>  The symptoms started an hour ago with weakness in the right arm and leg  Gradually increasing numbness  Moderate (5/10 in severity) headache that is felt all over the head  Nausea but no vomiting  No slurred speech or difficulty swallowing  No blurred or double vision  No recent falls or loss of consciousness  No symptoms like this in the past <strong>Review of systems</strong>  No fever  No chest pain or palpitations  No diarrhea or constipation  No urinary symptoms  No seizures <strong>Past medical/family/social history</strong>  High blood pressure for 25 years  High cholesterol  Heart attack 6 years ago; heart bypass surgery at that time  Medications:  Simvastatin 20 mg daily, aspirin 81 mg daily, atenolol 50 mg daily  Medication allergies:  None  Both parents had hypertension and died in their 60s of heart attacks  Widow (husband died 8 years ago); lives alone  Brought to the hospital by neighbor (Steve) who is closest contact and is like a son to me  Tobacco:  2 packs of cigarettes a day for 35 years and quit 6 years ago  Alcohol:  1-2 drinks, once a month  Recreational drugs:  None <strong>Physical examination</strong> Neurological:  Weaker on the right side of the body  Unable to lift right leg or arm without assistance  Unable to stand  Cranial nerves are normal  Reflexes are slightly exaggerated on the right  Babinski:  Upgoing on right and downgoing on left  Sensation is normal on both sides of body The rest of the examination is normal. <strong>Ask this question:  If the examinee does not discuss the possibility of a stroke, ask, Doctor, is it a stroke?</strong>  Checklist:  Following the encounter, check which of the following items were performed by the examinee. <strong>History of present illness/review of systems</strong>  Asked about the onset of weakness  Asked where the weakness is felt  Asked if the weakness is changing over time  Asked how you felt prior to onset of the weakness  Asked about associated symptoms Sensory changes or numbness  Loss of consciousness  Seizures/jerky movements  Fever  Nausea/vomiting  Chest pain, palpitations  Problems with speech or swallowing  Visual changes (eg, blurred vision, double vision)  Incontinence/bowel or bladder dysfunction  Asked about a history of frequent falls/spells  Asked about any history of recent head trauma <strong>Past/family/social history</strong>  Asked about similar symptoms in the past  Asked about past/other medical issues (especially hypertension, diabetes mellitus, hypercholesterolemia, myocardial infarction, strokes, migraine headaches)  Asked about previous hospitalizations and surgeries  Asked about current medications  Asked about medication allergies  Asked about any family history of strokes, heart attacks, or aneurysms  Asked about smoking  Asked about alcohol intake  Asked about living situation <strong>Examination</strong>  Examinee washed hands before examination  Examined without gown, not through gown  Checked cranial nerves II-XII  Tested muscle power bilaterally  Checked deep-tendon reflexes in both the upper/lower extremities  Checked for sensory modalities proximally and distally  Checked cerebellar function (eg, Romberg test)  Checked coordination and gait  Listened for carotid bruit  Checked for neck stiffness  Auscultated heart <strong>Counseling</strong>  Explained the physical findings and possible diagnosis  Explained further workup <strong>Communication skills and professional conduct</strong>  Knocked before entering the room  Introduced self and greeted you warmly  Used your name to address you  Paid attention to what you said and maintained good eye contact  Asked open-ended questions  Asked non-leading questions  Asked one question at a time  Listened to what you said without interrupting  Used plain English rather than technical jargon  Used appropriate transition sentences  Used appropriate draping techniques  Expressed empathy and made appropriate reassurances  Asked whether you had any concerns/questions <strong>Differential diagnosis</strong>  Stroke  Transient ischemic attack (TIA)  Subarachnoid hemorrhage <strong>Diagnostic study/studies</strong>  CBC with differential  Basic metabolic panel (or glucose and electrolytes)  CT scan of the head without contrast  Doppler ultrasound of the carotid arteries  ECG  Transesophageal echocardiogram <strong>Case 3 Patient Note</strong> <strong>The following represents a typical note for this patient encounter. The details may vary depending on the information given by the simulated patient.</strong> <strong>History:</strong>  Describe the history you just obtained from this patient.  Include only information (pertinent positives and negatives) relevant to this patient's problem(s).  65-yo female with an hour of acute-onset, right-sided weakness and headache.  Gradually progressing symptoms over the past hour.  Nausea without vomiting.  No history of fall or syncope. ROS:  No fever, chest pain, shortness of breath, vision changes, dysarthria, seizures PMHx:  HTN, hypercholesterolemia, CAD PSHx:  CABG 6 years ago Meds:  Aspirin, simvastatin, atenolol Allergies: None FHx:  Mother and father had HTN and died of MI, brother has HTN and hypercholesterolemia SHx:  Smoked 2 PPD for 35 years but quit 6 years ago <strong>Physical examination:</strong>  Describe any positive and negative findings relevant to this patient's problem(s).  Be careful to include only those parts of the examination performed in this encounter.  Vital signs:  Temperature, 36.8 C (98.2 F); blood pressure, 160/90 mm Hg; pulse, 78/min; and respirations, 16/min  Lungs:  CTA bilaterally  Heart:  RRR without M/G/R  Neurological:  A&O ×3, CN 2-12 intact, motor 5/5 on LUE and LLE but 3/5 in RUE and RLE, sensory grossly intact, DTR 2+ on left but 3+ in RUE and RLE, upgoing toes on right and downgoing on left, gait unable to be assessed <strong>Data interpretation:</strong>  Based on what you have learned from the history and physical examination, list up to 3 diagnoses that might explain this patient's complaint(s).  List your diagnoses from most to least likely.  For some cases, fewer than 3 diagnoses will be appropriate.  Then, enter the positive or negative findings from the history and the physical examination (if present) that support each diagnosis.  Lastly, list initial diagnostic studies (if any) you would order for each listed diagnosis (e.g., restricted physical examination maneuvers, laboratory tests, imaging, ECG, etc.). <strong>Diagnosis #1:  Evolving stroke</strong>     <strong>Diagnosis #2:  TIA or reversible ischemic neurological deficit</strong>     <strong>Diagnosis #3:  Subarachnoid hemorrhage</strong>
Diagnosis #2:  TIA or reversible ischemic neurological deficit
Instructions:  <strong>If the doctor asks you about anything other than these, just say no, or provide an answer that a normal patient might give.</strong> You are a 65-year-old woman who comes to the emergency department with 1 hour of right arm and leg weakness. <strong>History of present illness</strong>  The symptoms started an hour ago with weakness in the right arm and leg  Gradually increasing numbness  Moderate (5/10 in severity) headache that is felt all over the head  Nausea but no vomiting  No slurred speech or difficulty swallowing  No blurred or double vision  No recent falls or loss of consciousness  No symptoms like this in the past <strong>Review of systems</strong>  No fever  No chest pain or palpitations  No diarrhea or constipation  No urinary symptoms  No seizures <strong>Past medical/family/social history</strong>  High blood pressure for 25 years  High cholesterol  Heart attack 6 years ago; heart bypass surgery at that time  Medications:  Simvastatin 20 mg daily, aspirin 81 mg daily, atenolol 50 mg daily  Medication allergies:  None  Both parents had hypertension and died in their 60s of heart attacks  Widow (husband died 8 years ago); lives alone  Brought to the hospital by neighbor (Steve) who is closest contact and is like a son to me  Tobacco:  2 packs of cigarettes a day for 35 years and quit 6 years ago  Alcohol:  1-2 drinks, once a month  Recreational drugs:  None <strong>Physical examination</strong> Neurological:  Weaker on the right side of the body  Unable to lift right leg or arm without assistance  Unable to stand  Cranial nerves are normal  Reflexes are slightly exaggerated on the right  Babinski:  Upgoing on right and downgoing on left  Sensation is normal on both sides of body The rest of the examination is normal. <strong>Ask this question:  If the examinee does not discuss the possibility of a stroke, ask, Doctor, is it a stroke?</strong>  Checklist:  Following the encounter, check which of the following items were performed by the examinee. <strong>History of present illness/review of systems</strong>  Asked about the onset of weakness  Asked where the weakness is felt  Asked if the weakness is changing over time  Asked how you felt prior to onset of the weakness  Asked about associated symptoms Sensory changes or numbness  Loss of consciousness  Seizures/jerky movements  Fever  Nausea/vomiting  Chest pain, palpitations  Problems with speech or swallowing  Visual changes (eg, blurred vision, double vision)  Incontinence/bowel or bladder dysfunction  Asked about a history of frequent falls/spells  Asked about any history of recent head trauma <strong>Past/family/social history</strong>  Asked about similar symptoms in the past  Asked about past/other medical issues (especially hypertension, diabetes mellitus, hypercholesterolemia, myocardial infarction, strokes, migraine headaches)  Asked about previous hospitalizations and surgeries  Asked about current medications  Asked about medication allergies  Asked about any family history of strokes, heart attacks, or aneurysms  Asked about smoking  Asked about alcohol intake  Asked about living situation <strong>Examination</strong>  Examinee washed hands before examination  Examined without gown, not through gown  Checked cranial nerves II-XII  Tested muscle power bilaterally  Checked deep-tendon reflexes in both the upper/lower extremities  Checked for sensory modalities proximally and distally  Checked cerebellar function (eg, Romberg test)  Checked coordination and gait  Listened for carotid bruit  Checked for neck stiffness  Auscultated heart <strong>Counseling</strong>  Explained the physical findings and possible diagnosis  Explained further workup <strong>Communication skills and professional conduct</strong>  Knocked before entering the room  Introduced self and greeted you warmly  Used your name to address you  Paid attention to what you said and maintained good eye contact  Asked open-ended questions  Asked non-leading questions  Asked one question at a time  Listened to what you said without interrupting  Used plain English rather than technical jargon  Used appropriate transition sentences  Used appropriate draping techniques  Expressed empathy and made appropriate reassurances  Asked whether you had any concerns/questions <strong>Differential diagnosis</strong>  Stroke  Transient ischemic attack (TIA)  Subarachnoid hemorrhage <strong>Diagnostic study/studies</strong>  CBC with differential  Basic metabolic panel (or glucose and electrolytes)  CT scan of the head without contrast  Doppler ultrasound of the carotid arteries  ECG  Transesophageal echocardiogram <strong>Case 3 Patient Note</strong> <strong>The following represents a typical note for this patient encounter. The details may vary depending on the information given by the simulated patient.</strong> <strong>History:</strong>  Describe the history you just obtained from this patient.  Include only information (pertinent positives and negatives) relevant to this patient's problem(s).  65-yo female with an hour of acute-onset, right-sided weakness and headache.  Gradually progressing symptoms over the past hour.  Nausea without vomiting.  No history of fall or syncope. ROS:  No fever, chest pain, shortness of breath, vision changes, dysarthria, seizures PMHx:  HTN, hypercholesterolemia, CAD PSHx:  CABG 6 years ago Meds:  Aspirin, simvastatin, atenolol Allergies: None FHx:  Mother and father had HTN and died of MI, brother has HTN and hypercholesterolemia SHx:  Smoked 2 PPD for 35 years but quit 6 years ago <strong>Physical examination:</strong>  Describe any positive and negative findings relevant to this patient's problem(s).  Be careful to include only those parts of the examination performed in this encounter.  Vital signs:  Temperature, 36.8 C (98.2 F); blood pressure, 160/90 mm Hg; pulse, 78/min; and respirations, 16/min  Lungs:  CTA bilaterally  Heart:  RRR without M/G/R  Neurological:  A&O ×3, CN 2-12 intact, motor 5/5 on LUE and LLE but 3/5 in RUE and RLE, sensory grossly intact, DTR 2+ on left but 3+ in RUE and RLE, upgoing toes on right and downgoing on left, gait unable to be assessed <strong>Data interpretation:</strong>  Based on what you have learned from the history and physical examination, list up to 3 diagnoses that might explain this patient's complaint(s).  List your diagnoses from most to least likely.  For some cases, fewer than 3 diagnoses will be appropriate.  Then, enter the positive or negative findings from the history and the physical examination (if present) that support each diagnosis.  Lastly, list initial diagnostic studies (if any) you would order for each listed diagnosis (e.g., restricted physical examination maneuvers, laboratory tests, imaging, ECG, etc.). <strong>Diagnosis #1:  Evolving stroke</strong>     <strong>Diagnosis #2:  TIA or reversible ischemic neurological deficit</strong>     <strong>Diagnosis #3:  Subarachnoid hemorrhage</strong>
Diagnosis #3:  Subarachnoid hemorrhage
Instructions:  <strong>If the doctor asks you about anything other than these, just say no, or provide an answer that a normal patient might give.</strong> You are a 65-year-old woman who comes to the emergency department with 1 hour of right arm and leg weakness. <strong>History of present illness</strong>  The symptoms started an hour ago with weakness in the right arm and leg  Gradually increasing numbness  Moderate (5/10 in severity) headache that is felt all over the head  Nausea but no vomiting  No slurred speech or difficulty swallowing  No blurred or double vision  No recent falls or loss of consciousness  No symptoms like this in the past <strong>Review of systems</strong>  No fever  No chest pain or palpitations  No diarrhea or constipation  No urinary symptoms  No seizures <strong>Past medical/family/social history</strong>  High blood pressure for 25 years  High cholesterol  Heart attack 6 years ago; heart bypass surgery at that time  Medications:  Simvastatin 20 mg daily, aspirin 81 mg daily, atenolol 50 mg daily  Medication allergies:  None  Both parents had hypertension and died in their 60s of heart attacks  Widow (husband died 8 years ago); lives alone  Brought to the hospital by neighbor (Steve) who is closest contact and is like a son to me  Tobacco:  2 packs of cigarettes a day for 35 years and quit 6 years ago  Alcohol:  1-2 drinks, once a month  Recreational drugs:  None <strong>Physical examination</strong> Neurological:  Weaker on the right side of the body  Unable to lift right leg or arm without assistance  Unable to stand  Cranial nerves are normal  Reflexes are slightly exaggerated on the right  Babinski:  Upgoing on right and downgoing on left  Sensation is normal on both sides of body The rest of the examination is normal. <strong>Ask this question:  If the examinee does not discuss the possibility of a stroke, ask, Doctor, is it a stroke?</strong>  Checklist:  Following the encounter, check which of the following items were performed by the examinee. <strong>History of present illness/review of systems</strong>  Asked about the onset of weakness  Asked where the weakness is felt  Asked if the weakness is changing over time  Asked how you felt prior to onset of the weakness  Asked about associated symptoms Sensory changes or numbness  Loss of consciousness  Seizures/jerky movements  Fever  Nausea/vomiting  Chest pain, palpitations  Problems with speech or swallowing  Visual changes (eg, blurred vision, double vision)  Incontinence/bowel or bladder dysfunction  Asked about a history of frequent falls/spells  Asked about any history of recent head trauma <strong>Past/family/social history</strong>  Asked about similar symptoms in the past  Asked about past/other medical issues (especially hypertension, diabetes mellitus, hypercholesterolemia, myocardial infarction, strokes, migraine headaches)  Asked about previous hospitalizations and surgeries  Asked about current medications  Asked about medication allergies  Asked about any family history of strokes, heart attacks, or aneurysms  Asked about smoking  Asked about alcohol intake  Asked about living situation <strong>Examination</strong>  Examinee washed hands before examination  Examined without gown, not through gown  Checked cranial nerves II-XII  Tested muscle power bilaterally  Checked deep-tendon reflexes in both the upper/lower extremities  Checked for sensory modalities proximally and distally  Checked cerebellar function (eg, Romberg test)  Checked coordination and gait  Listened for carotid bruit  Checked for neck stiffness  Auscultated heart <strong>Counseling</strong>  Explained the physical findings and possible diagnosis  Explained further workup <strong>Communication skills and professional conduct</strong>  Knocked before entering the room  Introduced self and greeted you warmly  Used your name to address you  Paid attention to what you said and maintained good eye contact  Asked open-ended questions  Asked non-leading questions  Asked one question at a time  Listened to what you said without interrupting  Used plain English rather than technical jargon  Used appropriate transition sentences  Used appropriate draping techniques  Expressed empathy and made appropriate reassurances  Asked whether you had any concerns/questions <strong>Differential diagnosis</strong>  Stroke  Transient ischemic attack (TIA)  Subarachnoid hemorrhage <strong>Diagnostic study/studies</strong>  CBC with differential  Basic metabolic panel (or glucose and electrolytes)  CT scan of the head without contrast  Doppler ultrasound of the carotid arteries  ECG  Transesophageal echocardiogram <strong>Case 3 Patient Note</strong> <strong>The following represents a typical note for this patient encounter. The details may vary depending on the information given by the simulated patient.</strong> <strong>History:</strong>  Describe the history you just obtained from this patient.  Include only information (pertinent positives and negatives) relevant to this patient's problem(s).  65-yo female with an hour of acute-onset, right-sided weakness and headache.  Gradually progressing symptoms over the past hour.  Nausea without vomiting.  No history of fall or syncope. ROS:  No fever, chest pain, shortness of breath, vision changes, dysarthria, seizures PMHx:  HTN, hypercholesterolemia, CAD PSHx:  CABG 6 years ago Meds:  Aspirin, simvastatin, atenolol Allergies: None FHx:  Mother and father had HTN and died of MI, brother has HTN and hypercholesterolemia SHx:  Smoked 2 PPD for 35 years but quit 6 years ago <strong>Physical examination:</strong>  Describe any positive and negative findings relevant to this patient's problem(s).  Be careful to include only those parts of the examination performed in this encounter.  Vital signs:  Temperature, 36.8 C (98.2 F); blood pressure, 160/90 mm Hg; pulse, 78/min; and respirations, 16/min  Lungs:  CTA bilaterally  Heart:  RRR without M/G/R  Neurological:  A&O ×3, CN 2-12 intact, motor 5/5 on LUE and LLE but 3/5 in RUE and RLE, sensory grossly intact, DTR 2+ on left but 3+ in RUE and RLE, upgoing toes on right and downgoing on left, gait unable to be assessed <strong>Data interpretation:</strong>  Based on what you have learned from the history and physical examination, list up to 3 diagnoses that might explain this patient's complaint(s).  List your diagnoses from most to least likely.  For some cases, fewer than 3 diagnoses will be appropriate.  Then, enter the positive or negative findings from the history and the physical examination (if present) that support each diagnosis.  Lastly, list initial diagnostic studies (if any) you would order for each listed diagnosis (e.g., restricted physical examination maneuvers, laboratory tests, imaging, ECG, etc.). <strong>Diagnosis #1:  Evolving stroke</strong>     <strong>Diagnosis #2:  TIA or reversible ischemic neurological deficit</strong>     <strong>Diagnosis #3:  Subarachnoid hemorrhage</strong>

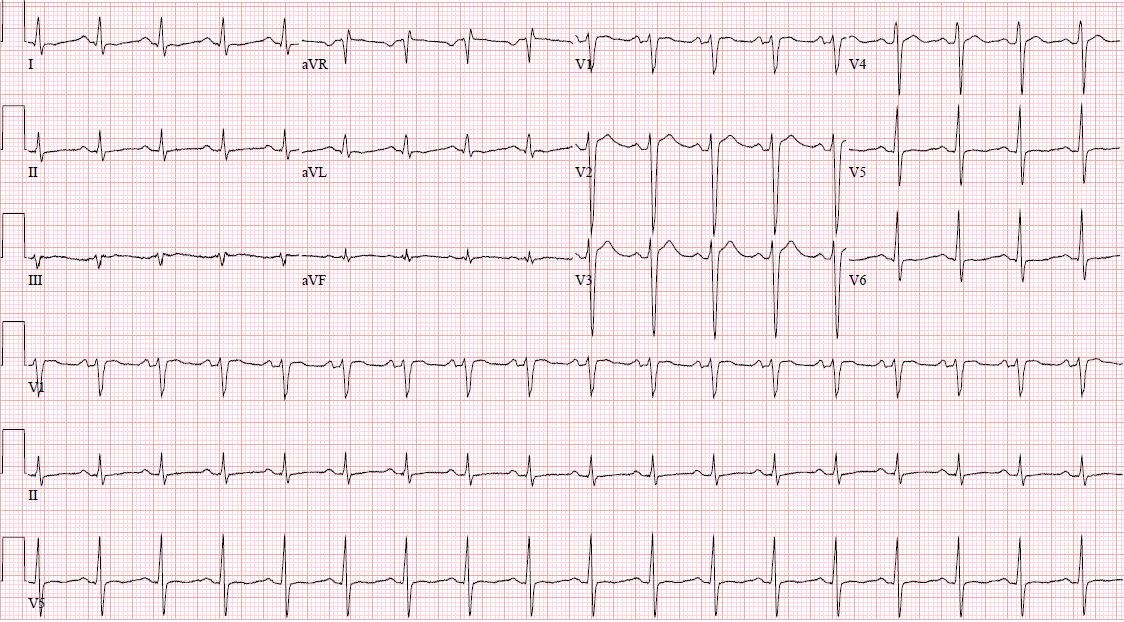
Doorway information about patient The patient is a 29-year-old woman with known sickle cell anemia who comes to the emergency department due to chest pain. Vital signs Temperature: 38.5 C (101.3 F) Blood pressure: 120/75 mm Hg Pulse: 110/min Respirations: 22/min Clinical images Electrocardiogram is shown in the image.<strong>Doorway information about patient</strong> The patient is a 29-year-old woman with known sickle cell anemia who comes to the emergency department due to chest pain. <strong>Vital signs</strong> Temperature: 38.5 C (101.3 F) Blood pressure: 120/75 mm Hg Pulse: 110/min Respirations: 22/min <strong>Clinical images</strong> Electrocardiogram is shown in the image.  <strong>Basic differential diagnosis</strong> Hematologic  Chest syndrome due to sickle cell anemia Cardiovascular  Pericarditis  Acute coronary syndrome Pulmonary  Pneumonia  Pulmonary thromboembolism Musculoskeletal  Costochondritis  Salmonella osteomyelitis Other  Panic attacks Basic differential diagnosis Hematologic Chest syndrome due to sickle cell anemia Cardiovascular Pericarditis Acute coronary syndrome Pulmonary Pneumonia Pulmonary thromboembolism Musculoskeletal Costochondritis Salmonella osteomyelitis Other Panic attacks
Free
(Essay)
4.8/5
(61)
Correct Answer:
Verified

Instructions:
If the doctor asks you about anything other than these, just say "no," or provide an answer that a normal patient might give.
You are a 29-year-old woman who comes to the emergency department with chest pain.
History of present illness
Pain started 12 hours ago
Pain located in the middle of the chest and does not move
Pain started slowly but is increasing and is now 7-8/10 in severity
Pain worse with any movement or deep breathing
Took acetaminophen, which reduced the pain slightly
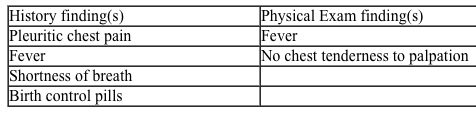
Fever as high as 38.3 C (101 F), cough with green sputum, and mild shortness of breath for the last 3 days
No blood in the sputum or recent chest trauma
Review of systems
No nausea, vomiting, diarrhea, or abdominal pain
No leg pain or swelling
No back pain
No urinary symptoms
Last menstrual period was 2 weeks ago
Past medical/family/social history
Sickle cell anemia: Diagnosed in childhood; had mild pain episodes at that time. 1 transfusion (age 18).  Admitted once for abdominal pain 5 years ago that resolved with supportive care in the hospital.
No surgeries
No pregnancies
Medications: Birth control pill, acetaminophen as needed
Allergies: No drug allergies
Mother also has sickle cell anemia; brother and father are healthy
Occupation: Teacher
Single, sexually active with 1 boyfriend and use condoms regularly
Tobacco: No
Alcohol: No
Recreational drugs: No
Physical examination
Head and neck:
No redness or exudates in the mouth/pharynx
No enlarged lymph nodes
Chest/lungs:
No tenderness to palpation of the chest wall
Clear to auscultation bilaterally
Heart:
Regular rhythm with borderline tachycardia
No murmurs
Abdomen:
Nontender, nondistended
Normoactive bowel sounds throughout
Tympanic to percussion
No hepatosplenomegaly
Extremities:
No cyanosis, clubbing, or edema
No tenderness in the legs
You should also try to breathe a little faster than normal to a rate near 20/min.  The rest of the examination is normal.
Checklist:
Following the encounter, check which of the following items were performed by the examinee.
History of present illness/review of systems
Asked about the location of pain
Asked about the intensity of pain
Asked about the quality of pain
Asked about the origin and duration of pain
Asked about the progression of pain
Asked about any radiation of pain
Asked about the aggravating/relieving factors
Asked about associated symptoms, especially: Nausea and vomiting
Fever
Cough (including sputum and blood)
Shortness of breath
Asked about precipitating factors of sickle cell crisis (eg, diarrhea, dehydration, stress)
Asked about history of chest trauma
Asked about any leg pain/swelling/redness
Asked about blood in the urine
Asked about prior blood transfusion
Past medical/family/social history
Asked about any similar problems in past
Asked about other past medical issues
Asked about previous hospitalizations and surgeries
Asked about menstrual/reproductive history
Asked about current medications (prescription and over the counter)
Asked about medication allergies
Asked about family history of sickle cell anemia, heart problems, and blood clots
Asked about tobacco, alcohol, and drug use
Asked about occupation
Examination
Examinee washed hands before examination
Examined without gown, not through gown
Examined the oral cavity
Examined for enlarged lymph nodes
Performed inspection and palpation of the chest
Performed palpation of area
Auscultated the lungs and heart
Palpated abdomen (superficial and deep)
Examined hands and fingers
Examined legs for tenderness
Counseling
Explained the physical findings and possible diagnosis
Explained the complications of sickle cell disease (infections, hypoxia can precipitate pain)
Explained further workup
Discussed the importance of avoiding hypoxemia and maintaining hydration
Communication skills and professional conduct
Knocked before entering the room
Introduced self and greeted you warmly
Used your name to address you
Paid attention to what you said and maintained good eye contact
Asked few open-ended questions
Asked nonleading questions
Asked one question at a time
Listened to what you said without interrupting
Used plain English rather than technical jargon
Used appropriate transition sentences
Used appropriate draping techniques
Expressed empathy and made appropriate reassurances
Asked whether you had any concerns/questions
Differential diagnosis
Chest syndrome due to sickle cell anemia
Pneumonia
Costochondritis
Pericarditis
Pulmonary thromboembolism
Salmonella osteomyelitis
Diagnostic study/studies
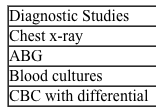
CBC with differential
Urinalysis
Sputum Gram stain and culture
Blood cultures
Chest x-ray
ECG (provided with doorway information)
Case 4 Patient Note
The following represents a typical note for this patient encounter. The details may vary depending on the information given by the simulated patient.
History:  Describe the history you just obtained from this patient.  Include only information (pertinent positives and negatives) relevant to this patient's problem(s).
29-yo female with history of sickle cell anemia and 12 hours of acute-onset chest pain.
Gradual increase in pain to 7-8 on a scale of 10 over the past 12 hours.
Pain is worse with movement and respiration and improved with acetaminophen.
3 days of fever to 38.3 C (101 F), cough productive of green sputum, and mild shortness of breath.
ROS:  No nausea, vomiting, trauma to chest, dysuria, diarrhea, leg swelling, or leg pain
PMHx:  Admitted once 5 years ago for abdominal pain that resolved
PSHx:  None
Meds:  Birth control pills, Tylenol PRN
Allergies: None
FHx:  Mother has sickle cell anemia
SHx:  Denies use of tobacco, alcohol, and illicit drugs.  Had a blood transfusion as a child.
ECG shows sinus tachycardia with no diagnostic abnormalities.
Physical examination:  Describe any positive and negative findings relevant to this patient's problem(s).  Be careful to include only those parts of the examination performed in this encounter.
Vital signs:  Temperature, 38.5 C (101.3 F); blood pressure, 120/75 mm Hg; pulse, 110/min; and respirations, 22/min
HEENT:  Oropharynx without erythema or exudates
Neck:  No cervical lymphadenopathy, trachea midline
Lungs:  CTA bilaterally, no chest tenderness to palpation
Heart:  RRR without M/G/R
Abdomen:  Nontender, nondistended, normoactive bowel sounds throughout; tympanic to percussion; no hepatosplenomegaly
Extremities:  No cyanosis, clubbing, or edema; no swelling or tenderness in the legs
Data interpretation:  Based on what you have learned from the history and physical examination, list up to 3 diagnoses that might explain this patient's complaint(s).  List your diagnoses from most to least likely.  For some cases, fewer than 3 diagnoses will be appropriate.  Then, enter the positive or negative findings from the history and the physical examination (if present) that support each diagnosis.  Lastly, list initial diagnostic studies (if any) you would order for each listed diagnosis (e.g., restricted physical exam maneuvers, laboratory tests, imaging, ECG, etc.).
Diagnosis #1:  Acute chest syndrome
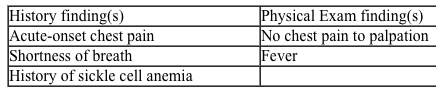
Instructions:  <strong>If the doctor asks you about anything other than these, just say no, or provide an answer that a normal patient might give.</strong> You are a 29-year-old woman who comes to the emergency department with chest pain. <strong>History of present illness</strong>  Pain started 12 hours ago  Pain located in the middle of the chest and does not move  Pain started slowly but is increasing and is now 7-8/10 in severity  Pain worse with any movement or deep breathing  Took acetaminophen, which reduced the pain slightly  Fever as high as 38.3 C (101 F), cough with green sputum, and mild shortness of breath for the last 3 days  No blood in the sputum or recent chest trauma <strong>Review of systems</strong>  No nausea, vomiting, diarrhea, or abdominal pain  No leg pain or swelling  No back pain  No urinary symptoms  Last menstrual period was 2 weeks ago <strong>Past medical/family/social history</strong>  Sickle cell anemia: Diagnosed in childhood; had mild pain episodes at that time. 1 transfusion (age 18).  Admitted once for abdominal pain 5 years ago that resolved with supportive care in the hospital.  No surgeries  No pregnancies  Medications: Birth control pill, acetaminophen as needed  Allergies: No drug allergies  Mother also has sickle cell anemia; brother and father are healthy  Occupation: Teacher  Single, sexually active with 1 boyfriend and use condoms regularly  Tobacco: No  Alcohol: No  Recreational drugs: No <strong>Physical examination</strong> Head and neck:  No redness or exudates in the mouth/pharynx  No enlarged lymph nodes Chest/lungs:  No tenderness to palpation of the chest wall  Clear to auscultation bilaterally Heart:  Regular rhythm with borderline tachycardia  No murmurs Abdomen:  Nontender, nondistended  Normoactive bowel sounds throughout  Tympanic to percussion  No hepatosplenomegaly Extremities:  No cyanosis, clubbing, or edema  No tenderness in the legs You should also try to breathe a little faster than normal to a rate near 20/min.  The rest of the examination is normal.  Checklist:  Following the encounter, check which of the following items were performed by the examinee. <strong>History of present illness/review of systems</strong>  Asked about the location of pain  Asked about the intensity of pain  Asked about the quality of pain  Asked about the origin and duration of pain  Asked about the progression of pain  Asked about any radiation of pain  Asked about the aggravating/relieving factors  Asked about associated symptoms, especially: Nausea and vomiting  Fever  Cough (including sputum and blood)  Shortness of breath  Asked about precipitating factors of sickle cell crisis (eg, diarrhea, dehydration, stress)  Asked about history of chest trauma  Asked about any leg pain/swelling/redness  Asked about blood in the urine  Asked about prior blood transfusion <strong>Past medical/family/social history</strong>  Asked about any similar problems in past  Asked about other past medical issues  Asked about previous hospitalizations and surgeries  Asked about menstrual/reproductive history  Asked about current medications (prescription and over the counter)  Asked about medication allergies  Asked about family history of sickle cell anemia, heart problems, and blood clots  Asked about tobacco, alcohol, and drug use  Asked about occupation <strong>Examination</strong>  Examinee washed hands before examination  Examined without gown, not through gown  Examined the oral cavity  Examined for enlarged lymph nodes  Performed inspection and palpation of the chest  Performed palpation of area  Auscultated the lungs and heart  Palpated abdomen (superficial and deep)  Examined hands and fingers  Examined legs for tenderness <strong>Counseling</strong>  Explained the physical findings and possible diagnosis  Explained the complications of sickle cell disease (infections, hypoxia can precipitate pain)  Explained further workup  Discussed the importance of avoiding hypoxemia and maintaining hydration <strong>Communication skills and professional conduct</strong>  Knocked before entering the room  Introduced self and greeted you warmly  Used your name to address you  Paid attention to what you said and maintained good eye contact  Asked few open-ended questions  Asked nonleading questions  Asked one question at a time  Listened to what you said without interrupting  Used plain English rather than technical jargon  Used appropriate transition sentences  Used appropriate draping techniques  Expressed empathy and made appropriate reassurances  Asked whether you had any concerns/questions <strong>Differential diagnosis</strong>  Chest syndrome due to sickle cell anemia  Pneumonia  Costochondritis  Pericarditis  Pulmonary thromboembolism  Salmonella osteomyelitis <strong>Diagnostic study/studies</strong>  CBC with differential  Urinalysis  Sputum Gram stain and culture  Blood cultures  Chest x-ray  ECG (provided with doorway information) <strong>Case 4 Patient Note</strong> <strong>The following represents a typical note for this patient encounter. The details may vary depending on the information given by the simulated patient.</strong> <strong>History:</strong>  Describe the history you just obtained from this patient.  Include only information (pertinent positives and negatives) relevant to this patient's problem(s).  29-yo female with history of sickle cell anemia and 12 hours of acute-onset chest pain.  Gradual increase in pain to 7-8 on a scale of 10 over the past 12 hours.  Pain is worse with movement and respiration and improved with acetaminophen.  3 days of fever to 38.3 C (101 F), cough productive of green sputum, and mild shortness of breath. ROS:  No nausea, vomiting, trauma to chest, dysuria, diarrhea, leg swelling, or leg pain PMHx:  Admitted once 5 years ago for abdominal pain that resolved PSHx:  None Meds:  Birth control pills, Tylenol PRN Allergies: None FHx:  Mother has sickle cell anemia SHx:  Denies use of tobacco, alcohol, and illicit drugs.  Had a blood transfusion as a child. ECG shows sinus tachycardia with no diagnostic abnormalities. <strong>Physical examination:</strong>  Describe any positive and negative findings relevant to this patient's problem(s).  Be careful to include only those parts of the examination performed in this encounter.  Vital signs:  Temperature, 38.5 C (101.3 F); blood pressure, 120/75 mm Hg; pulse, 110/min; and respirations, 22/min  HEENT:  Oropharynx without erythema or exudates  Neck:  No cervical lymphadenopathy, trachea midline  Lungs:  CTA bilaterally, no chest tenderness to palpation  Heart:  RRR without M/G/R  Abdomen:  Nontender, nondistended, normoactive bowel sounds throughout; tympanic to percussion; no hepatosplenomegaly  Extremities:  No cyanosis, clubbing, or edema; no swelling or tenderness in the legs <strong>Data interpretation:</strong>  Based on what you have learned from the history and physical examination, list up to 3 diagnoses that might explain this patient's complaint(s).  List your diagnoses from most to least likely.  For some cases, fewer than 3 diagnoses will be appropriate.  Then, enter the positive or negative findings from the history and the physical examination (if present) that support each diagnosis.  Lastly, list initial diagnostic studies (if any) you would order for each listed diagnosis (e.g., restricted physical exam maneuvers, laboratory tests, imaging, ECG, etc.). <strong>Diagnosis #1:  Acute chest syndrome</strong>     <strong>Diagnosis #2:  Pneumonia</strong>     <strong>Diagnosis #3:  Pulmonary embolism</strong>
Diagnosis #2:  Pneumonia
Instructions:  <strong>If the doctor asks you about anything other than these, just say no, or provide an answer that a normal patient might give.</strong> You are a 29-year-old woman who comes to the emergency department with chest pain. <strong>History of present illness</strong>  Pain started 12 hours ago  Pain located in the middle of the chest and does not move  Pain started slowly but is increasing and is now 7-8/10 in severity  Pain worse with any movement or deep breathing  Took acetaminophen, which reduced the pain slightly  Fever as high as 38.3 C (101 F), cough with green sputum, and mild shortness of breath for the last 3 days  No blood in the sputum or recent chest trauma <strong>Review of systems</strong>  No nausea, vomiting, diarrhea, or abdominal pain  No leg pain or swelling  No back pain  No urinary symptoms  Last menstrual period was 2 weeks ago <strong>Past medical/family/social history</strong>  Sickle cell anemia: Diagnosed in childhood; had mild pain episodes at that time. 1 transfusion (age 18).  Admitted once for abdominal pain 5 years ago that resolved with supportive care in the hospital.  No surgeries  No pregnancies  Medications: Birth control pill, acetaminophen as needed  Allergies: No drug allergies  Mother also has sickle cell anemia; brother and father are healthy  Occupation: Teacher  Single, sexually active with 1 boyfriend and use condoms regularly  Tobacco: No  Alcohol: No  Recreational drugs: No <strong>Physical examination</strong> Head and neck:  No redness or exudates in the mouth/pharynx  No enlarged lymph nodes Chest/lungs:  No tenderness to palpation of the chest wall  Clear to auscultation bilaterally Heart:  Regular rhythm with borderline tachycardia  No murmurs Abdomen:  Nontender, nondistended  Normoactive bowel sounds throughout  Tympanic to percussion  No hepatosplenomegaly Extremities:  No cyanosis, clubbing, or edema  No tenderness in the legs You should also try to breathe a little faster than normal to a rate near 20/min.  The rest of the examination is normal.  Checklist:  Following the encounter, check which of the following items were performed by the examinee. <strong>History of present illness/review of systems</strong>  Asked about the location of pain  Asked about the intensity of pain  Asked about the quality of pain  Asked about the origin and duration of pain  Asked about the progression of pain  Asked about any radiation of pain  Asked about the aggravating/relieving factors  Asked about associated symptoms, especially: Nausea and vomiting  Fever  Cough (including sputum and blood)  Shortness of breath  Asked about precipitating factors of sickle cell crisis (eg, diarrhea, dehydration, stress)  Asked about history of chest trauma  Asked about any leg pain/swelling/redness  Asked about blood in the urine  Asked about prior blood transfusion <strong>Past medical/family/social history</strong>  Asked about any similar problems in past  Asked about other past medical issues  Asked about previous hospitalizations and surgeries  Asked about menstrual/reproductive history  Asked about current medications (prescription and over the counter)  Asked about medication allergies  Asked about family history of sickle cell anemia, heart problems, and blood clots  Asked about tobacco, alcohol, and drug use  Asked about occupation <strong>Examination</strong>  Examinee washed hands before examination  Examined without gown, not through gown  Examined the oral cavity  Examined for enlarged lymph nodes  Performed inspection and palpation of the chest  Performed palpation of area  Auscultated the lungs and heart  Palpated abdomen (superficial and deep)  Examined hands and fingers  Examined legs for tenderness <strong>Counseling</strong>  Explained the physical findings and possible diagnosis  Explained the complications of sickle cell disease (infections, hypoxia can precipitate pain)  Explained further workup  Discussed the importance of avoiding hypoxemia and maintaining hydration <strong>Communication skills and professional conduct</strong>  Knocked before entering the room  Introduced self and greeted you warmly  Used your name to address you  Paid attention to what you said and maintained good eye contact  Asked few open-ended questions  Asked nonleading questions  Asked one question at a time  Listened to what you said without interrupting  Used plain English rather than technical jargon  Used appropriate transition sentences  Used appropriate draping techniques  Expressed empathy and made appropriate reassurances  Asked whether you had any concerns/questions <strong>Differential diagnosis</strong>  Chest syndrome due to sickle cell anemia  Pneumonia  Costochondritis  Pericarditis  Pulmonary thromboembolism  Salmonella osteomyelitis <strong>Diagnostic study/studies</strong>  CBC with differential  Urinalysis  Sputum Gram stain and culture  Blood cultures  Chest x-ray  ECG (provided with doorway information) <strong>Case 4 Patient Note</strong> <strong>The following represents a typical note for this patient encounter. The details may vary depending on the information given by the simulated patient.</strong> <strong>History:</strong>  Describe the history you just obtained from this patient.  Include only information (pertinent positives and negatives) relevant to this patient's problem(s).  29-yo female with history of sickle cell anemia and 12 hours of acute-onset chest pain.  Gradual increase in pain to 7-8 on a scale of 10 over the past 12 hours.  Pain is worse with movement and respiration and improved with acetaminophen.  3 days of fever to 38.3 C (101 F), cough productive of green sputum, and mild shortness of breath. ROS:  No nausea, vomiting, trauma to chest, dysuria, diarrhea, leg swelling, or leg pain PMHx:  Admitted once 5 years ago for abdominal pain that resolved PSHx:  None Meds:  Birth control pills, Tylenol PRN Allergies: None FHx:  Mother has sickle cell anemia SHx:  Denies use of tobacco, alcohol, and illicit drugs.  Had a blood transfusion as a child. ECG shows sinus tachycardia with no diagnostic abnormalities. <strong>Physical examination:</strong>  Describe any positive and negative findings relevant to this patient's problem(s).  Be careful to include only those parts of the examination performed in this encounter.  Vital signs:  Temperature, 38.5 C (101.3 F); blood pressure, 120/75 mm Hg; pulse, 110/min; and respirations, 22/min  HEENT:  Oropharynx without erythema or exudates  Neck:  No cervical lymphadenopathy, trachea midline  Lungs:  CTA bilaterally, no chest tenderness to palpation  Heart:  RRR without M/G/R  Abdomen:  Nontender, nondistended, normoactive bowel sounds throughout; tympanic to percussion; no hepatosplenomegaly  Extremities:  No cyanosis, clubbing, or edema; no swelling or tenderness in the legs <strong>Data interpretation:</strong>  Based on what you have learned from the history and physical examination, list up to 3 diagnoses that might explain this patient's complaint(s).  List your diagnoses from most to least likely.  For some cases, fewer than 3 diagnoses will be appropriate.  Then, enter the positive or negative findings from the history and the physical examination (if present) that support each diagnosis.  Lastly, list initial diagnostic studies (if any) you would order for each listed diagnosis (e.g., restricted physical exam maneuvers, laboratory tests, imaging, ECG, etc.). <strong>Diagnosis #1:  Acute chest syndrome</strong>     <strong>Diagnosis #2:  Pneumonia</strong>     <strong>Diagnosis #3:  Pulmonary embolism</strong>
Diagnosis #3:  Pulmonary embolism
Instructions:  <strong>If the doctor asks you about anything other than these, just say no, or provide an answer that a normal patient might give.</strong> You are a 29-year-old woman who comes to the emergency department with chest pain. <strong>History of present illness</strong>  Pain started 12 hours ago  Pain located in the middle of the chest and does not move  Pain started slowly but is increasing and is now 7-8/10 in severity  Pain worse with any movement or deep breathing  Took acetaminophen, which reduced the pain slightly  Fever as high as 38.3 C (101 F), cough with green sputum, and mild shortness of breath for the last 3 days  No blood in the sputum or recent chest trauma <strong>Review of systems</strong>  No nausea, vomiting, diarrhea, or abdominal pain  No leg pain or swelling  No back pain  No urinary symptoms  Last menstrual period was 2 weeks ago <strong>Past medical/family/social history</strong>  Sickle cell anemia: Diagnosed in childhood; had mild pain episodes at that time. 1 transfusion (age 18).  Admitted once for abdominal pain 5 years ago that resolved with supportive care in the hospital.  No surgeries  No pregnancies  Medications: Birth control pill, acetaminophen as needed  Allergies: No drug allergies  Mother also has sickle cell anemia; brother and father are healthy  Occupation: Teacher  Single, sexually active with 1 boyfriend and use condoms regularly  Tobacco: No  Alcohol: No  Recreational drugs: No <strong>Physical examination</strong> Head and neck:  No redness or exudates in the mouth/pharynx  No enlarged lymph nodes Chest/lungs:  No tenderness to palpation of the chest wall  Clear to auscultation bilaterally Heart:  Regular rhythm with borderline tachycardia  No murmurs Abdomen:  Nontender, nondistended  Normoactive bowel sounds throughout  Tympanic to percussion  No hepatosplenomegaly Extremities:  No cyanosis, clubbing, or edema  No tenderness in the legs You should also try to breathe a little faster than normal to a rate near 20/min.  The rest of the examination is normal.  Checklist:  Following the encounter, check which of the following items were performed by the examinee. <strong>History of present illness/review of systems</strong>  Asked about the location of pain  Asked about the intensity of pain  Asked about the quality of pain  Asked about the origin and duration of pain  Asked about the progression of pain  Asked about any radiation of pain  Asked about the aggravating/relieving factors  Asked about associated symptoms, especially: Nausea and vomiting  Fever  Cough (including sputum and blood)  Shortness of breath  Asked about precipitating factors of sickle cell crisis (eg, diarrhea, dehydration, stress)  Asked about history of chest trauma  Asked about any leg pain/swelling/redness  Asked about blood in the urine  Asked about prior blood transfusion <strong>Past medical/family/social history</strong>  Asked about any similar problems in past  Asked about other past medical issues  Asked about previous hospitalizations and surgeries  Asked about menstrual/reproductive history  Asked about current medications (prescription and over the counter)  Asked about medication allergies  Asked about family history of sickle cell anemia, heart problems, and blood clots  Asked about tobacco, alcohol, and drug use  Asked about occupation <strong>Examination</strong>  Examinee washed hands before examination  Examined without gown, not through gown  Examined the oral cavity  Examined for enlarged lymph nodes  Performed inspection and palpation of the chest  Performed palpation of area  Auscultated the lungs and heart  Palpated abdomen (superficial and deep)  Examined hands and fingers  Examined legs for tenderness <strong>Counseling</strong>  Explained the physical findings and possible diagnosis  Explained the complications of sickle cell disease (infections, hypoxia can precipitate pain)  Explained further workup  Discussed the importance of avoiding hypoxemia and maintaining hydration <strong>Communication skills and professional conduct</strong>  Knocked before entering the room  Introduced self and greeted you warmly  Used your name to address you  Paid attention to what you said and maintained good eye contact  Asked few open-ended questions  Asked nonleading questions  Asked one question at a time  Listened to what you said without interrupting  Used plain English rather than technical jargon  Used appropriate transition sentences  Used appropriate draping techniques  Expressed empathy and made appropriate reassurances  Asked whether you had any concerns/questions <strong>Differential diagnosis</strong>  Chest syndrome due to sickle cell anemia  Pneumonia  Costochondritis  Pericarditis  Pulmonary thromboembolism  Salmonella osteomyelitis <strong>Diagnostic study/studies</strong>  CBC with differential  Urinalysis  Sputum Gram stain and culture  Blood cultures  Chest x-ray  ECG (provided with doorway information) <strong>Case 4 Patient Note</strong> <strong>The following represents a typical note for this patient encounter. The details may vary depending on the information given by the simulated patient.</strong> <strong>History:</strong>  Describe the history you just obtained from this patient.  Include only information (pertinent positives and negatives) relevant to this patient's problem(s).  29-yo female with history of sickle cell anemia and 12 hours of acute-onset chest pain.  Gradual increase in pain to 7-8 on a scale of 10 over the past 12 hours.  Pain is worse with movement and respiration and improved with acetaminophen.  3 days of fever to 38.3 C (101 F), cough productive of green sputum, and mild shortness of breath. ROS:  No nausea, vomiting, trauma to chest, dysuria, diarrhea, leg swelling, or leg pain PMHx:  Admitted once 5 years ago for abdominal pain that resolved PSHx:  None Meds:  Birth control pills, Tylenol PRN Allergies: None FHx:  Mother has sickle cell anemia SHx:  Denies use of tobacco, alcohol, and illicit drugs.  Had a blood transfusion as a child. ECG shows sinus tachycardia with no diagnostic abnormalities. <strong>Physical examination:</strong>  Describe any positive and negative findings relevant to this patient's problem(s).  Be careful to include only those parts of the examination performed in this encounter.  Vital signs:  Temperature, 38.5 C (101.3 F); blood pressure, 120/75 mm Hg; pulse, 110/min; and respirations, 22/min  HEENT:  Oropharynx without erythema or exudates  Neck:  No cervical lymphadenopathy, trachea midline  Lungs:  CTA bilaterally, no chest tenderness to palpation  Heart:  RRR without M/G/R  Abdomen:  Nontender, nondistended, normoactive bowel sounds throughout; tympanic to percussion; no hepatosplenomegaly  Extremities:  No cyanosis, clubbing, or edema; no swelling or tenderness in the legs <strong>Data interpretation:</strong>  Based on what you have learned from the history and physical examination, list up to 3 diagnoses that might explain this patient's complaint(s).  List your diagnoses from most to least likely.  For some cases, fewer than 3 diagnoses will be appropriate.  Then, enter the positive or negative findings from the history and the physical examination (if present) that support each diagnosis.  Lastly, list initial diagnostic studies (if any) you would order for each listed diagnosis (e.g., restricted physical exam maneuvers, laboratory tests, imaging, ECG, etc.). <strong>Diagnosis #1:  Acute chest syndrome</strong>     <strong>Diagnosis #2:  Pneumonia</strong>     <strong>Diagnosis #3:  Pulmonary embolism</strong>

Doorway information about patient The patient is a 50-year-old man who comes to the office due to difficulty swallowing. Vital signs Temperature: 36.7 C (98.1 F) Blood pressure: 130/90 mm Hg Pulse: 85/min Respirations: 16/min Basic differential diagnosis Oropharyngeal dysphagia Neuromuscular (stroke, parkinsonism, multiple sclerosis) Mechanical obstruction (Zenker diverticulum, thyromegaly) Skeletal muscle disorders (myasthenia gravis, muscular dystrophies, polymyositis) Miscellaneous (medications, radiation) Esophageal dysphagia Mechanical obstruction (esophageal carcinoma, benign strictures, webs and rings [Schatzki]) Abnormal motility (achalasia, scleroderma) Gastroesophageal reflux disease Miscellaneous (diabetes, alcoholism)

Free
(Essay)
5.0/5
(91)
Correct Answer:
Verified

Instructions:
If the doctor asks you about anything other than these, just say "no," or provide an answer that a normal patient might give.
You are a 50-year-old man who comes to the clinic due to difficulty swallowing.
History of present illness
Onset 3 months ago
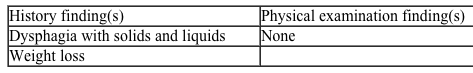
Initially had difficulty swallowing solids (food would get stuck in the middle of the chest before slowly going down)
Symptoms progressed slowly and now you have had difficulty swallowing liquids for the past 3 weeks
Food regurgitates into the chest 2-3 hours after eating
No problem chewing or transferring food out of the mouth into the throat
10-lb (4.5 kg) weight loss in the past 3 months; decreased appetite for the past 3 weeks
Review of systems
No weakness in the arms or legs
No shortness of breath or chest pain
No nausea, vomiting, diarrhea, or constipation
Past medical/family/social history
Gastroesophageal reflux (symptoms 2-3 times a week for the past 25 years; relieved with antacids)
No surgeries
No other medications
No drug allergies
Father, mother, and 2 siblings are healthy
Married, live with wife
Occupation: Stockbroker
Tobacco: 1 pack a day for last 30 years
Alcohol: Occasional wine
Recreational drugs: No
Physical examination
HEENT:
Oropharynx clear, difficulty swallowing water
Neck:
Supple with no visible deformity
Lymph nodes:
No cervical, axillary, or supraclavicular adenopathy
Lungs:
Clear to auscultation bilaterally
Heart:
Regular rate and rhythm
No murmurs, gallops, or rubs
Abdomen:
Nontender, nondistended
Normoactive bowel sounds
No hepatosplenomegaly
No CVA tenderness
Checklist:
Following the encounter, check which of the following items were performed by the examinee.
History of present illness/review of systems
Asked an open-ended question about describing the dysphagia
Asked about the onset and progression over time
Asked about exact location where food gets stuck
Asked whether the dysphagia is for solids, liquids, or both
Asked which started first (solids or liquids)
Asked whether there is any associated pain
Asked about any aggravating or relieving factors
Asked about episodes of choking or regurgitation/aspiration
Asked about any nausea and vomiting
Asked about heartburn/gastroesophageal reflux
Asked about history of ingestion of corrosive materials
Asked about appetite and changes in weight
Past medical/family/social history
Asked about similar episodes in the past
Asked about past medical issues
Asked about medications
Asked about medication allergies
Asked about family health
Asked about occupation
Asked about tobacco, alcohol, and recreational drug use
Examination
Washed hands before examination
Examined without gown, not through gown
Palpated neck for swelling
Examined mouth and throat
Gave you water and asked you to swallow
Palpated lymph nodes in neck, axilla, and above the clavicles
Auscultated abdomen
Palpated abdomen (superficial and deep)
Examined heart and lungs
Counseling
Explained physical findings and possible diagnosis
Explained further workup
Discussed smoking cessation
Communication skills and professional conduct
Knocked before entering the room
Introduced self and greeted you warmly
Used your name to address you
Paid attention to what you said and maintained good eye contact
Asked open-ended questions
Asked nonleading questions
Asked one question at a time
Listened to what you said without interrupting
Used plain English rather than technical jargon
Used appropriate transition sentences
Used appropriate draping techniques
Summarized the history and explained physical findings
Expressed empathy and gave appropriate reassurances
Differential diagnosis
Carcinoma of the esophagus
Achalasia
Reflux esophagitis
Stricture
Diagnostic study/studies
CBC
Esophagram
Esophagogastroduodenoscopy
Chest x-ray
Case 32 Patient Notes
The following represents a typical note for this patient encounter.  The details may vary depending on the information given by the simulated patient.
History:  Describe the history you just obtained from this patient.  Include only information (pertinent positives and negatives) relevant to this patient's problem(s).
50-yo man with 3 months of dysphagia, initially with solids and now with liquids for the past 3 weeks.
No problem with chewing and transferring food to throat, but feels food getting stuck in the middle of the chest.
Decreased appetite and 4.5-kg (10-lb) weight loss.
Food regurgitation 2-3 hours after eating.
ROS:  No weakness in the arms or legs, shortness of breath, nausea, vomiting, chest pain, diarrhea, constipation, or urinary problems
PMHx:  GERD for 25 years relieved with OTC antacids
PSHx:  None
Meds:  OTC antacids
Allergies:  None
FHx:  Father, mother, and 2 siblings are healthy
SHx:  1 PPD smoker for 30 years, occasional alcohol use
Physical examination:  Describe any positive and negative findings relevant to this patient's problem(s).  Be careful to include only those parts of examination performed in this encounter.
Vital signs:  Temperature, 36.7 C (98.1 F); blood pressure,130/90 mm Hg; pulse, 85/min; and respirations, 16/min
HEENT:  Oropharynx clear, difficulty swallowing water
Neck:  Supple with no lymphadenopathy
Lymph nodes:  No axillary or supraclavicular adenopathy
Lungs:  Clear to auscultation bilaterally
Heart:  RRR with no murmurs, gallops, or rubs
Abdomen:  Nontender, nondistended, normoactive bowel sounds, no hepatosplenomegaly, no CVA tenderness
Data interpretation:  Based on what you have learned from the history and physical examination, list up to 3 diagnoses that might explain this patient's complaint(s).  List your diagnoses from most to least likely.  For some cases, fewer than 3 diagnoses will be appropriate.  Then enter the positive or negative findings from the history and the physical examination (if present) that support each diagnosis.  Lastly, list initial diagnostic studies (if any) you would order for each listed diagnosis (eg, restricted physical examination maneuvers, laboratory tests, imaging, ECG)
Diagnosis #1:  Esophageal cancer
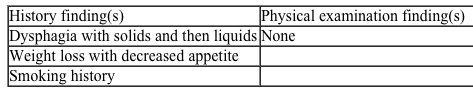
Instructions:  <strong>If the doctor asks you about anything other than these, just say no, or provide an answer that a normal patient might give.</strong> You are a 50-year-old man who comes to the clinic due to difficulty swallowing. <strong>History of present illness</strong>  Onset 3 months ago  Initially had difficulty swallowing solids (food would get stuck in the middle of the chest before slowly going down)  Symptoms progressed slowly and now you have had difficulty swallowing liquids for the past 3 weeks  Food regurgitates into the chest 2-3 hours after eating  No problem chewing or transferring food out of the mouth into the throat  10-lb (4.5 kg) weight loss in the past 3 months; decreased appetite for the past 3 weeks <strong>Review of systems</strong>  No weakness in the arms or legs  No shortness of breath or chest pain  No nausea, vomiting, diarrhea, or constipation <strong>Past medical/family/social history</strong>  Gastroesophageal reflux (symptoms 2-3 times a week for the past 25 years; relieved with antacids)  No surgeries  No other medications  No drug allergies  Father, mother, and 2 siblings are healthy  Married, live with wife  Occupation: Stockbroker  Tobacco: 1 pack a day for last 30 years  Alcohol: Occasional wine  Recreational drugs: No <strong>Physical examination</strong> HEENT:  Oropharynx clear, difficulty swallowing water Neck:  Supple with no visible deformity Lymph nodes:  No cervical, axillary, or supraclavicular adenopathy Lungs:  Clear to auscultation bilaterally Heart:  Regular rate and rhythm  No murmurs, gallops, or rubs Abdomen:  Nontender, nondistended  Normoactive bowel sounds  No hepatosplenomegaly  No CVA tenderness  Checklist:  Following the encounter, check which of the following items were performed by the examinee. <strong>History of present illness/review of systems</strong>  Asked an open-ended question about describing the dysphagia  Asked about the onset and progression over time  Asked about exact location where food gets stuck  Asked whether the dysphagia is for solids, liquids, or both  Asked which started first (solids or liquids)  Asked whether there is any associated pain  Asked about any aggravating or relieving factors  Asked about episodes of choking or regurgitation/aspiration  Asked about any nausea and vomiting  Asked about heartburn/gastroesophageal reflux  Asked about history of ingestion of corrosive materials  Asked about appetite and changes in weight <strong>Past medical/family/social history</strong>  Asked about similar episodes in the past  Asked about past medical issues  Asked about medications  Asked about medication allergies  Asked about family health  Asked about occupation  Asked about tobacco, alcohol, and recreational drug use <strong>Examination</strong>  Washed hands before examination  Examined without gown, not through gown  Palpated neck for swelling  Examined mouth and throat  Gave you water and asked you to swallow  Palpated lymph nodes in neck, axilla, and above the clavicles  Auscultated abdomen  Palpated abdomen (superficial and deep)  Examined heart and lungs <strong>Counseling</strong>  Explained physical findings and possible diagnosis  Explained further workup  Discussed smoking cessation <strong>Communication skills and professional conduct</strong>  Knocked before entering the room  Introduced self and greeted you warmly  Used your name to address you  Paid attention to what you said and maintained good eye contact  Asked open-ended questions  Asked nonleading questions  Asked one question at a time  Listened to what you said without interrupting  Used plain English rather than technical jargon  Used appropriate transition sentences  Used appropriate draping techniques  Summarized the history and explained physical findings  Expressed empathy and gave appropriate reassurances <strong>Differential diagnosis</strong>  Carcinoma of the esophagus  Achalasia  Reflux esophagitis  Stricture <strong>Diagnostic study/studies</strong>  CBC  Esophagram  Esophagogastroduodenoscopy  Chest x-ray <strong>Case 32 Patient Notes</strong> <strong>The following represents a typical note for this patient encounter.  The details may vary depending on the information given by the simulated patient.</strong> <strong>History:</strong>  Describe the history you just obtained from this patient.  Include only information (pertinent positives and negatives) relevant to this patient's problem(s).  50-yo man with 3 months of dysphagia, initially with solids and now with liquids for the past 3 weeks.  No problem with chewing and transferring food to throat, but feels food getting stuck in the middle of the chest.  Decreased appetite and 4.5-kg (10-lb) weight loss.  Food regurgitation 2-3 hours after eating. ROS:  No weakness in the arms or legs, shortness of breath, nausea, vomiting, chest pain, diarrhea, constipation, or urinary problems PMHx:  GERD for 25 years relieved with OTC antacids PSHx:  None Meds:  OTC antacids Allergies:  None FHx:  Father, mother, and 2 siblings are healthy SHx:  1 PPD smoker for 30 years, occasional alcohol use <strong>Physical examination:</strong>  Describe any positive and negative findings relevant to this patient's problem(s).  Be careful to include only those parts of examination performed in this encounter.  Vital signs:  Temperature, 36.7 C (98.1 F); blood pressure,130/90 mm Hg; pulse, 85/min; and respirations, 16/min  HEENT:  Oropharynx clear, difficulty swallowing water  Neck:  Supple with no lymphadenopathy  Lymph nodes:  No axillary or supraclavicular adenopathy  Lungs:  Clear to auscultation bilaterally  Heart:  RRR with no murmurs, gallops, or rubs  Abdomen:  Nontender, nondistended, normoactive bowel sounds, no hepatosplenomegaly, no CVA tenderness <strong>Data interpretation:</strong>  Based on what you have learned from the history and physical examination, list up to 3 diagnoses that might explain this patient's complaint(s).  List your diagnoses from most to least likely.  For some cases, fewer than 3 diagnoses will be appropriate.  Then enter the positive or negative findings from the history and the physical examination (if present) that support each diagnosis.  Lastly, list initial diagnostic studies (if any) you would order for each listed diagnosis (eg, restricted physical examination maneuvers, laboratory tests, imaging, ECG) <strong>Diagnosis #1:  Esophageal cancer</strong>     <strong>Diagnosis #2:  Achalasia</strong>     <strong>Diagnosis #3:  Reflux esophagitis/stricture</strong>
Diagnosis #2:  Achalasia
Instructions:  <strong>If the doctor asks you about anything other than these, just say no, or provide an answer that a normal patient might give.</strong> You are a 50-year-old man who comes to the clinic due to difficulty swallowing. <strong>History of present illness</strong>  Onset 3 months ago  Initially had difficulty swallowing solids (food would get stuck in the middle of the chest before slowly going down)  Symptoms progressed slowly and now you have had difficulty swallowing liquids for the past 3 weeks  Food regurgitates into the chest 2-3 hours after eating  No problem chewing or transferring food out of the mouth into the throat  10-lb (4.5 kg) weight loss in the past 3 months; decreased appetite for the past 3 weeks <strong>Review of systems</strong>  No weakness in the arms or legs  No shortness of breath or chest pain  No nausea, vomiting, diarrhea, or constipation <strong>Past medical/family/social history</strong>  Gastroesophageal reflux (symptoms 2-3 times a week for the past 25 years; relieved with antacids)  No surgeries  No other medications  No drug allergies  Father, mother, and 2 siblings are healthy  Married, live with wife  Occupation: Stockbroker  Tobacco: 1 pack a day for last 30 years  Alcohol: Occasional wine  Recreational drugs: No <strong>Physical examination</strong> HEENT:  Oropharynx clear, difficulty swallowing water Neck:  Supple with no visible deformity Lymph nodes:  No cervical, axillary, or supraclavicular adenopathy Lungs:  Clear to auscultation bilaterally Heart:  Regular rate and rhythm  No murmurs, gallops, or rubs Abdomen:  Nontender, nondistended  Normoactive bowel sounds  No hepatosplenomegaly  No CVA tenderness  Checklist:  Following the encounter, check which of the following items were performed by the examinee. <strong>History of present illness/review of systems</strong>  Asked an open-ended question about describing the dysphagia  Asked about the onset and progression over time  Asked about exact location where food gets stuck  Asked whether the dysphagia is for solids, liquids, or both  Asked which started first (solids or liquids)  Asked whether there is any associated pain  Asked about any aggravating or relieving factors  Asked about episodes of choking or regurgitation/aspiration  Asked about any nausea and vomiting  Asked about heartburn/gastroesophageal reflux  Asked about history of ingestion of corrosive materials  Asked about appetite and changes in weight <strong>Past medical/family/social history</strong>  Asked about similar episodes in the past  Asked about past medical issues  Asked about medications  Asked about medication allergies  Asked about family health  Asked about occupation  Asked about tobacco, alcohol, and recreational drug use <strong>Examination</strong>  Washed hands before examination  Examined without gown, not through gown  Palpated neck for swelling  Examined mouth and throat  Gave you water and asked you to swallow  Palpated lymph nodes in neck, axilla, and above the clavicles  Auscultated abdomen  Palpated abdomen (superficial and deep)  Examined heart and lungs <strong>Counseling</strong>  Explained physical findings and possible diagnosis  Explained further workup  Discussed smoking cessation <strong>Communication skills and professional conduct</strong>  Knocked before entering the room  Introduced self and greeted you warmly  Used your name to address you  Paid attention to what you said and maintained good eye contact  Asked open-ended questions  Asked nonleading questions  Asked one question at a time  Listened to what you said without interrupting  Used plain English rather than technical jargon  Used appropriate transition sentences  Used appropriate draping techniques  Summarized the history and explained physical findings  Expressed empathy and gave appropriate reassurances <strong>Differential diagnosis</strong>  Carcinoma of the esophagus  Achalasia  Reflux esophagitis  Stricture <strong>Diagnostic study/studies</strong>  CBC  Esophagram  Esophagogastroduodenoscopy  Chest x-ray <strong>Case 32 Patient Notes</strong> <strong>The following represents a typical note for this patient encounter.  The details may vary depending on the information given by the simulated patient.</strong> <strong>History:</strong>  Describe the history you just obtained from this patient.  Include only information (pertinent positives and negatives) relevant to this patient's problem(s).  50-yo man with 3 months of dysphagia, initially with solids and now with liquids for the past 3 weeks.  No problem with chewing and transferring food to throat, but feels food getting stuck in the middle of the chest.  Decreased appetite and 4.5-kg (10-lb) weight loss.  Food regurgitation 2-3 hours after eating. ROS:  No weakness in the arms or legs, shortness of breath, nausea, vomiting, chest pain, diarrhea, constipation, or urinary problems PMHx:  GERD for 25 years relieved with OTC antacids PSHx:  None Meds:  OTC antacids Allergies:  None FHx:  Father, mother, and 2 siblings are healthy SHx:  1 PPD smoker for 30 years, occasional alcohol use <strong>Physical examination:</strong>  Describe any positive and negative findings relevant to this patient's problem(s).  Be careful to include only those parts of examination performed in this encounter.  Vital signs:  Temperature, 36.7 C (98.1 F); blood pressure,130/90 mm Hg; pulse, 85/min; and respirations, 16/min  HEENT:  Oropharynx clear, difficulty swallowing water  Neck:  Supple with no lymphadenopathy  Lymph nodes:  No axillary or supraclavicular adenopathy  Lungs:  Clear to auscultation bilaterally  Heart:  RRR with no murmurs, gallops, or rubs  Abdomen:  Nontender, nondistended, normoactive bowel sounds, no hepatosplenomegaly, no CVA tenderness <strong>Data interpretation:</strong>  Based on what you have learned from the history and physical examination, list up to 3 diagnoses that might explain this patient's complaint(s).  List your diagnoses from most to least likely.  For some cases, fewer than 3 diagnoses will be appropriate.  Then enter the positive or negative findings from the history and the physical examination (if present) that support each diagnosis.  Lastly, list initial diagnostic studies (if any) you would order for each listed diagnosis (eg, restricted physical examination maneuvers, laboratory tests, imaging, ECG) <strong>Diagnosis #1:  Esophageal cancer</strong>     <strong>Diagnosis #2:  Achalasia</strong>     <strong>Diagnosis #3:  Reflux esophagitis/stricture</strong>
Diagnosis #3:  Reflux esophagitis/stricture
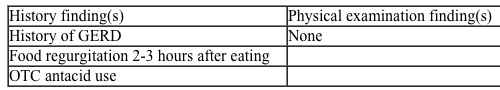
Instructions:  <strong>If the doctor asks you about anything other than these, just say no, or provide an answer that a normal patient might give.</strong> You are a 50-year-old man who comes to the clinic due to difficulty swallowing. <strong>History of present illness</strong>  Onset 3 months ago  Initially had difficulty swallowing solids (food would get stuck in the middle of the chest before slowly going down)  Symptoms progressed slowly and now you have had difficulty swallowing liquids for the past 3 weeks  Food regurgitates into the chest 2-3 hours after eating  No problem chewing or transferring food out of the mouth into the throat  10-lb (4.5 kg) weight loss in the past 3 months; decreased appetite for the past 3 weeks <strong>Review of systems</strong>  No weakness in the arms or legs  No shortness of breath or chest pain  No nausea, vomiting, diarrhea, or constipation <strong>Past medical/family/social history</strong>  Gastroesophageal reflux (symptoms 2-3 times a week for the past 25 years; relieved with antacids)  No surgeries  No other medications  No drug allergies  Father, mother, and 2 siblings are healthy  Married, live with wife  Occupation: Stockbroker  Tobacco: 1 pack a day for last 30 years  Alcohol: Occasional wine  Recreational drugs: No <strong>Physical examination</strong> HEENT:  Oropharynx clear, difficulty swallowing water Neck:  Supple with no visible deformity Lymph nodes:  No cervical, axillary, or supraclavicular adenopathy Lungs:  Clear to auscultation bilaterally Heart:  Regular rate and rhythm  No murmurs, gallops, or rubs Abdomen:  Nontender, nondistended  Normoactive bowel sounds  No hepatosplenomegaly  No CVA tenderness  Checklist:  Following the encounter, check which of the following items were performed by the examinee. <strong>History of present illness/review of systems</strong>  Asked an open-ended question about describing the dysphagia  Asked about the onset and progression over time  Asked about exact location where food gets stuck  Asked whether the dysphagia is for solids, liquids, or both  Asked which started first (solids or liquids)  Asked whether there is any associated pain  Asked about any aggravating or relieving factors  Asked about episodes of choking or regurgitation/aspiration  Asked about any nausea and vomiting  Asked about heartburn/gastroesophageal reflux  Asked about history of ingestion of corrosive materials  Asked about appetite and changes in weight <strong>Past medical/family/social history</strong>  Asked about similar episodes in the past  Asked about past medical issues  Asked about medications  Asked about medication allergies  Asked about family health  Asked about occupation  Asked about tobacco, alcohol, and recreational drug use <strong>Examination</strong>  Washed hands before examination  Examined without gown, not through gown  Palpated neck for swelling  Examined mouth and throat  Gave you water and asked you to swallow  Palpated lymph nodes in neck, axilla, and above the clavicles  Auscultated abdomen  Palpated abdomen (superficial and deep)  Examined heart and lungs <strong>Counseling</strong>  Explained physical findings and possible diagnosis  Explained further workup  Discussed smoking cessation <strong>Communication skills and professional conduct</strong>  Knocked before entering the room  Introduced self and greeted you warmly  Used your name to address you  Paid attention to what you said and maintained good eye contact  Asked open-ended questions  Asked nonleading questions  Asked one question at a time  Listened to what you said without interrupting  Used plain English rather than technical jargon  Used appropriate transition sentences  Used appropriate draping techniques  Summarized the history and explained physical findings  Expressed empathy and gave appropriate reassurances <strong>Differential diagnosis</strong>  Carcinoma of the esophagus  Achalasia  Reflux esophagitis  Stricture <strong>Diagnostic study/studies</strong>  CBC  Esophagram  Esophagogastroduodenoscopy  Chest x-ray <strong>Case 32 Patient Notes</strong> <strong>The following represents a typical note for this patient encounter.  The details may vary depending on the information given by the simulated patient.</strong> <strong>History:</strong>  Describe the history you just obtained from this patient.  Include only information (pertinent positives and negatives) relevant to this patient's problem(s).  50-yo man with 3 months of dysphagia, initially with solids and now with liquids for the past 3 weeks.  No problem with chewing and transferring food to throat, but feels food getting stuck in the middle of the chest.  Decreased appetite and 4.5-kg (10-lb) weight loss.  Food regurgitation 2-3 hours after eating. ROS:  No weakness in the arms or legs, shortness of breath, nausea, vomiting, chest pain, diarrhea, constipation, or urinary problems PMHx:  GERD for 25 years relieved with OTC antacids PSHx:  None Meds:  OTC antacids Allergies:  None FHx:  Father, mother, and 2 siblings are healthy SHx:  1 PPD smoker for 30 years, occasional alcohol use <strong>Physical examination:</strong>  Describe any positive and negative findings relevant to this patient's problem(s).  Be careful to include only those parts of examination performed in this encounter.  Vital signs:  Temperature, 36.7 C (98.1 F); blood pressure,130/90 mm Hg; pulse, 85/min; and respirations, 16/min  HEENT:  Oropharynx clear, difficulty swallowing water  Neck:  Supple with no lymphadenopathy  Lymph nodes:  No axillary or supraclavicular adenopathy  Lungs:  Clear to auscultation bilaterally  Heart:  RRR with no murmurs, gallops, or rubs  Abdomen:  Nontender, nondistended, normoactive bowel sounds, no hepatosplenomegaly, no CVA tenderness <strong>Data interpretation:</strong>  Based on what you have learned from the history and physical examination, list up to 3 diagnoses that might explain this patient's complaint(s).  List your diagnoses from most to least likely.  For some cases, fewer than 3 diagnoses will be appropriate.  Then enter the positive or negative findings from the history and the physical examination (if present) that support each diagnosis.  Lastly, list initial diagnostic studies (if any) you would order for each listed diagnosis (eg, restricted physical examination maneuvers, laboratory tests, imaging, ECG) <strong>Diagnosis #1:  Esophageal cancer</strong>     <strong>Diagnosis #2:  Achalasia</strong>     <strong>Diagnosis #3:  Reflux esophagitis/stricture</strong>

Doorway information about patient The patient is a 35-year-old man who comes to the office due to acute diarrhea. Vital signs Temperature: 36.7 C (98.1 F) Blood pressure: 110/65 mm Hg Pulse: 100/min Respirations: 18/min Basic differential diagnosis Viral gastroenteritis Bacterial gastroenteritis & food-borne pathogens Medication induced Giardiasis Clostridium difficle colitis Inflammatory bowel disease Irritable bowel disease Malabsorption HIV

(Essay)
4.7/5
(71)

Doorway information about patient The patient is a 56-year-old woman who comes to the emergency department due to vomiting blood. Vital signs Temperature: 36.7 C (98 F) Blood pressure: 90/60 mm Hg Pulse: 98/min Respirations: 20/min Clinical images The patient has vomited into a pan of water at the bedside, as shown in the image.<strong>Doorway information about patient</strong> The patient is a 56-year-old woman who comes to the emergency department due to vomiting blood. <strong>Vital signs</strong> Temperature: 36.7 C (98 F) Blood pressure: 90/60 mm Hg Pulse: 98/min Respirations: 20/min <strong>Clinical images</strong> The patient has vomited into a pan of water at the bedside, as shown in the image.  <strong>Basic differential diagnosis</strong>  Peptic ulcer disease  Gastric erosions  Esophageal varices  Mallory-Weiss tear  Esophagitis  Duodenitis  Malignancy (esophageal and gastric) Basic differential diagnosis Peptic ulcer disease Gastric erosions Esophageal varices Mallory-Weiss tear Esophagitis Duodenitis Malignancy (esophageal and gastric)

(Essay)
4.8/5
(82)

Doorway information about patient The patient is a 35-year-old woman who comes to the office due to acute right lumbar and lower abdominal pain. Vital signs Temperature: 38.3 C (100.9 F) Blood pressure: 110/70 mm Hg Pulse: 100/min Respirations: 16/min Basic differential diagnosis Renal colic Ovarian torsion Urinary tract infection/pyelonephritis Pelvic inflammatory disease Mittelschmerz Appendicitis Threatened abortion Ectopic pregnancy Dysmenorrhea Endometriosis Fibroids

(Essay)
4.9/5
(86)

Doorway information about patient The patient is a 35-year-old man who comes to the office due to fatigue. Vital signs Temperature: 37 C (98.6 F) Blood pressure: 120/80 mm Hg Pulse: 82/min Respirations: 16/min Basic differential diagnosis Depression Anemia Thyroid disorders HIV/AIDS Chronic fatigue syndrome

(Essay)
4.7/5
(72)

Doorway information about patient The patient is a 35-year-old man who comes to the office due to a cough. Vital signs Temperature: 38.5 C (101.3 F) Blood pressure: 120/75 mm Hg Pulse: 98/min Respirations: 20/min Basic differential diagnosis Common cold Acute sinusitis Allergic rhinitis Acute bronchitis Pneumonia Pertussis Pulmonary embolism Drugs (ACE inhibitors) Asthma Congestive heart failure Chronic obstructive pulmonary disease (COPD) exacerbation

(Essay)
4.8/5
(83)

Doorway information about patient The patient is a 35-year-old man who comes to the office due to cough and chest pain. Vital signs Temperature: 38.7 C (101.7 F) Blood pressure: 130/80 mm Hg Pulse: 94/min Respirations: 24/min Basic differential diagnosis Pneumonia Pleuritic pain Pleural effusion Pulmonary edema Tuberculosis Pulmonary embolism Lung cancer Infective endocarditis GERD

(Essay)
4.8/5
(82)

Doorway information about patient The patient is a 53-year-old man who comes to the emergency department due to epigastric pain. Vital signs Temperature: 36.1 C (97 F) Blood pressure: 120/70 mm Hg Pulse: 84/min Respirations: 16/min Abdominal x-ray is as shown in the exhibit.<strong>Doorway information about patient</strong> The patient is a 53-year-old man who comes to the emergency department due to epigastric pain. <strong>Vital signs</strong> Temperature: 36.1 C (97 F) Blood pressure: 120/70 mm Hg Pulse: 84/min Respirations: 16/min Abdominal x-ray is as shown in the exhibit.  <strong>Basic differential diagnosis</strong>  Peptic ulcer  Gastritis  Esophagitis (GERD)  Carcinoma of esophagus, stomach, or pancreas  Acute or chronic pancreatitis  Cholecystitis  Hepatitis  Acute coronary event Basic differential diagnosis Peptic ulcer Gastritis Esophagitis (GERD) Carcinoma of esophagus, stomach, or pancreas Acute or chronic pancreatitis Cholecystitis Hepatitis Acute coronary event
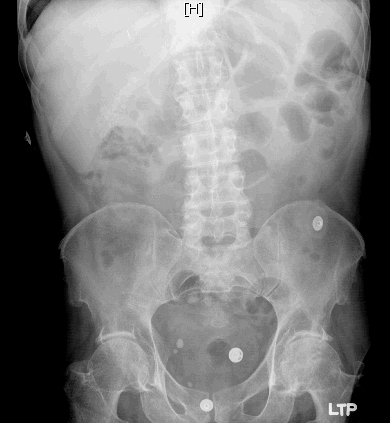
(Essay)
4.8/5
(84)

Doorway information about patient The patient is a 20-year-old woman who comes to the office due to burning during urination. Vital signs Temperature: 38.3 C (100.9 F) Blood pressure: 110/80 mm Hg Pulse: 82/min Respirations: 16/min Basic differential diagnosis Cystitis Pyelonephritis Urethritis Vulvovaginitis Pelvic inflammatory disease

(Essay)
4.9/5
(83)

Doorway information about patient The patient is a 60-year-old man who comes to the emergency department due to acute shortness of breath. Vital signs Temperature: 36.7 C (98 F) Blood pressure: 110/70 mm Hg Pulse: 90/min Respirations: 26/min Basic differential diagnosis Pulmonary embolism Congestive heart failure Chronic obstructive pulmonary disease exacerbation Pneumonia Spontaneous pneumothorax Asthma exacerbation Anxiety/panic attack

(Essay)
4.7/5
(79)

Doorway information about patient The patient is a 55-year-old man who comes to the emergency department due to chest pain. Vital signs Temperature: 37.1 C (98.7 F) Blood pressure: 130/80 mm Hg Pulse: 78/min Respirations: 20/min Clinical images ECG is shown in the image.<strong>Doorway information about patient</strong> The patient is a 55-year-old man who comes to the emergency department due to chest pain. <strong>Vital signs</strong> Temperature: 37.1 C (98.7 F) Blood pressure: 130/80 mm Hg Pulse: 78/min Respirations: 20/min <strong>Clinical images</strong> ECG is shown in the image.  <strong>Basic differential diagnosis</strong>  Myocardial infarction  Unstable angina  Pulmonary embolism  Costochondritis  Pleuritis  Pericarditis  Aortic dissection  Gastroesophageal reflux  Esophageal perforation Basic differential diagnosis Myocardial infarction Unstable angina Pulmonary embolism Costochondritis Pleuritis Pericarditis Aortic dissection Gastroesophageal reflux Esophageal perforation
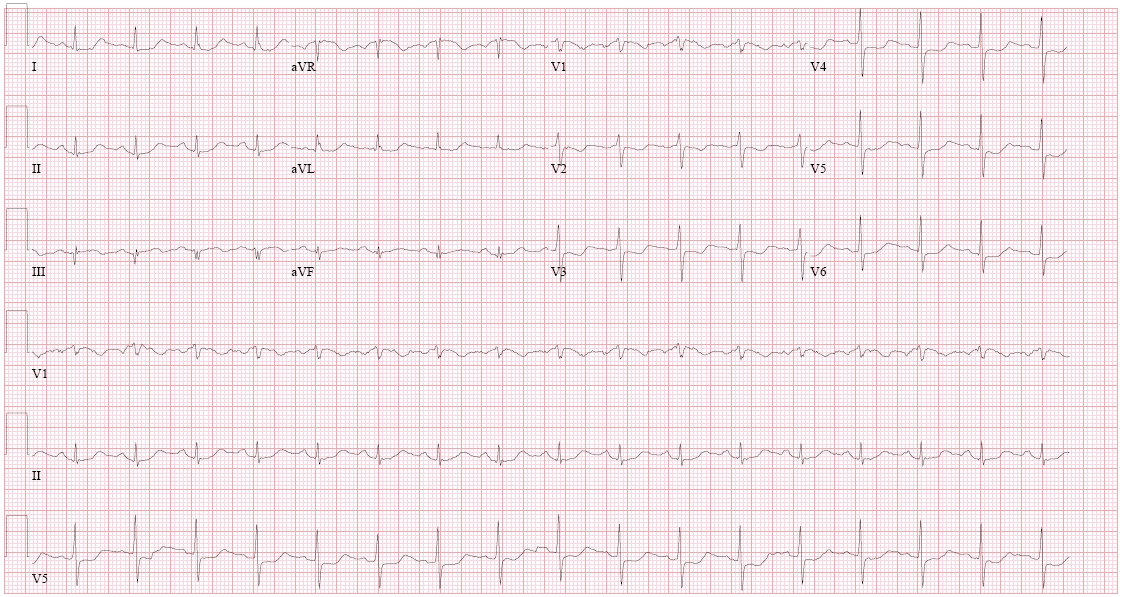
(Essay)
5.0/5
(88)

Doorway information about patient The patient is a 35-year-old woman who comes to the emergency department due to chest pain. Vital signs Temperature: 36.8 C (98.3 F) Blood pressure: 120/75 mm Hg Pulse: 98/min Respirations: 12/min Chest x-ray is as shown in the exhibit.<strong>Doorway information about patient</strong> The patient is a 35-year-old woman who comes to the emergency department due to chest pain. <strong>Vital signs</strong> Temperature: 36.8 C (98.3 F) Blood pressure: 120/75 mm Hg Pulse: 98/min Respirations: 12/min Chest x-ray is as shown in the exhibit.  <strong>Basic differential diagnosis</strong>  Pneumonia  Gastroesophageal reflux disease  Panic disorder/hyperventilation syndrome  Hyperthyroidism  Angina  Costochondritis Basic differential diagnosis Pneumonia Gastroesophageal reflux disease Panic disorder/hyperventilation syndrome Hyperthyroidism Angina Costochondritis
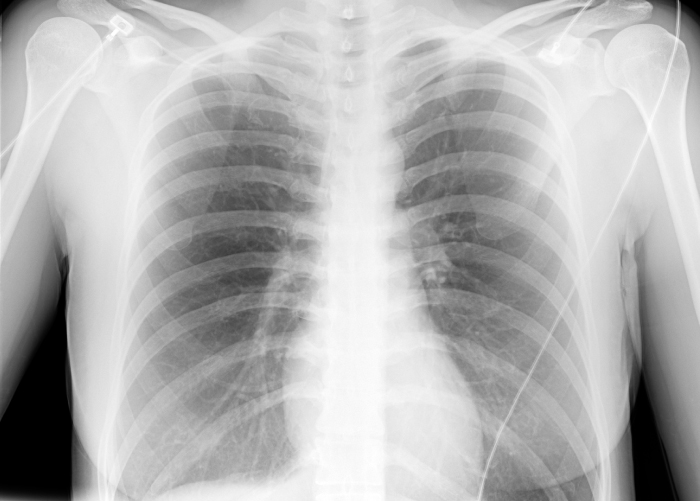
(Essay)
4.9/5
(85)

Doorway information about patient The patient is a 35-year-old woman who comes to the emergency department due to breathlessness and anxiety. Vital signs Temperature: 36.1 C (97 F) Blood pressure: 130/80 mm Hg Pulse: 94/min Respirations: 22/min Basic differential diagnosis Anxiety secondary to medical condition (eg, hyperthyroidism, arrhythmias) Substance abuse Panic disorder Generalized anxiety disorder Adjustment disorder with anxious mood Acute stress disorder or post-traumatic stress disorder Hypochondriasis

(Essay)
4.8/5
(87)

Doorway information about patient The patient is a 50-year-old man who comes to the office due to bilateral leg pain. Vital signs Temperature: 36.7 C (98 F) Blood pressure: 140/80 mm Hg Pulse: 78/min Respirations: 20/min Basic differential diagnosis Bilateral pain Atherosclerotic vascular disease Lumbar spinal stenosis Diabetic polyneuropathy Radiculopathy due to spinal disease Medications, such as statins Trauma Thromboangiitis obliterans Unilateral pain Cellulitis/myofasciitis Deep vein thrombosis Rupture of Baker cyst Osteomyelitis Radiculopathy/sciatica Pathological fracture of the bone

(Essay)
4.8/5
(80)

Doorway information about patient You will be speaking with the mother of a 1-year-old with fever. Basic differential diagnosis Respiratory tract infection Ear infection Exanthematous disease Meningitis Urinary tract infection Gastroenteritis

(Essay)
4.8/5
(76)

Doorway information about patient The patient is a 24-year-old woman who comes to the office for an initial prenatal visit. Vital signs Temperature: 37.1 C (98.8 F) Blood pressure: 120/75 mm Hg Pulse: 78/min Respirations: 20/min

(Essay)
4.9/5
(62)

Doorway information about patient The patient is a 65-year-old man who comes to the office due to difficulty with urination. Vital signs Temperature: 37.2 C (99 F) Blood pressure: 130/80 mm Hg Pulse: 92/min Respirations: 16/min Basic differential diagnosis Benign prostatic hyperplasia Prostatitis UTI/cystitis Carcinoma of the prostate Stone in the urinary tract (obstructive) Carcinoma of the bladder Neurological dysfunction Drug-induced bladder dysfunction

(Essay)
4.8/5
(80)

Doorway information about patient The patient is a 35-year-old woman who comes to the office due to jaundice. Vital signs Temperature: 38.5 C (101.3 F) Blood pressure: 120/75 mm Hg Pulse: 98/min Respirations: 22/min Basic differential diagnosis Infectious hepatitis Hemolytic jaundice Alcoholic hepatitis Drug-induced hepatitis Primary biliary cirrhosis Wilson disease Hemochromatosis Malignancy

(Essay)
4.9/5
(78)
Showing 1 - 20 of 43
close modal

Filters

  • Essay(0)
  • Multiple Choice(0)
  • Short Answer(0)
  • True False(0)
  • Matching(0)