
Exam 16: Manipulation of the Immune Response

arrow
  • Select Tags
search iconSearch Question
flashcardsStudy Flashcards
  • Select Tags

In the first few days following organ transplantation, patients are often treated with several doses of an antibody mixture known as anti-thymocyte globulin. The anti-thymocyte globulin is generated by immunizing rabbits or horses with human T cells, to generate antibodies against the human T cell surface molecules. Following the anti-thymocyte globulin treatment, patients are generally put on a sustained regimen of cyclosporin A or other small-molecule immunosuppressive drugs. The immediate post-operative treatment with anti-thymocyte globulin is likely used to:

(Multiple Choice)
5.0/5
(75)

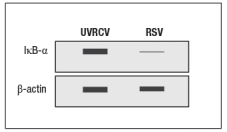
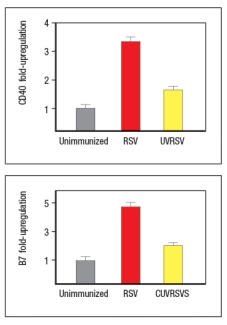
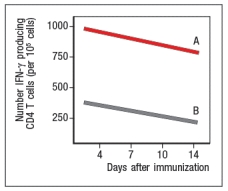
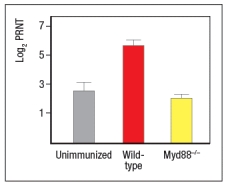
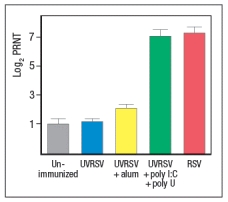
Early efforts to develop a vaccine against respiratory syncytial virus (RSV) using inactivated virus were unsuccessful. Antibody responses to the vaccine were poor, and were not protective against the natural infection. Studies in mice revealed a likely explanation for the poor performance of the inactivated RSV vaccine. For these studies, inactivated RSV was generated by UV-treatment of the virus, and was referred to as UVRSV. This UVRSV was compared to live RSV in a number of assays. First, mice were immunized by footpad (intradermal, also known as subcutaneous) injection of either UVRSV or live RSV, and dendritic cells from the draining lymph node were isolated 24 hours later. Cell lysates from these dendritic cells were prepared, and were immunoblotted for the levels of I κ\kappa B α\alpha protein, the inhibitory subunit of the cytosolic complex of NF κ\kappa B that is degraded following stimulation of receptors that activate NF κ\kappa B. A loading control of β\beta -actin is shown to indicate comparable amounts of total protein in each sample.   Early efforts to develop a vaccine against respiratory syncytial virus (RSV) using inactivated virus were unsuccessful. Antibody responses to the vaccine were poor, and were not protective against the natural infection. Studies in mice revealed a likely explanation for the poor performance of the inactivated RSV vaccine. For these studies, inactivated RSV was generated by UV-treatment of the virus, and was referred to as UVRSV. This UVRSV was compared to live RSV in a number of assays. First, mice were immunized by footpad (intradermal, also known as subcutaneous) injection of either UVRSV or live RSV, and dendritic cells from the draining lymph node were isolated 24 hours later. Cell lysates from these dendritic cells were prepared, and were immunoblotted for the levels of I \kappa B \alpha  protein, the inhibitory subunit of the cytosolic complex of NF \kappa B that is degraded following stimulation of receptors that activate NF \kappa B. A loading control of  \beta -actin is shown to indicate comparable amounts of total protein in each sample.    a) Given these data, name two classes of receptors in dendritic cells that might account for the difference seen in the immunoblot. To examine further the different effects of the UVRSV versus live RSV immunization on dendritic cells, the dendritic cells were isolated from draining lymph nodes 24 hours after immunization and stained for surface expression of CD40 and the co-stimulatory B7 receptors. These data are shown in Figure as fold-increase over the levels of expression of these molecules detected on dendritic cells from unimmunized mice.     Next, mice were immunized with live RSV or UVRSV, and CD4 T cells were isolated from draining lymph nodes on various days post-immunization.  The T cells were examined for IFN- \gamma  production in response to viral antigens mixed with antigen-presenting-cells by ELISPOT, and the numbers of responding cells at each time point were graphed, as shown in Figure.      b) Which data (A or B) represents the live RSV versus the UVRSV, and why? To determine which dendritic cell pathway might be important for the improved responses to live RSV compared to UVRSV, live RSV was used to immunize mice with reduced expression of the adapter protein, MyD88, and the responses of the Myd88+/- mice were compared to wild-type immunized mice. In these studies, anti-RSV antibodies in sera of immunized mice were tested for their ability to neutralize infectious virus in an in vitro assay, as shown in Figure. Log2PRNT indicates the amount the sera can be diluted before it loses the ability to neutralize 50% of the infectious virus in each sample, on a log2 scale (i.e., the higher the value the more potent the sera is for neutralizing virus).    c) Based on these data, what is the likely identity of the receptor family required for live RSV immunization to produce neutralizing antibodies to RSV?   To determine whether the pathway identified above was responsible for the more robust response to live RSV compared to UVRSV, mice were immunized with UVRSV alone, UVRSV in combination with alum, or UVRSV in combination with synthetic double-stranded RNA (poly I:C) plus synthetic single-stranded RNA (poly U). The sera from these mice were then tested for their ability to neutralize infectious RSV, in comparison to sera from unimmunized mice or mice immunized with live RSV, as shown in .    d) Do these data support or refute your answer to question (c) above? Do they implicate any specific receptors in the pathway required to generate a robust neutralizing antibody response to RSV? a) Given these data, name two classes of receptors in dendritic cells that might account for the difference seen in the immunoblot. To examine further the different effects of the UVRSV versus live RSV immunization on dendritic cells, the dendritic cells were isolated from draining lymph nodes 24 hours after immunization and stained for surface expression of CD40 and the co-stimulatory B7 receptors. These data are shown in Figure as fold-increase over the levels of expression of these molecules detected on dendritic cells from unimmunized mice.   Early efforts to develop a vaccine against respiratory syncytial virus (RSV) using inactivated virus were unsuccessful. Antibody responses to the vaccine were poor, and were not protective against the natural infection. Studies in mice revealed a likely explanation for the poor performance of the inactivated RSV vaccine. For these studies, inactivated RSV was generated by UV-treatment of the virus, and was referred to as UVRSV. This UVRSV was compared to live RSV in a number of assays. First, mice were immunized by footpad (intradermal, also known as subcutaneous) injection of either UVRSV or live RSV, and dendritic cells from the draining lymph node were isolated 24 hours later. Cell lysates from these dendritic cells were prepared, and were immunoblotted for the levels of I \kappa B \alpha  protein, the inhibitory subunit of the cytosolic complex of NF \kappa B that is degraded following stimulation of receptors that activate NF \kappa B. A loading control of  \beta -actin is shown to indicate comparable amounts of total protein in each sample.    a) Given these data, name two classes of receptors in dendritic cells that might account for the difference seen in the immunoblot. To examine further the different effects of the UVRSV versus live RSV immunization on dendritic cells, the dendritic cells were isolated from draining lymph nodes 24 hours after immunization and stained for surface expression of CD40 and the co-stimulatory B7 receptors. These data are shown in Figure as fold-increase over the levels of expression of these molecules detected on dendritic cells from unimmunized mice.     Next, mice were immunized with live RSV or UVRSV, and CD4 T cells were isolated from draining lymph nodes on various days post-immunization.  The T cells were examined for IFN- \gamma  production in response to viral antigens mixed with antigen-presenting-cells by ELISPOT, and the numbers of responding cells at each time point were graphed, as shown in Figure.      b) Which data (A or B) represents the live RSV versus the UVRSV, and why? To determine which dendritic cell pathway might be important for the improved responses to live RSV compared to UVRSV, live RSV was used to immunize mice with reduced expression of the adapter protein, MyD88, and the responses of the Myd88+/- mice were compared to wild-type immunized mice. In these studies, anti-RSV antibodies in sera of immunized mice were tested for their ability to neutralize infectious virus in an in vitro assay, as shown in Figure. Log2PRNT indicates the amount the sera can be diluted before it loses the ability to neutralize 50% of the infectious virus in each sample, on a log2 scale (i.e., the higher the value the more potent the sera is for neutralizing virus).    c) Based on these data, what is the likely identity of the receptor family required for live RSV immunization to produce neutralizing antibodies to RSV?   To determine whether the pathway identified above was responsible for the more robust response to live RSV compared to UVRSV, mice were immunized with UVRSV alone, UVRSV in combination with alum, or UVRSV in combination with synthetic double-stranded RNA (poly I:C) plus synthetic single-stranded RNA (poly U). The sera from these mice were then tested for their ability to neutralize infectious RSV, in comparison to sera from unimmunized mice or mice immunized with live RSV, as shown in .    d) Do these data support or refute your answer to question (c) above? Do they implicate any specific receptors in the pathway required to generate a robust neutralizing antibody response to RSV? Next, mice were immunized with live RSV or UVRSV, and CD4 T cells were isolated from draining lymph nodes on various days post-immunization. The T cells were examined for IFN- γ\gamma production in response to viral antigens mixed with antigen-presenting-cells by ELISPOT, and the numbers of responding cells at each time point were graphed, as shown in Figure.   Early efforts to develop a vaccine against respiratory syncytial virus (RSV) using inactivated virus were unsuccessful. Antibody responses to the vaccine were poor, and were not protective against the natural infection. Studies in mice revealed a likely explanation for the poor performance of the inactivated RSV vaccine. For these studies, inactivated RSV was generated by UV-treatment of the virus, and was referred to as UVRSV. This UVRSV was compared to live RSV in a number of assays. First, mice were immunized by footpad (intradermal, also known as subcutaneous) injection of either UVRSV or live RSV, and dendritic cells from the draining lymph node were isolated 24 hours later. Cell lysates from these dendritic cells were prepared, and were immunoblotted for the levels of I \kappa B \alpha  protein, the inhibitory subunit of the cytosolic complex of NF \kappa B that is degraded following stimulation of receptors that activate NF \kappa B. A loading control of  \beta -actin is shown to indicate comparable amounts of total protein in each sample.    a) Given these data, name two classes of receptors in dendritic cells that might account for the difference seen in the immunoblot. To examine further the different effects of the UVRSV versus live RSV immunization on dendritic cells, the dendritic cells were isolated from draining lymph nodes 24 hours after immunization and stained for surface expression of CD40 and the co-stimulatory B7 receptors. These data are shown in Figure as fold-increase over the levels of expression of these molecules detected on dendritic cells from unimmunized mice.     Next, mice were immunized with live RSV or UVRSV, and CD4 T cells were isolated from draining lymph nodes on various days post-immunization.  The T cells were examined for IFN- \gamma  production in response to viral antigens mixed with antigen-presenting-cells by ELISPOT, and the numbers of responding cells at each time point were graphed, as shown in Figure.      b) Which data (A or B) represents the live RSV versus the UVRSV, and why? To determine which dendritic cell pathway might be important for the improved responses to live RSV compared to UVRSV, live RSV was used to immunize mice with reduced expression of the adapter protein, MyD88, and the responses of the Myd88+/- mice were compared to wild-type immunized mice. In these studies, anti-RSV antibodies in sera of immunized mice were tested for their ability to neutralize infectious virus in an in vitro assay, as shown in Figure. Log2PRNT indicates the amount the sera can be diluted before it loses the ability to neutralize 50% of the infectious virus in each sample, on a log2 scale (i.e., the higher the value the more potent the sera is for neutralizing virus).    c) Based on these data, what is the likely identity of the receptor family required for live RSV immunization to produce neutralizing antibodies to RSV?   To determine whether the pathway identified above was responsible for the more robust response to live RSV compared to UVRSV, mice were immunized with UVRSV alone, UVRSV in combination with alum, or UVRSV in combination with synthetic double-stranded RNA (poly I:C) plus synthetic single-stranded RNA (poly U). The sera from these mice were then tested for their ability to neutralize infectious RSV, in comparison to sera from unimmunized mice or mice immunized with live RSV, as shown in .    d) Do these data support or refute your answer to question (c) above? Do they implicate any specific receptors in the pathway required to generate a robust neutralizing antibody response to RSV? b) Which data (A or B) represents the live RSV versus the UVRSV, and why? To determine which dendritic cell pathway might be important for the improved responses to live RSV compared to UVRSV, live RSV was used to immunize mice with reduced expression of the adapter protein, MyD88, and the responses of the Myd88+/- mice were compared to wild-type immunized mice. In these studies, anti-RSV antibodies in sera of immunized mice were tested for their ability to neutralize infectious virus in an in vitro assay, as shown in Figure. Log2PRNT indicates the amount the sera can be diluted before it loses the ability to neutralize 50% of the infectious virus in each sample, on a log2 scale (i.e., the higher the value the more potent the sera is for neutralizing virus).   Early efforts to develop a vaccine against respiratory syncytial virus (RSV) using inactivated virus were unsuccessful. Antibody responses to the vaccine were poor, and were not protective against the natural infection. Studies in mice revealed a likely explanation for the poor performance of the inactivated RSV vaccine. For these studies, inactivated RSV was generated by UV-treatment of the virus, and was referred to as UVRSV. This UVRSV was compared to live RSV in a number of assays. First, mice were immunized by footpad (intradermal, also known as subcutaneous) injection of either UVRSV or live RSV, and dendritic cells from the draining lymph node were isolated 24 hours later. Cell lysates from these dendritic cells were prepared, and were immunoblotted for the levels of I \kappa B \alpha  protein, the inhibitory subunit of the cytosolic complex of NF \kappa B that is degraded following stimulation of receptors that activate NF \kappa B. A loading control of  \beta -actin is shown to indicate comparable amounts of total protein in each sample.    a) Given these data, name two classes of receptors in dendritic cells that might account for the difference seen in the immunoblot. To examine further the different effects of the UVRSV versus live RSV immunization on dendritic cells, the dendritic cells were isolated from draining lymph nodes 24 hours after immunization and stained for surface expression of CD40 and the co-stimulatory B7 receptors. These data are shown in Figure as fold-increase over the levels of expression of these molecules detected on dendritic cells from unimmunized mice.     Next, mice were immunized with live RSV or UVRSV, and CD4 T cells were isolated from draining lymph nodes on various days post-immunization.  The T cells were examined for IFN- \gamma  production in response to viral antigens mixed with antigen-presenting-cells by ELISPOT, and the numbers of responding cells at each time point were graphed, as shown in Figure.      b) Which data (A or B) represents the live RSV versus the UVRSV, and why? To determine which dendritic cell pathway might be important for the improved responses to live RSV compared to UVRSV, live RSV was used to immunize mice with reduced expression of the adapter protein, MyD88, and the responses of the Myd88+/- mice were compared to wild-type immunized mice. In these studies, anti-RSV antibodies in sera of immunized mice were tested for their ability to neutralize infectious virus in an in vitro assay, as shown in Figure. Log2PRNT indicates the amount the sera can be diluted before it loses the ability to neutralize 50% of the infectious virus in each sample, on a log2 scale (i.e., the higher the value the more potent the sera is for neutralizing virus).    c) Based on these data, what is the likely identity of the receptor family required for live RSV immunization to produce neutralizing antibodies to RSV?   To determine whether the pathway identified above was responsible for the more robust response to live RSV compared to UVRSV, mice were immunized with UVRSV alone, UVRSV in combination with alum, or UVRSV in combination with synthetic double-stranded RNA (poly I:C) plus synthetic single-stranded RNA (poly U). The sera from these mice were then tested for their ability to neutralize infectious RSV, in comparison to sera from unimmunized mice or mice immunized with live RSV, as shown in .    d) Do these data support or refute your answer to question (c) above? Do they implicate any specific receptors in the pathway required to generate a robust neutralizing antibody response to RSV? c) Based on these data, what is the likely identity of the receptor family required for live RSV immunization to produce neutralizing antibodies to RSV? To determine whether the pathway identified above was responsible for the more robust response to live RSV compared to UVRSV, mice were immunized with UVRSV alone, UVRSV in combination with alum, or UVRSV in combination with synthetic double-stranded RNA (poly I:C) plus synthetic single-stranded RNA (poly U). The sera from these mice were then tested for their ability to neutralize infectious RSV, in comparison to sera from unimmunized mice or mice immunized with live RSV, as shown in .   Early efforts to develop a vaccine against respiratory syncytial virus (RSV) using inactivated virus were unsuccessful. Antibody responses to the vaccine were poor, and were not protective against the natural infection. Studies in mice revealed a likely explanation for the poor performance of the inactivated RSV vaccine. For these studies, inactivated RSV was generated by UV-treatment of the virus, and was referred to as UVRSV. This UVRSV was compared to live RSV in a number of assays. First, mice were immunized by footpad (intradermal, also known as subcutaneous) injection of either UVRSV or live RSV, and dendritic cells from the draining lymph node were isolated 24 hours later. Cell lysates from these dendritic cells were prepared, and were immunoblotted for the levels of I \kappa B \alpha  protein, the inhibitory subunit of the cytosolic complex of NF \kappa B that is degraded following stimulation of receptors that activate NF \kappa B. A loading control of  \beta -actin is shown to indicate comparable amounts of total protein in each sample.    a) Given these data, name two classes of receptors in dendritic cells that might account for the difference seen in the immunoblot. To examine further the different effects of the UVRSV versus live RSV immunization on dendritic cells, the dendritic cells were isolated from draining lymph nodes 24 hours after immunization and stained for surface expression of CD40 and the co-stimulatory B7 receptors. These data are shown in Figure as fold-increase over the levels of expression of these molecules detected on dendritic cells from unimmunized mice.     Next, mice were immunized with live RSV or UVRSV, and CD4 T cells were isolated from draining lymph nodes on various days post-immunization.  The T cells were examined for IFN- \gamma  production in response to viral antigens mixed with antigen-presenting-cells by ELISPOT, and the numbers of responding cells at each time point were graphed, as shown in Figure.      b) Which data (A or B) represents the live RSV versus the UVRSV, and why? To determine which dendritic cell pathway might be important for the improved responses to live RSV compared to UVRSV, live RSV was used to immunize mice with reduced expression of the adapter protein, MyD88, and the responses of the Myd88+/- mice were compared to wild-type immunized mice. In these studies, anti-RSV antibodies in sera of immunized mice were tested for their ability to neutralize infectious virus in an in vitro assay, as shown in Figure. Log2PRNT indicates the amount the sera can be diluted before it loses the ability to neutralize 50% of the infectious virus in each sample, on a log2 scale (i.e., the higher the value the more potent the sera is for neutralizing virus).    c) Based on these data, what is the likely identity of the receptor family required for live RSV immunization to produce neutralizing antibodies to RSV?   To determine whether the pathway identified above was responsible for the more robust response to live RSV compared to UVRSV, mice were immunized with UVRSV alone, UVRSV in combination with alum, or UVRSV in combination with synthetic double-stranded RNA (poly I:C) plus synthetic single-stranded RNA (poly U). The sera from these mice were then tested for their ability to neutralize infectious RSV, in comparison to sera from unimmunized mice or mice immunized with live RSV, as shown in .    d) Do these data support or refute your answer to question (c) above? Do they implicate any specific receptors in the pathway required to generate a robust neutralizing antibody response to RSV? d) Do these data support or refute your answer to question (c) above? Do they implicate any specific receptors in the pathway required to generate a robust neutralizing antibody response to RSV?
(Essay)
4.9/5
(91)

Conjugate vaccines, such as those developed against H. influenzae type B and N. meningitidis type C, provide protection in small children and infants that are unable to make antibody responses to isolated polysaccharide antigens. However, one group of individuals that would generate antibody responses to the purified polysaccharide vaccine that are as effective as the antibodies they would make in response to the conjugate vaccine is:

(Multiple Choice)
4.8/5
(65)

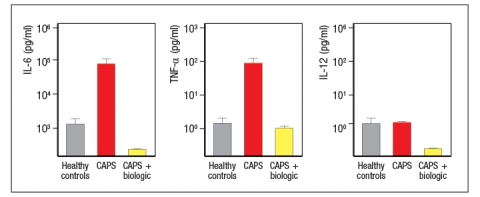
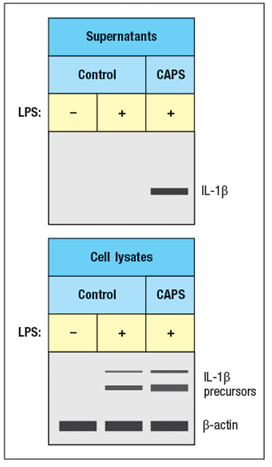
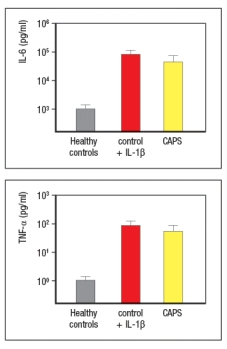
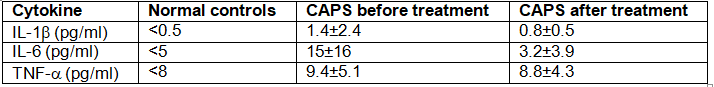
Autoimmune diseases are characterized by an adaptive immune response directed at self-tissue or self-antigens. One hallmark of these diseases is their responsiveness to treatments that inhibit B or T lymphocytes. A set of diseases known as autoinflammatory diseases are, instead, caused by aberrant activation of innate immune responses. Some of these are monogenic inherited disorders, for example, a spectrum of diseases resulting from mutations in the innate sensor protein, NLRP3. These diseases are inherited as autosomal dominant diseases, and are due to gain-of-function mutations in NLRP3, a key component of the inflammasome. Altogether, these disorders are known as CAPS, for cryopyrin-associated periodic syndrome, as they generally cause periodic episodes of fever and inflammation. Common symptoms of these disorders include severe skin rashes, fevers, joint disease, and central nervous system disease. A biologic has been developed to treat patients with CAPS, with remarkable success. Initial studies first examined the responses of peripheral blood cells from CAPS patients to this biologic, compared to controls. For these experiments, peripheral blood mononuclear cells (all white blood cells) were cultured for 48 hours, without stimulation, and the cytokine levels in the supernatants were then measured by ELISA. These data are shown in Figure.  Autoimmune diseases are characterized by an adaptive immune response directed at self-tissue or self-antigens. One hallmark of these diseases is their responsiveness to treatments that inhibit B or T lymphocytes. A set of diseases known as autoinflammatory diseases are, instead, caused by aberrant activation of innate immune responses. Some of these are monogenic inherited disorders, for example, a spectrum of diseases resulting from mutations in the innate sensor protein, NLRP3. These diseases are inherited as autosomal dominant diseases, and are due to gain-of-function mutations in NLRP3, a key component of the inflammasome. Altogether, these disorders are known as CAPS, for cryopyrin-associated periodic syndrome, as they generally cause periodic episodes of fever and inflammation. Common symptoms of these disorders include severe skin rashes, fevers, joint disease, and central nervous system disease. A biologic has been developed to treat patients with CAPS, with remarkable success. Initial studies first examined the responses of peripheral blood cells from CAPS patients to this biologic, compared to controls. For these experiments, peripheral blood mononuclear cells (all white blood cells) were cultured for 48 hours, without stimulation, and the cytokine levels in the supernatants were then measured by ELISA. These data are shown in Figure.    a) Based on these data, which cells in the peripheral blood of CAPS patients are spontaneously producing cytokines? b) Based on the fact that CAPS patients have a mutation in a single gene, NLRP3, propose an explanation for the cytokine data shown above Next, peripheral blood mononuclear cells from controls or CAPS patients were stimulated in vitro with LPS alone, and protein was isolated from cell lysates and cell supernatants, and immunoblotted as shown in Figure    c) What do these results indicate about the consequences of the gain-of-function NLRP3 mutations in patients with CAPS?on normal healthy peripheral blood mononuclear cells, cells from healthy controls were cultured in vitro for 48 hours in the presence or absence of IL-1 \beta . Cytokines in the supernatants were then analyzed, in comparison to supernatants from cultured CAPS patients' cells. For these studies, the CAPS patients' cells were cultured without stimulation and in the absence of any biologic treatment. These data are shown in Figure.   In addition, serum cytokine levels from CAPS patients were measured before and after treatment with the biologic, and the results are shown in Table .   d) What  do these data suggest a possible explanation for the inflammatory syndrome seen in CAPS patients? e) Based on all of these data, what is the likely target of the biologic used to treat the CAPS patients? a) Based on these data, which cells in the peripheral blood of CAPS patients are spontaneously producing cytokines? b) Based on the fact that CAPS patients have a mutation in a single gene, NLRP3, propose an explanation for the cytokine data shown above Next, peripheral blood mononuclear cells from controls or CAPS patients were stimulated in vitro with LPS alone, and protein was isolated from cell lysates and cell supernatants, and immunoblotted as shown in Figure  Autoimmune diseases are characterized by an adaptive immune response directed at self-tissue or self-antigens. One hallmark of these diseases is their responsiveness to treatments that inhibit B or T lymphocytes. A set of diseases known as autoinflammatory diseases are, instead, caused by aberrant activation of innate immune responses. Some of these are monogenic inherited disorders, for example, a spectrum of diseases resulting from mutations in the innate sensor protein, NLRP3. These diseases are inherited as autosomal dominant diseases, and are due to gain-of-function mutations in NLRP3, a key component of the inflammasome. Altogether, these disorders are known as CAPS, for cryopyrin-associated periodic syndrome, as they generally cause periodic episodes of fever and inflammation. Common symptoms of these disorders include severe skin rashes, fevers, joint disease, and central nervous system disease. A biologic has been developed to treat patients with CAPS, with remarkable success. Initial studies first examined the responses of peripheral blood cells from CAPS patients to this biologic, compared to controls. For these experiments, peripheral blood mononuclear cells (all white blood cells) were cultured for 48 hours, without stimulation, and the cytokine levels in the supernatants were then measured by ELISA. These data are shown in Figure.    a) Based on these data, which cells in the peripheral blood of CAPS patients are spontaneously producing cytokines? b) Based on the fact that CAPS patients have a mutation in a single gene, NLRP3, propose an explanation for the cytokine data shown above Next, peripheral blood mononuclear cells from controls or CAPS patients were stimulated in vitro with LPS alone, and protein was isolated from cell lysates and cell supernatants, and immunoblotted as shown in Figure    c) What do these results indicate about the consequences of the gain-of-function NLRP3 mutations in patients with CAPS?on normal healthy peripheral blood mononuclear cells, cells from healthy controls were cultured in vitro for 48 hours in the presence or absence of IL-1 \beta . Cytokines in the supernatants were then analyzed, in comparison to supernatants from cultured CAPS patients' cells. For these studies, the CAPS patients' cells were cultured without stimulation and in the absence of any biologic treatment. These data are shown in Figure.   In addition, serum cytokine levels from CAPS patients were measured before and after treatment with the biologic, and the results are shown in Table .   d) What  do these data suggest a possible explanation for the inflammatory syndrome seen in CAPS patients? e) Based on all of these data, what is the likely target of the biologic used to treat the CAPS patients? c) What do these results indicate about the consequences of the gain-of-function NLRP3 mutations in patients with CAPS?on normal healthy peripheral blood mononuclear cells, cells from healthy controls were cultured in vitro for 48 hours in the presence or absence of IL-1 β\beta . Cytokines in the supernatants were then analyzed, in comparison to supernatants from cultured CAPS patients' cells. For these studies, the CAPS patients' cells were cultured without stimulation and in the absence of any biologic treatment. These data are shown in Figure.  Autoimmune diseases are characterized by an adaptive immune response directed at self-tissue or self-antigens. One hallmark of these diseases is their responsiveness to treatments that inhibit B or T lymphocytes. A set of diseases known as autoinflammatory diseases are, instead, caused by aberrant activation of innate immune responses. Some of these are monogenic inherited disorders, for example, a spectrum of diseases resulting from mutations in the innate sensor protein, NLRP3. These diseases are inherited as autosomal dominant diseases, and are due to gain-of-function mutations in NLRP3, a key component of the inflammasome. Altogether, these disorders are known as CAPS, for cryopyrin-associated periodic syndrome, as they generally cause periodic episodes of fever and inflammation. Common symptoms of these disorders include severe skin rashes, fevers, joint disease, and central nervous system disease. A biologic has been developed to treat patients with CAPS, with remarkable success. Initial studies first examined the responses of peripheral blood cells from CAPS patients to this biologic, compared to controls. For these experiments, peripheral blood mononuclear cells (all white blood cells) were cultured for 48 hours, without stimulation, and the cytokine levels in the supernatants were then measured by ELISA. These data are shown in Figure.    a) Based on these data, which cells in the peripheral blood of CAPS patients are spontaneously producing cytokines? b) Based on the fact that CAPS patients have a mutation in a single gene, NLRP3, propose an explanation for the cytokine data shown above Next, peripheral blood mononuclear cells from controls or CAPS patients were stimulated in vitro with LPS alone, and protein was isolated from cell lysates and cell supernatants, and immunoblotted as shown in Figure    c) What do these results indicate about the consequences of the gain-of-function NLRP3 mutations in patients with CAPS?on normal healthy peripheral blood mononuclear cells, cells from healthy controls were cultured in vitro for 48 hours in the presence or absence of IL-1 \beta . Cytokines in the supernatants were then analyzed, in comparison to supernatants from cultured CAPS patients' cells. For these studies, the CAPS patients' cells were cultured without stimulation and in the absence of any biologic treatment. These data are shown in Figure.   In addition, serum cytokine levels from CAPS patients were measured before and after treatment with the biologic, and the results are shown in Table .   d) What  do these data suggest a possible explanation for the inflammatory syndrome seen in CAPS patients? e) Based on all of these data, what is the likely target of the biologic used to treat the CAPS patients? In addition, serum cytokine levels from CAPS patients were measured before and after treatment with the biologic, and the results are shown in Table .  Autoimmune diseases are characterized by an adaptive immune response directed at self-tissue or self-antigens. One hallmark of these diseases is their responsiveness to treatments that inhibit B or T lymphocytes. A set of diseases known as autoinflammatory diseases are, instead, caused by aberrant activation of innate immune responses. Some of these are monogenic inherited disorders, for example, a spectrum of diseases resulting from mutations in the innate sensor protein, NLRP3. These diseases are inherited as autosomal dominant diseases, and are due to gain-of-function mutations in NLRP3, a key component of the inflammasome. Altogether, these disorders are known as CAPS, for cryopyrin-associated periodic syndrome, as they generally cause periodic episodes of fever and inflammation. Common symptoms of these disorders include severe skin rashes, fevers, joint disease, and central nervous system disease. A biologic has been developed to treat patients with CAPS, with remarkable success. Initial studies first examined the responses of peripheral blood cells from CAPS patients to this biologic, compared to controls. For these experiments, peripheral blood mononuclear cells (all white blood cells) were cultured for 48 hours, without stimulation, and the cytokine levels in the supernatants were then measured by ELISA. These data are shown in Figure.    a) Based on these data, which cells in the peripheral blood of CAPS patients are spontaneously producing cytokines? b) Based on the fact that CAPS patients have a mutation in a single gene, NLRP3, propose an explanation for the cytokine data shown above Next, peripheral blood mononuclear cells from controls or CAPS patients were stimulated in vitro with LPS alone, and protein was isolated from cell lysates and cell supernatants, and immunoblotted as shown in Figure    c) What do these results indicate about the consequences of the gain-of-function NLRP3 mutations in patients with CAPS?on normal healthy peripheral blood mononuclear cells, cells from healthy controls were cultured in vitro for 48 hours in the presence or absence of IL-1 \beta . Cytokines in the supernatants were then analyzed, in comparison to supernatants from cultured CAPS patients' cells. For these studies, the CAPS patients' cells were cultured without stimulation and in the absence of any biologic treatment. These data are shown in Figure.   In addition, serum cytokine levels from CAPS patients were measured before and after treatment with the biologic, and the results are shown in Table .   d) What  do these data suggest a possible explanation for the inflammatory syndrome seen in CAPS patients? e) Based on all of these data, what is the likely target of the biologic used to treat the CAPS patients? d) What do these data suggest a possible explanation for the inflammatory syndrome seen in CAPS patients? e) Based on all of these data, what is the likely target of the biologic used to treat the CAPS patients?
(Essay)
4.9/5
(79)

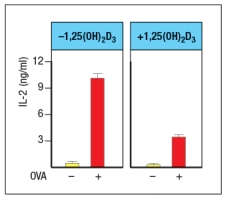
The vitamin D3 metabolite 1,25(OH)2D3 binds to the vitamin D receptor (VDR). This complex then functions as a transcriptional regulator. The activation of VDR following treatment of cells with 1,25(OH)2D3 has been found to modulate the activity of antigen-presenting dendritic cells. In one study, dendritic cells were isolated from wild-type mice and activated in vitro by stimulation with LPS plus IFN- γ\gamma in the presence or absence of 1,25(OH)2D3 for 24 hours. These activated dendritic cells were then pulsed with a peptide from the chicken ovalbumin protein (OVA) that binds to MHC class II and is recognized by OT-II CD4 T cells. The peptide-pulsed dendritic cells and T cells were incubated together for 3 days, and then IL-2 levels in the supernatants were measured, as shown in Figure .  The vitamin D3 metabolite 1,25(OH)<sub>2</sub>D<sub>3</sub> binds to the vitamin D receptor (VDR). This complex then functions as a transcriptional regulator. The activation of VDR following treatment of cells with 1,25(OH)<sub>2</sub>D<sub>3</sub> has been found to modulate the activity of antigen-presenting dendritic cells. In one study, dendritic cells were isolated from wild-type mice and activated in vitro by stimulation with LPS plus IFN- \gamma  in the presence or absence of 1,25(OH)<sub>2</sub>D<sub>3</sub> for 24 hours. These activated dendritic cells were then pulsed with a peptide from the chicken ovalbumin protein (OVA) that binds to MHC class II and is recognized by OT-II CD4 T cells. The peptide-pulsed dendritic cells and T cells were incubated together for 3 days, and then IL-2 levels in the supernatants were measured, as shown in Figure .     Based on these data, dendritic cells activated in the presence of 1,25(OH)<sub>2</sub>D<sub>3</sub> are likely to show: Based on these data, dendritic cells activated in the presence of 1,25(OH)2D3 are likely to show:
(Multiple Choice)
4.8/5
(89)

Safety concerns in the latter part of the twentieth century prompted the development of an acellular formulation of a vaccine directed against Bordetella pertussis, the causative agent of whooping cough. This acellular vaccine, made from a mixture of four

(Multiple Choice)
4.9/5
(91)

As of 2014, a total of 452 clinical studies of peptide-based vaccines were registered with the US federal government clinical trials database. Of these, none have progressed to market, and only a small number (12) made it to phase III clinical trials; furthermore, of these phase III trials, none were for vaccines directed against infectious diseases. The lack of success of peptide vaccines against pathogenic infections is due to the fact that antibodies against a single epitope on a pathogen are rarely protective.

(True/False)
4.7/5
(88)

A recent strategy showing some promise for the treatment of IgE-mediated allergies is a form of allergen immunotherapy, in which allergic individuals are given 3-4 intradermal injections of soluble peptides. For example, in one study, allergic individuals were injected with a set of 13-17 amino acid long peptides derived from the house dust mite protein antigen; these peptides were selected based on predictions for sequences likely to be MHC class II binding epitopes. Following the treatment, individuals were found to have increased numbers of antigen-specific IL-10-producing CD4 T cells, a finding that correlated with reduced allergic responses to allergen challenge. One of the goals of this therapy might also be to:

(Multiple Choice)
4.8/5
(73)

The US Department of Health and Human Services has a stated goal for the seasonal influenza vaccine of vaccinating 80% of healthy (i.e., low-risk) individuals. This vaccine is formulated each year from the serotypes of influenza likely to be circulating in the population during the coming flu season. The reason this goal is not 100% of individuals is because:

(Multiple Choice)
4.8/5
(86)

One successful cancer vaccine targets human papilloma virus serotypes (HPV-16, -18) associated with the majority of cases of cervical cancer. Follow-up studies performed on large cohorts of women who received this vaccine showed long-lasting (~10 years) serum antibody responses to the vaccine. How does this vaccine prevent cancer?

(Essay)
4.9/5
(95)

Immunotoxin therapy as an anticancer treatment is a focus of current efforts to develop new anticancer drugs. An alternative strategy, known as radioimmunotherapy, involves the conjugation of a tumor-antigen specific antibody to a radioisotope, rather than to a bacterial toxin. One advantage of radioimmunotherapy over that of immunotoxin therapy is that the radioisotope:

(Multiple Choice)
4.8/5
(72)

Natalizumab is a humanized monoclonal antibody directed at the α\alpha 4-integrin protein, a subunit of VLA-4, the binding partner of VCAM-1 expressed on endothelium in the central nervous system, and of α\alpha 4 β\beta -integrin, the binding partner of MadCAM-1 expressed on endothelium in the gut. While natalizumab has had great success in alleviating the symptoms of autoimmune diseases such as multiple sclerosis and Crohn's disease, a small number of patients have acquired life threatening infections of the neurotrophic virus, JC. Why are patients on natalizumab particularly susceptible to a virus infection of the central nervous system?

(Essay)
4.8/5
(74)

Immunotherapies aimed at promoting anti-tumor immune responses are being developed for tumors of many different tissue or cell-type origins. Interestingly, some of these approaches, when tested in clinical trials, were found to also cause patients to develop autoimmune symptoms related to their tumor type. For instance, in patients with malignant skin cancer (melanoma), immunotherapy treatment can develop an autoimmune disorder known as vitiligo, in which T cells attack and destroy melanocytes in the skin, causing depigmentation. These findings indicate that, in some individuals the melanoma-specific anti-tumor T cell responses are directed at:

(Multiple Choice)
4.8/5
(75)

Alefacept is a fusion protein that contains the CD2-binding domain of LFA3 fused to human IgG1, and it is used to block CD2 function on human T cells. In addition, following in vivo administration, alefacept was also shown to deplete T cells of the effector or memory subsets that express high levels of CD2. Surprisingly, clinical trials data indicated that patients on alefacept still retained responses to vaccination. For example, one set of data showed that patients on alefacept made similar responses as the control group to a vaccine designed to protect against pneumococcal disease, which is composed entirely of bacterial polysaccharide antigens (pneumococcal polysaccharide vaccine; PPV). This normal response to PPV by patients on alefacept is not surprising because:

(Multiple Choice)
4.8/5
(89)
Showing 21 - 34 of 34
close modal

Filters

  • Essay(0)
  • Multiple Choice(0)
  • Short Answer(0)
  • True False(0)
  • Matching(0)